Course Articles
An RT Overview of the Revised PARDS Guidelines from PALICC II
Evan Richards, Advanced Practice Clinical Consultant, BSc, RT
The following is a transcript of the live webinar An RT Overview of the Revised Pediatric Acute Respiratory Distress Syndrome (PARDS) Guidelines from PALICC II, presented by Evan Richards, BSc, RT.
It is recommended that you download the course handout to supplement this text format.
Learning Outcomes
After this course, participants will be able to:
- Identify the key revisions in the Pediatric Acute Respiratory Distress Syndrome (PARDS) guidelines from PALICC II and understand their implications for clinical practice.
- Explain how to apply the revised PARDS guidelines in real-world scenarios, enhancing clinical decision-making and patient management skills in pediatric respiratory care.
- Discuss strategies to implement the updated guidelines effectively, aiming to improve patient outcomes through evidence-based respiratory therapy practices.
Introduction
I appreciate the opportunity to present this material, and I want to acknowledge that people take time out of their day to learn. That means a great deal to me. Everything I am about to share with you is based on clinical recommendations from evidence-based medicine, largely from randomized controlled trials or smaller individual trials. All content is evidence-based, and you will see why that matters when it comes to establishing guidelines.
Before going any further, let me simplify the terminology. Pediatric Acute Respiratory Distress Syndrome will be referred to throughout as PARDS, and the Pediatric Acute Lung Injury Consensus Conference will be called PALICC. The first consensus conference, PALICC 1, took place in 2015. The second, PALICC 2, was completed in 2023, and the revised guidelines it produced are the focus of this course.
I would like to acknowledge four colleagues whose contributions were essential to this presentation: Alex Rotta, MD, from Duke University; Robi Khemani, MD, the senior author of the PALICC 2 guidelines, from Children's Hospital Los Angeles; Ira Cheifetz, MD, from Rainbow Babies in Cleveland; and Martin Kneyber, MD, from Beatrix Children's Hospital in the Netherlands. I could not have assembled this content without them.
Why Children Are Not Small Adults
For many years, clinicians managed pediatric patients with ARDS by applying adult definitions and protocols to children. This approach is fundamentally flawed. Children are not small adults, and the physiological differences between children and adults have profound implications for how ARDS must be defined and managed.
Key physiological distinctions include the following.
- Airway cartilage formation is incomplete in children, whereas it is fully established in adults.
- Children have greater airway resistance due to smaller airways, making them more resistant to gas flow in both directions.
- Children have greater chest wall compliance because ossification of the rib cage is not yet complete, whereas the adult rib cage is solidified.
- Respiratory muscle reserve differs: children rely more heavily on the diaphragm than adults do.
- Pulmonary vascular resistance is a significantly greater problem in children, whose lungs are still growing and whose alveolar capillary proliferation is incomplete.
- Alveolar maturation differs dramatically: a child may have 20 to 50 million alveoli, resulting in a lower functional residual capacity, compared to approximately 500 million alveoli in a healthy adult.
These differences make it essential that pediatric ARDS be defined and managed on its own terms, not as a scaled-down version of adult ARDS.
What Is PARDS and Why Does It Matter?
Prior to 2015, there had never been a pediatric-specific definition of ARDS. Existing definitions, including the American-European Consensus Conference definition from 1994, the Murray Acute Lung Injury Score from 1998, the Delphi Consensus definition from 2005, and the Berlin definition from 2012, were all designed for adult populations.
Although PARDS affects only about 6 to 10 percent of patients in the pediatric intensive care unit, these patients consume approximately 80 percent of the unit's time and resources. They are, by definition, among the sickest children in any PICU. This clinical burden makes it essential to develop sound, evidence-based guidelines for their management.
The causes of PARDS are numerous. Sepsis and infectious pneumonia, bronchiolitis, aspiration, major trauma, pulmonary contusion, burns, inhalational injury, massive transfusions, transfusion-related acute lung injury, acute pancreatitis, fat embolism, envenomation, drowning, drug reactions, malignancy, and lung transplantation can all trigger PARDS. Regardless of the initiating cause, every one of these conditions presents a ventilation challenge that demands a carefully considered approach.
How PARDS Develops: Pathophysiology
In a healthy lung, each alveolus contains a layer of surfactant produced by type 2 pneumocytes. This surfactant maintains appropriate surface tension to keep the alveolus inflated. A basement membrane protects the alveolar wall. Capillaries remain close to the alveolar surface, enabling good ventilation-perfusion matching, and alveolar macrophages remain relatively quiescent.
When a patient becomes critically ill and requires mechanical ventilation, the shear forces generated by the ventilator can slough bronchial epithelium, denude the basement membrane, and create stress fractures in alveolar tissue. Interstitial flooding leads to protein-rich edema, which inactivates surfactant. Disrupted apoptosis impairs normal cellular renewal. Fibrin collects within alveolar walls, and gap formations develop in capillary walls under the pressure and volume delivered by the ventilator.
Once blood enters the air spaces or air enters the tissue spaces, an inflammatory cascade is triggered. Activated alveolar macrophages release interleukins and tumor necrosis factor, which act as chemoattractants for neutrophils. Neutrophils migrate into the lung from the bloodstream and, in attempting to contain the injury, release oxidants, leukotrienes, and proteases. The result is the full clinical picture of PARDS.
PALICC 1 (2015): The First Pediatric ARDS Consensus
In response to the absence of pediatric-specific ARDS guidelines, the first Pediatric Acute Lung Injury Consensus Conference convened. PALICC 1, completed in 2015, brought together 27 experts from eight countries. It was the first attempt to define ARDS specifically for pediatric patients. Over approximately three years, the group produced nine sections of guidance and more than 151 recommendations. The evidence base drew from both adult data and infant data, including studies conducted in neonatal intensive care units.
PALICC 2 (2023): An Expanded Effort
PALICC 2 was far more ambitious in scope. The consensus group expanded to 56 experts representing 15 countries across six continents. Forty-one percent of the participants were women, a significant increase from 2015. For the first time in either consensus conference, a respiratory therapist was included among the experts: Natalie Napolitano, MPH, RRT-NPS.
The process began in 2019 and was completed in 2023. The group conducted a systematic literature review to identify, assess, and combine all available evidence from adult randomized controlled trials, pediatric studies, and meta-analyses. Critically, no perinatal or neonatal data were included, reflecting the recognition that children are also not premature infants. The GRADE framework (Grading of Recommendations, Assessment, Development, and Evaluation) was used to classify each recommendation as either weak or strong. A strong recommendation required at least 96 percent agreement among participants after up to three rounds of voting. The final product comprised 11 sections and more than 160 recommendations.
Two new sections were added that had not existed in PALICC 1. The first addressed noninvasive respiratory support, reflecting the dramatically expanded use of noninvasive ventilation in pediatric critical care since 2015. The second addressed implementation in resource-limited settings, recognizing that not all centers have access to advanced equipment, full staffing, or the complete range of ventilatory options available in major teaching hospitals.
One inherent challenge for any PARDS guideline is the extraordinary range of patients it must cover. A pediatric patient with ARDS may be a young infant or a 17-year-old adolescent. Achieving consensus recommendations that apply meaningfully across this entire age spectrum is part of why strong recommendations require such a high level of agreement.
The Updated PARDS Definition
The core elements of the PARDS definition remained unchanged between PALICC 1 and PALICC 2. A patient with an oxygen index (OI) greater than 4, or an oxygen saturation index (OSI) greater than 5, should be considered at risk for PARDS. The major addition in PALICC 2 was the formal inclusion of a definition for noninvasive patients who cannot have an OI calculated because they do not have a measured mean airway pressure.
PALICC 2 also introduced an important change regarding the timing of diagnosis. Clinicians should not diagnose PARDS immediately upon a patient's arrival. Instead, the patient should be given four or more hours to stabilize with appropriate support before the diagnosis is made. The rationale is that modern therapists using modern equipment have become quite effective at rapidly stabilizing these patients. Premature diagnosis risks overloading a child with intervention before it is clear how sick that child truly is.
Severity Classification
PALICC 1 defined mild and moderate PARDS as separate categories. PALICC 2 combined them into a single category, because the data show very little difference in mortality rates between the two groups. Treating them separately created a false distinction in a population that is uniformly high-risk.
For intubated patients, mild to moderate PARDS is defined as an OI less than 16 or an OSI less than 12. Severe PARDS is defined as an OI of 16 or greater, or an OSI of 12 or greater. These thresholds are unchanged from PALICC 1.
For noninvasive patients, the PF ratio (PaO2 divided by FiO2) is used in place of the OI. A PF ratio greater than 100 indicates mild to moderate PARDS, while a PF ratio of 100 or less indicates severe PARDS.
To calculate the OI for an intubated patient, multiply the FiO2 (expressed as a decimal) by the mean airway pressure, divide by the PaO2, then multiply by 100. For example, a patient on 65 percent oxygen with a mean airway pressure of 16 and a PaO2 of 82 yields an OI of 12.5, placing that patient in the mild to moderate category. If that same patient deteriorates to 90 percent oxygen, a mean airway pressure of 19, and a PaO2 of 72, the OI rises to 24, indicating severe PARDS.
Resource-Limited Settings
PALICC 2 added guidance for resource-limited settings where full imaging, conventional mechanical ventilation, or adequate staffing may not be available. In these settings, a patient who requires supplemental oxygen to maintain an SpO2 of 88 percent or greater should be considered at risk for PARDS. Possible PARDS is defined by high-flow nasal cannula use at 1.5 L/kg/min or 30 L/min, or by a PF ratio of 300 or less, or an SF ratio of 250 or less in a patient on nasal noninvasive ventilation.
These patients are extremely high-risk. Approximately 50 percent of PARDS patients managed on noninvasive support ultimately require intubation, and those who do have very high mortality rates. Noninvasive ventilation in this population must be approached as a time-limited trial, with active monitoring for physiological stability including heart rate, respiratory rate, oxygenation, and work of breathing. If a patient with severe PARDS does not improve on noninvasive support, intubation should be pursued within one hour. For mild to moderate PARDS, a trial of four to six hours is appropriate before escalating to intubation. Resource-limited centers should also ensure they have a system in place for transferring patients who require a higher level of care.
Tidal Volume
PALICC 1 recommended a tidal volume (VT) of 5 to 8 mL/kg for patients with better respiratory system compliance, and 3 to 6 mL/kg for those with poor compliance. PALICC 2 updated this guidance based on a rigorous review of the evidence.
A landmark 1998 study by Amato and colleagues compared conventional ventilation using a VT of 12 mL/kg against a more protective strategy with a VT of 6 mL/kg. Patients on 12 mL/kg had a survival rate of approximately 28 percent. Those on 6 mL/kg had a survival rate of approximately 60 percent, demonstrating clearly that protective ventilation saves lives.
A subsequent multicenter randomized controlled trial by Dr. Khemani and colleagues found that 6 to 8 mL/kg produced the highest survival rates. Dropping below 6 mL/kg was associated with worse outcomes, possibly due to inadequate alveolar ventilation.
PALICC 2 revised the tidal volume recommendation to 6 to 8 mL/kg, with strong agreement at 98 percent. For patients in whom these volumes would cause plateau or driving pressures to exceed recommended limits, a VT less than 6 mL/kg should be used. In the most severely ill patients where survival is the primary concern, VT less than 4 mL/kg may be used with caution.
PEEP Recommendations
PALICC 1 recommended moderately elevated PEEP levels of 10 to 15 cm H2O, with higher levels considered acceptable in severe PARDS. PALICC 2 moved to a more structured approach.
PALICC 2 endorsed the Low PEEP/High FiO2 table from the ARDS Network protocol, which provides specific FiO2 and PEEP combinations to achieve adequate oxygenation. The target SpO2 range is 88 to 97 percent. Clinicians should use the table to guide their FiO2 and PEEP selections, recognizing that a PEEP lower than what the ARDSnet protocol specifies for a given FiO2 level is associated with higher pediatric mortality. There was strong agreement on this point at 96 percent.
The FiO2/PEEP table provides the following general pairings: FiO2 of 30 percent pairs with a PEEP of 5; 40 percent with 6 to 8; 50 percent with 8 to 10; 60 percent with 10; 70 percent with 10 to 14; 80 percent with 14; 90 percent with 14 to 18; and 100 percent with 18 to 24.
Importantly, PEEP should not be raised in isolation. As the patient's compliance, tidal volume, and hemodynamics change, PEEP should be titrated accordingly. As oxygenation improves and FiO2 is weaned, PEEP should be weaned in parallel to track the table. Conversely, when adjusting PEEP upward, clinicians must monitor that plateau pressure and driving pressure do not exceed their recommended limits. There was 100 percent agreement on this principle.
Evidence from large-scale studies supports elevating PEEP as the most effective single strategy for reducing the relative risk of death in ARDS. Research comparing three approaches, raising PIP without changing PEEP, raising both PIP and PEEP to maintain driving pressure, and raising PEEP while holding PIP stable, found that the last approach produced the most stable and favorable outcomes.
Driving Pressure: A New Addition in PALICC 2
Driving pressure is entirely new to PALICC 2; it was not addressed in PALICC 1. Driving pressure is defined as the difference between plateau pressure and PEEP. It is calculated by performing a brief inspiratory pause of two to three seconds. During this pause, pressure drops slightly as the lung and circuit absorb the delivered volume. The pressure at the end of that pause is the plateau pressure, not the peak inspiratory pressure. Driving pressure equals plateau pressure minus PEEP.
PALICC 2 recommends keeping plateau pressure at or below 28 cm H2O, with low agreement at 92 percent. In patients with reduced chest wall compliance, plateau pressures of 29 to 32 cm H2O may be necessary. These values are unchanged from PALICC 1.
The new addition is a specific limit on driving pressure: it should not exceed 15 cm H2O, as measured under static conditions. Although this recommendation achieved only 82 percent agreement and is therefore categorized as very low agreement in the GRADE framework, the clinical rationale is compelling. The lower the driving pressure, the lower the alveolar strain, and the better the patient's outcomes.
Consider a patient on a PEEP of 9 with a plateau pressure of 24: the driving pressure is 15, which is exactly at the recommended limit. If PEEP is then increased to 12 to improve oxygenation, the plateau pressure may rise above 28, pushing the patient into the lung injury risk zone. The appropriate response is to lower the tidal volume, which will bring the plateau pressure and driving pressure back within acceptable limits.
In practice, the three variables of PEEP, tidal volume, and driving pressure must be managed together. Increasing PEEP may require a corresponding reduction in tidal volume to stay within driving pressure limits.
Noninvasive Ventilation
PALICC 1 contained no guidance on noninvasive ventilation (NIV). PALICC 2 added a dedicated section reflecting the significant expansion of NIV use in pediatric critical care over the intervening years.
Meta-analytic data reviewed by PALICC 2 consistently showed that noninvasive approaches, including CPAP and high-flow nasal cannula, favor outcomes compared to standard oxygenation therapy. PALICC 2 recommends a time-limited trial of NIV, specifically CPAP or BiPAP, for patients who do not have a clear indication for immediate intubation. There was 88 percent agreement on this recommendation.
However, the time-limited nature of this trial must be taken seriously. If a patient on NIV does not demonstrate clinical improvement within four to six hours, or shows signs of deterioration, intubation should occur. There was 94 percent agreement on this point. The rationale is important: even patients who are never intubated can develop chronic lung disease if they struggle on noninvasive support for too long. Prolonged effort without adequate mean airway pressure to maintain an open lung strategy leads to ongoing injury through a different mechanism.
I recall a Canadian respiratory therapist describing a patient who was managed on NIV for 24 days before the team finally decided to intubate. The first post-intubation chest radiograph revealed chronic lung disease, despite the patient having never been on a conventional ventilator. Prolonged struggle on NIV had produced the injury.
For resource-limited settings, PALICC 2 suggests using CPAP or high-flow nasal cannula over standard oxygen therapy for patients at risk for PARDS (92 percent agreement), and CPAP over high-flow nasal cannula for patients with possible PARDS (83 percent agreement).
P-SILI: Patient Self-Inflicted Lung Injury
P-SILI, or patient self-inflicted lung injury, is another concept that is entirely new to PALICC 2. Unlike ventilator-induced lung injury, P-SILI is driven by the patient's own spontaneous breathing effort. When spontaneous breathing is intensely labored, large swings in transpulmonary pressure are generated. These pressure swings create alveolar stress even in the absence of mechanical ventilation. The worse the lung compliance, the more severe the problem.
P-SILI can occur in patients on conventional mechanical ventilation as well as those on noninvasive support. A patient taking large unassisted breaths through a poorly calibrated ventilator circuit is effectively injuring himself with each breath. This is why monitoring work of breathing is so important in every PARDS patient. Signs of excessive respiratory effort may indicate the need for sedation, neuromuscular blockade adjustment, or a reassessment of the ventilatory strategy itself.
Before proceeding to sedation or neuromuscular blockade, it is worth evaluating whether the ventilatory strategy itself can be adjusted to reduce the patient's drive to breathe. If a patient is working hard against the ventilator, it may be that the ventilator is not meeting the patient's needs. Modifying the strategy may reduce the work of breathing without requiring additional pharmacological intervention.
Putting It All Together
When a patient arrives in the PICU and is placed on noninvasive support, the clinician should begin calculating SF ratios and monitoring work of breathing immediately. Targeted sedation, adequate nutrition, and fluid management should be established as standard practice. Oxygenation targets on noninvasive support are an SpO2 of 92 to 97 percent.
If the patient requires intubation, the OI becomes the primary severity measure. On invasive ventilation, the PALICC 2 framework directs clinicians to maintain plateau pressure at or below 28 cm H2O, driving pressure at or below 15 cm H2O, tidal volume at 6 to 8 mL/kg, and PEEP according to the ARDSnet Low PEEP/High FiO2 table. The SpO2 target shifts to 88 to 97 percent to avoid exposing the patient to excessive oxygen toxicity.
As the OI worsens and the patient's condition deteriorates, additional interventions may be considered. Tidal volume may be reduced to 4 to 6 mL/kg. Neuromuscular blockade, inhaled nitric oxide therapy, prone positioning, and recruitment maneuvers may all be appropriate depending on the clinical picture. High-frequency jet ventilation (HFJV) or high-frequency oscillatory ventilation (HFOV), while not receiving a formal recommendation in PALICC 2, are available options when standard approaches are insufficient. If all conventional and rescue strategies are failing, extracorporeal membrane oxygenation (ECMO) must be considered before the window for safe cannulation closes.
Recruitment Maneuvers and High-Frequency Jet Ventilation
Recruitment maneuvers aim to open collapsed lung units and stabilize them at an adequate PEEP. An approach supported by evidence involves delivering a pressure 5 to 8 cm H2O above PEEP, no more than 15 cm above, and sustaining that pressure for 20 to 30 seconds, followed by a brief release, and then repeating the maneuver three times. On a conventional ventilator, this is approximated using two- to three-second inspiratory pause times. The underlying mechanism is pendulluft flow: when the inspiratory pause is long enough, air redistributes from better-ventilated alveoli to adjacent collapsed units, promoting gradual recruitment. This effect does not occur with the very short inspiratory times often used in standard ventilation.
PALICC 1 stated that HFJV could not be recommended for the routine management of PARDS but acknowledged it as a possible option in patients with severe pulmonary air leak syndrome, with 64 percent agreement. PALICC 2 made no recommendation for or against high-frequency ventilation of any type, despite the existence of multiple published studies. Research published in 2015 and 2020 as well as a 2021 study in the Respiratory Care journal demonstrated that HFJV improves oxygenation indices, normalizes pH, reduces FiO2 requirements, and may reduce the need for ECMO in PARDS patients. These studies also suggested that starting HFJV before the condition becomes too severe produces the best results.
The absence of HFJV from PALICC 2 reflects a gap in the evidence rather than evidence of harm. This represents an area where respiratory therapy researchers can make a meaningful contribution ahead of future consensus development.
The most important message from PALICC 2 was articulated simply by Dr. Cheifetz: back to basics and protective ventilation. How a patient is ventilated must be as protective as possible. Maintaining lower driving pressures, optimizing PEEP, delivering appropriate tidal volumes, and using longer inspiratory times at lower pressures all contribute to a safer ventilatory approach. High-frequency ventilation, conceptually described as CPAP with a wiggle, takes this principle to its logical extreme by delivering mean airway pressure without high-volume, high-pressure excursions.
Summary
PALICC 2 represents a rigorous, methodologically sound advance in the management of pediatric ARDS. Key achievements include the use of a larger and more diverse expert group, the exclusion of neonatal data to focus specifically on pediatric populations, the consolidation of mild and moderate PARDS into a single category, a four-hour observation window before diagnosis, and the formal extension of guidance to noninvasive patients and resource-limited settings.
The core recommendations that respiratory therapists should carry into practice are the tidal volume target of 6 to 8 mL/kg, PEEP management guided by the ARDSnet Low PEEP/High FiO2 table, plateau pressure at or below 28 cm H2O, driving pressure at or below 15 cm H2O, and active monitoring of work of breathing to detect P-SILI. Time-limited trials of noninvasive support with a clear threshold for escalating to intubation are also central to the revised guidelines.
Many recommendations carry only low or very low certainty of evidence, primarily because insufficient pediatric-specific research exists. This is an opportunity and a call to action for respiratory therapists who wish to engage in research. The areas with the weakest evidence, including high-frequency ventilation and several adjunctive therapies, are precisely where new data would have the greatest impact. If you are involved in PARDS research, you are contributing directly to the evidence base that will inform PALICC 3.
Questions and Answers
Given the broad age range of pediatric patients, from infants to adolescents, is it surprising that such a high level of agreement was required to achieve a strong recommendation?
That is an important point. The age range is precisely why strong recommendations are so difficult to achieve. The variability in patient size, developmental stage, and pathophysiology across the pediatric spectrum means that a recommendation which applies well to a one-year-old may not apply equally well to a fifteen-year-old. The requirement for 96 percent or greater agreement likely reflects this challenge. It is very hard to achieve near-universal consensus when the patient population is so heterogeneous.
What areas of PARDS research would you most encourage respiratory therapists to pursue?
The best strategy is to look at the PALICC 2 guidelines themselves and identify the sections where the recommendations carry the weakest evidence. Those are the areas where new research would have the greatest impact. High-frequency ventilation is a clear example: it received a strong recommendation in PALICC 1 only for air leak syndrome, received no consideration at all in PALICC 2, and yet multiple published studies suggest clinical benefit. That gap between available evidence and guideline inclusion represents an opportunity. More broadly, any section of the guidelines where the certainty of evidence is categorized as low or very low is a candidate for future study. Respiratory therapists who engage in this research will be among the heroes of PALICC 3.
References
References are provided in the course handout.
Citation
Richards, E. (2026). An RT overview of the revised pediatric acute respiratory distress syndrome (PARDS) guidelines from PALICC II. SpeechPathology.com, Article 283. Available at https://www.continued.com/respiratory-therapy/.
Mar 19, 2025
1 CE HourSMA in Pediatrics (Spinal Muscular Atrophy)
Nadia Smith-Chant, RRT, BS
Editor’s note: This text-based course is an edited transcript of the webinar, SMA in Pediatrics (Spinal Muscular Atrophy), presented by Nadia Boussalham, BS, RRT.
It is recommended that you download the course handout to supplement this text format.
Learning Outcomes
After this course, participants will be able to:
- Recognize Spinal Muscular Atrophy (SMA) and review its implications in pediatric patients
- Discuss the different types of Spinal Muscular Atrophy (SMA) and identify the available medications for treatment
- Describe respiratory treatments and management strategies for pediatric patients diagnosed with Spinal Muscular Atrophy (SMA)
What Happens With SMA?
To begin with, Spinal Muscular Atrophy (SMA) is a genetic disorder that causes muscle weakness, particularly in the skeletal muscles. As a result, it can severely affect a child's ability to crawl, walk, or even control head movements. In more severe cases, SMA can impair the muscles involved in breathing and swallowing, posing serious health risks.
The root of the problem lies in the motor neurons, which control muscle strength and movement. These neurons are located in the spinal cord and the lower part of the brain. In individuals with SMA, these motor neurons start to break down, preventing the brain’s signals from reaching the muscles. As a result, the muscles weaken and eventually deteriorate, a process known as atrophy, similar to what occurs in other genetic disorders.
SMA is an autosomal recessive disorder, meaning a person must inherit two mutated genes—one from each parent—to develop the condition. Most forms of SMA are linked to a mutation in the SMN1 gene, which fails to produce sufficient protein to support the motor neurons. Without enough of this protein, the neurons degenerate and lose their ability to send signals to the muscles, leading to progressive muscle weakening and damage.
Genetic Disease
A child with spinal muscular atrophy (SMA) inherits one copy of the mutated gene from each parent. For a child to develop SMA, they must inherit two non-functioning SMN1 genes—one from each parent. This pattern of inheritance is known as autosomal recessive, meaning both copies of the gene must be defective for the disease to manifest.
If both parents are carriers of the same SMN1 gene mutation, there is a 25% (or one in four) chance that the child will inherit the mutated gene from both parents, resulting in the child developing SMA. This is because each parent has one functioning and one non-functioning gene copy, and the likelihood of both non-functioning genes being passed down simultaneously is 25%. This scenario can happen with no prior symptoms in the family, as carriers of the mutation are asymptomatic.
In addition to the 25% chance of having a child with SMA, there is a 50% chance that the child will inherit only one copy of the mutated gene, making them a carrier, like their parents. Carriers of the SMA gene do not exhibit symptoms of the disease but can pass the mutated gene to their children. This means that while carriers themselves are unaffected, they still have a 50% chance of passing the defective gene to the next generation, increasing the likelihood of SMA in future descendants if both parents are carriers.
Lastly, there is a 25% chance that the child will inherit two fully functioning SMN1 genes, one from each parent, meaning the child will neither have the disease nor be a carrier of the mutated gene. In this case, the child is entirely free from the SMA gene mutation and its associated risks.
It is crucial to understand the value of carrier testing, which can identify individuals who carry the SMN1 gene mutation. Carrier testing is particularly important for families with a history of SMA or for couples planning to have children. Early knowledge of carrier status allows for genetic counseling, where healthcare professionals can help prospective parents understand the risks and implications of SMA, guide them in making informed reproductive decisions, and discuss potential options like in vitro fertilization (IVF) with pre-implantation genetic diagnosis (PGD) to select embryos without the mutation.
Additionally, prenatal testing can be conducted during pregnancy to determine if the fetus has inherited the mutated genes. This can provide critical information for managing pregnancy and preparing for potential outcomes if the child is diagnosed with SMA.
Overall, understanding the inheritance pattern of SMA and the options available for carrier testing and genetic counseling can help families make proactive choices and manage risks associated with this genetic disorder.
Severe Neuromuscular Disease
SMA is a severe and progressive neuromuscular disease that primarily affects motor neurons, leading to muscle weakness and atrophy. According to the Centers for Disease Control and Prevention (CDC), as of 2021, approximately one in every 10,000 births result in a baby being born with SMA, making it one of the most common causes of genetic infant mortality. Furthermore, an estimated one in 51 people worldwide is a carrier of the SMA gene mutation, underscoring its prevalence as one of the most common rare diseases.
This frequency places SMA alongside other well-known genetic conditions such as cystic fibrosis, Duchenne muscular dystrophy, and amyotrophic lateral sclerosis (ALS), also known as Lou Gehrig's disease. Like these conditions, SMA can have a profound impact on motor function, with the severity of symptoms varying based on the specific type of SMA and the number of copies of the SMN2 gene a person carries.
SMA affects individuals across all genders, races, and ethnicities, with no disparities in its prevalence. Both males and females are equally likely to inherit the disease, as SMA is passed down through an autosomal recessive inheritance pattern. This means that for a child to develop SMA, they must inherit two copies of the defective SMN1 gene—one from each parent. If both parents are carriers of the mutation, there is a 25% chance that their child will inherit both faulty genes and develop SMA, a 50% chance that the child will be a carrier like the parents and a 25% chance that the child will inherit two normal copies of the SMN1 gene.
The diagnosis of SMA is confirmed through molecular genetic testing, a highly reliable method that identifies mutations in the SMN1 gene responsible for the disorder. Genetic testing typically involves a blood sample, and in some cases, prenatal genetic testing may be offered if there is a family history of SMA or if both parents are known carriers. In recent years, many states have also included SMA in their newborn screening programs, allowing for early detection before symptoms appear. Early diagnosis is critical because it enables early intervention with treatments that can significantly improve outcomes, particularly with the advent of gene therapy and splice-modifying therapies.
Diagnosis of SMA
Testing for mutations in the SMN1 and SMN2 genes is highly reliable and considered the gold standard for diagnosing spinal muscular atrophy (SMA) when typical symptoms are present. Because of the accuracy of genetic testing, there is usually no need for a muscle biopsy. Genetic testing involves a quantitative analysis of both SMN1 and SMN2 genes using a technique known as multiplex ligation-dependent probe amplification (MLPA). This method allows for the detection of copy number variations in both genes.
Another commonly used method is PCR followed by restriction digest, which can identify homozygous deletions in the SMN1 gene. While PCR is faster and less expensive than MLPA, it does not provide a quantitative analysis of SMN1 or SMN2 copy numbers. However, it is often readily available in many labs and remains a reliable diagnostic option.
Understanding the number of SMN1 copies is crucial for identifying heterozygous deletions, while the number of SMN2 copies plays a key role in predicting disease severity and guiding therapeutic approaches. In diagnosing SMA, it is important to note that some of its symptoms can resemble those of other neuromuscular disorders, such as muscular dystrophy. To determine the cause of these symptoms, healthcare providers will typically conduct a physical exam and obtain a comprehensive medical history. Physicians may also order additional tests, including genetic testing, to confirm the diagnosis of SMA.
Some of the tests used to diagnose SMA include blood tests, such as enzyme and protein tests, which check for elevated levels of creatine kinase. This enzyme is released into the bloodstream when muscles deteriorate, serving as a potential indicator of muscle damage. A genetic test is another critical diagnostic tool specifically designed to identify mutations in the SMN1 gene. Genetic testing is highly effective, with a 95% success rate in detecting altered SMN1 genes.
In some states, SMA is included in routine newborn screening, which may also involve nerve conduction tests, such as an electromyogram (EMG). An EMG measures the electrical activity of nerves and muscles, helping to assess neuromuscular function.
In rare cases, a muscle biopsy may be performed. This procedure involves removing a small sample of muscle tissue and sending it to a lab for analysis. The biopsy can reveal muscle atrophy, which, as previously mentioned, is the progressive loss of muscle tissue.
But why does this happen? As we have discussed, spinal muscular atrophy is a genetic disorder. Most forms of SMA are caused by mutations in the survival motor neuron (SMN) gene, which leads to the degeneration of motor neurons and the resulting muscle weakness and atrophy.
Why Does It Happen?
The SMN1 gene, located on the fifth chromosome, is crucial for producing the survival motor neuron (SMN) protein, which plays an essential role in the health and function of motor neurons. These motor neurons are responsible for transmitting signals from the brain to the muscles, allowing for voluntary muscle movements. When the SMN1 gene is functioning normally, it produces sufficient levels of the SMN protein to maintain normal motor neuron function, enabling muscles to receive the necessary signals to move.
However, when the SMN1 gene is mutated or deleted, there is an insufficient production of SMN protein, leading to the degeneration of motor neurons. This deterioration disrupts the brain's ability to communicate with the muscles, ultimately causing the characteristic muscle weakness and wasting (atrophy) seen in SMA. The progressive loss of motor neurons results in the muscles' inability to contract and move, affecting a person's mobility and, in severe cases, their ability to breathe and swallow.
The severity of SMA is heavily influenced by the number of copies of the SMN2 gene, a gene that is similar to SMN1 but produces less functional SMN protein. The SMN2 gene is considered a "backup" gene because, while it cannot fully replace SMN1, it can still produce a small amount of functional SMN protein. The number of SMN2 copies a person has varies from individual to individual, and this variation significantly impacts the severity and progression of the disease.
Individuals with fewer copies of SMN2 (typically one or two copies) tend to experience the most severe forms of SMA, such as Type 1 SMA, which manifests in infancy. These individuals produce very little functional SMN protein, leading to the early onset of symptoms, including severe muscle weakness, difficulty breathing, and problems with swallowing.
Individuals with more copies of SMN2 (three or more copies) generally have a later onset and a milder disease course, as seen in Type 2 or Type 3 SMA. These individuals produce more SMN protein, which provides some level of compensation for the loss of SMN1 function. This results in less severe symptoms, such as delayed motor milestones (e.g., sitting, standing, walking), but they still experience progressive muscle weakness over time.
In Type 4 SMA, which typically occurs in adulthood, individuals may have up to six or eight copies of SMN2, allowing for a relatively mild progression of the disease with less impairment in daily activities compared to earlier-onset forms.
While the SMN2 gene provides some compensation for the lack of SMN1, most of the SMN protein it produces is truncated and non-functional due to a splicing error that removes exon 7. Only a small fraction of the protein produced by SMN2 is full-length and functional. Therefore, the more copies of SMN2 an individual has, the more functional SMN protein is produced, which helps mitigate the severity of the disease but does not fully prevent the symptoms of SMA.
What Is A Gene?
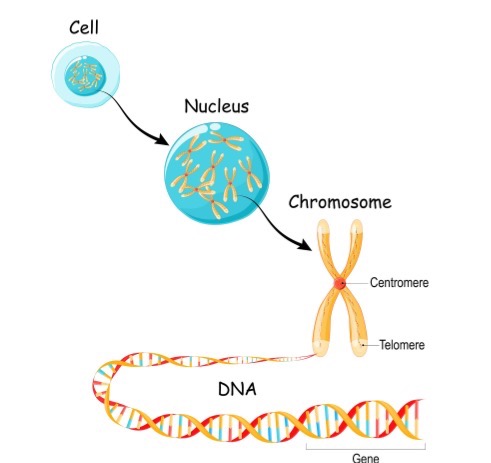
Figure 1. Illustration of a gene (Continued, Getty).
A gene is the basic physical and functional unit of heredity, made up of DNA (Figure 1). Some genes provide instructions for making molecules called proteins, which are essential for the body’s structure and function. In humans, genes vary widely in size, ranging from a few hundred DNA bases to over 2 million bases.
Humans have approximately 20,000 to 25,000 genes—that is a lot of genetic material! To keep track of them, scientists give each gene a unique name. Since gene names can be long, they are often assigned symbols, which are short combinations of letters and sometimes numbers that serve as an abbreviated version of the full gene name. For example, a gene on chromosome seven associated with cystic fibrosis is called the cystic fibrosis transmembrane conductance regulator, but its symbol is CFTR.
Gene Defect in SMA
- Patients with SMA lack a functioning SMN1 gene
- The SMN1 gene tells the body how to make survival motor neuron (SMN) protein
Patients with SMA lack a functioning SMN1 gene. The SMN1 gene provides instructions for the body to produce SMN protein, which is essential for maintaining the health and function of motor neurons.
To give an example, most people are familiar with cystic fibrosis, a genetic condition linked to a specific gene mutation. Similarly, the most common form of SMA is caused by a mutated or missing SMN1 gene. This gene is located on chromosome five and produces the SMN protein, which is critical for motor neuron survival. When a mutation occurs in both copies of the SMN1 gene (one on each chromosome five), there is a deficiency in SMN protein production. Normally, most proteins produced by SMN1 are full-length and functional, but in SMA, little to no full-length, functional SMN protein is made.
However, this loss can be partially compensated by the presence of neighboring SMN2 genes, which are 99% similar to SMN1. The number of SMN2 gene copies varies between individuals. Although most proteins produced by SMN2 are short and non-functional, some are full-length and functional. The more copies of SMN2 a person has, the more functional SMN protein is produced, which can moderate the severity of the disease.
SMA is a neuromuscular disorder characterized by this deficiency in SMN protein, leading to the degeneration of motor neurons and progressive muscle weakness. Understanding the role of both SMN1 and SMN2 is essential for grasping the genetic basis and variability of the disease.
SMN Protein
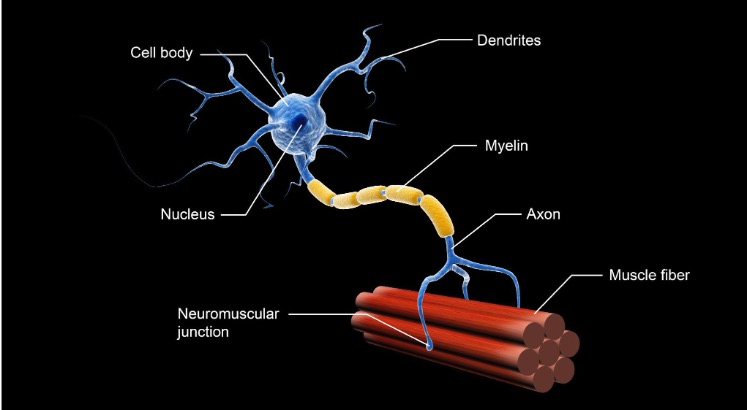
Figure 2. Structure of a motor neuron (Continued, Getty).
Figure 2 illustrates the structure of a motor neuron. The motor neuron dysfunction in SMA leads to progressive muscle weakness and atrophy, with the severity typically greater in the proximal muscles—those closer to the center of the body, such as the muscles in the trunk, chest, upper legs, and arms. In contrast, the distal muscles, such as those in the hands and feet, are generally less affected. This pattern of muscle weakness makes tasks like standing, walking, or lifting objects more difficult, especially as the disease progresses.
The SMN protein, which is deficient in SMA, plays a critical role in processing molecules called messenger RNA (mRNA). mRNA is essential in the process of protein synthesis, where genetic information from DNA is translated into functional proteins. The SMN protein is specifically involved in the assembly of small nuclear ribonucleoproteins (snRNPs), which are necessary for the accurate splicing of pre-mRNA. Proper splicing ensures that mRNA is correctly formed, allowing the production of functional proteins. Additionally, the SMN protein supports the development and maintenance of dendrites and axons, which are extensions of nerve cells (neurons) that facilitate the transmission of signals between the brain, spinal cord, and muscles.
For example, the phrenic nerve, which originates in the neck and extends to the diaphragm, sends involuntary signals to the diaphragm to control breathing. In severe forms of SMA, the degeneration of motor neurons that control the phrenic nerve can compromise respiratory function, making it difficult for affected individuals to breathe independently. This is why many patients with severe SMA, particularly Type 1, often require respiratory support, such as non-invasive ventilation or mechanical ventilation, to assist with breathing.
The SMN2 gene is considered the disease-modifying gene in SMA because it is almost identical to SMN1, except for a single nucleotide difference in exon 7. This small difference has significant consequences for the processing of SMN2 mRNA. In most cases, the exclusion of exon 7 during the splicing process results in the production of truncated, non-functional versions of the SMN protein. However, SMN2 can still produce some functional SMN protein, as one of the versions, known as isoform D, includes exon 7 and is full-length and functional.
Isoform D accounts for approximately 10% of the total functional SMN protein produced by SMN2. While this small amount of protein can help mitigate the severity of SMA, it is insufficient to fully compensate for the loss of SMN1. The more copies of SMN2 a person has, the greater the amount of isoform D that can be produced, which helps increase the overall levels of functional SMN protein in the body. This is why individuals with more copies of SMN2 tend to have a milder form of SMA with a later onset of symptoms, as their bodies can produce more functional SMN protein.
In severe cases of SMA, such as Type 1, patients may have only one or two copies of SMN2, leading to very low levels of functional SMN protein. This results in early-onset symptoms, such as profound muscle weakness, difficulty swallowing, and respiratory complications. On the other hand, patients with Type 3 or Type 4 SMA often have three or more copies of SMN2, allowing for a higher production of isoform D and thus a milder disease course with later onset symptoms and slower progression of muscle weakness.
SMN2 Gene
The SMN2 gene produces several different versions of the SMN protein, most of which are shorter and quickly degraded due to the exclusion of exon 7 during the splicing process. These truncated proteins are non-functional and cannot adequately support motor neuron survival. Only a small fraction of the protein produced by SMN2 is full-length and functional, which contributes to the overall amount of functional SMN protein in the body.
The number of SMN2 gene copies a person has can vary between individuals, ranging from two to eight copies, and this number plays a crucial role in determining the severity and type of SMA a person develops. The more copies of SMN2 a person has, the more functional SMN protein they can produce, which helps mitigate the severity of the disease.
- Type 1 SMA (the most severe form of the disease) is typically associated with two copies of the SMN2 gene. Patients with Type 1 SMA usually show symptoms early in infancy, such as severe muscle weakness, respiratory issues, and difficulty swallowing. These patients often require respiratory support and have a limited ability to achieve motor milestones, such as sitting or standing without assistance.
- Type 2 SMA patients usually have three copies of SMN2. This form of the disease presents in early childhood, with symptoms appearing between six months and two years of age. While Type 2 patients may be able to sit independently, they generally cannot walk unaided and will experience progressive muscle weakness over time.
- Type 3 SMA, which can manifest later in childhood or adolescence, is also associated with three copies of SMN2 but tends to be less severe than Type 2. Within Type 3, there is a subcategory known as Type 3b SMA, which is linked to four copies of SMN2. Individuals with Type 3b typically experience a later onset of symptoms and may retain the ability to walk longer than those with fewer SMN2 copies, though they will still experience progressive muscle weakness.
- Type 4 SMA, the mildest form of the disease, usually appears in adulthood and is linked to four to six copies of SMN2. Patients with Type 4 SMA may retain most of their motor function for a significant portion of their lives and tend to experience slower progression of muscle weakness compared to those with earlier-onset forms of the disease.
The relationship between SMN2 copy number and the severity of SMA is a key factor in understanding the variability of the disease. In patients with more SMN2 copies, the increased production of full-length SMN protein provides greater support for motor neuron function, leading to a milder disease course. However, despite the presence of additional SMN2 copies, none of the forms of SMA can be completely prevented, as SMN2 cannot fully replace the function of the SMN1 gene.
As we continue, we will delve deeper into the different types of SMA and discuss their clinical characteristics, treatment strategies, and management approaches to help better understand the variability and progression of this complex neuromuscular disorder.
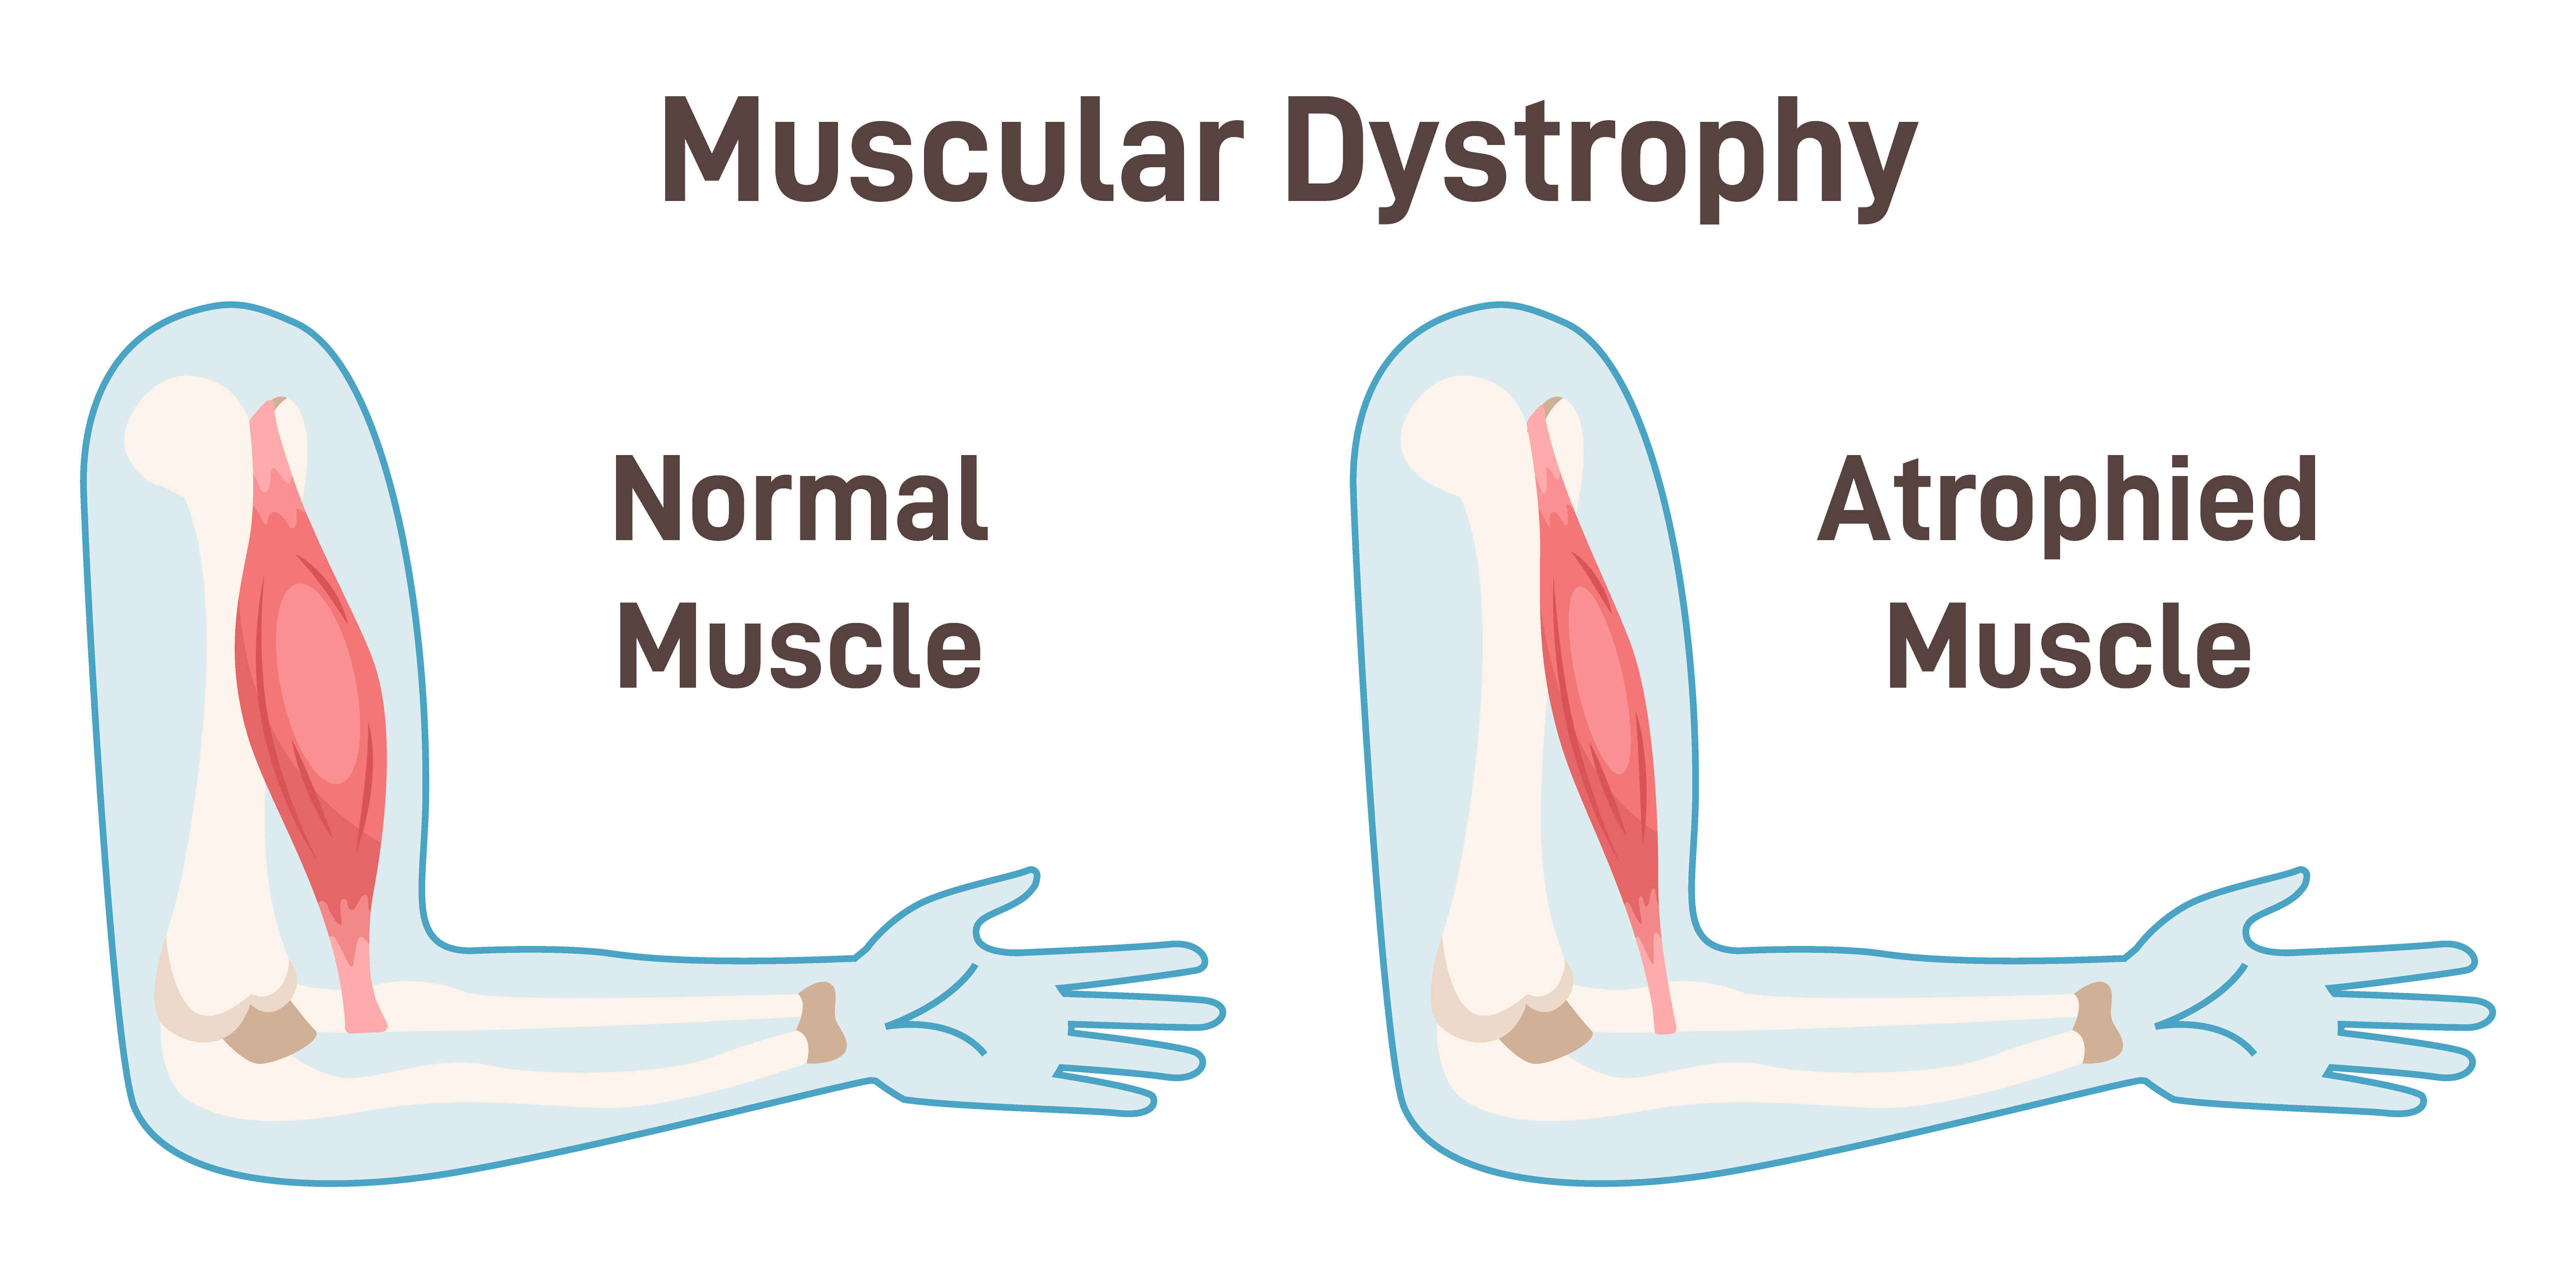
Figure 3. Illustration of normal muscle and atrophied muscle (Continued, Getty).
In SMA, the deterioration of motor neurons—the nerves responsible for controlling muscle strength and movement—leads to progressive muscle weakness (Figure 3). These motor neurons are located in the spinal cord and the lower part of the brain. As they break down, they lose the ability to transmit signals from the brain to the muscles. Without these signals, muscles are unable to contract, leading to a gradual loss of muscle mass, a process known as atrophy.
Muscle weakness in SMA is usually symmetrical, meaning it affects both sides of the body equally. The weakness tends to be more severe in the proximal muscles, which are the muscles closest to the body’s core, such as those in the shoulders, hips, thighs, and upper arms. In contrast, the distal muscles, such as those in the hands and feet, are often less affected. This pattern of weakness makes it difficult for individuals with SMA to perform tasks like lifting objects, walking, or even holding up their heads in severe cases.
As the muscles atrophy, they become visibly smaller and thinner. In advanced stages of SMA, this muscle wasting can lead to significant physical impairments, including difficulty with basic motor functions, such as sitting up or moving the limbs. Over time, the lack of muscle activity can also result in complications such as joint contractures (stiffening of joints due to shortened muscles) and scoliosis (curvature of the spine), which can further limit mobility.
In addition to muscle weakness, the breakdown of motor neurons in severe cases of SMA can also affect respiratory muscles, particularly the diaphragm, making it difficult for patients to breathe independently. This is why many patients with more severe forms of SMA may require respiratory support, such as non-invasive ventilation or mechanical ventilation, to assist with breathing. As muscle atrophy in SMA is a gradual process, early intervention through physical therapy, assistive devices, and modern treatments can help slow the progression and improve the patient’s quality of life.
Staying Ahead of the Progression of SMA Today
SMA is often discovered through newborn screening, which has become a routine part of early diagnostics in many countries. If a child tests positive for SMA during this screening, doctors will typically order genetic tests to confirm the diagnosis and determine the number of copies of the SMN2 backup gene that the child has. These tests may also detect specific genetic mutations that indicate whether the SMN1 gene is malfunctioning or missing entirely. The number of SMN2 copies is crucial because it plays a significant role in predicting the severity of SMA—the more copies a person has, the milder the progression of the disease is likely to be. Identifying the number of SMN2 copies before a baby shows any symptoms is vital for initiating early treatment, which can significantly alter the course of the disease.
For example, if left untreated, a baby with only two copies of SMN2 is likely to show symptoms much earlier than a baby with four copies. In the past, before newborn screening was widely implemented, most children weren’t diagnosed with SMA until they began showing symptoms. At that point, the child was assigned a "type" of SMA based on when symptoms first appeared and which motor milestones they had or had not reached. Since newborn screening wasn’t always routine, this classification was largely based on observation and, in many cases, a degree of guesswork. The earlier the onset of symptoms, the more severe the type of SMA was assumed to be. There are currently four main types of SMA, with an additional fifth type that can be classified as Type 0 or congenital SMA.
By screening newborns and identifying SMA before symptoms appear, doctors can now take a more proactive approach. Early diagnosis through newborn screening and genetic testing has revolutionized how SMA is managed. It allows families and healthcare providers to stay ahead of the disease, implement treatments before irreversible damage occurs, and give children with SMA a better chance at a more typical developmental trajectory.
Different Types of SMA
There are four main types of SMA, each varying in severity, onset, and progression. Understanding these types is crucial for identifying the disease and providing appropriate treatment. Additionally, there is a Type 0, or congenital SMA, which is extremely rare and severe.
- Type 1 SMA (Werdnig-Hoffmann disease):
- This is the most common and severe form of SMA. Without treatment, it can be fatal, sometimes even before birth or within the first two years of life. Children with Type 1 SMA often show symptoms very early, usually by the age of 6 months. These symptoms include severe muscle weakness, difficulty breathing, and trouble swallowing. Thanks to routine newborn screenings, most children are diagnosed before they are assigned a specific type, allowing for early intervention with therapies that can dramatically improve their prognosis. Treatments such as Spinraza and Zolgensma can slow the progression of the disease and help maintain motor function.
- Type 2 SMA:
- Type 2 SMA typically presents in infancy, but it is less severe than Type 1. Children with Type 2 usually develop symptoms between 6 and 18 months of age. While they may be able to sit independently, they generally cannot walk unaided. Muscle weakness progresses over time, and respiratory issues may develop later. With advancements in treatment, many children with Type 2 SMA can live longer and maintain more motor function than previously possible.
- Type 3 SMA (Kugelberg-Welander disease):
- Type 3 SMA has a later onset, usually during childhood or adolescence. Individuals with Type 3 can often walk independently for some time but may gradually lose the ability to walk as they age. Symptoms such as muscle weakness and fatigue become more pronounced over time, especially in the legs and hips. While less severe than Types 1 and 2, Type 3 can still significantly impact daily life, and ongoing treatment and physical therapy are essential to maintain mobility for as long as possible.
- Type 4 SMA:
- Type 4 SMA is the mildest form, usually manifesting in adulthood. Symptoms such as muscle weakness and difficulty with movement develop slowly and may not become apparent until later in life. Individuals with Type 4 may not realize they have SMA for years, as the progression is very gradual. While this form of SMA is the least debilitating, it still requires medical management to slow the progression and address muscle fatigue and weakness.
- Type 0 (congenital SMA):
- Although rare, Type 0 SMA is the most severe form, often presenting at birth. Babies born with Type 0 typically show signs of severe muscle weakness and respiratory difficulties right away. Without immediate treatment, Type 0 SMA is often fatal within the first few months of life. Early diagnosis and intervention, even in these severe cases, can offer some improvement in survival and quality of life.
The different types of SMA vary not only in severity but also in the age of onset and rate of progression. Type 1 is the most severe, with rapid progression and early onset, while Type 4 is the slowest-developing form, often not diagnosed until adulthood. Some individuals with Type 3 or 4 SMA may not realize they have the condition until years after symptoms begin due to the gradual progression of muscle weakness. Early diagnosis, genetic testing, and advancements in treatment have significantly improved outcomes across all types of SMA, allowing many individuals to live longer, healthier lives with better motor function.
Type 1 (Infantile Onset)
Now, let's discuss Type 1 SMA, also known as infantile-onset SMA or Werdnig-Hoffmann disease. This is the most common and severe form of spinal muscular atrophy, typically affecting infants within the first six months of life. Muscle weakness associated with Type 1 SMA is often noticeable by around three months of age, but symptoms can begin as early as birth and appear anytime up to six months.
Children with Type 1 SMA often display a sunken chest appearance. Type 1 can be further classified into Type 1a, Type 1b, and Type 1c, with each subtype showing very similar symptoms but differing in the timing of onset and the severity of motor function impairment.
- Type 1b SMA: Symptoms typically emerge between zero to three months of age. Infants with Type 1b exhibit profound muscle weakness, much like their Type 1a counterparts. Early respiratory failure and severe hypotonia are common, as are sucking and swallowing difficulties, which complicate feeding and lead to malnutrition.
- Type 1c SMA: Onset occurs between zero to six months, and these patients may display mild to moderate head control—a slight improvement over Type 1a and 1b. Unlike Type 1a, these infants may be able to roll over, but they will never sit unsupported. Without respiratory support, the lifespan for infants with Type 1c is generally less than two years.
Across all subtypes of Type 1 SMA, affected infants often present with a characteristic frog-leg posture, where their legs are positioned outward, resembling a frog. This posture results from the profound weakness in their proximal muscles, particularly in the hips and thighs. Additionally, they display hyporeflexia, a diminished or absent reflex response, which is typical in children with motor neuron dysfunction.
Feeding issues are common, as these infants have significant sucking and swallowing difficulties—symptoms that typically start to become apparent in children around six months of age when they begin eating solid foods. Weakness in the muscles responsible for these actions increases the risk of aspiration and malnutrition, further complicating their care.
Children with Type 1 SMA experience profound muscle weakness and hypotonia, which significantly impairs their ability to achieve basic motor milestones. For example, these children are typically unable to sit independently, roll over, or hold their heads up, which are movements usually expected at this developmental stage. In addition to motor deficits, children with Type 1 often lack control over their head movement, which is one of the early signs of this severe muscle weakness.
One of the most critical complications of Type 1 SMA is early respiratory failure. The muscles responsible for breathing, including the diaphragm and intercostal muscles (between the ribs), are weakened, making it difficult for these infants to breathe effectively. This often leads to life-threatening respiratory problems early in life. Many children with Type 1 require respiratory support, such as non-invasive ventilation or even tracheostomy with mechanical ventilation, to assist with breathing and maintain oxygen levels.
In addition to respiratory issues, infants with Type 1 SMA often have trouble with feeding and swallowing, as the muscles involved in these functions are also weakened. This can lead to poor weight gain, malnutrition, and an increased risk of aspiration pneumonia—a serious condition where food or liquids are inhaled into the lungs due to weak swallowing muscles.
While Type 1 SMA presents with a range of severe challenges, early diagnosis through newborn screening and the availability of advanced treatments have significantly improved the prognosis for many of these children. However, even with treatment, children with Type 1 SMA often require ongoing medical support to manage symptoms and maintain quality of life.
Type 2 (Dubowitz Disease)
Now, moving on to Type 2 SMA, also known as Dubowitz disease, which is considered a mild to severe form of SMA. Children with Type 2 SMA typically have three or more copies of the SMN2 gene, which results in a milder disease course compared to Type 1. Symptoms of Type 2 SMA usually begin to manifest between six and 18 months of age, often when motor milestones such as sitting, crawling, and walking are expected to develop.
Importantly, the lifespan of children with Type 2 SMA is generally longer than that of Type 1 patients, often exceeding two years. With the right combination of respiratory support and therapeutic interventions, many children with Type 2 SMA can live well into adolescence and adulthood, with improved quality of life through medical management and physical therapy.
Unlike Type 1 SMA, where the lifespan is typically less than two years without respiratory support, children with Type 2 SMA can achieve important motor milestones, such as being able to sit unassisted. However, they are generally unable to walk independently, which distinguishes Type 2 as an intermediate form of spinal muscular atrophy. While these milestones are often delayed compared to typically developing children, they still represent significant progress for individuals with Type 2 SMA.
In addition to delayed motor development, Type 2 SMA often causes postural hand tremors and progressive weakness, particularly in the proximal leg muscles. This weakness affects the muscles closest to the body's core, making it difficult for children to stand or walk without assistance. Over time, the weakness in the legs becomes more pronounced, leading to increased reliance on mobility aids such as wheelchairs.
One common complication in children with Type 2 SMA is the development of scoliosis, a curvature of the spine that occurs as a result of weakened muscles that can no longer support proper posture. Scoliosis can progress over time and may require orthopedic intervention or surgical correction to improve the child’s quality of life and prevent further complications with breathing or sitting.
The severity of symptoms in Type 2 SMA can vary widely. Some children may experience respiratory difficulties, requiring non-invasive ventilation to assist with breathing, while others may maintain stable respiratory function for longer periods. Over time, muscle weakness tends to progress, and affected individuals may lose some of the motor abilities they initially developed.
Type 3 (Kugelberg-Welander Disease)
Type 3 SMA, also known as Kugelberg-Welander disease, children experience less severe symptoms compared to Types 1 and 2. The onset of symptoms typically occurs later, usually between 18 months and three years of age. Unlike children with Type 1 and Type 2 SMA, those with Type 3 can often walk independently for a period of time. However, this ability may gradually decline as they age due to progressive muscle weakness.
As we see across the spectrum of SMA types, the age of symptom onset becomes progressively later with each type. In Type 1, symptoms manifest very early, often within the first few months of life. For Type 2, symptoms typically appear between 6 and 18 months. By the time we reach Type 3, symptoms do not usually present until toddlerhood or early childhood. This later onset is associated with a milder disease progression, though muscle weakness, particularly in the legs, continues to worsen over time.
Children with Type 3 SMA generally retain the ability to walk unassisted at some point in their lives, distinguishing them from those with Type 1 and Type 2. However, they often present with progressive proximal weakness, especially in the legs, more so than in the arms. Over time, this leg weakness may necessitate the use of a wheelchair, especially as the child grows older and walking becomes more difficult.
In many ways, Type 3 SMA resembles muscular dystrophy, given the gradual loss of motor function and progressive muscle weakness. While the disease progression is slower than in Type 1 and Type 2, the ongoing weakening of the leg muscles can still significantly impact mobility and quality of life.
Type 4 (Adult SMA)
Lastly, Type 4 SMA is the adult form of spinal muscular atrophy. This form typically begins in adulthood, often after the age of 35, and is characterized by a slow progression of symptoms. Because the disease develops so gradually, many adults do not even realize they have SMA until years after the initial symptoms appear. Unlike the earlier-onset types of SMA, Type 4 is generally milder, though it still involves muscle weakness that worsens over time.
One notable difference in Type 4 SMA is the absence of severe breathing difficulties that are more commonly seen in infants with Type 1 SMA. However, breathing issues can still develop in adults, albeit to a lesser extent. Problems may include weak or underdeveloped lungs, shortness of breath, and shallow breathing, particularly while sleeping. Some adults may also experience stomach breathing, a term used to describe the reliance on abdominal muscles rather than the diaphragm for breathing. While no one actually breathes "on their stomach," this phrase is often used in reference to SMA, indicating a change in breathing mechanics due to weakened respiratory muscles.
Though Type 4 SMA is the least severe form of the disease, its slow progression can still impact daily activities, especially as muscle weakness in the legs and arms becomes more noticeable with age. Early diagnosis and medical intervention can help manage symptoms and maintain mobility for as long as possible.
Congenital SMA
Congenital SMA, also referred to as Type 0 SMA, is the most severe and rare form of SMA. This type can be identified in utero and is characterized by profound muscle weakness and hypotonia (low muscle tone) at birth. In many cases, there may be a history of decreased fetal movement during pregnancy, which can signal early signs of muscle degeneration before birth. Due to this lack of movement in the womb, infants with congenital SMA are often born with joint contractures (stiffness in joints due to restricted movement) or even broken bones as a result of the fragility of their muscles and skeletal structure.
In addition to the musculoskeletal issues, infants with congenital SMA frequently experience severe respiratory compromise from birth. The muscles responsible for breathing are significantly weakened, leading to life-threatening breathing difficulties. Congenital SMA also carries a higher incidence of heart defects, which can be detected either in utero via prenatal screenings or shortly after birth. These heart issues further complicate the infant’s health and contribute to the overall poor prognosis for survival.
Sadly, infants diagnosed with congenital SMA typically have a very limited lifespan, rarely surviving beyond six months of age without intensive medical intervention. The combination of respiratory failure, feeding difficulties, and other complications makes this type of SMA particularly challenging to manage.
Studies have also shown that seizures are frequently seen in infants with Type 0 SMA. These seizures are often linked to hypoxic-ischemic encephalopathy (HIE), a condition caused by oxygen deprivation to the brain during or shortly after birth. This birth asphyxia exacerbates the neurological damage, further complicating the infant's overall condition and contributing to poor survival outcomes.
While congenital SMA remains rare, it underscores the importance of early detection and the critical need for advanced medical interventions in severe cases. Unfortunately, even with early diagnosis, the severity of Type 0 SMA limits the options for treatment, and the focus is often on providing palliative care to manage symptoms and improve comfort.
Breathing Difficulties
As we have learned, SMA primarily affects the muscles, including those between the ribs, which are essential for normal breathing. In children with SMA, the intercostal muscles (the muscles between the ribs) often don’t function properly due to weakness, but the diaphragm typically remains unaffected. As a result, the chest wall does not expand as it normally should during breathing. Instead, the diaphragm pulls the ribcage down, causing the stomach area to expand rather than the chest. This gives the appearance that the child is "breathing from their stomach," a phenomenon often referred to as stomach breathing in SMA.
While this type of breathing may look unusual, it is the body’s way of compensating for the weakened chest muscles. The term "terminal stomach breathing" is sometimes used to describe this characteristic, reflecting how the diaphragm takes over the work of breathing when the chest wall muscles are compromised.
Feeding Difficulties
Another common symptom of SMA is feeding difficulties, which arise from the muscle weakness that extends to the muscles involved in sucking and swallowing. This weakness makes it challenging for children to eat or drink properly, leading to potential complications such as poor weight gain, malnutrition, and an increased risk of aspiration—where food or liquid accidentally enters the lungs instead of the stomach. Aspiration can further complicate the child's condition by increasing the risk of respiratory infections, including aspiration pneumonia.
Due to the difficulty with swallowing, specialized interventions may be required to ensure children with SMA receive the nutrition and calories they need for healthy growth. For younger children or those with more severe muscle weakness, feeding tubes may be necessary to bypass the challenges of oral feeding. In some cases, modified diets, such as thicker liquids or pureed foods, can help reduce the risk of choking or aspiration during meals.
For older children who can manage some oral intake, cutting food into smaller pieces or offering softer textures can make it easier for them to chew and swallow, reducing the risk of choking. Swallowing specialists and physical therapists can also work with children to develop techniques for safer eating and drinking. These professionals may use exercises to strengthen the swallowing muscles and help children learn adaptive strategies for safer meals.
However, if these modifications are not effective and the child continues to struggle with eating and drinking safely, a feeding tube may be necessary to ensure proper nutrition and prevent further complications related to poor intake. This step can be crucial for maintaining the child's overall health and preventing malnutrition.
Muscle Weakness
In SMA, muscle weakness typically begins in the shoulder and leg muscles, which are among the most affected areas when the condition is diagnosed in infancy, around age one. In many cases, the muscles in the lower limbs are impacted first, leading to difficulty with basic motor functions such as sitting or walking. This can significantly delay a child’s motor development milestones—one of the early signs that parents may notice. When a baby with SMA isn't meeting important milestones, such as being able to sit up or crawl, parents often become concerned and seek medical evaluation.
In addition to lower limb weakness, infants with SMA may show signs of poor neck and head control, which further impairs their ability to achieve motor milestones. The inability to control the head or maintain posture is a common observation, especially in children with Type 1 or Type 2 SMA.
Unfortunately, muscle weakness in SMA tends to worsen over time. As the disease progresses, the muscles become increasingly weaker, leading to a gradual decline in motor function. Due to the progressive nature of the condition, some children who are able to walk during childhood may lose this ability as they get older. This deterioration of muscle strength can eventually lead to the need for mobility aids, such as wheelchairs, as walking becomes more difficult or impossible.
The loss of motor function can be emotionally and physically challenging for both the child and their family. As the disease advances, maintaining mobility and independence becomes more difficult, emphasizing the need for early intervention and therapies that can slow the progression of the disease and support muscle function for as long as possible.
Scoliosis
Scoliosis, or the irregular curvature of the spine, is a common complication in children with SMA. This condition develops because the muscles that support the spine are too weak to maintain proper alignment, causing the spine to curve abnormally over time. Without sufficient muscle strength to keep the spine in place, the curvature can become progressively worse, especially as the child grows.
Scoliosis not only affects a child's posture, but it can also lead to severe pain, discomfort, and even numbness in some cases. As the curvature worsens, it can place pressure on the surrounding muscles, nerves, and internal organs, potentially affecting breathing and mobility. In severe cases, scoliosis may require orthopedic intervention, such as bracing or surgical correction, to prevent further complications and improve the child's quality of life. Early detection and management of scoliosis in children with SMA are critical to minimizing its impact on the child's mobility and overall well-being.
Unique Features of SMA Patients
In addition, severe cases of scoliosis can lead to breathing difficulties, as the curvature of the spine may compress the lungs and restrict their expansion. Children with scoliosis often display physical signs such as uneven shoulders, a curved spine, and uneven hips. As mentioned earlier in the presentation, the bell-shaped chest is a unique feature seen in many patients with SMA, and it can be clearly observed in the photo of the baby. This characteristic chest shape occurs because these children rely almost exclusively on their diaphragm for breathing, as the weakened chest muscles are unable to expand properly.
When the diaphragm is overused for breathing, the chest muscles remain underdeveloped, which prevents the chest from expanding in a normal, rounded fashion. This leads to the bell-shaped chest, where the chest is wider at the bottom and narrower at the top, giving the appearance of an inverted bell. In a healthy individual, the rib cage expands evenly during breathing, but in children with SMA, the chest appears sunken as the rib cage pulls inward, and the sternum (the bone in the middle of the chest) may become depressed or pushed inward. This abnormal development further contributes to the respiratory challenges these children face.
Another physical characteristic seen in SMA patients, particularly those who rely on non-invasive ventilation (NIV), is a flattened face. Prolonged use of ventilation masks can gradually alter the shape of the face, as the constant pressure from the mask flattens the bones and soft tissues, especially around the cheeks and nose. This facial flattening is more pronounced in SMA patients due to their long-term reliance on NIV, often beginning from a very young age.
Many children with SMA begin using non-invasive ventilation early in life and continue to rely on it as they grow. During illness, they may need to use NIV continuously throughout the day, with only short breaks to relieve pressure on their face. These breaks help prevent the worsening of the facial flattening while still supporting their respiratory needs.
Another notable feature of SMA patients is their muffled voice quality. Due to decreased lung volumes and weakened respiratory muscles, it becomes difficult for them to phonate or produce clear sounds. Adequate airflow past the vocal cords is essential for strong, clear speech, but the weakened muscles in SMA patients limit this airflow, resulting in a muffled voice. The reduced lung capacity makes it challenging for them to generate the necessary force to project their voice, further contributing to the muffled sound.
One helpful tool we have utilized at our hospital is a Speak X, a sticker microphone that attaches to the noninvasive ventilation mask. This device has been particularly beneficial for our SMA patients who struggle with a muffled voice. The positive pressure from the ventilation mask, combined with their already reduced vocal volume, makes it difficult to understand them clearly. The Speak X microphone allows them to phonate more effectively by amplifying their voice through the mask.
The microphone picks up their voice and transmits it to a receiver outside the mask, where we, as caregivers, can hear them more clearly through a connected external speaker or microphone. While their voice is still somewhat muffled, the Speak X significantly improves our ability to understand what they are saying, whether they are trying to express a need or communicate with family and medical staff.
Unfortunately, to my knowledge, these Speak X microphones are not yet available for home use, but they have been a valuable tool in the hospital setting, enhancing communication between SMA patients and their caregivers.
Respiratory Infections
Frequent respiratory infections are a common symptom of SMA, and respiratory complications are the leading cause of morbidity and mortality in patients with this condition. The respiratory muscle weakness associated with SMA leads to an impaired ability to cough, making it difficult to clear mucus and debris from the airways. This increases the risk of recurrent respiratory tract infections, including pneumonia, which can eventually progress to respiratory failure if left untreated.
The weakened respiratory muscles, combined with breathing difficulties inherent to SMA, make patients—particularly infants and young children with early-onset forms—highly susceptible to infections. The inability to effectively clear the lungs through coughing means that bacteria and viruses can more easily take hold, leading to severe respiratory infections.
For infants diagnosed with early-onset SMA, these infections are particularly dangerous and are often the reason why many do not survive beyond a few months or years. Their already compromised ability to breathe makes it exceedingly difficult for them to cope with the added strain of a respiratory infection. When a severe respiratory infection develops, the additional burden on their already weak respiratory system can be overwhelming, often leading to respiratory failure or other life-threatening complications.
The impact of these infections highlights the critical need for proactive respiratory management in SMA patients, including the use of non-invasive ventilation, airway clearance techniques, and regular monitoring to prevent infections and manage them quickly if they do occur.
Common Respiratory Symptoms in Children With SMA
Common respiratory symptoms in children with SMA include chest wall underdevelopment and lung underdevelopment, which contribute to an impaired cough. This impaired cough makes it difficult for the child to clear secretions from the lower airways, resulting in poor secretion clearance. As a result, the respiratory therapist plays a key role in pulmonary toileting, utilizing techniques and equipment to help these children manage their airway secretions more effectively.
Children with SMA are also prone to recurrent respiratory infections, which further exacerbate muscle weakness and compromise the integrity of the lung parenchyma (the functional tissue of the lungs). Viral respiratory infections—such as those caused by COVID-19, rhinovirus, enterovirus, or parainfluenza—can be especially severe in SMA patients, as their already weakened respiratory muscles struggle to fight off the infection.
Aspiration problems are another common complication in SMA. Swallowing difficulties often lead to food or liquids entering the airways, which can result in aspiration pneumonia. This poses an additional risk to the respiratory health of these children, who are already vulnerable to infections.
Hypoventilation, or shallow breathing, is also common in SMA patients due to their inability to take deep breaths. This can lead to sleep problems, as their breathing may become even more shallow while asleep, contributing to sleep-disordered breathing. In such cases, families may consider having a sleep study performed to assess the child's breathing patterns during sleep. This is often requested by the family or recommended by the pulmonary care team to gain further insights into how best to manage the child's respiratory challenges.
Treatment Options for SMA
Now, let's discuss how we can potentially treat SMA. While there is currently no cure for SMA, three FDA-approved drugs have been developed to treat the condition: Spinraza, Zolgensma, and Evrysdi. These treatments have been groundbreaking, but as you can see, they come at a high cost, and the prices can be staggering.
The first drug to be approved was Spinraza, which received FDA approval in December 2016 for the treatment of all forms of SMA. Spinraza is priced around $625,000 to $750,000 for the first year of treatment. After that, the cost is reduced to approximately $375,000 annually, which is still a significant financial burden, considering that most patients will require lifelong treatment.
Despite its cost, Spinraza has proven to be effective, with around 40% of patients treated with the drug achieving improvements in motor skills milestones. In contrast, none of the control group patients in clinical trials showed significant improvement. Spinraza works by being injected into the cerebrospinal fluid surrounding the spinal cord, where it helps increase the production of functional SMN protein, which is critical for motor neuron survival.
As a long-term treatment, Spinraza has dramatically changed the natural history of SMA, especially in Type 1 and later-onset SMA (Types 2 and 3). In key randomized controlled trials, Spinraza has shown significant improvements in motor function and survival rates in patients with early-onset SMA (Type 1) and later-onset forms (Types 2 and 3). These results offer hope for many families facing the challenges of SMA, as patients can now experience improved motor function and extended survival through early and consistent treatment with Spinraza.
Spinraza has shown greater benefits when treatment is started early in life, with significant improvements in motor function and survival rates for infants and young children. However, even older children—up to 15 years of age—have experienced clinically meaningful improvements in motor function, although the benefits are typically more pronounced in those who begin treatment earlier.
How does Spinraza work? It is administered intrathecally, meaning it is injected directly into the cerebrospinal fluid surrounding the spinal cord, which allows the medication to reach the motor neurons more effectively. The treatment protocol begins with an initiation phase involving four loading doses in the first year. This initiation phase is the most expensive, as the first three doses are administered 14 days apart, with the fourth dose given 30 days after the third. After these four initial doses, a maintenance dose is required every four months to continue treatment.
Spinraza works by binding to a specific sequence downstream of exon 7 on the SMN2 gene—which, as we discussed earlier in the presentation, is crucial for increasing the production of functional SMN protein. In patients with SMA, only about 10% of the SMN2 gene produces properly spliced SMN protein. By targeting exon 7, Spinraza helps the body produce more full-length, functional SMN protein, which is essential for motor neuron survival and improved motor function. This increase in SMN protein helps slow the progression of muscle weakness and supports better outcomes for individuals with SMA.
Spinraza binds to SMN2, allowing the gene to increase the production of functional SMN protein, which is critical for improving motor neuron survival and function in patients with SMA. While Spinraza has significant benefits, it is important to note that, though rare, there are some potential risks associated with its administration.
One potential risk is an increased risk of bleeding. Complications involving bleeding have been observed in patients receiving intrathecal medications like Spinraza. Because of this risk, blood tests are routinely performed before starting treatment and prior to each subsequent dose to monitor for any abnormalities in clotting or blood health. These tests help ensure that the patient is not at elevated risk for bleeding complications during treatment.
Similarly, there is also an increased risk of kidney damage, which has been reported with the administration of medications similar to Spinraza. To mitigate this risk, kidney function tests are also performed regularly before treatment and prior to each dose. These tests are crucial for monitoring kidney health and preventing any potential complications related to kidney function during the course of treatment.
By closely monitoring both blood health and kidney function, healthcare providers can help ensure the safety of patients receiving Spinraza while maximizing the treatment's benefits. Before each dose of Spinraza, a urine test should be obtained to monitor kidney function and detect any signs of potential damage. In addition to the risks of bleeding and kidney complications, there are several common side effects associated with Spinraza. These include lower respiratory infections, fevers, constipation, headaches, vomiting, back pain, and post-lumbar puncture syndrome. As healthcare providers, it is crucial to monitor these side effects and remain vigilant about the potential risks of bleeding and kidney damage.
Zolgensma is a gene replacement therapy specifically designed for individuals with SMA. In SMA patients, the SMN2 gene serves as the primary source of SMN protein production, but it only generates around 10% of the functional SMN protein needed. Zolgensma works by delivering a new, working SMN1 gene directly to the body’s cells, effectively replacing the function of the missing or defective SMN1 gene. This is a major breakthrough because it allows the cells—particularly the motor neuron cells—to begin producing the SMN protein needed to maintain motor function and prevent muscle weakness.
Approved by the FDA in 2019, Zolgensma represents a significant advancement in the treatment of SMA. As a one-time gene replacement therapy, it has the potential to dramatically change the course of the disease by addressing the root cause of SMA at the genetic level, allowing for improved motor function and a better quality of life for those with SMA.
Zolgensma costs approximately $2.1 million for a single-use treatment, making it one of the most expensive drugs in the world. The high cost of this gene therapy is due to the expensive research and development processes involved, as well as the complexity and cost of manufacturing gene therapies. Developing gene therapy is significantly more expensive than traditional drugs due to the specialized technology required to create these treatments, including the use of viral vectors and genetic engineering.
Unlike Spinraza, which requires lifelong administration, Zolgensma is a one-time dose delivered through intravenous (IV) infusion. The drug works by using a viral vector to deliver a functional human SMN1 gene directly to the motor neurons, effectively replacing the defective or missing SMN1 gene that causes SMA.
Zolgensma is FDA-approved for children under the age of two years with SMA Type 1, the most severe form of the disease. However, it comes with some serious potential side effects. One of the primary risks is an increase in liver enzyme levels, which can lead to acute liver injury or, in severe cases, acute liver failure, a condition that could be fatal. Due to this risk, patients receiving Zolgensma are given an oral corticosteroid before and after the infusion to help protect the liver and manage inflammation. In addition, patients will undergo regular blood tests to monitor their liver function and ensure any potential liver issues are detected early.
Another potential complication is decreased platelet counts, which can increase the risk of bleeding and bruising. Parents and caregivers are advised to seek immediate medical attention if the patient experiences any unexpected bleeding or bruising following the infusion. Lastly, like many other medications, including Spinraza, vomiting is a common side effect of Zolgensma.
Lastly, Evrysdi (risdiplam) was FDA-approved in 2020, making it the first oral drug treatment for SMA. The cost of Evrysdi is approximately $27,884 per year, making it more affordable compared to other SMA treatments like Spinraza and Zolgensma. Evrysdi is a small molecule SMN2 splicing modifier designed to treat the underlying cause of SMA by increasing the production of full-length SMN protein, which is essential for maintaining motor neuron function. It is approved for SMA patients who are two months of age and older, offering a broader age range for treatment compared to other therapies.
Like all medications, Evrysdi has its side effects, and these differ slightly based on the type of SMA being treated:
- In later-onset SMA, common side effects include fever, diarrhea, and rash.
- In infantile-onset SMA, the side effects also include fever, diarrhea, and rash, but additional symptoms such as runny nose, sneezing, sore throat (signs of upper respiratory infections), lung infections (lower respiratory infections), constipation, vomiting, and cough are more frequently observed.
The introduction of Evrysdi as an oral medication has provided a more convenient treatment option for many SMA patients, especially those who may find regular intrathecal injections or IV infusions challenging.
The Role of a Respiratory Therapist With SMA Patients
- Assess patient
- Discuss with parents/caregivers baseline treatments when the patient is well
- Suggested therapies:
- Bronchodilators and hypertonic saline
- Cough assist
- CPT/Vest therapy and postural drainage
- Some therapy schedules may be every 2 hours to prevent plugging and intubation
Previously, patients with SMA had limited treatment options, and their care was often restricted to managing symptoms rather than addressing the underlying cause of the disease. However, with recent medical advances, patients now have access to a variety of treatments that can significantly improve their quality of life and help manage the comorbidities associated with SMA, such as respiratory issues. This is where the role of the respiratory therapist becomes essential.
As medical treatments like Spinraza, Zolgensma, and Evrysdi have become available, respiratory therapists play a critical role in supporting patients' respiratory health and helping manage complications such as impaired cough, recurrent infections, and respiratory muscle weakness. Their expertise in pulmonary toileting, ventilatory support, and airway clearance techniques can make a substantial difference in the long-term health and survival of SMA patients.
As learning and research in the field of SMA continue to evolve, the role of respiratory therapists (RTs) has become increasingly important in providing early and aggressive respiratory therapies for these patients. Implementing these therapies as soon as possible is critical for managing respiratory distress and preventing complications.
The first step for an RT when an SMA patient is admitted with any type of respiratory distress is to assess the patient immediately. A key part of this assessment involves communicating with the parents or caregivers to understand the patient’s baseline respiratory status when they are well. This provides valuable information for establishing a plan of care and allows the healthcare team to better understand the degree of deterioration when the patient is sick.
Some of the respiratory therapies commonly administered by RTs for SMA patients include:
- Bronchodilators: Medications like albuterol or levalbuterol (Xopenex) are used to help open the airways, making breathing easier for the patient.
- Hypertonic saline nebulizers: These are often given to help thin mucus, making it easier for the patient to clear secretions from their airways.
- Pulmozyme (dornase alfa): This is another medication frequently used in SMA patients to break down thick mucus in the lungs, improving airway clearance and reducing the risk of respiratory infections.
By employing these therapies, RTs can help manage respiratory complications and improve the overall pulmonary health of patients with SMA. Maintaining open communication with caregivers about the patient’s home care regimen is vital for ensuring that treatments are tailored to the individual needs of each patient.
Cough Assist Device
One of the key respiratory treatments for SMA patients is the use of a cough assist device, also known as an insufflator-exsufflator machine. This non-invasive device helps clear the lungs by mimicking the action of a natural cough. The machine works by blowing air into the lungs and then quickly sucking it out, helping to expel mucus that the patient would otherwise struggle to clear on their own. The goal of the cough assist is to increase the amount of mucus expelled, reducing the risk of respiratory infections and other complications.
Chest Physiotherapy (CPT)
Next, we have chest physiotherapy, commonly referred to as CPT therapy. This therapy involves gently clapping on the chest wall to help loosen mucus. Alternatively, a pneumatic percussor, a vibrating device, can be used to help loosen mucus by using vibration and gravity to encourage the movement of secretions from the lower airways to the upper airways, which can then trigger a cough. For some SMA patients, this therapy may be required daily, while for others, it may only be necessary during illness, depending on their baseline respiratory status.
Vest Therapy
Another effective tool is vest therapy, which involves the use of a wearable device that vibrates to help loosen and move mucus. The vest connects to an air pulse generator that inflates and deflates the vest around the patient’s chest. This vibration helps dislodge mucus so it can be coughed out more easily. Vest therapy sessions typically last anywhere from 10 to 30 minutes and can be customized with different pressures and frequencies (measured in hertz). The therapy is most effective when done in the reverse Trendelenburg position, which uses gravity to help move mucus from the lower airways to the upper airways, where it can be suctioned or expelled with the help of the cough assist device. For many SMA patients, these therapies can be scheduled as frequently as every 2 hours to prevent airway plugging and reduce the risk of requiring intubation.
Invasive Ventilation in SMA Patients
While invasive ventilation is an option for SMA patients, it is typically considered a last resort. Invasive ventilation involves inserting a breathing tube into the airway and attaching it to a mechanical ventilator, which assists or fully controls breathing. Long-term invasive ventilation usually requires a tracheostomy, where a doctor makes a small incision in the neck and inserts a tube directly into the trachea. This procedure is more common as SMA patients age and their disease progresses, particularly when non-invasive ventilation is no longer sufficient.
Many individuals with SMA, especially those with Type 1 (non-sitters), may require more breathing support as they grow older and their respiratory muscles weaken. However, many SMA patients can successfully manage their respiratory needs with non-invasive ventilation, using breathing support primarily during sleep or when they are sick. The decision to move from non-invasive to invasive ventilation should be carefully discussed with healthcare providers, as it is a significant step in the care of an SMA patient. These decisions are based on the individual’s needs and the progression of the disease, and it's crucial for parents and caregivers to have open discussions with their medical team as early as possible after diagnosis.
NIV and the SMA Patient
- BIPAP
- Pushes air in and opens lungs through positive pressure ventilation
- SMA type 2 or 3 may only need support while sleeping or when ill
- Cure SMA: if the child who already uses Bipap is sick, they will need to use Bipap during all sleep, including naps, and sometimes while awake
- OSA
- Hypoventilation
Non-invasive ventilation (NIV) is very common for patients with SMA, and one of the most widely used forms is BiPAP (Bilevel Positive Airway Pressure). At our hospital, BiPAP is the primary non-invasive ventilation option for SMA patients. This type of ventilation is particularly beneficial for individuals with SMA because the intercostal muscles—the muscles located between the ribs that help the chest expand and allow the lungs to fill with air—are often significantly weakened by the disease.
Due to the weakness of these intercostal muscles, SMA patients struggle to maintain a normal breathing pattern. A BiPAP machine helps facilitate breathing by using positive pressure to push air into the lungs, supporting their weakened respiratory muscles. The machine provides two different levels of pressure:
- Higher pressure during inhalation, which allows the patient to take in a larger volume of air.
- Lower pressure during exhalation, which helps ease the breathing process by reducing the resistance as the patient breathes out.
BiPAP machines are designed to sense the normal breathing cycle and synchronize with the patient's natural rhythm. This is especially important for SMA patients, as they often experience dysynchrony between their breathing efforts and the need for support when they are sick or in respiratory distress. The synchronization capability of the BiPAP helps ensure the machine works in tandem with the patient’s own breathing efforts, making breathing more comfortable and effective.
Additionally, a BiPAP machine plays a vital role in ensuring patients receive adequate air during deep sleep. SMA patients may not breathe as effectively while sleeping due to their weakened respiratory muscles, so the BiPAP helps maintain proper ventilation and oxygen levels throughout the night.
Because SMA patients are typically shallow breathers, many patients with Type 2 or Type 3 SMA can manage with BiPAP and only require this support while sleeping or during illness. Even something as minor as the common cold can significantly weaken breathing in children with SMA. According to Cure SMA, if a child who already uses BiPAP contracts a cold, they will need to use the machine during all sleep periods—including daytime naps, nighttime sleep, and anytime they doze off. This ensures that their lungs stay open and prevents derecruitment (collapse of the small airways). In some cases, BiPAP may even be needed while the child is awake, depending on the severity of their symptoms.
For Type 3 SMA patients, both children and adults, frequent checkups are essential to monitor for any breathing difficulties that may not be immediately noticeable. These can include conditions such as obstructive sleep apnea and hypoventilation (shallow breathing). In these cases, a sleep study may be recommended to ensure that the patient is receiving the appropriate level of BiPAP support while sleeping, especially when at home. Proper BiPAP use during all types of sleep can greatly benefit SMA patients, helping them maintain adequate ventilation and oxygenation.
However, NIV does have some potential side effects. One of the most common issues is facial indentation or skin breakdown from the mask, which occurs due to the tightness required to create a proper seal on the face. To protect against skin damage, we can use products like Mepilex or LiquiCell—skin protection materials that are applied to the patient’s face to prevent irritation and breakdown from prolonged mask use. In some cases, a different mask size or type may be needed to improve comfort and fit.
We have a plethora of options for comfort, including various mask sizes and fittings to ensure a proper and comfortable fit for each patient, from children to adults. Ensuring the right fit is essential for effective BiPAP therapy.
It is also important to note that patients should never eat or drink while using the BiPAP machine. Doing so increases the risk of aspiration, where food or beverages can be inhaled into the lungs, which could lead to aspiration pneumonia—a serious complication we want to avoid.
In addition to this, there are other potential risks and side effects associated with BiPAP use, including:
- Dry mouth: This can occur due to the constant flow of air.
- Eye irritation: Air leaks around the mask may cause discomfort or dryness in the eyes.
- Mask leaks: Leaks from the mask can reduce the air pressure being delivered, compromising the machine’s ability to keep the lungs open. It is essential to ensure that the leak is appropriate and that the mask is properly fitted to maintain effective therapy.
- Sinus pain or congestion: The positive air pressure can sometimes cause discomfort in the sinuses.
- Mild stomach bloating: This can happen if air is inadvertently swallowed, causing it to accumulate in the stomach.
By addressing these issues, we can help ensure the BiPAP machine works effectively and comfortably for each patient, preventing complications while providing the necessary respiratory support.
Respiratory Care Options for Desaturations
When managing desaturations in SMA patients, it's crucial to remember that oxygen supplementation should not be provided without the concurrent use of BiPAP or another form of non-invasive ventilation. As RTs, our focus should always be on lung expansion. If the patient is desaturating, it is important to assess the situation thoroughly and choose the most effective course of action. This often includes performing a cough assist treatment, followed by suctioning to clear the airways. Additionally, evaluating whether the patient requires airway pressure release ventilation (APRV) or other forms of respiratory support is key to maintaining adequate oxygenation.
Our goal is to choose the most effective interventions while providing the patient with the best breathing support possible. By taking a proactive approach, we can help prevent further desaturations and ensure the patient’s lungs stay as open and clear as possible.
SMA is one of the most common rare diseases, and although there is no cure, there are currently three FDA-approved drugs available to help manage its symptoms. The treatment of SMA requires multidisciplinary management, addressing not only the neurological aspects but also the respiratory complications that arise. The role of the respiratory therapist is critical in providing ongoing care, including pulmonary toileting, airway clearance, and ventilatory support, all of which are vital for the survival and quality of life of SMA patients.
Questions and Answers
For a respiratory therapist, what are the key considerations when transitioning an SMA patient from the hospital to home care in terms of equipment needs, caregiver training, and setting them up for success?
It is crucial to ensure that the BiPAP mask fits properly and there’s minimal leakage to maintain lung expansion. Many SMA patients rely on BiPAP for breathing support. Proper caregiver training on respiratory toileting, including the use of bronchodilators, cough assist, and suctioning, is essential. We also emphasize how to handle emergency situations, such as a mucus plug or respiratory distress, and when to use a bag mask.
Most families are well-versed in the condition, often participating in support groups for emotional and practical support. For some, even small things like customizing vest therapy devices can brighten their day, as these patients spend a significant amount of time on pulmonary care.
Can you tell us more about the Speak X device you mentioned earlier?
The Speak X is a small microphone sticker that attaches to the patient’s non-invasive mask. It helps amplify their voice, making it easier for caregivers to hear, despite the muffled effect caused by the mask. While it doesn’t eliminate the muffling completely, it allows patients to communicate without removing the mask, which helps avoid derecruiting their lungs. The device is especially helpful for teens who want to communicate more freely.
How important is communication for SMA patients, especially teens?
Communication is vital, especially for teens who want to express themselves socially. Devices like the Speak X help them talk more easily without compromising their respiratory support, reducing frustration and improving their ability to express needs or interests.
References
https://www.cdc.gov/
Mercuri, E., Finkel, R. S., Muntoni, F., Wirth, B., Montes, J., Main, M., Mazzone, E. S., Vitale, M., Snyder, B., Quijano-Roy, S., Bertini, E., Davis, R. H., Meyer, O. H., Simonds, A. K., Schroth, M. K., Graham, R. J., Kirschner, J., Iannaccone, S. T., Crawford, T. O., Woods, S., … SMA Care Group (2018). Diagnosis and management of spinal muscular atrophy: Part 1: Recommendations for diagnosis, rehabilitation, orthopedic and nutritional care. Neuromuscular disorders: NMD, 28(2), 103–115.
Nemours Children’s Hospital. (2023). Spinal Muscular Atrophy (SMA.https://kidshealth.org/en/parents/sma.html
Office of the Commissioner. (2020, August 7). FDA approves oral treatment for spinal muscular atrophy. U.S. Food And Drug Administration. https://www.fda.gov/news-events/press-announcements/fda-approves-oral-treatment-spinal-muscular-atrophy
Respiratory therapy for SMA (2024). mySMAteam. https://www.mysmateam.com
Roland, J. (2022, February 28). What are the signs of spinal muscular atrophy? Healthline. https://www.healthline.com/health/signs-of-spinal-muscular-atrophy#symptoms
Citation
Boussalham, N. (2024). SMA in Pediatrics (Spinal Muscular Atrophy), Continued.com - Respiratory Therapy, Article 243. Available at www.continued.com/respiratory-therapy
Sep 11, 2024
1 CE HourBronchopulmonary dysplasia (BPD) Historical and Scientific Update
Katlyn Burr, MSM-HCA, RRT, RRT-NPS, AE-C
Editor’s note: This text-based course is an edited transcript of the webinar, Bronchopulmonary dysplasia (BPD) Historical and Scientific Update, presented by Katlyn Burr, MSM-HCA, RRT, RRT-NPS, AE-C.
It is recommended to download the course handout to supplement this text format.
Learning Outcomes
After this course, participants will be able to:
- Define BPD
- Discuss the historical background and advancement of the definition and disease
- Review best practices to drive the best patient outcomes in BPD patients
The Birth of BPD
The origins of Bronchopulmonary Dysplasia (BPD) can be traced back to the era of President Kennedy. The story begins with the challenges that President Kennedy and his wife, First Lady Jackie Kennedy, faced in starting a family. Before his presidency, the couple endured heartache. Their first pregnancy ended in a miscarriage, and their second, tragically, resulted in the stillbirth of a daughter, Arabella. Despite these losses, they were eventually blessed with two healthy children, Caroline and John. However, one year into Kennedy’s presidency, Jackie became pregnant again. This time, she gave birth prematurely to a son, Patrick, at 34 weeks. Unfortunately, Patrick only survived for 39 hours, succumbing to respiratory distress syndrome and hyaline membrane disease.
That same year, a Canadian doctor made significant strides in neonatology by pioneering the controversial use of a ventilator. His groundbreaking work saved a similarly ill 34-week-old baby, marking a pivotal moment in the history of neonatal care and the development of treatments for conditions like BPD. Unfortunately, American doctors at the time were unable to replicate the success seen elsewhere. When Patrick was born at Otis Air Force Base, it became immediately clear that he was showing signs of respiratory distress and would require urgent intervention. At that time, the available treatments for babies with respiratory distress and hyaline membrane disease were limited. The medical team focused on stabilizing his blood gases, adjusting his blood chemistry as best they could, and administering hyperbaric oxygen. Despite their efforts, these measures were not enough to save Patrick.
When President Kennedy learned about the Canadian doctor who successfully used a ventilator to save a very sick 34-week-old baby, he felt a deep sense of embarrassment. Patrick's death had already sharpened the national focus on neonatal lung disease, a condition responsible for about 20% of all neonatal deaths in the late 1960s and early 1970s. In response, President Kennedy signed into law a significant grant authorizing $265 million over five years for newborn research. This initiative was sponsored by the National Institute of Child Health and Human Development, an organization that Kennedy had established with his sister, Eunice Shriver, a year earlier.
While $265 million was a significant sum at the time, in today’s terms, it equates to about $2.1 billion—a truly remarkable investment in advancing neonatal research, particularly in lung development, to help newborns survive. Sadly, President Kennedy was assassinated three months after Patrick’s birth and death, and he never witnessed the breakthroughs in research and treatments that have since saved countless lives.
Patrick's birth and death did indeed intensify the focus on neonatal lung disease, but other critical developments were also underway. One of the most significant was the discovery of surfactants, which played a pivotal role in the evolution of BPD. In 1957, John Clements became the first researcher to identify a mucoprotein, later known as surfactant, which was crucial for maintaining alveolar stability in animal models.
Avery and Mead, two pioneering researchers, observed that the surface tension of lung extracts from premature infants with hyaline membrane disease was significantly higher than that of similarly sized infants who were dying of non-respiratory causes. This critical finding led them to hypothesize that the increased surface tension and subsequent lung collapse were due to the absence of surfactant in infants weighing less than 1,100 grams. The term Bronchopulmonary Dysplasia (BPD) was later coined to describe this emerging pattern of lung disease in premature infants who were surviving longer, thanks to advances in ventilator care. Today, BPD is recognized as the most common cause of chronic lung disease in infancy. The clinical, radiological, and pathological features of BPD were first detailed over three decades ago.
Before the 1960s and the introduction of the controversial mechanical ventilator, premature infants who developed respiratory distress syndrome often faced two outcomes: they either passed away within their first week of life, as Patrick did, or they survived without significant pulmonary complications. However, with advancements in medical technology and the use of mechanical ventilation, infants who once would have perished are now being supported and given a chance to live. While mechanical ventilation greatly improved the survival rates of these infants, it also led to a new form of lung injury.
Old BPD
In 1967, William Northway first described this new chronic lung disease, known as Bronchopulmonary Dysplasia (BPD). He observed it in a group of premature infants with respiratory distress syndrome who had undergone prolonged ventilation with high oxygen concentrations and high peak inspiratory pressures.
The infants studied had a mean gestational age of 34 weeks and an average weight of 2.4 kilograms. All of them required oxygen 28 days after birth and showed progressive changes on chest radiographs, which were graded according to severity. Pathologic examination of their lung tissues revealed necrotizing bronchiolitis, vascular changes indicative of pulmonary hypertension, infiltration of inflammatory cells, and alternating areas of atelectasis and pulmonary fibrosis. The term "bronchopulmonary dysplasia" was coined to emphasize that both the airways and the lung parenchyma were affected. These abnormalities were attributed to injuries caused by mechanical ventilation and prolonged oxygen exposure. Since Northway’s initial definition in 1967, advancements in medical technology have led to an evolving understanding and redefinition of BPD.
In 1979, Bancalari and colleagues introduced the first revision to Northway's original definition of BPD. Their updated criteria included the need for oxygen at 28 days, chronic changes on a chest X-ray, and the presence of tachypnea with crackles or retractions, though they removed the grading system for chest X-rays. As time passed, it became evident that fewer babies required as much oxygen at 28 days post-birth, prompting another update in 1988. This revision shifted the focus to assessing supplemental oxygen needs at 36 weeks postmenstrual age. However, as medical technology continued to advance, the 1988 definition became less predictive and less useful. With the increased survival rates of extremely low birth weight infants and the broader spectrum of disease severity, new treatment options for respiratory distress have further refined our understanding and management of BPD.
New BPD
The failure to account for gestational age at birth and disease severity led to concerns that the existing definition of BPD was inadequate. In 2000, a review of the definition of BPD and chronic lung disease of infancy in preterm infants was conducted at a workshop hosted by the National Institute of Child Health and Human Development and the National Heart, Lung, and Blood Institute. The consensus from this workshop addressed two key groups of infants: those born at less than 32 weeks estimated gestational age. For infants requiring oxygen at 28 days, they were reassessed at 36 weeks postmenstrual age. Based on this reassessment, infants breathing room air at 36 weeks were classified as having mild BPD, those requiring less than 30% FiO2 were classified as having moderate BPD, and those needing more than 30% FiO2 or positive pressure ventilation were classified as having severe BPD.
Old versus New BPD
It is not until about 32 weeks of gestation that alveoli begin to form, which is a key reason why the definitions of BPD have evolved. The "old" BPD primarily affected older preterm infants who suffered from structural injuries to their lungs. In contrast, "new" BPD involves caring for infants who may not have significant structural damage but instead experience developmental arrest or delays in lung tissue maturation due to their extremely early birth. Despite the evolution of the BPD definition over time, a consensus remains: chronic lung disease develops in preterm infants exposed to oxygen and positive pressure ventilation. BPD cannot occur in term infants; it is a condition exclusive to those born preterm and who require oxygen and positive pressure ventilation.
BPD Definitions
The evolution of BPD definitions reflects our growing understanding of the condition and the advancements in neonatal care over the decades.
- 1967 (Northway): The initial definition of BPD was based on progressive clinical symptoms, radiographic findings, and histological changes. This definition highlighted the physical changes in the lungs that could be observed over time.
- 1988 (Shennan): The definition was refined to focus on the need for supplemental oxygen at 36 weeks postmenstrual age (PMA) as a key criterion, marking a shift toward recognizing the ongoing oxygen dependency as a critical aspect of BPD.
- 2004 (Walsh): A more physiological approach was introduced, defining BPD in infants ≤32 weeks gestational age (GA) at 36 weeks PMA by the requirement for invasive mechanical ventilation (IMV) or continuous positive airway pressure (CPAP). Additional criteria included a PaO₂/FiO₂ ratio ≥0.3 or failure to maintain oxygen saturation ≥90% for 30 minutes following an oxygen reduction test.
- 1979 (Tooley): This definition focused on radiographic abnormalities, identifying abnormal lung findings on a radiograph at 30 days of life as a key indicator. Critical PaO₂ was defined as less than 60 mmHg in room air, and PaCO₂ as less than 45 mmHg, with oxygen dependency at 30 days being a significant marker.
- 2001 (NIH): BPD was categorized based on FiO₂ requirements for 28 or more days. The severity was graded according to the level of oxygen support required: mild BPD was associated with breathing in room air, moderate BPD with FiO₂ less than 0.3, and severe BPD with FiO₂ ≥ 0.3 and/or the need for CPAP or IMV.
- 2018 (NIH): The definition was further refined to apply to infants ≤32 weeks GA with persistent radiographic lung disease who required respiratory support at 36 weeks PMA for three or more days to maintain arterial oxygen saturation between 90-95%. The grading system became more detailed, with specific criteria based on the type and level of respiratory support needed, including considerations for the risk of death.
- 2019 (Jensen): This definition focused on grading BPD in infants less than 32 weeks GA based on the level of respiratory support required at 36 weeks PMA or discharge. The grades ranged from mild, involving nasal cannula flow ≤2 LPM, to severe, requiring invasive mechanical ventilation.
This progression in BPD definitions shows a trend towards more precise and individualized criteria, reflecting the complexities of the condition as we better understand its varied presentations and underlying mechanisms. As neonatal care continues to evolve, the hope is that more preventive and less invasive treatments will be developed, reducing the need for intensive interventions. However, as we push the boundaries of survival for younger and more fragile infants, the necessity for advanced medical technologies, including potentially more invasive options like external wound management or liquid ventilation, may also increase. This duality underscores the ongoing challenge of balancing advancements in care with the needs of an increasingly vulnerable patient population.
BPD Evolvement
The evolution of BPD definitions continued with significant updates in 2018 and 2019. In 2018, the NIH introduced a new grading system, replacing the traditional terms of mild, moderate, and severe BPD with a more nuanced classification of grades I, II, III, and IIIa. This change aimed to provide a more precise characterization of the disease based on the level of respiratory support required by the infant.
In 2019, the grading system was further refined. The NIH removed grade IIIa and focused on grades I, II, and III, specifically for infants born at less than 32 weeks gestational age. This updated system categorizes BPD based on the level of respiratory support required at 36 weeks postmenstrual age or at discharge, whichever occurs first.
- Grade I BPD is assigned to infants who are on nasal cannula flow rates of less than or equal to two liters per minute.
- Grade II BPD applies to those with nasal cannula flow rates greater than two liters per minute, or those who require CPAP or other non-invasive respiratory support.
- Grade III BPD is used for infants who require invasive mechanical ventilation at 36 weeks postmenstrual age or at discharge.
This refined classification system allows for a more detailed understanding of the severity of BPD, which can better guide treatment decisions and provide clearer prognostic information. By categorizing BPD based on specific respiratory needs, clinicians can more accurately assess the level of care required and anticipate potential challenges as these infants continue to develop.
Review of BPD
- Chronic Lung Disease
- Developed in preterm infants who are exposed to:
- Oxygen
- Positive Pressure Ventilation
- Difficult to manage because conventional treatment of symptoms results in the disease
- The premature development of the lung allows for recovery if we provide appropriate intervention
If you recall your anatomy and physiology classes as a respiratory therapy student, you likely had a lecture on fetal lung development. During that course, you might remember learning about the stages of lung development. Around 16 weeks of gestation, the fetus enters the canalicular stage, and by approximately 23 weeks, the development progresses to the saccular stage.
All of these factors must converge for BPD to develop. The disease has always been challenging to manage because the very treatments used to address it can also cause or exacerbate the condition. Additionally, the premature development of the lungs presents its own set of challenges. However, due to the immaturity of these lungs, there is a narrow window in which appropriate interventions can aid recovery without further damaging lung tissue.
BPD occurs when lung development arrests during the late canalicular to saccular stages. The pathology of BPD is characterized by decreased septation and alveolar hypoplasia, leading to the formation of large, simplified alveoli. This abnormality significantly reduces the surface area available for gas exchange, further complicating the condition.
These infants also exhibit dysregulated vasculature, characterized by smooth muscle hyperplasia in their pulmonary vessels and abnormal alveolar capillaries. Additionally, there is increased interstitial fibroproliferation and impaired alveolar septation. The advantage of being born early is that their lung development is still ongoing. Although these infants may not have fully formed alveolar sacs at birth, their lung tissue continues to develop after they are born.
Review of BPD- Lung Development
Remarkably, babies grow approximately 3.3 alveoli per second from birth until they reach the age of one. This means that every moment spent caring for a baby at the bedside during their first year of life, they were developing around three new alveoli every second. These alveoli are the tiny air sacs in the lungs where gas exchange occurs, and their development is crucial for establishing healthy lung function.
This rapid growth does not stop after the first year; it continues at a rate of about one alveolus per second until the age of two. This incredible pace of alveolar development is vital for building the lung’s capacity to exchange oxygen and carbon dioxide efficiently, which is especially critical in premature infants. Premature infants often have underdeveloped lungs, making them more susceptible to conditions like bronchopulmonary dysplasia (BPD).
For these vulnerable infants, receiving protective ventilation strategies, such as gentle ventilation and permissive hypercapnia, can make a significant difference. By minimizing lung injury and promoting a favorable environment for lung development, these interventions help ensure that the new alveoli they rapidly form are healthy. This not only has the potential to reduce the severity of lung disease but also supports better long-term outcomes, including improved lung function and a reduced risk of respiratory complications as they grow.
Understanding the critical period of alveolar development underscores the importance of providing optimal care during the early stages of life, particularly for those born prematurely. It also highlights the potential for targeted interventions to make a lasting impact on the health and well-being of these infants.
Alveolar Multiplication
The theory of alveolar multiplication, which involves the subdivision of terminal units, the formation of primary pulmonary saccules and secondary alveolar crests, and the alveolarization of non-alveolated and partly alveolated airways, is not new. Although the precise mechanisms of alveolar development and the relative importance of these processes are still not fully understood, it is clear that alveolar growth is most rapid in the first years of life and appears to slow down as we age.
Some research suggests that alveolar growth stops by around age eight, while other evidence indicates it may continue until somatic growth ceases. For example, a 2011 study published in the American Journal of Respiratory and Critical Care Medicine examined 100 patients aged 7 to 21 years. The researchers used hyperpolarized helium, which the patients inhaled before undergoing MRI scans. The hyperpolarized gas, acting like a magnet, is aligned in one direction, as you can see in the image on the screen. By analyzing how the gas decayed in the lungs, the researchers could estimate the size of the alveoli. They found that while the size of the alveoli showed very little difference, total lung volume increased significantly, ranging from about one to four liters.
Researchers concluded that if the size of the alveoli remains largely unchanged, the increase in lung size must be due to the growth of new alveoli. This suggests that until we stop growing in height, we likely continue developing alveoli. This is particularly fascinating for those who care for pediatric patients, who are constantly growing.
BPD- CXR Findings
- Coarse, irregular, rope-like, linear densities
- Could represent atelectasis or fibrosis
- Lucent cyst-like foci
- Areas of air-trapping
- Shifting atelectasis
- May be combined with pneumonia
In children with BPD, chest X-rays typically reveal irregular rope-like densities that can resemble atelectasis or fibrosis. These images often show lucent cyst foci and multiple areas of air trapping. When comparing serial X-rays taken on different days, one might observe shifting atelectatic areas within the lungs of these patients. All of these factors, including conditions like pneumonia, can occur simultaneously in a child with BPD.
BPD Prevalence
- 45-68% of VLBW infants diagnosed with BPD
- 80% of infants born 22-24 weeks of gestation are diagnosed with BPD, whereas only 20% of infants at 28 weeks develop BPD
- ~40% of preterm infants born prior to 29 weeks GA
- 11-50% in different countries around the world
- 10,000 births annually in the US with BPD
- 12-39% for preterm babies born before 32 weeks GA
- <1000g babies is 30-50%
- Overall, younger, smaller, less mature babies are at higher risk (Mandell et al., 2019; Clin Perinatol Zhang et al., 2022)
The prevalence of BPD varies widely depending on the definitions used, as you have seen with the different criteria that have evolved over time. The reported prevalence is influenced by factors such as whether the definition of very low birth weight versus extremely low birth weight infants is used and whether all babies are included or only a subset. In 2010, the National Institute of Child Health and Human Development Neonatal Research Network used severity-based and physiologic definitions of BPD and estimated that as many as 68% of very low birth weight infants could be diagnosed with BPD.
In the United States, approximately 10,000 babies born each year will either have or develop Bronchopulmonary Dysplasia (BPD). The risk of developing BPD is directly related to the baby's age, size, and maturity—the younger, smaller, and less mature the infant, the higher the risk of developing BPD. This risk is also closely linked to the severity of the disease.
BPD remains the most expensive morbidity in neonatal intensive care units (NICUs), with an estimated annual economic burden of $1.7 billion in the United States. Caring for these patients in NICUs costs the healthcare system $1.7 billion each year, making the reduction of BPD risk a critical clinical and economic priority in the care of very low birth weight infants.
BPD Impact
These patients face a significant challenge, with mortality rates reaching up to 40%. Additionally, about 25% of infants with moderate to severe BPD develop BPD-associated pulmonary hypertension, a condition linked to even higher rates of mortality and morbidity. The most common causes of death in these patients include recurrent respiratory tract infections, pulmonary heart disease, and pulmonary hypertension.
For those who survive, the challenges do not end there. About 50% of these patients are readmitted within the first year, often due to lower respiratory tract infections. Survivors also face a heightened risk of various complications, including gross motor delays, reactive airway disease, asthma, emphysema, RSV, bronchiolitis, growth delays, language delays, and ongoing cardiopulmonary issues.
Given these severe outcomes, it is crucial to do everything possible to reduce the risk of developing BPD or mitigate its severity in the patients we care for. Early intervention, careful management, and ongoing monitoring are essential to improve long-term outcomes and quality of life for these vulnerable infants.
Predisposing Factors
The development of BPD is influenced by several predisposing factors, especially in infants born prematurely. These infants have underdeveloped lungs and often experience stressors that not only contribute to their premature birth but also play a role in the onset of BPD. These stressors can directly impede lung development or trigger an immune response that worsens the condition.
When the immune response is activated, it leads to an increase in free radicals and inflammatory markers. This reaction causes the body to enter a defensive mode, halting normal developmental processes. The resulting inflammation, swelling, and injury further contribute to the development of BPD.
From a postnatal perspective, premature birth alone is a significant risk factor for BPD. The combination of underdeveloped lungs and the immune responses triggered by various stressors creates a challenging environment for healthy lung development, highlighting the importance of prevention and careful management in reducing the impact of BPD.
Lung immaturity at birth increases the likelihood of developing BPD. Other risk factors include poor nutrition, the need for mechanical ventilation and oxygen, and the development of infection or sepsis shortly after birth. Certain demographic groups are also at higher risk, including male infants, those with low birth weight, white infants, and those with impaired growth for gestational age. A family history of asthma further increases the likelihood of developing BPD.
In addition to underdeveloped lungs, premature babies are often affected by conditions such as chorioamnionitis, sepsis, and pneumonia. These conditions contribute to inflammation and oxidative stress, which increase microvascular permeability and lead to pulmonary edema. Treatment for these symptoms typically involves the use of oxygen, positive pressure ventilation, and sometimes nitric oxide. Unfortunately, while necessary, these interventions can lead to aberrant tissue repair and a slowed rate of alveolarization. For instance, instead of the normal rate of developing 3.3 alveoli per second, this process might slow to one or none, leading to impaired alveolar and vascular development—key factors in the progression of BPD.
The complexity of BPD underscores the need for individualized care and ongoing research to better understand and mitigate the risks associated with this condition.
Maternal Factors
From a maternal standpoint, several factors can significantly contribute to a baby's risk of developing BPD. If the mother smoked during pregnancy, had intrauterine growth restriction, or was diagnosed with preeclampsia, her baby is at an elevated risk for BPD. Additionally, preterm babies, who are often born with low birth weight and underdeveloped organs, are already at a greater risk for developing bronchopulmonary dysplasia due to their premature status. These maternal and neonatal factors combined can increase the vulnerability of these infants to BPD and related complications.
Pre-Term Delivery
The same increased risk applies to babies with lower gestational ages. Unfortunately, in our efforts to support these extremely low and very low birth weight infants, as well as those born at reduced gestational ages, we often rely on mechanical ventilation and supplemental oxygen. While these interventions are crucial for sustaining life, they can inadvertently contribute to the development of BPD, further compounding the problem. The very treatments that are necessary for survival can also increase the risk of lung injury, highlighting the delicate balance required in the care of these vulnerable infants.
Chorioamnionitis
Chorioamnionitis, an inflammation of the fetal membranes typically caused by an ascending infection, has been investigated as a potential cause of BPD. The research findings in this area have been mixed. Some studies have indicated an increased risk of BPD in the presence of maternal chorioamnionitis, while others have shown no difference or even a decreased risk.
In 2009, a significant 13-year multicenter study conducted by Lahra and colleagues examined this relationship and concluded that histologic chorioamnionitis was actually protective against BPD. This surprising finding led other researchers, such as Wright and Kirpani, to explore whether the fetal response to chorioamnionitis might play a role in the development of BPD. This area of research continues to be explored as we seek to better understand the complex factors contributing to BPD. Wright and Kirpani delved into the role of a transcription factor, nuclear kB, and its involvement in inflammation in the pathogenesis of BPD. This area is still under investigation, and much more research is needed to fully understand these mechanisms.
Ureaplasma Colonization in the Infant Lung and Bacteria Sepsis
In 2005, Schelonka and colleagues conducted a meta-analysis of 23 studies, which revealed a significant association between ureaplasma colonization and the development of BPD at 36 weeks gestational age. The meta-analysis included 23 studies that measured BPD at 28 days postnatally and eight studies that measured BPD at 36 weeks postmenstrual age. The analysis found a significant association between ureaplasma colonization and BPD at both measurement points, although the association was more pronounced in smaller studies with fewer participants.
Additionally, bacterial sepsis has consistently been linked to higher rates of BPD, further emphasizing the complex interplay between infections and the development of this condition. Understanding these connections is crucial for improving prevention and treatment strategies for BPD. In one cohort study, researchers reviewed recent literature ranging from bench studies to clinical trials and discovered that BPD rates increased from 35% to 62% following early onset sepsis. This and other studies demonstrate a strong association between sepsis and chronic lung disease, particularly highlighting the role of gram-negative bacteria in the development of bronchopulmonary dysplasia (BPD).
Patent Ductus Arteriosus (PDA)
Patent ductus arteriosus (PDA) is another condition that can contribute to hemodynamic instability, and it has been linked to an increased risk of BPD. The left-to-right shunting through a PDA can cause lung endothelial damage, which, combined with the increased need for mechanical ventilation due to pulmonary edema and lung dysfunction, may elevate the risk of BPD in patients with PDA. These findings underscore the complex interplay between various conditions and the development of BPD, making it clear that managing these risk factors is crucial in reducing the incidence and severity of the disease.
However, some studies have shown that despite reducing the size of PDA, indomethacin prophylaxis does not decrease the rates of BPD. Interestingly, PDA ligation has been associated with an increased risk of BPD rather than reducing it. This suggests that the relationship between PDA and BPD may not be direct or causal. Instead, it appears that factors such as high fluid intake in the first days after birth may predispose infants to both PDA and BPD, leading to an observed association.
Moreover, lower serum cortisol levels in very low birthweight infants have been correlated with both PDA and BPD. This correlation suggests that early adrenal insufficiency in these infants could be a contributing factor that explains the link between the two conditions.
Genetic Factors
Genetic factors are also being explored as potential predispositions for BPD. Significant research is currently underway to identify specific genes, nucleotides, alleles, and mRNA that may contribute to a genetic predisposition to BPD. This ongoing work could provide valuable insights into the underlying causes of BPD and help identify at-risk infants earlier, allowing for more targeted interventions.
Yu and colleagues, along with Parad and Torgerson in the TOLSURF study, are currently investigating various genetic factors related to BPD. These researchers are exceptionally knowledgeable, and while we do not have enough time today to delve into all their findings, it is important to note that the evidence so far is mixed. Some studies suggest that BPD can run in families—if one baby has BPD, there is a higher likelihood that a subsequent baby might also develop it. However, twin studies have not consistently shown strong heritability, indicating that more research is needed to understand which genetic factors might predispose infants to BPD.
What we do know is that premature babies are at a significantly higher risk for developing BPD due to their underdeveloped lungs. These immature lungs often lead to signs of respiratory distress, which we commonly treat with positive pressure and oxygen therapy. While these treatments are necessary, they can also contribute to the development of BPD, underscoring the complexity of managing and preventing this condition. More research is needed to clarify the genetic components and improve our strategies for treating at-risk infants.
Given this complex cycle, the critical question becomes: How can we prevent it from occurring? The literature discusses a variety of prevention strategies, each with potential roles in the treatment and management of BPD. We'll explore these strategies, examining how they are supported by current research and their practical application in clinical settings.
Prevention Strategies
Reducing PPV
When we discuss prevention strategies for BPD, one key principle is to minimize the amount of oxygen and positive pressure ventilation these babies receive. Both barotrauma and volutrauma can cause significant lung damage, and this is especially true in the fragile lungs of premature infants. Any ventilation with increased volumes or pressures can lead to immediate lung injury. For instance, even a small number of large-volume breaths delivered with a bag valve mask during resuscitation can cause harm, particularly in surfactant-deficient lungs that do not inflate uniformly.
The risk of injury is especially high during initial resuscitation attempts. During this critical period, the goal is to create functional residual capacity while carefully managing ventilator volumes to stay below the total lung capacity. Striking this balance is challenging but crucial to avoid lung damage.
Reducing oxygen %
Oxygen toxicity is another major factor in the development of BPD. Exposure to high levels of oxygen (hyperoxia) can halt lung development, generate reactive oxygen species, and trigger the inflammatory process. This cascade of events can lead to the type of lung injury that contributes to BPD. Therefore, the careful management of oxygen levels is essential in preventing the development of this condition.
In 2009, a significant study published in Pediatrics by Vento explored the impact of oxygen levels during resuscitation on infants born between 24 and 28 weeks of gestational age. This randomized controlled trial assigned babies to two different FiO₂ groups for resuscitation—one group received 30% FiO₂, while the other received 90% FiO₂. The results were striking: in the group that received 30% FiO₂, the incidence of BPD was reduced by half, from 32% to 15%.
Moreover, the study found that biomarkers of oxidative stress increased exponentially in the group exposed to 90% FiO₂, and these increases correlated strongly with the development of BPD. This research underscores the importance of minimizing oxygen exposure in these vulnerable infants. Providing less oxygen not only reduces oxidative stress but also supports the creation of new alveoli, which is crucial for healthy lung development. These findings highlight the need for careful oxygen management in the care of premature infants, particularly those at risk for or diagnosed with BPD.
When managing infants at risk for BPD, even small adjustments in oxygen delivery can make a significant difference. For instance, when administering a nebulizer treatment, it is beneficial to use 21% oxygen (room air) rather than 100%. Similarly, employing a high-flow device can be advantageous because it allows for the use of higher flow rates with lower FiO₂, with the settings for flow and FiO₂ being adjustable independently rather than being tied together. This approach helps reduce the risk of oxygen toxicity while still providing the necessary respiratory support.
Antenatal corticosteroids
Antenatal corticosteroids have become a standard of care for women between 24 and 34 weeks of gestation who are experiencing preterm labor. These steroids are administered to help accelerate fetal lung development. However, their effect on the incidence of BPD remains a topic of debate. While the mechanism of action for corticosteroids in promoting lung maturation is well understood and listed on the current slide, some animal studies have raised concerns. These studies suggest that corticosteroids might arrest alveolarization and microvascular development, potentially contributing to the development of BPD. Therefore, while antenatal corticosteroids are widely used, their role in BPD prevention continues to be carefully evaluated.
Postnatal corticosteroids
The use of postnatal corticosteroids in managing BPD should be carefully considered on a case-by-case basis. Early studies indicated that administering corticosteroids within the first two weeks of birth could reduce the risk of developing BPD and shorten the time to extubation. However, when corticosteroids are administered later, more than three weeks after birth, they may not reduce the risk of BPD but can still help facilitate earlier extubation.
The side effects of corticosteroids in this population are consistent with those observed in others, including hyperglycemia, hypertension, gastrointestinal bleeding, hypertrophic cardiomyopathy, and an increased risk of infection. Importantly, long-term studies have highlighted a clear association between postnatal corticosteroid use and poor neurodevelopmental outcomes, including an increased risk of cerebral palsy.
A recent study published in JAMA in 2021 suggested that early initiation of medium cumulative doses of systemic dexamethasone might be the most effective regimen for reducing mortality associated with BPD by 36 weeks postmenstrual age. This finding underscores the importance of carefully weighing the benefits and risks of corticosteroid use in premature infants to optimize outcomes.
Azithromycin
Azithromycin and other macrolides, known for their antibiotic and anti-inflammatory properties, have been investigated as potential therapies for preventing BPD in preterm infants, particularly due to their activity against ureaplasma infections. In one randomized controlled trial, a six-week course of azithromycin was administered to very low birth weight infants, but the results showed no statistically significant difference in BPD incidence compared to a placebo. However, among infants colonized with ureaplasma, azithromycin did reduce the incidence of BPD, indicating a potential benefit in this specific subgroup.
Vitamin A
Vitamin A, or retinol, plays a crucial role in the regulation of lung development and injury repair. Low levels of vitamin A have been associated with an increased risk of developing BPD. Consequently, prophylactic administration of vitamin A has been shown to significantly reduce the risk of BPD in extremely low birth weight infants. Importantly, this intervention did not result in any difference in neurodevelopmental impairment at 18- and 22-month follow-up visits for this patient population, making it a promising strategy for BPD prevention without long-term adverse effects.
Vitamin E and Selenium
Currently, there is no evidence to support the use of vitamin E or selenium for reducing or preventing the development of BPD in preterm infants. However, other prevention strategies have shown promise.
Caffeine
One such strategy is the use of caffeine, as demonstrated in the Caffeine for Apnea of Prematurity Trial. This trial compared caffeine to a placebo administered within the first 10 days after birth. Although the primary focus was on preventing apnea of prematurity, the study unexpectedly found a significant reduction in the incidence of BPD at 36 weeks postmenstrual age in the group that received caffeine compared to the placebo group. The exact mechanism by which caffeine reduces the risk of BPD is still unclear.
Pentoxifylline
Another potential intervention is pentoxifylline, a non-specific phosphodiesterase inhibitor known for its ability to decrease pulmonary inflammation. In a study comparing nebulized pentoxifylline to intravenous dexamethasone, nebulized pentoxifylline was found to reduce the risk of BPD by 27%. This suggests that pentoxifylline might offer a beneficial approach to reducing BPD risk, though further research is needed to confirm these findings and better understand the underlying mechanisms.
Cromolyn
Cromolyn, a mast cell stabilizer commonly used in the treatment of asthma, has not been effective in preventing BPD in preterm infants. Despite its benefits in other respiratory conditions, it does not appear to offer protection against BPD.
Nitric Oxide
Nitric oxide, on the other hand, has shown promise in reducing oxidative stress and supporting lung development. However, studies in humans have produced mixed results. Because of this inconsistency, the National Institutes of Health (NIH) consensus statement does not recommend the routine use of nitric oxide in the care of preterm infants. Nonetheless, the NIH acknowledges that basic research, particularly animal studies, has provided valuable insights into the potential benefits of nitric oxide for lung development and function in infants at high risk for BPD. The consensus calls for more research in this area to better understand its role and potential applications.
Surfactant
Surfactant therapy, delivered either through the INSURE (Intubation-SURfactant-Extubation) approach or the LISA (Less Invasive Surfactant Administration) technique, offers a way to administer surfactant to premature infants without the need for intubation. This approach has been effective in reducing the risk of respiratory distress syndrome (RDS) in these babies. However, despite its benefits in managing RDS, surfactant therapy has not been shown to significantly reduce the incidence of BPD by 36 weeks gestational age.
Ventilatory Strategies
In terms of ventilatory strategies, goals for managing infants with BPD have included practices like permissive hypercapnia and gentle ventilation. Although clinical trials have not demonstrated a significant reduction in BPD rates with permissive hypercapnia, some trends suggest a potential reduction in BPD without an increase in adverse events.
Studies comparing ventilation strategies, specifically high-frequency ventilation versus conventional ventilation, have shown that both methods result in nearly comparable rates of BPD in this population. This indicates that while the choice of ventilation strategy is crucial for managing premature infants, neither approach has proven to be markedly superior in reducing the incidence of BPD.
Acetylcysteine
Acetylcysteine, a mucolytic agent, has been explored for its potential to prevent BPD development. However, current evidence does not support its effectiveness in reducing the risk of BPD.
Nutrition
One of the most discussed topics in the literature concerning BPD patients is fluid management, which is crucial from the day these infants are born through all of their outpatient care. Babies at risk for BPD are often fluid-restricted because excessive fluid intake during the first 10 days after birth has been linked to an increased risk of BPD. To compensate for the reduced fluid intake, feedings are fortified to ensure these infants receive adequate calories. Infants who develop BPD may require up to 40% more kilocalories than their age-matched peers to meet their energy needs and support their growth and development.
Infants with BPD continue to have an increased caloric expenditure, approximately 35% above their typical needs. Unfortunately, 30 to 65% of these infants experience growth failure soon after their initial hospital discharge. To mitigate this risk, it is crucial to ensure that they are set up for success with the appropriate formula and caloric intake before they leave the hospital. However, even with optimal in-hospital care, strong outpatient follow-up is essential. This follow-up ensures that these babies continue to meet their elevated caloric needs and support their growth and development.
When it comes to prevention strategies for BPD, there is a wide array of options and interventions to consider. Each has its own set of benefits, limitations, and areas where further research is needed to optimize care for these vulnerable infants. The various prevention strategies we've discussed are categorized based on their proven benefits, according to the available literature. it is important to remember that no two patients with BPD are exactly alike, and their care must be tailored to their individual needs and circumstances.
Treatment of Established BPD
Each patient with BPD has a unique journey, making it crucial to tailor treatment and care to the individual needs of the child and their family. Once a child begins to show signs of BPD or is diagnosed with the condition, the focus naturally shifts from prevention to treatment. Several strategies can be employed to manage BPD effectively. Among these, inhaled steroids, diuretics, and bronchodilators are the most commonly referenced treatments in the literature. These therapies are central to managing the symptoms and complications associated with BPD, helping to improve outcomes for these vulnerable patients.
Inhaled Steroids
Inhaled corticosteroids have been increasingly employed in the treatment of both developing and established BPD. The growing body of evidence supports their use, particularly in terms of their positive impact on patient outcomes. This underscores the importance of continuously refining and personalizing treatment strategies to meet the specific needs of each child with BPD.
A Cochrane Systematic Review of randomized controlled trials provided significant insights into this treatment approach. The review found that early administration of inhaled steroids to very low birth weight infants effectively reduces the incidence of death or chronic lung disease at 36 weeks postmenstrual age, whether considering all randomized infants or the survivors.
However, it is crucial to identify the optimal risk-benefit ratio for these patients. This involves exploring different delivery techniques and dosing schedules to maximize both short- and long-term benefits while minimizing adverse effects. Of particular concern are the neurodevelopmental outcomes associated with the use of inhaled steroids, making it essential to carefully weigh the potential benefits against any potential risks. Further research in this area will be key to optimizing care for infants with BPD.
Diuretics
Diuretics are commonly used in patients with known BPD to reduce pulmonary alveolar and interstitial edema and improve lung function. However, the effectiveness of diuretics, particularly systemic loop diuretics like furosemide, has been subject to extensive research with mixed results.
A systematic review of clinical trials investigating the use of intravenous (IV) or enteral furosemide in infants with developing or established BPD found no consistent benefit for infants less than three weeks old. For infants older than three weeks, a single dose of 1 mg per kg of IV furosemide only provided transient improvement in lung mechanics. Based on this evidence, the literature suggests that systemic loop diuretics should not be routinely used for infants with BPD.
In contrast, a Cochrane Review focusing on thiazides and spironolactone for patients with moderate BPD found that these medications improved lung mechanics. Moreover, when administered for four weeks, they were associated with a reduction in mortality among these patients.
Aerosolized diuretics have also been studied, but they have not shown long-term benefits and are not routinely recommended. For patients with BPD who are on diuretics in an outpatient setting, the best approach is to allow for growth rather than increasing the diuretic dose. A gradual weaning of diuretics as the child grows is often the preferred strategy in managing these patients.
Bronchodilators
Studies have shown that inhaled bronchodilators, particularly beta-agonists, can provide short-term improvement in lung function for infants with BPD, especially during acute exacerbations. These medications are not necessary on a regular basis but can be beneficial during respiratory infections or when reversible bronchospasm occurs.
Growth and Nutrition
In terms of growth and nutrition, it is crucial to select the appropriate caloric intake for these infants, typically ranging from 22 to 30 calories per ounce. The balance between fat and carbohydrates is also important, as these babies need nutrients like zinc to support tissue repair, carbohydrate tolerance, and immune healing. Additional vitamin A is often recommended, and it is important to avoid lipid restriction and excessive glucose infusion in this patient population.
European Respiratory Society Guideline
The European Respiratory Society's consensus group (Duijts et al., 2020) conducted a thorough review of several key areas related to the care of BPD patients after discharge, but they concluded that the evidence supporting many interventions is generally low. For instance, they do not recommend routine lung imaging for BPD patients unless the patient has severe BPD or significant respiratory symptoms. Similarly, they advise against using lung function tests to monitor children with BPD, citing the low certainty of the evidence.
When it comes to deciding whether to send a child with BPD to daycare, the task force suggests that this decision should be based on a combination of factors, including local experience, the child's age, the season, and the family's preferences and circumstances. They support the use of inhaled bronchodilators only during acute exacerbations, as we discussed earlier. Additionally, they recommend against treating BPD children with inhaled or systemic corticosteroids and advocate for the weight growth weaning strategy for diuretics.
This comprehensive approach underscores the importance of individualized care for BPD patients. It emphasizes the need to base treatment decisions on evidence-based practices while also considering the unique needs and circumstances of each child and their family. The European Respiratory Society's consensus group also recommended that for children with BPD, supplemental oxygen should be maintained with a minimum saturation target level of 90% until further studies provide more definitive guidance.
Van Hus et al., in a study published in Acta Paediatrica in 2016, examined neurologic outcomes in NICU babies through a multicenter randomized controlled trial. This study involved 176 infants who were either born at less than 32 weeks of gestational age or weighed less than 1,500 grams at birth. The infants were divided into two groups: an intervention group and a control group. Neurological assessments were conducted at 12 and 24 months to evaluate the impact of the intervention on their cognitive and motor development.
The intervention group received seven to nine physical therapy visits in their home, while the control group received standard care. Importantly, if infants in the control group met the criteria for home physical therapy, they still received those visits as part of their standard care. The researchers were able to follow these infants for an impressive 5 1/2 years, which is a substantial duration when studying BPD patients. After this period, they had a good follow-up rate, with 69 and 67 patients remaining in the intervention and control groups, respectively.
The study found that children with BPD who received home physical therapy showed significant benefits in both cognitive and motor domains compared to those who received standard care. The differences observed between the intervention and control groups were quite pronounced, as illustrated in the slides.
This research highlights the importance of recommending outpatient support, such as physical therapy, for children with BPD. Such interventions can have a profound impact on their neurodevelopmental, learning, and cognitive outcomes in the long term, underscoring the need for a comprehensive approach to their care beyond the NICU.
Surfactant Study
The next study, conducted by Hascoet et al. and published in JAMA Pediatrics in 2016, focused on the effects of late surfactant administration in infants with prolonged respiratory distress who remained on ventilators at 36 weeks postmenstrual age and at one year postmenstrual age. This was a double-blind, randomized, controlled trial conducted across 13 centers involving 113 patients. The infants were randomized to receive either 200 mg per kg of surfactant or a syringe filled with air. To maintain blinding, the syringes were weighted the same and covered in light-protective tubing, so those administering the treatment were unaware of whether they were delivering surfactant or air. This careful design aimed to ensure the objectivity of the trial’s outcomes.
The study by Hascoet et al. showed no significant difference in outcomes at 36 weeks postmenstrual age between the two groups. However, the intervention group that received late surfactant administration was associated with reduced respiratory morbidity at one year of age, indicating a potential long-term benefit.
The next study, conducted by Yeh et al. and published in the American Journal of Respiratory and Critical Care Medicine in 2015, was a clinical trial conducted at two neonatal centers in the US and Taiwan. This trial included infants with severe respiratory distress who required mechanical ventilation and had oxygen requirements exceeding 50%. The intervention group received a combination of surfactant and budesonide, while the control group received only surfactant until the infants required 30% or less FiO2 or were extubated.
In this study, Survanta, a specific type of surfactant, was administered every eight hours for up to six doses, following the manufacturer's instructions. The results were significant: the incidence of BPD or death in the intervention group was reduced from 66% in the control group to 42%. This finding suggests that the combination of surfactant and budesonide could be effective in reducing the incidence of BPD or death in infants with severe respiratory distress. The study demonstrated a significant reduction in the incidence of BPD or death when multiple doses of surfactant and budesonide were administered to infants with severe respiratory distress. This treatment was continued until the patients were either extubated or required less than 30% FiO2. The intervention group saw a reduction in the incidence of BPD or death from 66% in the control group to 42%, highlighting the potential effectiveness of this combined therapy in improving outcomes for these high-risk infants.
SUPPORT Trial 2017
The SUPPORT trial, conducted in 2017, was a significant randomized controlled trial that used a multicenter approach to examine the effects of different oxygen saturation (SpO2) targets on preterm infants. The study specifically focused on infants born between 24 and 27 weeks of gestational age and included a large cohort of 1,316 infants. These infants were randomized into two groups with different SpO2 targets: 85-89% and 91-95%.
The trial aimed to determine the association of PaCO2 levels with severe intraventricular hemorrhage (IVH), BPD, and neurodevelopmental outcomes at 18 and 22 months of age. The analysis of blood gases revealed that a higher PaCO2 was an independent predictor of several adverse outcomes, including severe IVH and death, BPD and death, and neurodevelopmental impact and death.
These findings underscore the importance of closely monitoring and managing PaCO2 levels in preterm infants to minimize the risk of these severe complications. The SUPPORT trial provided critical insights into how different oxygenation strategies and PaCO2 levels can influence the long-term outcomes of very preterm infants.
Montelukast Treatment in Severe BPD
The study by Ruprecht et al., published in Respiration in 2014, explored the use of montelukast as a treatment for severe BPD in preterm infants. This unblinded prospective trial included infants between 23 and 27 weeks of gestational age, all of whom were diagnosed with severe BPD. The treatment regimen involved administering montelukast at a dose of 1 mg per kg once daily for the first week, increasing to 1.5 mg per kg in the second week and 2 mg per kg in the third week. Treatment continued until the clinical signs of BPD cleared or the infant was discharged.
The results were quite compelling. The survival rate in the treatment group was 91%, compared to 36% in the non-treatment group, demonstrating a significant survival advantage for those receiving montelukast. Additionally, the treatment group experienced a dramatic reduction in the number of days on mechanical ventilation, from an average of 103 days down to 41 days. This reduction in ventilation days by more than half further highlights the potential effectiveness of montelukast in managing severe BPD and improving outcomes in this vulnerable population.
Hydrocortisone
Renault et al. published a significant study in 2016 that investigated the effects of hydrocortisone on infants born at less than 27 weeks gestational age. The study was conducted between 2005 and 2008 across two centers, with one center administering hydrocortisone to these infants while the other did not. The results were notable: the use of hydrocortisone was associated with a reduction in the incidence of bronchopulmonary dysplasia (BPD). Moreover, at the two-year follow-up, there was no observed neurodevelopmental impairment in the infants who received hydrocortisone, suggesting that this treatment could be both effective and safe in preventing BPD without long-term neurodevelopmental risks.
The following two studies you mentioned are more recent and represent some of the cutting-edge research currently being explored. These studies are part of the ongoing efforts to expand our understanding of BPD prevention and treatment and could shape future approaches to neonatal care.
Mesenchymal Stem Cells
If you haven't heard about mesenchymal stem cells, or MSCs for short, they play a crucial role in lung development. Stem cell dysfunction can hinder the self-repair mechanisms of immature lung tissue, contributing to the development of BPD. Research has shown that the depletion or dysfunction of endogenous or progenitor stem cells can increase the risk of BPD. In animal studies, exogenous stem cells have been found to protect and repair lung injury, partly due to their ability to preserve the pools of endogenous stem cells.
Bone marrow-derived MSCs have shown considerable promise in improving BPD by preventing lung inflammation. What's particularly interesting is that the beneficial effects of MSCs are believed to be primarily hormone-related rather than due to the cells' ability to engraft into lung tissue. The discovery of MSCs in human umbilical cord tissue and cord blood marked a significant advancement, as it provided a clinically relevant and feasible source of these potent cells for the treatment of neonatal diseases, including BPD. This breakthrough opens new avenues for treating BPD and potentially improving outcomes for affected infants. This development opens up new possibilities for treating BPD by harnessing the regenerative potential of MSCs, offering hope for better outcomes in affected infants.
For example, Chang et al., in The Journal of Pediatrics, reported on a phase I trial of human cord blood-derived MSCs successfully conducted in South Korea involving nine extremely preterm neonates. The two-year outcomes from this trial did not reveal any safety concerns, which is encouraging for the continued exploration of this treatment. In the United States, another phase I clinical trial of human umbilical cord blood-derived MSCs has been completed, with a phase II trial currently underway. In this trial, the babies received three doses of MSCs, and it was found that the severity of BPD was lower in those who received the transplant.
Beyond MSCs, other sources of cells are also under investigation. An Australian group has been studying stem-like cells derived from placental membranes, specifically human amnion epithelial cells (HAECs), which have shown therapeutic promise in preclinical models of BPD. This group conducted the first-in-human clinical trial of HAECs in neonates with BPD to assess the safety of these cells. With the exception of one patient who developed respiratory distress attributed to an embolic event, the investigators reported no other adverse events related to the administration of these cells. This suggests that HAECs could be another promising avenue for treating BPD.
Additionally, there is growing interest in the potential role of insulin-like growth factor (IGF-1) in treating BPD. IGF-1, part of the insulin family, is crucial for promoting mitosis, stimulating cell proliferation, and driving DNA synthesis, which are key processes in pulmonary development during both the fetal and postnatal periods. IGF-1 is an important regulator of fetal growth, lung angiogenesis, and overall lung development, making it a potential therapeutic target for improving outcomes in infants at risk of or suffering from BPD. These emerging therapies, including MSCs, HAECs, and IGF-1, represent exciting developments in the quest to better understand and treat BPD, offering new hope for improving the lives of affected infants.
Insulin-like Growth Factor-1
IGF-1 levels increase significantly during the last two trimesters of pregnancy, with a sharp rise that you would clearly see on a graph. After birth, these levels decrease rapidly. In extremely preterm neonates, lower serum IGF-1 levels have been independently associated with an increased risk of BPD and other complications such as retinopathy of prematurity.
In neonatal rodent models, administering IGF-1 appears to reduce lung injury caused by hypoxia, even when the animals are exposed to oxygen. This suggests that IGF-1 could help mitigate some of the damage associated with oxygen therapy, which is often necessary for preterm infants. Several studies have reported that IGF-1 influences BPD development and progression by regulating biological processes related to the disease. Additionally, the exogenous administration of IGF-1 has been shown to alleviate lung inflammation, reduce cell apoptosis, and correct alveolar development disorders in children with BPD.
These findings suggest that IGF-1 could be a promising new target for treating BPD. For instance, recombinant human IGF-1, when combined with its binding protein (known as RH1 GF-1), has been shown to reduce the number of extremely preterm neonates developing severe BPD and shift the disease severity towards a milder form of BPD. This means that even if these infants are born prematurely and require oxygen and positive pressure ventilation, increasing their IGF-1 levels could potentially reduce their risk of developing BPD or at least lead to a milder form of the disease.
The potential of IGF-1 as a therapeutic target is indeed exciting, as it offers a new avenue for improving outcomes in preterm infants who are at high risk of BPD
Limitations
When discussing BPD research, it is important to acknowledge several limitations, particularly the ongoing controversy over meaningful endpoints. One of the biggest questions in the field is determining the appropriate duration for studying patients with BPD. Should research focus only on the period when they are in the NICU, or should it extend to when they leave the PICU, their first outpatient primary care visit, or even further? Some argue that studies should continue until these individuals reach significant life milestones, such as entering kindergarten, graduating from high school, starting their first job, or even until they have children or pass away. The challenge lies in deciding at what point the data collected provides the most meaningful and relevant insights.
Additionally, there are significant gaps in our understanding of long-term clinical outcomes for BPD patients. Specifically, there is limited information on what certain treatments or diagnoses mean for these individuals as they progress into adulthood and geriatrics. For example, how does BPD impact their long-term lung function, overall health, and quality of life? What are the potential late-onset complications? These are critical questions that remain largely unanswered due to the difficulty of conducting long-term studies and the variability in individual outcomes.
The controversy over meaningful endpoints and the scarcity of long-term data make it challenging to develop a comprehensive understanding of BPD and its implications across the lifespan. This highlights the need for continued research that not only addresses immediate outcomes but also tracks patients well into adulthood to provide a fuller picture of how BPD affects long-term health and well-being.
These are critical questions that highlight the complexities and uncertainties in BPD research, particularly regarding the long-term consequences of current treatments. For instance, if patients receive multiple doses of surfactant during infancy, we do not yet know if this could lead to stiffer lungs later in life, potentially contributing to conditions like COPD or emphysema as they age. The long-term pulmonary outcomes for BPD survivors are not well understood, especially as these individuals reach older adulthood, and this remains an area needing further study.
Another area of active discussion in the literature is the role of placental dysfunction as a primary factor in the development of BPD. The relationship between antenatal exposures—such as maternal smoking—and early postnatal events—like neonatal sepsis—has not been fully explored in terms of which has the most significant impact on BPD risk and severity.
There are still many unknowns regarding how these factors interact. For example, if a mother smokes during pregnancy and the infant later develops neonatal sepsis, does the combination of these factors exacerbate the risk of BPD, or does one dominate? Additionally, we need to understand better whether prevention strategies can mitigate these risks or if certain predisposing factors might offset the benefits of interventions aimed at reducing BPD incidence.
These gaps in our knowledge underscore the need for more comprehensive studies that examine the interplay between antenatal exposures, postnatal events, and various treatment strategies. Understanding these relationships could inform better prevention and treatment approaches, potentially leading to improved long-term outcomes for individuals with BPD.
There is still much to learn about the complex and multifactorial nature of BPD. Currently, there is limited research that connects the dots between various factors, such as antenatal exposures, postnatal events, and the development of BPD. Some researchers are now exploring the idea that BPD may actually begin during early fetal life. If this proves to be true, it could revolutionize our understanding of BPD and how we predict its occurrence. For instance, it might be possible in the future to identify babies at risk for BPD through amniotic fluid samples or choriocentesis long before they are exposed to oxygen or positive pressure ventilation. This would represent a significant shift from our current understanding and the traditional definition of BPD, which primarily focuses on postnatal factors.
The fact that we do not fully understand the pathophysiologic mechanisms leading to BPD highlights how complex this condition is. We are gradually learning more, but the pathogenesis of BPD remains highly multifactorial. It involves a wide range of pre and post-natal exposures that influence lung development in ways we do not yet fully comprehend. The interplay between these factors—ranging from genetic predispositions to environmental influences like maternal smoking or neonatal sepsis—makes it challenging to pinpoint a single cause or to develop a one-size-fits-all prevention or treatment strategy.
As research continues to evolve, gaining a deeper understanding of these mechanisms and their interactions will be crucial. It could open the door to new diagnostic tools, early interventions, and personalized treatment approaches that could significantly improve outcomes for infants at risk of or diagnosed with BPD.
The explanation captures the complexity of BPD and how various exposures and factors interact to influence its development. BPD likely involves multiple different pathophysiologies, depending on the timing and combinations of exposures. Some exposures may protect against BPD and promote lung repair, while others may injure the preterm lung and contribute to BPD pathogenesis. This dynamic interaction leads to the clinical manifestations observed, where BPD-typical lungs develop or, alternatively, where lung health is preserved. For those seeking a deeper understanding of BPD, it is essential to address any questions related to the evidence and historical context.
Questions and Answers
Could you share your thoughts on how the decision to administer antenatal corticosteroids is made, particularly given that it is made before birth?
Certainly. The decision to administer antenatal corticosteroids can vary greatly depending on where you are—whether in different regions of the United States or around the world. The recommendations can differ based on the provider's experience and the specific circumstances of the pregnancy. From what I've seen in the literature, the key takeaway is to administer these steroids early if they are deemed beneficial. However, it is important not to continue administering them after the baby has been in the NICU for three weeks and has been on a ventilator. At that point, the evidence indicates a significant risk of poor neurodevelopmental outcomes, which suggests that it wouldn't be appropriate to continue treatment at that stage.
We discussed how nutrition is crucial for these children. After they leave the hospital or ICU, how long should we continue to monitor their nutritional status? Additionally, how significant is the impact of nutrition on their growth? It seems like these factors are interrelated—almost like a "chicken or the egg" situation. Could you elaborate on that?
Absolutely, that makes perfect sense. I think it is really important to communicate to the families of BPD patients that they are facing significant challenges. A large proportion of these babies—around 65%—are diagnosed with growth failure after they leave the hospital. While we can do a lot to support them nutritionally in the hospital, the resources available at home are often more limited. it is crucial to emphasize to parents that inadequate nutrition could lead to their child needing to be readmitted. We should provide them with resources and guidance to ensure they feel in control. Something as seemingly small as not finishing a full bottle can have a much bigger impact on a child with BPD than on a healthy newborn. If a healthy newborn only takes three ounces instead of six, it might not be a big deal. However, for a child with BPD, that difference can be significant. That is why it is so important to share information and educate families about the challenges they may face. By helping them understand what they are up against, we can better partner with them to ensure their child’s success.
Given all the research you have reviewed, do you believe we’re on the right path toward effectively bridging the gap between the evidence-based recommendations you presented and what we are currently implementing? Considering that change can often be gradual, how do you see this progress unfolding?
I agree that having multiple definitions is something we need to address by working towards a consensus definition that everyone can agree on. However, I understand that it is challenging because we cannot predict the medical advancements that will occur in five or ten years when we set the definition today. Considering the history of how these definitions have evolved and the new treatments we're implementing, it makes sense, but it also complicates determining the best treatment plans. The constant changes and shifting targets make it difficult. That said, it is wonderful to see these babies surviving and thriving—becoming functional toddlers, attending school, and eventually creating families of their own. However, it is crucial that we continue to follow up and support these patients into adulthood and even into their geriatric years. I believe we’re on the right track, but it would be beneficial to see more global collaboration and consensus.
References
Ballard, R. A., Ballard, P. L., & Ballard, R. (2011). Corticosteroids (antenatal and postnatal) for preventing bronchopulmonary dysplasia. Pediatric Pulmonology.
Bancalari, J., & Jobe, A. H. (2001). Bronchopulmonary dysplasia: Then and now. American Journal of Respiratory and Critical Care Medicine.
Bauer, S. E., & Parham, K. (2021). Growth and nutrition in infants with bronchopulmonary dysplasia. Pediatric Pulmonology.
Brion, L. P., & Primhak, R. A. (2002). Diuretics for respiratory distress syndrome in preterm infants. Cochrane Database of Systematic Reviews.
Chang, Y. S., & Park, W. S. (2016). Mesenchymal stem cell therapy for bronchopulmonary dysplasia. The Journal of Pediatrics.
Collins, J. J., & Bell, E. F. (2017). Long-term outcomes of bronchopulmonary dysplasia. Frontiers in Medicine.
Davidson, L. M., & Berkelhamer, S. K. (2017). Bronchopulmonary dysplasia: An historical overview and scientific update. Pediatric Research.
Duijts, L., Reiss, I. K., Brusselle, G., & de Jongste, J. C. (2020). European Respiratory Society guidelines for the management of children with bronchopulmonary dysplasia. European Respiratory Journal.
Ehrenkranz, R. A., et al. (2005). Bronchopulmonary dysplasia and outcomes in very low birth weight infants. Pediatrics.
Fok, T. F. (2009). Prevention and management of bronchopulmonary dysplasia. Seminars in Fetal and Neonatal Medicine.
Gilfillan, M., Bhandari, V., & Kinsella, J. P. (2021). The evolving definition of bronchopulmonary dysplasia. BMJ.
Hagadorn, J. I., Sinkin, R. A., & Heard, M. (2006). Strategies for reducing the incidence of bronchopulmonary dysplasia. Pediatrics.
Hascoet, J. M., et al. (2016). Late surfactant administration for infants with bronchopulmonary dysplasia. JAMA Pediatrics.
Jobe, A. J. (1999). Mechanisms of lung injury and bronchopulmonary dysplasia. Pediatric Research.
Kugelman, A., & Durand, M. (2001). Current concepts in the pathogenesis of bronchopulmonary dysplasia. Pediatric Pulmonology.
Lauterbach, R., & Prendiville, O. (2006). Management of infants with bronchopulmonary dysplasia. Journal of Maternal-Fetal and Neonatal Medicine.
Mandell, E., & Raju, T. (2019). Clinical practices in the management of bronchopulmonary dysplasia. Clinics in Perinatology.
Northway, W. H., Jr., et al. (1967). Bronchopulmonary dysplasia: A new clinical entity. New England Journal of Medicine.
Parad, R. B., & Alexander, M. (2023). Bronchopulmonary dysplasia: Current perspectives and future directions. Pediatrics.
Renault, J. F., & Ancel, P. Y. (2016). Hydrocortisone therapy for bronchopulmonary dysplasia in preterm infants. Pediatric Pulmonology.
Ruprecht, J., & Schuhmann, M. U. (2014). Montelukast treatment in severe bronchopulmonary dysplasia. Respiration.
Salimi, A., & Wood, T. (2021). Perspectives on bronchopulmonary dysplasia: Advances and challenges. Pediatrics.
Sahni, R., & Mowes, A. (2023). Bronchopulmonary dysplasia: An evolving disease. Pediatric Research.
Schmidt, B., Roberts, R. S., Davis, P., & Doyle, L. W. (2006). Caffeine therapy for apnea of prematurity. New England Journal of Medicine.
Shah, P. S., et al. (2017). Inhaled steroids for the prevention of bronchopulmonary dysplasia in preterm infants. Cochrane Database of Systematic Reviews.
Stevens, T. P., Finer, N. N., Carlo, W. A., & Rich, W. (2007). Ventilator strategies in the prevention of bronchopulmonary dysplasia. Cochrane Database of Systematic Reviews.
Thome, U. H., & Carlo, W. A. (2002). Gentle ventilation and permissive hypercapnia in bronchopulmonary dysplasia. Seminars in Neonatology.
Tyson, J. E., et al. (1999). Vitamin A supplementation for bronchopulmonary dysplasia in preterm infants. New England Journal of Medicine.
Van Hus, J. W., Potharst, E. S., Jeukens-Visser, M., & Kok, J. H. (2016). Early intervention and developmental outcomes in preterm infants. Acta Paediatrica.
Watterburg, K. L., & Fern, A. (2000). The role of inflammation in bronchopulmonary dysplasia. Pediatrics.
Wheeler, K. I., & Rich, W. (2010). Preventing bronchopulmonary dysplasia: Evidence-based strategies. Cochrane Database of Systematic Reviews.
Wright, C. J., & Kirpalani, H. M. (2009). Infection and inflammation in the pathogenesis of bronchopulmonary dysplasia. Seminars in Fetal and Neonatal Medicine.
Yeh, T. F., et al. (2015). Surfactant and budesonide therapy for prevention of bronchopulmonary dysplasia. American Journal of Respiratory and Critical Care Medicine.
Zhang, C., Yu, H., & Zhang, X. (2022). Insulin-like growth factor-1 and its role in the development of bronchopulmonary dysplasia. Experimental and Therapeutic Medicine.
Citation
Burr, K (2024). Bronchopulmonary dysplasia (BPD) historical and scientific update. Continued.com - Respiratory Therapy, Article 240. Available at www.continued.com/respiratory-therapy
Aug 23, 2024
1 CE HourMD Flavor of the Month…High Frequency Jet versus Oscillatory Ventilation
Kelly Massa, BHS, RRT-NPS
Editor’s note: This text-based course is an edited transcript of the webinar, MD Flavor of the Month…High Frequency Jet versus Oscillatory Ventilation, presented by Kelly Massa BHS, RRT-NPS.
It is recommended to download the course handout to supplement this text format.
Learning Outcomes
After this course, participants will be able to:
- Discuss HFOV and HFJV, including the mechanism of action, description of settings, and review of initial settings
- Explain the major differences between HFOV and HFJV
- Describe how to choose which high-frequency ventilator
Introduction
Let's start with a brief definition of high-frequency ventilation. High-frequency ventilation is a mechanical ventilation strategy that uses very small tidal volumes, typically between one to four milliliters per kilogram of dead space, coupled with very high respiratory rates. High-frequency ventilation minimizes alveolar damage caused by positive pressure. Large positive pressure swings and subsequent collapse during exhalation can cause significant harm. By reducing this stretch and recoil, high-frequency ventilation provides a safer alternative, particularly when conventional ventilation has failed.
Many institutions use two different types of high-frequency ventilators that operate uniquely. Let’s explore these differences. If you have worked in a NICU, you might be familiar with the scenario where, during your morning shift, a physician approaches you and says, "I think this patient needs to go on an oscillator."
As a dedicated respiratory therapist, you might respond, "Okay, sounds great. Conventional ventilation is failing, so we need to consider a high-frequency option. You are the physician; let's use the oscillator." However, when the shift changes, another physician might come in and say, "Actually, I believe this patient would be much better off on the jet." This scenario often leads to confusion in the NICU, as the choice of ventilator can vary depending on the physician on duty. It highlights the inconsistency driven by individual preferences and comfort levels with different machines. However, there is a well-defined mechanism of action for each type of ventilator that we will break down. As a respiratory therapist and ventilation specialist, you can offer valuable suggestions to physicians about the best choice for the patient.
When to Consider High Frequency
- Excessive conventional ventilator settings
- Plateau pressure ≥ 30-35cmH2O, large VT, pH < 7.1
- Avoid further VILI
- Lung recruitment
- Prophylactic treatment for ELBW neonates
- Infants less than 26 weeks
- Air leak syndrome
- Meconium aspiration, PPHN
- ARDS
- Available data comparing HFOV and HFJV has not shown a true superiority of either modality!
When should you consider high-frequency ventilation in general, without delving into the differences between oscillatory and jet? It is typically when conventional ventilator settings have become excessive. At this point, the settings may be causing more harm than benefit. It becomes a Catch-22: we need to use high pressures to deliver adequate tidal volumes and ventilate the patient, but these high pressures can also cause damage.
To achieve effective ventilation, very high peak inspiratory pressures and plateau pressures, often greater than or equal to 30 centimeters of water pressure, are required. Additionally, large tidal volumes of 10 to 12 milliliters per kilogram are used. If a patient's pH remains significantly acidotic, below 7.1, despite these measures, it indicates the need for an alternative approach.
In these instances, conventional settings can cause irreversible damage. While some lung tissue can regenerate up to the age of eight, we want to avoid causing damage that leads to long-term issues. Particularly in the neonatal population, where high-frequency ventilators are frequently used, we risk causing bronchopulmonary dysplasia (BPD). Therefore, it is crucial to consider high-frequency ventilation to mitigate these risks and provide safer respiratory support.
The main goal is to avoid further ventilator-induced lung injury. We should consider high-frequency ventilation when facing issues with lung recruitment. In our PICU and CICU settings, we frequently use this approach for pediatric ARDS patients. It can also be used prophylactically for extremely low birth weight neonates or infants born before 26 weeks gestation. We are seeing younger and younger babies being born and surviving past birth, making this consideration even more critical.
Patients with air leak syndrome, meconium aspiration, or persistent pulmonary hypertension are also candidates for high-frequency ventilation. These conditions often involve high blood pressure in the lung capillary beds, requiring careful management to prevent further complications. Patients with conditions like ARDS or pediatric ARDS can present significant challenges in ventilation.
When examining available data comparing the oscillator and the jet, you will find no clear evidence that one modality is superior to the other. This can be surprising, given how strongly some physicians advocate for one over the other. The reality is that neither is inherently better; they simply operate on fundamentally different principles. One machine may be more suitable for a particular patient due to its mechanism of action rather than any inherent superiority.
High Frequency Jet Ventilation (HFJV)
Figure 1. Example of High Frequency Jet Ventilation (IMEwee, CC BY-SA 3.0 via Wikimedia Commons).
What Is HFJV?
Let’s start with a basic overview of the high-frequency jet ventilation (HFJV) device itself, as shown in Figure 1. In the top left corner is the monitoring screen, which displays vital information. In the top right corner, you will find all the alarms, crucial for patient safety. The controls are centrally located, allowing us to set various parameters on the jet ventilator. Below the controls are the humidifier controls, essential for humidifying the jet propulsion gas. This is where the humidifier cassette is inserted.
Additionally, we have the primary buttons, including the alarm silence button, the power button, and the enter/reset button, all of which are important for operating the device efficiently.
Next, let's review the connection to the whisper jet, also known as the patient box. Visit bunl.com-"see HFJV" for more information. This component is essential for creating the jet propulsion we discuss in this lecture. The patient box has several key features:
- Cable Connector: This connects to the front interface of the jet ventilator.
- Purge Port: Keeps the lines clear.
- Pressure Monitoring Port: This connects to the life port adapter
- Push Button: Used to load the circuitry beneath the pinch valve.
The pinch valve is crucial as it controls the transitional flow of the jet ventilator, creating the jet propulsion needed for effective ventilation. The pinch valve literally shuts at the rate and speed set on the jet ventilator, creating the jet propulsion necessary for ventilation. This patient box is crucial to the jet ventilator's function. What is the jet ventilator overall? A jet ventilator is essentially a pressure-limited, time-cycled ventilator with an adjustable rate.
Key settings include:
- Rate: The frequency of breaths.
- Peak Inspiratory Pressure (PIP): This can be set on the ventilator for jet PIP.
- Inspiratory Time (iTime): Also known as valve time, this determines how long the valve remains open during inhalation.
- Passive Exhalation: The jet ventilator relies on passive exhalation, which is important when comparing it to the oscillator.
When delivering tidal volumes, the jet ventilator uses very small tidal volumes at rapid rates via a special ET tube adapter called the life port adapter. This adapter is crucial for high-frequency jet ventilation. Without it, the jet ventilator cannot function. Jet ventilation is always used in tandem with another conventional ventilator. At our institution, we use the Drager, but other institutions may use different ventilators, such as the Servos or Puritan Bennett models.
The choice of ventilator is not about superiority; it is about compatibility and institutional preference. The jet ventilator itself has settings for PIP, rate, and iTime. We will delve deeper into the life port adapter. Without it, we cannot use high-frequency jet ventilation. The jet ventilator does not have a PIP setting, which means we need a conventional ventilator to provide positive end-expiratory pressure (PEEP). This is crucial for creating the mean airway pressure, which we discuss further.
How Does the Jet Ventilator Work?
The life port adapter is also known as the jet nozzle. Here's an overview:
- Life Port Adapter: The jet adapter or life port adapter replaces the standard ET tube connection. Typically, an ET tube has an adapter with a 15-millimeter connector at the end. To use the jet ventilator, we remove this standard ET tube adapter and replace it with the life port adapter.
- Adapter Sizes: The life port adapter comes in various sizes to match ET tubes, ranging from 2.5 to 3.5 millimeters, 4.5 millimeters, and 5.5 millimeters. Ensuring the correct adapter size is essential for the therapy's effectiveness.
- Connection: The life port adapter fits snugly onto the ET tube, maintaining the 15-millimeter connector for attachment to conventional vent circuitry.
By replacing the standard ET tube adapter with the life port adapter, the jet ventilator can deliver the necessary rapid, small tidal volumes through the specialized nozzle. This setup allows for precise control and effective ventilation in tandem with a conventional ventilator. Next, let’s talk about the components and functionality of the life port adapter.
- Pressure Monitor Tube
- This tube connects to the patient box, providing feedback to the ventilator about what is being delivered to the patient in terms of PIPs and other parameters.
- Jet Port
- The jet port is equipped with a removable cap. If you are not using the jet but want to keep the life port adapter in place, you can cap off both the jet port and the pressure line, using it as a standard ET tube adapter. This allows you to avoid constantly switching adapters. When the jet ventilator is in use, the pinch valve circuitry connects to the jet port. This connection facilitates the delivery of fresh gas, creating jet propulsion.
- Transitional Flow
- The life port adapter is designed to deliver fresh gas that pierces through dead space, avoiding the creation of turbulent flow. Turbulent flow acts like a bulldozer, pushing through the entire airway width, which can move dead space and secretions further into the lungs—an undesirable outcome.
Benefits of Transitional Flow
- Reduces Turbulence: By creating transitional flow, the adapter minimizes turbulent flow.
- Pierces Dead Space: Fresh gas pierces through dead space more effectively.
- Prevents Secretions Build-Up: Helps prevent secretions from being pushed further into the lungs.
This transitional flow is essential for the effectiveness of high-frequency jet ventilation, making the life port adapter a critical component in delivering this advanced respiratory therapy. Here is a detailed review of how the jet ventilator operates and the benefits of its design. The jet ventilator’s life port adapter works by piercing through the center of the airway, effectively cutting through dead space. This design ensures that much smaller tidal volumes are just as effective as larger ones because they bypass the rebreathing of dead space gas.
Benefits
- Secretion Removal: Helps with secretion removal.
- CO2 Elimination: Enhances the elimination of CO2.
- Passive Exhalation: Facilitates passive exhalation, which we discuss further.
Comparison to Oscillator
- While both the jet ventilator and the oscillator utilize transitional flow, the oscillator's flow is more rounded and closer to laminar flow. This difference in flow dynamics is due to the design of the life port adapter.
Jet stream advantage allows injured lungs to rest and heal. The jet ventilator may be preferred if the patient has a diagnosis of air leak syndrome. The very short inspiratory times (iTime) and tiny tidal volumes (about one milliliter per kilogram) set on the jet ventilator can avoid areas of increased resistance, such as air leaks or severely damaged lung tissue.
This targeted approach prevents further damage to already compromised areas by avoiding unnecessary alveolar stretch and strain. The jet ventilator’s design and function make it a powerful tool for managing specific respiratory conditions, offering a targeted and effective approach to ventilation that minimizes further lung injury.
The beauty of the jet ventilator is that it avoids areas of damage, allowing them to rest and heal. However, it is crucial to note that the life port adapter is size-dependent. If a patient has an ET tube size outside the available options, we cannot utilize the jet ventilator.
Passive Exhalation
Figure 2. HFJV Passive Exhaltion (IMEwee, CC BY-SA 3.0, via Wikimedia Commons).
Let’s expand a bit more on passive exhalation with the jet ventilator seen in Figure 2. We have already discussed laminar flow, but it is crucial to understand how this flow impacts exhalation. With passive exhalation, the laminar flow moves down the center of the airways. When the patient exhales, there is a helix-like spiral around the outer areas of the airways. This spiral flow allows the patient to exhale passively.
This design helps to clear secretions and reduce the work of breathing by allowing air to flow smoothly and naturally out of the lungs. Passive exhalation is particularly beneficial because it minimizes the need for forced exhalation, which can be more taxing for the patient and potentially harmful to delicate lung tissues. Understanding this mechanism underscores why the jet ventilator can be a better choice for patients who need gentle ventilation support, such as those with fragile lung conditions or significant secretions that need to be managed effectively.
- Allows Jet to run at lower MAP compared to HFOV to achieve adequate oxygenation.
- Not competing with negative pressure from an active exhalation
- Enhances airway clearance
- Inspired gas shoots down the middle of the airway, leaving the path of least resistance for exhalation and secretions against airway walls.
- Can create gas trapping if not enough eT
The theory behind this flow is that secretions can be carried out of the airways rather than getting caked down lower. This transitional flow creates a really beneficial phenomenon for our patients. It is more comfortable because we are not sucking the air back out; instead, we are piercing it in, allowing patients to passively exhale on their own. Because of this mechanism, we can set the jet ventilator to run at a slightly lower mean airway pressure compared to the oscillator to achieve the same level of oxygenation.
This is significant because it means we can be gentler on the lungs while still providing effective ventilation. When we talk more about the oscillator, we review how it uses active exhalation. For now, it is important to understand that the jet's passive exhalation is a big advantage, allowing for lower mean airway pressures and, therefore, potentially less stress on the lungs.
The oscillator's mechanism involves the bellows swinging forward to push air in and then swinging back to suck the air out. This dynamic means the mean airway pressure (MAP) competes with the backswing of the bellows or piston. As a result, we need to set a slightly higher MAP to compensate for the negative pressure during active exhalation. In contrast, the jet ventilator avoids this issue since it does not involve fighting against negative pressure from active exhalation. This means we do not need to set the MAP as high.
The jet ventilator likewise enhances airway clearance due to its unique transitional flow. This flow pierces through the middle of the airway, allowing for a more effective exhalation path along the airway walls. As a result, secretions can spiral out naturally, making the ventilation process more efficient and less taxing on the patient.
The main takeaway is that the jet ventilator's use of passive exhalation and lower MAP settings offers a gentler and potentially more effective option for patients, especially those with delicate or damaged lung tissues. In contrast, the oscillator requires higher MAP due to the active exhalation process, which can be more demanding on the patient's respiratory system. This fundamental difference highlights why the jet ventilator can be preferable in certain clinical scenarios.
One important consideration with jet ventilation is ensuring adequate exhalation time to prevent gas trapping. Similar to conventional ventilation, where we carefully set iTime and rate to achieve a good I:E ratio, we need to be mindful of the expiratory time with jet ventilation. Since exhalation is passive, it is crucial to set an appropriate expiratory time.
Inspiratory Time
When we discuss the settings on the jet ventilator, the first one to address is the inspiratory time, also known as the valve time. Typically, we start with a default minimum of 0.02 seconds. To put that in perspective, it is about 25 times shorter than a conventional iTime of 0.5 seconds. This incredibly short inspiratory time is key to delivering those tiny tidal volumes rapidly, but it also means we need to be extra careful to ensure that there is enough time for exhalation to avoid gas trapping and associated complications.
While the jet ventilator offers many advantages, such as lower mean airway pressures and enhanced secretion clearance, we must remain vigilant about setting appropriate expiratory times, avoiding gas trapping, and maintaining effective and safe ventilation for our patients.
When we talk about the inspiratory time (iTime) on the jet ventilator, we typically start at a minimum of 0.02 seconds. This is about 25 times shorter than the 0.5-second iTime often used in conventional ventilation. This extremely short iTime is particularly useful in our smaller babies in the PICU versus the NICU. The main advantage of this very short inspiratory time is that it minimizes ventilation of the injured areas of the lungs.
For example, a short iTime of 0.02 seconds on the jet ventilator allows us to deliver significantly smaller tidal volumes, around one milliliter per kilogram, because it pierces through the dead space quickly.
These smaller tidal volumes allow for the safe utilization of much higher levels of PEEP. Moreover, the combination of small tidal volumes and a short iTime ensures that the peak inspiratory pressures (PIPs) used on the jet ventilator do not transmit to the alveoli, reducing the risk of further lung injury. The jet ventilator's settings, especially the short inspiratory time, enable it to provide effective ventilation while protecting the lungs from additional damage. This is particularly beneficial for patients with fragile lung tissues, ensuring they receive the necessary support without exacerbating their condition.
It is important to address a common concern about increasing jet PEEP. People often worry that a PEEP of 35 means the alveoli are seeing that exact pressure, but that is not the case. Due to the very small tidal volumes and short inspiratory times, the pressure tapers off significantly as it travels down the airways. While the PEEP at the end of the ET tube might be 35, the actual pressure reaching the alveoli is much lower, reducing the risk of damage.
Some physicians find this misconception challenging to understand. They might see a high PEEP number and assume It is what is reaching the patient's lower airways. However, with the jet ventilator, the fixed inspiratory time means that adjustments to the rate primarily affect the expiratory time, not the tidal volume.
Longer expiratory times are beneficial for patients with obstructive disease processes or for managing larger patients. We have used the jet ventilator in our PICU, which is not super typical but might be more common in other institutions. An important point to emphasize with our team, especially since our NICU team, accustomed to NICU settings, had to adapt to PICU settings.
Understanding these nuances helps ensure that the jet ventilator is used effectively and safely, providing the best possible care for our patients while mitigating potential risks. To manage larger patients effectively, we need to ensure longer expiratory times by adjusting either the iTime or the rates.
A shorter expiratory time, on the other hand, will increase minute ventilation, which is beneficial for restrictive disease processes. There are various theories about maintaining a fixed inspiratory time and its effects on expiratory time, as well as the patient populations that benefit from these settings.
HFJV PIP
Now, let's talk about the jet peak inspiratory pressure (PIP). The visual here helps illustrate that while the PIP might be set high on the jet ventilator, the actual pressure that reaches the distal airways and alveoli is significantly lower. This means that even if you set a higher jet PIP, it does not translate directly to the alveolar pressure, reducing the risk of lung damage.
Typically, we set the jet PIP higher or slightly higher than what was used during conventional mechanical ventilation. Due to the rapid inspirations, the PIP decreases quickly as the jet breaths travel down the airway. The peak alveolar pressure ends up being much lower than the peak airway pressure. By understanding and appropriately setting the iTime and PIP on the jet ventilator, we can tailor the ventilation to meet the needs of different patient populations, ensuring effective and safe respiratory support.
You do not need to be overly concerned about safety when increasing the jet PIP. In fact, increasing the jet PIP is the safest way to decrease PCO2 levels. More peak inspiratory pressure means more pressure and volumes are generated in the distal areas of the lungs. To effectively decrease CO2, you should increase your jet peak inspiratory pressure.
Servo Pressure
The jet ventilator also has a unique feature called servo pressure, which you will not find on the oscillator. If you understand it correctly, servo pressure can provide valuable information. Think of servo pressure as your driving pressure. Any changes in lung mechanics or volumes will affect the servo pressure.
Servo pressure is a generalized number specific to your patient at a given time, and it is important to note its trends. If the servo pressure is increasing, it typically indicates improved compliance and decreased resistance. This might mean better lung function or possibly a significant air leak around the ET tube or in the tubing. Monitoring this trend gives you insights into the patient's condition. Increasing the jet PIP safely reduces CO2 levels while monitoring servo pressure helps track lung mechanics and compliance, providing crucial information for managing patient care effectively.
Conversely, if our servo pressure decreases, it may indicate worsening compliance and increased resistance. This could be due to several issues, such as an obstructed ET tube that needs suctioning or a tension pneumothorax. It might also signal a misplaced intubation, like a right mainstem intubation. These conditions increase resistance, which in turn decreases servo pressure. Essentially, servo pressure going up is a positive sign, while a decrease suggests potential problems that need addressing.
Since servo pressure is specific to each patient's lung mechanics, it is important to monitor its trends rather than rely on a specific number. When you put a patient on the jet ventilator, observe their initial servo pressure and note its trajectory. Is it trending up or down? Is there an acute spike or drop, or is the change gradual over time? These observations provide valuable insights into the patient's condition.
Conventional Ventilation
Using a conventional ventilator in conjunction with the jet is crucial for two main reasons. Firstly, it controls the PEEP, which is not set on the jet ventilator. Secondly, the PEEP on the conventional ventilator becomes the main determinant of mean airway pressure. This setup ensures that we can manage and monitor the patient effectively, leveraging the strengths of both ventilation methods.
Mean airway pressure (MAP) is essentially a byproduct created by the PEEP and jet PIP settings, along with any sigh breaths or similar interventions. When facing issues with oxygenation, increasing the PEEP on your conventional ventilator will provide the most significant improvement.
Regarding the mode of the conventional ventilator, the choice depends on the patient's condition. For instance, if a patient has hyperinflation or an air leak, CPAP (Continuous Positive Airway Pressure) is preferable. CPAP maintains a steady pressure and avoids large breaths that could worsen the condition. We do not want big sigh breaths in these cases, as they could exacerbate the air leaks.
On the other hand, if recruitment is the goal, assist control or pressure control modes are more appropriate. For example, when the ventilator is set to deliver occasional large breaths at a low rate (anywhere from zero to five breaths per minute), then these larger breaths, or sigh breaths, help re-expand collapsed areas of the lung. However, it is crucial to ensure these sigh breaths are not larger than the jet PIP to avoid interrupting the jet propulsion.
If hyperinflation or air leaks are present, we want to avoid these large stretches and sighs because the lungs are already fragile and prone to leaking. Instead, maintaining a steady pressure with CPAP can help stabilize the lungs without causing additional damage. Choosing the appropriate mode on the conventional ventilator—whether CPAP for stability in hyperinflated or leaking lungs or assist control for lung recruitment—depends on the specific needs and condition of the patient. This strategic use of ventilation settings ensures optimal care and minimizes the risk of further lung injury.
Often, we start with a CPAP mode to monitor and allow the air leak to dissipate. Once the air leak has improved, we can gradually transition to assist control/pressure control (AC/PC) to slowly recruit the lungs. We might start by setting the rate to one, then increase it to three, and gradually continue to see if the air leak reappears or if we observe lung recruitment and improvement.
Conventional Ventilation with HFJV
When comparing conventional ventilation with jet ventilation, the differences in how PEEP and sigh breaths affect mean airway pressure (MAP) become evident. On a conventional ventilator, if we set a PEEP of 6, the MAP is at a baseline level. Increasing the PEEP to 8 results in a significant increase in MAP. Further increasing the PEEP to 10 leads to another noticeable rise in MAP. This demonstrates that PEEP is the primary factor in raising MAP because it increases expiratory pressure.
When using sigh breaths to recruit the lungs, we start with a PEEP of 6. As we increase the PEEP, the MAP goes up significantly. However, introducing sigh breaths changes the dynamic. With a very low rate on the conventional ventilator, these sigh breaths involve larger volumes and longer inspiratory times, which temporarily increase the MAP more dramatically.
Managing ventilation effectively requires understanding how adjustments in PEEP and the use of sigh breaths can influence MAP. Starting with CPAP to stabilize air leaks and then transitioning to AC/PC for gradual lung recruitment helps optimize patient care.
HFJV Management
Even without adjusting the PEEP, introducing sigh breaths increases the mean airway pressure. This happens because the sigh breaths open and stretch the collapsed airways, which helps with lung recruitment. Sigh breaths can be used to re-recruit lung areas, while adjustments to PEEP are primarily for increasing mean airway pressure and improving oxygenation. For management, here are some suggestions based on what we use institutionally:
- Jet Valve Time: Start at 0.02 seconds. Always consider the I:E ratio and be cautious about increasing iTime without accounting for eTime to avoid air trapping.
- Jet Rate: For neonates, typically start at around 420 breaths per minute. For pediatrics, a bit lower at 300 breaths per minute to ensure sufficient eTime.
It is critical to balance these settings to optimize patient care and avoid complications like air trapping. By carefully adjusting the jet valve time and rate, we can provide effective ventilation tailored to each patient's needs. If you need to decrease CO2, you can increase the jet rate. Conversely, if you are concerned about air trapping or hyperinflation or if the expiratory time (eTime) is not long enough, you can decrease the jet rate.
The jet PIP is critical for adjusting ventilation. Typically, we start with a jet PIP that provides desirable CO2 levels. To blow off more CO2, you can increase the jet PIP, and if you have reduced CO2 too much, you can decrease the jet PIP to let CO2 levels rise a bit. For the conventional ventilator, if you are using a recruitment maneuver with assist control, pressure control style ventilation, set the rate between zero to five breaths per minute.
This helps recruit more alveoli and minimizes volume trauma or hemodynamic compromise. The conventional PEEP should be just high enough to achieve chest rise without interrupting the jet breaths. You do not want the jet propulsions to pause when a sigh breath is given, so it should be continuous.
By setting the PEEP appropriately, you can improve atelectasis and minimize volume trauma or hemodynamic compromise. PEEP can be adjusted as needed, though it can be a bit daunting, especially in the NICU world, depending on physician comfort levels.
- Jet Rate: Increase to decrease CO2; decrease to avoid air trapping or hyperinflation.
- Jet PIP: Adjust based on CO2 levels; increase to reduce CO2, decrease to allow CO2 to rise.
- Conventional Ventilator: Use assist control, pressure control with a rate of zero to five breaths per minute for recruitment.
- PEEP: Set high enough for chest rise without interrupting jet breaths, adjusting as necessary to manage atelectasis and minimize trauma.
PEEP is your main determinant of oxygenation. To improve oxygenation, you can increase PEEP. For weaning or if there is a hemodynamic compromise, you might need to decrease it, especially if you have generated too much mean airway pressure.
The conventional ventilator inspiratory time (iTime) should be set anywhere from 0.35 to one whole second. A longer iTime elongates the sigh breath, generates more mean airway pressure, and improves atelectasis. However, if there is volume trauma or hemodynamic compromise, you might need to decrease the iTime, just as you would adjust the conventional rate.
High Frequency Oscillatory Ventilation
Figure 3. Example of High Frequency Oscillatory Ventilation (Brian Hall, Public domain, via Wikimedia Commons).
What is HFOV?
Now, let’s discuss oscillatory ventilation seen in Figure 3. The oscillator might look old-fashioned, but it is effective—“if it isn’t broken, don’t fix it,” right? Here's an overview of the key components of the oscillator:
- Mean Airway Pressure (MAP): Located in the top left corner, this is created by adjusting the combination of the adjust knob and the bias flow.
- Alarm Settings: These are small but efficient and located conveniently for quick access.
- Piston Position: This is an essential part of the oscillator, which we will delve into shortly.
The oscillator’s setup includes various dials and knobs, which might seem complex at first glance, but each serves a critical function in managing ventilation effectively. The mean airway pressure, for instance, is crucial for maintaining adequate oxygenation and ventilation in patients, and it is controlled through specific settings and adjustments.
- PEEP: Increase for better oxygenation, decrease for weaning, or if there is hemodynamic compromise.
- iTime: Longer for better atelectasis management, shorter if there are issues with volume trauma or hemodynamic stability.
- Oscillator: Effective, with important controls like the mean airway pressure and piston position, providing precise ventilation management.
How does HFOV work?
Understanding and utilizing these settings appropriately can significantly enhance patient care and outcomes in both conventional and oscillatory ventilation scenarios. The oscillator, another type of mechanical ventilation, uses very small tidal volumes at very high frequencies, similar to the jet ventilator. However, it operates at a constant descending airway pressure, allowing you to set the mean airway pressure (MAP) directly. This is different from the jet ventilator, where MAP is secondarily created by PEEP, sigh breaths, and jet PIP.
Key Components of the Oscillator:
- Amplitude or Delta P: Controlled by the power knob, it affects the volume of oscillation.
- Percentage of iTime: This is set as a percentage, unlike the time settings on other ventilators.
- Frequency: Located below the iTime setting, it determines the rate of oscillation.
Advantages of the Oscillator:
- Lung Recruitment: By setting the MAP, you can maintain consistent lung recruitment.
- Avoiding Overdistension: Helps in avoiding overdistension of lung tissue.
- Decreasing Vent-Induced Lung Injury: Overall, it reduces the risk of lung injury caused by the ventilator.
There are two models of the oscillator:
- Oscillator A: HFOV A ≤35kg
- Oscillator B: HFOV B >35k
The FDA has a weight cutoff of 35 kilos for these devices. While It is sometimes necessary to exceed this limit based on patient needs, it should always be done with team approval and careful consideration of the patient's condition.
Diaphragm/Piston
The oscillator features a diaphragm piston, which plays a crucial role in its operation. This piston moves to create the oscillations needed for ventilation. By setting the MAP directly on the oscillator, you can maintain the desired pressure and lung recruitment without relying on secondary factors like PEEP or sigh breaths.
The oscillator provides precise control over mean airway pressure, making it effective for maintaining lung recruitment and minimizing lung injury. By understanding its components and operation, healthcare providers can use it to optimize patient care in critical situations.
Within the oscillator, there is a piston driven by an electromagnetic coil. This mechanism pushes a flexible diaphragm made of black canvas material. When the diaphragm moves forward, it creates active inspiration by pushing flow and pressure into the patient. When it swings backward, it creates active exhalation by sucking the air back out. This bidirectional movement generates the oscillation and pressure needed for ventilation.
Key Features of the Oscillator:
- Active Inspiration and Exhalation: The diaphragm's forward movement forces air into the patient, while its backward movement sucks air out. This active process differentiates the oscillator from other ventilators.
- Tidal Volumes: The oscillator can deliver tidal volumes that are less than or equal to the dead space volume, making it highly effective for delicate ventilation needs.
The oscillator delivers tidal volumes of about one to four milliliters per kilogram, which is slightly higher than what the jet ventilator provides. It also employs a more laminar flow compared to the jet's transitional flow. This difference means the oscillator is not as effective at piercing through dead space.
For patients with conditions like RSV bronchiolitis, the jet might be a better option because it can pierce through secretions and potentially help clear them from the airway. In contrast, the oscillator could push these secretions further down, potentially causing complications.
Mean Airway Pressure (MAP)
Mean airway pressure (MAP) is the primary determinant of oxygenation for the jet ventilator. If oxygenation issues occur, increasing the MAP is necessary. This adjustment helps ensure adequate oxygenation by improving overall lung recruitment and gas exchange efficiency.
- Oscillator Tidal Volumes: Slightly higher (1-4 mL/kg) with more laminar flow.
- Jet Tidal Volumes: Better at handling secretions due to transitional flow.
- Mean Airway Pressure (MAP): The primary determinant of oxygenation in
When adjusting the MAP on the jet ventilator, It is necessary to do so very slowly. Specifically, adjusting PEEP, it can take several hours to see the effects of the change, especially when weaning. If you encounter an eager attending who wants immediate results, it is important to be the voice of reason and remind them that patience is necessary. Adjusting the MAP should be done incrementally and then monitored over a few hours to ensure that it does not cause any complications.
Each patient has a different threshold or tolerance for high MAPs, largely influenced by their venous return. High MAPs can impact venous return and cardiac output, so close monitoring and gradual adjustments are essential to avoid hemodynamic instability.
- Slow Adjustments: Make changes to MAP slowly and wait several hours to observe the effects.
- Patient-Specific Tolerance: Each patient’s tolerance for high MAPs varies, influenced by their venous return.
- Monitor Gradually: Be cautious and monitor the patient closely after any adjustments to avoid complications.
While adjusting MAP is critical for managing oxygenation, it must be done with caution and patience. Ensuring a gradual approach and closely monitoring the patient’s response will help avoid potential issues and provide the best care. Depending on the state of their disease process, some patients can tolerate mean airway pressures in the 30s or 40s, while others may experience significant drops in blood pressure at much lower settings, such as 23. This variation occurs because the lungs and heart share the confined space within the thoracic cavity. When the lungs expand and take up more room, the heart has less space to function properly.
Effects of High Mean Airway Pressure:
- Reduced Cardiac Space: As the lungs expand with higher mean airway pressures, they can compress the heart.
- Impaired Cardiac Function: Compression of the heart can prevent it from contracting and relaxing properly.
- Inadequate Filling: If the heart cannot fill properly due to compression, it can lead to reduced cardiac output and potentially plummeting blood pressure.
Considerations:
- Individual Tolerance: Each patient’s tolerance to high MAPs varies widely, influenced by their specific condition and overall thoracic compliance.
- Monitoring: Close monitoring of blood pressure and cardiac function is essential when adjusting MAP to avoid adverse effects.
When adjusting MAP, It is vital to consider the unique tolerance levels of each patient. Monitoring and adjusting slowly can help prevent complications related to the confined space of the thoracic cavity and ensure optimal patient care. If the heart does not fill appropriately, it cannot pump blood effectively, leading to an acute drop in blood pressure. Each patient has a different threshold for mean airway pressure (MAP). A simple guideline we teach our respiratory therapists is if increasing the MAP from 24 to 25 causes the blood pressure to plummet, return to 24, and the blood pressure should stabilize.
Practical Tips:
- Threshold Awareness: Each patient has a unique MAP threshold.
- Immediate Response: If an increase in MAP causes a significant drop in blood pressure, revert to the previous setting.
- Team Discussion: Communicate with the healthcare team about the need for higher MAP and consider supportive measures.
When discussing with your team, consider the following:
- Fluid Bolus: Administering fluids can help support blood pressure.
- Vasopressors: If not already in use, adding vasopressors may be necessary to maintain adequate blood pressure.
By understanding and managing these nuances, you can ensure that adjustments to MAP are made safely and effectively, maintaining optimal patient care and avoiding complications. Having an arterial (art) line can be very beneficial for these patients. I understand that at our institution, we are trying to minimize the use of additional lines due to infection risks, only using them when absolutely necessary. However, if you do not have an art line, it is crucial to continuously monitor blood pressure, especially when making adjustments and initially setting up the oscillator.
One way to determine if you have set the mean airway pressure (MAP) correctly or if you have gone too high or have more room to increase it is by using a chest X-ray. For example, if the chest X-ray shows that the lungs are only expanded to eight ribs, this could indicate that the MAP might need to be adjusted. While minimizing infection risks is important, ensuring accurate and continuous monitoring of blood pressure is crucial when adjusting MAP. Utilizing chest X-rays can also provide valuable information to guide these adjustments and ensure optimal lung expansion and patient care.
When evaluating mean airway pressure (MAP), a chest X-ray can be extremely informative. For instance, if the X-ray shows lung expansion up to only eight ribs, you know there is room to increase the MAP to expand the lungs further. On the other hand, if the X-ray reveals that the lungs are expanded to 12 ribs, you should stop increasing the MAP to avoid the risk of causing a pneumothorax, even if the patient is hemodynamically stable.
- Chest X-Ray Monitoring: Use X-rays to gauge lung expansion.
- Under-Expansion: If only expanded to eight ribs, consider increasing MAP.
- Over-Expansion: If expanded to 12 ribs, avoid further increases to prevent pneumothorax.
In standard mechanical conventional ventilation, the pressures swing between inspiratory peaks and drops during exhalation. This pattern shows how pressure changes during the breathing cycle and how adjustments to mean airway pressure (MAP) can influence lung expansion. With conventional ventilation, the MAP is typically around 25. The oscillator, on the other hand, maintains a fixed MAP of 30. The piston in the oscillator swings back and forth, creating small, rapid oscillations. This process involves a Delta P, which we discuss in more detail, contributing to the consistent maintenance of the MAP.
Key Differences Between Conventional Ventilation and Oscillator:
- Conventional Ventilation:
- MAP: Around 25
- Pressure Swings: Large swings between inspiratory and expiratory pressures
- Lung Impact: Higher potential for lung damage due to larger pressure swings
- Oscillator:
- MAP: Fixed at 30
- Piston Movement: Small, rapid swings (Delta P)
- Frequency: Set frequency determines the rate of oscillation
- Lung Impact:
- Less lung damage due to smaller, quicker oscillations, maintaining higher MAP without large pressure swings
The oscillator achieves a higher MAP with much smaller swings, reducing lung damage. This method avoids the significant stretches of inspiratory pressure and the drops during the expiratory phase, providing a gentler and more consistent approach to ventilation.
Amplitude (∆ P)
When it comes to amplitude, also known as Delta P, this is what actually drives the size of our tidal volume. Amplitude is a secondary effect based on where we set the power knob next to our Delta P. Adjusting the power controls the piston's movement, determining the size of the swings and, consequently, the tidal volume. Manipulating the amplitude is crucial for ventilation management.
- Amplitude/Delta P: Determines the size of the tidal volume.
- Power Knob: Adjusts the piston's movement to set the amplitude.
- Ventilation Impact:
- Increasing Amplitude: Increases Delta P, which in turn increases tidal volume.
- Decreasing Amplitude: Reduces Delta P, thus reducing tidal volume.
By increasing the amplitude, you inadvertently increase the tidal volume, which helps to decrease carbon dioxide (CO2) levels. This is because larger tidal volumes enhance CO2 removal from the lungs, improving overall ventilation.
Practical Application:
- To Decrease CO2: Increase the amplitude (Delta P) to raise the tidal volume.
- To Increase CO2: Decrease the amplitude to lower the tidal volume.
Adjusting the amplitude is a vital tool for effectively managing a patient's ventilation needs. Understanding this relationship allows for precise control over CO2 levels and overall respiratory function. Conventional ventilation creates large pressure swings, with the tidal volume represented by the difference between the peak inspiratory and expiratory pressures. In the case of the oscillator, the Delta P represents the amplitude. The width of this Delta P determines the generated tidal volume.
Key Concepts:
- Conventional Ventilation: Features large pressure swings to achieve tidal volume.
- Oscillator: Uses Delta P (amplitude) to generate tidal volume.
- Delta P: The distance between the two dotted lines; a wider Delta P means a larger tidal volume.
One crucial aspect of Delta P or amplitude is that it controls the chest wiggle. This wiggle is a visible indicator that the amplitude is set correctly. For initial settings, ensuring that the amplitude is sufficient to create a noticeable chest wiggle is vital.
Practical Application:
- Delta P (Amplitude): Controls the size of the tidal volume and the chest wiggle.
- Chest Wiggle: A visual cue indicating proper amplitude settings.
By setting the amplitude appropriately, you can ensure effective ventilation and monitor the patient's chest wiggle as an immediate indicator of correct settings. When manually ventilating someone, you want to apply enough pressure to get the chest to move. With the oscillator, you want to set the amplitude high enough to get a noticeable chest wiggle. For children and adults, the wiggle should be visible from the chest down to the mid-thigh.
In neonates, it typically extends from the chest to the umbilicus. Neonates often have more pronounced wiggles, sometimes even extending to their toes, but ideally, you want to see it reach their umbilicus to ensure you have set a good initial amplitude.
When you are setting the oscillator, keep an eye on that chest wiggle. For adults and kids, look for movement down to the mid-thigh. For neonates, aim for movement up to the umbilicus, even if it sometimes goes further. This visible chest wiggle is your immediate cue that you have set the amplitude correctly, ensuring proper ventilation for the patient.
Frequency
When it comes to the oscillator's frequency, it is important to remember that it is different from the respiratory rate we are used to. Frequency controls the time allowed for the piston to move back and forth. Essentially, it determines how quickly the piston oscillates within a given time frame. To put it into perspective, the oscillator can operate anywhere from 3 to 15 hertz. Remember, 1 hertz equals about 60 breaths per minute. With the oscillator you are looking at frequencies ranging from 180 to 900 breaths per minute. It moves incredibly fast!
Key Points about Frequency:
- Frequency vs. Respiratory Rate: Unlike the traditional respiratory rate, the frequency on an oscillator determines the piston’s oscillation speed.
- Range: The oscillator operates between 3 to 15 hertz.
- Conversion: 1 hertz is roughly equal to 60 breaths per minute, translating to 180 to 900 breaths per minute on the oscillator.
Understanding this helps you set the oscillator correctly and ensure It is providing the rapid, small-volume breaths necessary for effective ventilation. Absolutely, the frequency of an oscillator has a big impact on tidal volume. When you lower the frequency, say to 4 Hz, you get a greater tidal volume. Essentially, when the frequency is lower, the piston has more time to move back and forth, which increases the tidal volume.
Now, this is where it gets interesting: at a cellular level, the slower the movement, the more time CO2 and O2 have to exchange and diffuse. This means that by moving slower, you allow for better gas exchange. Contrary to what we might initially think as respiratory therapists, decreasing the frequency actually helps blow off more CO2. Lower frequency means larger tidal volumes. Slower frequencies allow more time for gas exchange. Decreasing frequency helps blow off more CO2, which is a bit counterintuitive for us.
This is an important concept for effectively setting and managing the oscillator to ensure proper ventilation and CO2 removal. If you have blown off too much CO2, you will want to increase the hertz. We typically adjust this by about one hertz at a time since changing the rate by 60 breaths per minute is quite significant, and we prefer not to make overly dramatic adjustments.
Bias Flow
When it comes to the bias flow on the oscillator, it is important to set it correctly, as it controls the flow rate of the humidified fresh gas. You need to ensure It is neither too high nor too low, as this helps in generating the desired mean airway pressure. On Oscillator A, the maximum bias flow you can set is 40 liters per minute, while on Oscillator B, it can go up to 60 liters per minute.
If you need to fine-tune your settings:
- Increase the hertz in small increments to manage CO2 levels.
- Adjust the bias flow carefully to regulate the flow rate and support proper mean airway pressure.
By making these adjustments thoughtfully, you can effectively manage ventilation and ensure the patient is receiving the appropriate support. The bias flow, in conjunction with the adjust knob, is crucial for creating your mean airway pressure. You use the bias flow and the adjust knob to balance each other. The adjust knob has a specific range for optimal performance. If you imagine the knob as the hand of a clock, you want it to be between the 10 o'clock and 2 o'clock positions.
If the adjust knob is before the 10 o'clock position, it indicates too much bias flow, and you need to reduce it to bring the knob back within the desired range. Conversely, if the knob is at the 2 o'clock position, it means there is not enough bias flow, so you will need to increase it. Keeping the adjust knob and bias flow within this "happy" range ensures the ventilator functions optimally.
When I first started at Nemours, we did not have an ECMO team, and we relied heavily on the oscillator for very sick kids in our PICU. Often, we had to max out the settings, with the bias flow up to 60 and the adjust knob turned all the way to maximum. However, the ventilator does not operate efficiently when pushed to its limits like that. It is always better to keep the settings within their optimal ranges to maintain the ventilator's performance and avoid overworking it.
If you push the ventilator too hard, it can overheat and shut down. Maintaining the balance between the adjust knob and the bias flow is crucial to prevent overheating and excessive bias flow, which could potentially cause a pneumothorax. Keeping these settings in check ensures the ventilator operates smoothly and safely.
Inspiratory Time
We typically set the inspiratory time at 33%, which gives a 1:2 ratio. This setting is a result of the rate and a set percentage of the respiratory cycle. Although 33% is common, it is not fixed and can be adjusted. The diaphragm excursion can be asymmetrical, spending more time in the inspiratory phase. This can help create more mean airway pressure if needed.
While we usually stick to 33%, you can increase it up to 50% in certain situations. This can be a last-ditch effort to help with ventilation and generate larger tidal volumes, aiding in lung recruitment and potentially improving oxygenation. However, the literature supporting this is not robust, so it should be considered only when all other options are exhausted.
HFOV Management
Initial Settings at Nemours:
- FiO2: Start at 100% for these patients, then quickly wean down to less than 60% as soon as possible to maintain safe oxygen saturation levels.
- Mean Airway Pressure (MAP): Begin with the conventional MAP, then increase by about 3 to 5 centimeters above the conventional ventilator MAP. In the NICU, we usually go 2 to 3 centimeters above, while in the PICU, It is closer to 5 centimeters above.
- Inspiratory Time: Typically set at 33%, providing a 1:2 I:E ratio.
- Bias Flow: For Oscillator A, start at 15 liters per minute, and for Oscillator B, start at 20 liters per minute. Adjust quickly to maintain the adjust knob in the optimal position and achieve the desired MAP.
- Amplitude: Rather than setting the amplitude directly, adjust the power to achieve the desired chest wiggle. The power setting will dictate the amplitude, ensuring effective ventilation.
By following these initial settings and making necessary adjustments based on the patient's response, we can effectively manage ventilation with the oscillator. This approach helps ensure adequate oxygenation and ventilation while minimizing the risk of complications. Starting with the power settings on the oscillator, Vyaire's recommendations are a good guide. For Oscillator A, you can set the power to 2.0, place it on the patient, and adjust based on the initial amplitude you observe. From there, you adjust the power up until you see an adequate chest wiggle. For Oscillator B, start with a power of 4.0 and follow the same process.
I often joke with new therapists about how doctors sometimes "order" an amplitude, like 50, without a specific rationale. It is more of an estimation when initially setting up a patient. Using the power method takes the guesswork out of it and provides a reliable starting point. Frequency Settings Based on Patient Size and Disease Process:
- Premature Babies: Typically need a very high frequency, around 12 to 15 Hz, due to their delicate and small lung volumes.
- Neonates: A slightly lower frequency, about 10 to 12 Hz.
- Children: Frequencies are adjusted down further as the size increases, usually around 8 to 10 Hz.
- Adolescents/Teenagers: Frequencies are set lower still, around 6 to 8 Hz, to accommodate larger lung volumes.
By setting the frequency based on patient size and their specific disease process, you can ensure effective ventilation. This gradual adjustment aligns with the patient's needs and helps maintain optimal respiratory function. For adults, the frequency on the oscillator is typically set between 4 to 6 Hz. As the patient size increases, the frequency decreases accordingly. In pediatric care, seeing an oscillator moving slowly, with a low frequency, usually signals serious ventilation issues. For instance, if you see a child on a frequency of 4 Hz, It is not ideal and often means we are facing significant challenges with ventilation.
When it comes to medical management with an oscillator, improving oxygenation involves increasing the FiO2 and mean airway pressure. You achieve this by adjusting the bias flow and the adjust knob. If we are focusing on ventilation, increasing the amplitude is key. Since we cannot set the amplitude directly, we increase the power to generate a higher amplitude. Additionally, lowering the frequency helps, as does increasing the inspiratory time percentage—though that's more of a last-resort tactic.
There is also a technique called creating a controlled ET tube cuff leak. This helps with ventilation by allowing some pressure to escape. However, it must be done carefully to avoid losing the mean airway pressure you have worked so hard to maintain. If you just drop the cuff haphazardly, you could lose all that pressure, which could lead to problems with oxygenation.
To sum it up, when you are trying to improve oxygenation, you look at increasing the FiO2 and mean airway pressure by tweaking the bias flow and adjust knob. For better ventilation, you boost the amplitude by increasing the power, lowering the frequency, and maybe even extending the inspiratory time if necessary. If things are really tough, you might consider a controlled ET tube cuff leak to help with ventilation without losing your precious mean airway pressure. This kind of careful management ensures that we address the patient’s specific needs effectively.
A tactical way to create a controlled ET tube cuff leak is by first increasing your mean airway pressure (MAP) by five. For example, if your current MAP is 25, increase it to 30. Then, use a syringe to slowly deflate the cuff until the MAP returns to the original setting of 25. This method allows you to create a purposeful leak in a controlled manner, minimizing the risk of large swings in MAP that might occur with an uncontrolled leak. By doing this, you enable CO2 to exhale around the ET tube, mimicking passive exhalation. Since oscillators do not have passive exhalation, this technique helps improve ventilation by allowing some of the exhaled gases to escape around the ET tube cuff.
HFOV vs HFJV
When comparing the jet ventilator and the oscillator side by side, you will notice that both deliver tidal volumes of about one to four milliliters per kilogram. The iTime on the oscillator is a result of the rate and set percentage. For the jet ventilator, the iTime is set directly and results in a similar tidal volume range. To recap this method: increase your MAP by five units, then slowly deflate the ET tube cuff with a syringe until the MAP returns to its original value.
This controlled approach helps facilitate CO2 exhalation and can improve ventilation. The jet and oscillator ventilators both deliver small tidal volumes, but their mechanisms and control settings differ, with the jet having a direct iTime setting and the oscillator relying on rate and percentage for iTime.
The inspiratory time (iTime) on an oscillator is a result of the rate and a set percentage of the respiratory cycle, not measured in seconds but as a percentage. The oscillator features active exhalation, which is different from other ventilators. However, one drawback is the potential loss of mean airway pressure (MAP) during suctioning. When you first put a patient on an oscillator, suctioning is usually avoided.
Inline suctioning while the oscillator is running is often ineffective because secretions tend to be caked down. Effective suctioning would require disconnecting the patient from the oscillator and performing vigorous manual ventilation and suctioning. However, physically disconnecting the patient can cause a significant loss of MAP.
Key Points on Oscillator Use:
- Indications: The oscillator is particularly useful for conditions like RDS (Respiratory Distress Syndrome) and pulmonary hyperplasia. It is ideal for managing oxygenation issues because you can directly set the MAP.
- Contraindications: Hemodynamic instability is a potential issue because adjusting the MAP has a direct and powerful effect. High MAP settings can increase intracranial pressure (ICP). Additionally, air leak syndrome is not ideally managed with oscillators.
The oscillator’s ability to set MAP directly makes it excellent for oxygenation issues. However, caution is needed due to the potential for hemodynamic instability and increased ICP. For patients with air leak syndrome, other ventilatory strategies might be more appropriate. The jet ventilator delivers tidal volumes closer to one milliliter per kilogram, which is slightly smaller than what the oscillator delivers.
Unlike the oscillator, the iTime on the jet is physically set, and it operates with passive exhalation. This difference is crucial, as the jet’s passive exhalation makes it easier to suction patients. The helix flow of expiratory gases helps move secretions up around the ET tube, reducing concerns about MAP drops during suctioning.
Key Points:
- Jet Ventilator:
- Tidal Volume: Approximately one ml per kilo.
- iTime: Physically set.
- Exhalation: Passive, unlike the oscillator's active exhalation.
- Suctioning: Easier due to passive exhalation and helix flow, which assists in moving secretions.
Indications for the Jet:
- Pulmonary Interstitial Emphysema (PIE): The jet is effective for patients with air leak syndromes.
- Airway Clearance: Ideal for patients with many secretions, as it can facilitate better clearance.
- Ventilation Issues: More suitable for addressing ventilation problems due to its passive exhalation.
Contraindications for the Jet:
- Asthmatics: This is not ideal for patients with severe air trapping, as passive exhalation might not be sufficient to manage their condition.
Comparisons with the Oscillator:
- Flow Characteristics: The oscillator’s smoother, less transitional flow can lead to spikes in tidal volume and pressure in damaged lung areas, potentially hindering the healing process.
- Exhalation: The jet's passive exhalation contrasts with the oscillator's active exhalation, making the jet more suitable for conditions requiring gentle ventilation.
- MAP and Suctioning: The jet allows for easier suctioning without significant MAP loss, unlike the oscillator, which can lose MAP during suctioning.
The jet ventilator is preferable for conditions like PIE, significant secretion clearance, and ventilation issues due to its smaller tidal volumes, passive exhalation, and ease of suctioning. Conversely, it is not ideal for patients with severe air trapping, such as asthmatics. The oscillator, with its ability to set MAP directly, is better for managing oxygenation issues but requires careful handling to avoid complications from its active exhalation and potential for increased intracranial pressure.
Essentially, adding air trapping on top of existing air trapping is definitely not good. Let’s talk about how air is delivered to patients using different ventilators. When you look at the jet ventilator, you will notice the jet PEEP starts high but drops significantly from the trachea to the alveoli. This drop means you should not be too worried about the initial high jet PEEP setting.
However, you will also see the mean airway pressure (MAP) drops a bit as well, making the jet ventilator less ideal for patients struggling with oxygenation issues. On the other hand, the oscillator shows big swings in pressure. Although the pressure dissipates as it does in the jet, the oscillator maintains a more consistent MAP throughout the airway. This consistency makes it a better choice for tackling oxygenation problems.
Comparing the Two:
- The jet ventilator is great for patients with ventilation issues or those needing better secretion clearance. The drop in jet PEEP and MAP makes it less suitable for severe oxygenation problems.
- The oscillator, with its consistent MAP, is better for patients with oxygenation issues. However, it is not the best for those with air trapping or significant secretion clearance needs.
Next time you are in the NICU and a doctor suggests putting a patient on the oscillator, you can take a moment to evaluate the situation. If you think the patient might benefit more from the jet ventilator, you can speak up and explain why, based on the patient’s specific needs and the strengths of each ventilator. Understanding these differences allows you to make informed decisions.
Whether it is advocating for the jet for better secretion management and ventilation or the oscillator for consistent oxygenation, you will be able to confidently suggest the best option for your patient. The jet ventilator offers passive exhalation and transitional flow, which can be advantageous in many situations. Understanding these details helps solidify your expertise as RTs at the bedside.
Questions and Answers:
The ET tube size is greater than the jet ventilator adapter. What are some options?
It kind of depends. You just have to take into consideration that if you are trying to use a jet ventilator adapter or a life port adapter that is not the appropriate size for the ET tube; you are going to get leaks. I know we have all been MacGyvers in our units and gotten creative to eliminate those leaks. You could, although I do not really recommend this, put tape around the adapter to make it a little thicker, but just know it is not going to be the same quality. If you are looking for true jet ventilation, you really should be using the correct adapter size. So keep in mind, if it is not working effectively, it might not be that the jet ventilation failed your patient. I would say that we do not have the proper equipment to appropriately provide this care to this patient.
Is there an upper limit where increasing power further provides no added benefit or even becomes detrimental?
When you think about a conventional ventilator, there comes a point where, as we turn it higher and higher, we have to consider what we are really doing to those airways over time. When it comes to a patient being on the oscillator, you have to weigh your options. An oscillator is generally more gentle than pressure-control-style ventilation or anything like that. When you increase the power on an oscillator, it increases the amplitude, which then increases the tidal volume. You have to do what is best for the patient, making sure you are providing appropriate chest wiggle and ventilation. Unfortunately, it comes down to doing what is best for the patient. I do not believe there are any studies that show if you went up to a power of six and it gave you an amplitude of 120, that you are definitely causing damage. It is more about doing what is necessary to move the patient's chest at that point.
Regarding maximum bias flows on both oscillator models, are there any humidity or temperature considerations at those higher flow rates?
The oscillator uses a single-limb humidified circuit, so the inspiratory limb is humidified. As long as you maintain your heater, ensure it is filled with water, and everything is working correctly, you should not have to worry about humidity or temperature. However, one thing to consider is that the expiratory line of the oscillator is not heated. This can lead to condensation buildup, especially in areas with dependent loops. When the heated, humidified gas cools, it creates droplets that form puddles in the circuit. you will see these sloshing around, which can cause your mean airway pressure (MAP) to fluctuate. To manage this, try to keep the circuit as parallel as possible to the patient's bed. This helps prevent condensation buildup. But overall, at higher flows, the humidity should still be maintained as set by your heater.
Are there certain disease states or conditions where accurately judging the appropriate chest wiggle becomes more challenging?
100%. You have to consider patients who are experiencing a really bad surge response or severe anasarca. These patients have very fluid-overloaded tissue, making their skin very taut and puffy. Their skin can be so tight that you cannot really see the chest wiggle. In these cases, you might have to put your hand on their chest to feel the intensity of their wiggle. Getting close and observing at eye level can also help you see the subtle movement. For these patients, it is more about detecting any wiggle rather than the intensity of it. You may need to get a little creative in finding the best way to visualize the chest wiggle, especially in patients with anasarca or systemic inflammatory response syndrome where it can be very difficult to see.
References
Bunnell Incorporated. (2022). Bunnell Ventilator User Guide. Retrieved from https://bunl.com/bunnell-guides-manuals/
Vyaire Medical. (n.d.). Clinical Education. Retrieved from https://www.vyaire.com/clinical-education
Young, D., Lamb, S. E., Shah, S., MacKenzie, I., Tunnicliffe, W., Lall, R., Rowan, K., Cuthbertson, B. H., & OSCAR Study Group (2013). High-frequency oscillation for acute respiratory distress syndrome. The New England journal of medicine, 368(9), 806–813.
Vyaire Medical. (2020). 3100A High Frequency Oscillatory Ventilator Operator’s Manual. https://www.vyaire.com/sites/us/files/2020-05/33437-001-a-operators-manual-3100a-hfov.pdf
Miller, A. G., Bartle, R. M., & Rehder, K. J. (2021). High-Frequency Jet Ventilation in Neonatal and Pediatric Subjects: A Narrative Review. Respiratory care, 66(5), 845–856.
Citation
Massa, K. (2024). MD flavor of the month…high frequency jet versus oscillatory ventilation. Continued.com - Respiratory Therapy, Article 233. Available at www.continued.com/respiratory-therapy
May 28, 2024
1 CE HourRespiratory Concerns for the Premature Infant
Tina Pennington, MNSc, RNC-NIC
Editor’s note: This text-based course is an edited transcript of the webinar, Respiratory Concerns for the Premature Infant, presented by Tina Pennington, MNSc, RNC-NIC.
Learning Outcomes
After this course, participants will be able to:
- Examine two pathological lung conditions common in premature infants, including acute chronic phases.
- Compare contrast key points to improving positive pressure ventilation (PPV) utilizing Neonatal Resuscitation guidelines.
- Distinguish the role of multi-disciplinary team follow-up in the care of premature infants.
Introduction
- Premature birth refers to any delivery before 37 weeks gestation
- Its complications are the leading cause of newborn death in the U.S
- In the U.S. approximately 380,000 babies are born premature every year.
- 10.1% of total live births
- 1/10 babies are born too soon
- Depending on where you live or your race/ethnicity the rate can be higher
I always love to open up my talks with a few statistics that give you the scope of the problem I am discussing. Premature birth refers to any delivery before 37 weeks gestation, and its complications are the leading cause of newborn death in the United States. Some complications are cerebral palsy, learning disabilities, chronic lung diseases, blindness, and hearing loss, to name a few. In the United States, approximately 380,000 babies are born prematurely every year. One out of every ten babies is born too soon. That is one out of ten, too many. Depending on where you live or your race or ethnicity, that rate can be higher.
Figure 1. March of Dimes Report Card.
I love this map from the March of Dimes in Figure 1. It shows a grade. Here is your grading card. Your reds are your Fs, and your purples are your A's. I practice here in Arkansas, and it is an "F," which is sad for me. We need to find out what they are doing in Vermont. After all, Vermont is the only one with an A score, paralleling the maternal mortality map. Anytime you are having issues with maternal mortality or morbidity with the mother, you are going to have it with the infant. Much of what we do as professionals are to combat this, and some facilities out of California have studied maternal mortality. California has some good numbers, and they have lots of educational tools that we use to help combat prematurity and maternal mortality. They go hand in hand with the newborn diagnoses and treatment outcomes of the common pulmonary diseases.
Common Pulmonary Diseases of the Newborn
Diagnosis, Treatments, & Outcomes
I will give a throwback to some of the disease processes, the treatments, and the outcomes. A more helpful explanation of why some of what our babies are doing and the pathophysiology behind some of these most common problems. You can see in Figure 2, there are many of them.
Common Diseases & Pathology Related to Prematurity
Figure 2. Acute and chronic diseases related to prematurity.
The acute problems usually happen to the babies in the early stages of development. Figure 2, covers all of the different courses of the body and different areas of pathology related to prematurity. Then as it becomes chronic, we get into the cerebral palsy, blindness, feeding difficulties, and neurological disorders. I will introduce you to some of the main ones and then what we can do to offset those.
Differentiating the Diagnosis
- Respiratory issues are the #1 cause for NICU admission
- Differentiating between the various disease process are important to ensure proper treatment & care (by all disciplines).
- Often determined by:
- Timing: some present immediately, within few hours, or later
- X-ray findings: some appear white or hazy, streaked or “ground glass, hypoinflation (RDS) or hyperinflation (TTN) or both
- Maternal history,infant’shistory
- Lookattheinfantasawhole
A crucial part is to diagnose and differentiate the diagnosis. To treat the disease properly, we need to know what we are treating. We know that respiratory issues are the number one cause of NICU admission worldwide. In utero, they are not using the respiratory system, as the blood is profusing out of the placenta. There is no gas exchange going on there. Suddenly, they have this physiological phenomenon going on when they take their first breath. Sometimes it does not work quite right. differentiating between those various disease processes interfering with the proper respiratory structure or physiology is very important to ensure that we get proper treatment, and this is by all the disciplines. Often it is determined by several different factors here. Timing is essential, as well as when the symptoms present. These things give you clues about what kind of disease process we are looking at.
Maternal history is important in an infant's history. Another thing is to look at the infant as a whole. Considering all of the mother's history, what is going on now? What was the birth like? Maternal history can give you a better clue about your diagnosis. Did the mother have diabetes? That will set you up for probably a week or two, lag in lung maturity, and glucose issues. You are going to have issues with feeding. Then another thing is other disease processes can mimic respiratory symptoms, which might not be your main issue. You have to figure out is there something underlying that we need to treat? The two most common things are infection and congenital heart disease. If you want to rule out infection, make sure that you draw complete blood counts, cultures, and CRP, which is a C-reactive protein test that indicates inflammation. Start antibiotics promptly if you suspect that there is an infection. Of course, cyanotic congenital heart diseases may have respiratory manifestations. An echocardiogram, an ultrasound of the heart, will give you a better clue about the heart's structure and function if that is causing the respiratory issue. If it is the heart, giving surfactant or putting the infant on the ventilator might not help the problem, because you need to treat that congenital heart defect.
Respiratory Distress Syndrome (RDS)
- Severity of chronic symptoms are often related to
- Gestational age at birth
- Severity of the RDS
- Treatment modalities (type of ventilator, medications, etc.)
- Level of Perinatal care (in-house birth vs flown to NICU)
- Bronchopulmonary Dysplasia (BPD)
- A serious chronic lung condition often related to damage to the lungs during the acute phases of RDS
Respiratory distress syndrome (RDS) is common at birth for premature infants. The first breath is an issue and does not get better. Does it recur within a few hours? That might mean you could have pneumonia, transient tachypnea, or other things. When your symptoms present, for example, aspiration, maybe the baby ate, choked, and then about an hour or later, we start to have respiratory issues. Chest X-rays are fun to look at and you learn a lot viewing them.
Figure 3. Respiratory distress syndrome (CC by SA 3.0 Wikimedia).
In Figure 3, RDS looks like "ground glass" with hypoinflated lungs, which means the air sacs are very close. There is not a significant expansion going on there. It looks like you have little shatters of glass all over.
Figure 4. Pneumonia (CC by SA 3.0 Wikimedia).
Figure 4, is a chest X-ray depicting pneumonia. The lungs are either hyperinflated or hypoinflated with air-trapping in one area, and then the air cannot get into another area, making for a very splotchy X-ray.
RDS is caused by the lack of sufficient amounts of surfactant in the lungs. The amount of surfactant in the lungs is often related to prematurity, maternal diabetes, and genetic errors in metabolism. This means many of your trisomies in genetic disorders will sometimes have respiratory manifestations or cardiac issues. Surfactant is a slippery phospholipid protein in the lungs that reduces surface tension. It is like dishwashing liquid because it allows things to slide around. When born prematurely, tiny air sacs all of a sudden are filled with air. When the infant exhales, the alveoli are going to stick together. They do not open and shut as they should. This will cause atelectasis, the sticky little lungs are sticking together. It comes across as looking white on the X-ray. Usually, surfactant begins developing at about 23 weeks and should be sufficient by 37 weeks gestation. We call the 23 weeks the "edge of viability." Anything over 37 weeks is considered a term because they should have sufficient surfactant to survive outside of the utero.Clinical presentation
Clinical presentation begins immediately at birth. The baby takes that first breath and starts having trouble. They will have tachypnea, retractions, nasal flaring, and grunting. They look like they are working to take every breath. "Grunting" is when the baby makes its own PEEP (positive end-expiratory pressure), by trying to pop those little lungs open that is slammed shut, and sticky. Oxygenation and ventilation are not taking place, and the blood in circulation is not well perfused. The baby's skin is going to be mottled. They will have cyanosis, both central and acrocyanosis with increased pallor. They will be very pale. When we look at blood gases, they will have increased carbon dioxide (CO2) levels and respiratory acidosis. If respiratory acidosis is not corrected, it can be mixed with the metabolic component coming into play. I will say that when you are dealing with a child with an acute respiratory issue, such as RDS, you want to have access to arterial blood gasses, either through an arterial, umbilical, or a peripheral arterial line because you are going to need to check those oxygen levels. You want to make sure oxygen levels are going to stay within a normal range. You can monitor oxygen saturations with the pulse oximeter, however, to get the most accurate reading for these delicate babies, you want those arterial gases. Later on, when it comes to chronic issues, CO2 becomes the problem. By then you can do heel sticks for capillary gasses.
Treatment
Treatment for RDS is providing exogenous surfactant replacement. Surfactant is a thick protein and is the number one reason our premature rates are not what they were 50 years ago. The invention of surfactant in the late seventies made a difference in the viability of a baby born before 37 weeks. We will assist them with respiratory support and positive pressure ventilation through CPAP (continuous positive airway pressure). We will place them on the ventilator with an endotracheal tube, depending on what the child needs because we have gotten good at putting their surfactant in with the ET tube, then placing the baby on CPAP because surfactant is usually fast-acting. You can give the baby surfactant almost immediately, see a rise in the pulse oximeter, and improve your gases. Depending on what brand you use and what type you use, you will give one to two doses. We will also use antenatal corticosteroids, caffeine, supportive NICU care antibiotics, intravenous nutritional support, thermoregulation, and fluid electrolytes management, all are integral parts of treating respiratory distress syndrome in the NICU.
Outcomes
The severity of the chronic symptoms is related to the gestational age at birth. The number one determinant of respiratory severity is that the earlier the baby is born, the more severe the chronic condition becomes. The severity of the symptoms, treatment modalities, ventilators, and medications will also increase. Several decades ago, the old pressure ventilators breathed in-out and had set pressures. Usually, it gave you a PEEP, peak inspiratory pressure (PIP) with a rate. Those poor lungs were getting high pressures, causing barotrauma.
High pressures cause damage to the lungs with scar tissue developing, fibrosis will build up and become chronic. Now we have the newer volume-based ventilators. They are less traumatic. We use nitric, quick use Surfactin, a considerable determinant in how severe your chronic issues become. With a higher level of perinatal care, there is a significant increase in their survival rate, and chronic symptoms are not as severe in a baby born in-house. We have referred to the "house" as a baby born in the same hospital with a NICU, and a care team that can take care of the infant versus putting the baby on a helicopter and flying them to the hospital. Those born in-house have much better outcomes than those that are flown in.Bronchopulmonary Dysplasia (BPD)
Clinical presentation
Bronchopulmonary dysplasia (BPG) is a severe chronic lung condition related to the damage to the lungs during the acute phase of RDS. The alveoli of the lungs do not oxygenate and ventilate as they should. It leads to increased carbon dioxide levels in the cells. Cells have a tiny window of normal carbon dioxide levels, usually 35 to 45, about 50 in a little premature baby, that is about it. Anything outside those ranges the cells do not act correctly and can cause issues. Sometimes it is tough to maintain carbon dioxide levels within those tight confines. As a result, pulmonary hypertension affects the flow of the blood into the lungs, then cor pulmonale, which is when you have right-sided heart failure related to blood pumping against the high pressure of those lungs. BPD is just not about the lungs either. It is like a syndrome. It covers a lot of different things. The impaired cellular function can lead to nutritional issues and make it very hard to keep the baby nutritionally balanced. They have many fluid imbalances. Fluid imbalances delay growth. They already have issues trying to feed, then you have the cellular function, which means the digestive cells are not working.
Treatment
The medical team will end up using many diuretics trying to keep these babies from gaining too much weight and edema. They tend to "third space" a lot with their fluids. You have to watch that. They are on steroids, which can delay their growth and increase their risk of infections.
Outcomes
In utero, babies tend to grow longer, their long bones get lean and long, and they may weigh eight pounds when they come out. Whereas a baby's bones born prematurely will not grow out as well outside of the uterus. It is challenging for us with total parenteral nutrition (TPN) or hyperalimentation to get their bones to grow as they should. Osteopenia is a considerable problem with babies, known as "rickets," where their bones are very brittle and do not grow. You end up with these little short, fat babies. When you see how they look, you notice that they have skinny heads, long foreheads, fat cheeks, and multiple chins because we are putting the weight on them, but we cannot make them grow longer.
Transient Tachypnea of the Newborn (TTN)
Clinical Presentation
Transient tachypnea of a newborn (TTN) is a benign, self-limiting lung condition that usually presents within a couple of hours of birth. The baby may come out breathing okay. As the day progresses, you start hearing some grunting and the baby does not want to eat. Usually, you will see TTN with your late preterm infants, those 33 to 37 weeks. Generally caused by a delayed clearance of fetal lung fluid and can be secondary to a C-section without labor or maternal diabetes. As the baby gets older and prepares for delivery, it goes through a diuresis phase, getting rid of much of that fluid. If the baby does not go through that phase, that fluid is still sitting in the lungs. You may want to consider some lab work to make sure that you do not have sepsis, and an echocardiogram to make sure there is no congenital heart defect, but these babies do pretty well most of the time. They will have tachypnea, mild nasal flaring, grunting, and retracting. The x-ray itself looks significantly streaked. It will be hyperinflated, which means the ribs are further apart than they should be. The chest may be slightly barrel-chested. The breath sounds are as expected. However, depending on their severity, you might hear some crackles and diminished or muffled breath sounds.
Treatment and Outcomes
Treatment is mainly supportive here, using a nasal cannula or CPAP. Rarely do they need to be intubated. Usually, we can keep their pulse oximeter in the nineties with less than 30% oxygen. Then, of course, routine NICU care, monitoring thermal environment, and IV access following with ABGs.
Apnea of Prematurity
Apnea of prematurity is frequently seen in infants born before 28 weeks, but it can also occur in term infants. It always worries me when you see apnea occur in term infants because that usually indicates a brain injury when they do not have that drive to breathe as they should. Formally, apnea is defined as sudden cessation of breathing that lasts greater than or equal to 20 seconds and is accompanied by: bradycardia, low heart rate, oxygen desaturations, or cyanosis in a child younger than 37 weeks gestation. There are three types, central, obstructive, and mixed apnea.
Types of Apnea
Central apnea is when the brain's respiratory centers forget to trigger you to breathe. There is no respiratory effort made. Again, when this happens in a term baby, something is going on there.
Obstructive apnea is when something is obstructing your breathing. Tracheobronchomalacia is an example of what could cause obstructive apnea. Other causes include the premature baby's poor muscle tone, pneumonia, or Croup resulting in secretions blocking airway movement. Maybe the baby was intubated in the past and the vocal cords were damaged. Congenital anomalies, for example, Pierre Robin syndrome, where the chin is small and the tongue is oversized in comparison, can all cause obstruction. Alternatively, babies are obligate nose breathers. When they have blockages in the back of their nose, they will not open their mouth to breathe unless you make them open their mouth.
You will see mixed apnea in many babies because they will lose the effort to breathe. The brain will tell them, to not breathe, and they will stop breathing for a second. However, because of their low muscle tone, vocal cord damage, or poor reflexes, those pliable tiny thoracic cages cannot recover from it. They cannot catch their breaths like adults. Adults who are not breathing for a second or two can catch their breath. The babies are not able to do that. They cannot do that "big gasp." Their vitals will drop, and you will have to stimulate them and get them back to breathing. When we have premature babies with apneic spells, we always chart the frequency. How long did the duration last, and did the baby's heart rate drop? Did the baby desat? Did the baby require stimulation to take a breath, or was it able to self recover? Those are all necessary details that the doctor will want to know because if that baby has constant apnea where you have to stimulate them all the time, the infant probably needs more respiratory support, such as CPAP or even intubation at that point.
Treatment and Outcomes
Methylxanthines are central nervous system stimulants to keep respiratory centers roused to breathe. You do not drink coffee before you go to bed, expecting to get a good night's sleep. When I first started back in the nineties, we used Theophylline. The babies stayed tachypneic. You had to give it three times a day. If the heart rate was over 160, it was contraindicated, however, if you did not give it, they would not breathe. Then we switched to caffeine. Caffeine is a fantastic drug. It is dosed once a day. We chuckle as we give them their little "afternoon cup of tea or coffee." It keeps them roused enough that it does not have side effects. It is naturally derived from the cocoa beans, much less strenuous than the old-time Theophylline was. We also use CPAP to help with that obstructive apnea. Remember, if they are sticky when breathing out, those lungs will collapse, then it is tough to get them going. Usually, we put them on a CPAP of five, and it leaves a little bit of cushion in the lungs. It makes that next breath easier to take. CPAP does not make you breathe but makes it easier to breathe. Easier to take that next breath of air.
Pneumothorax
Clinical Presentation
Next, we talk about pneumothorax or a pulmonary air leak. For some babies, a pneumothorax happens quickly and will go into respiratory failure pretty fast. Figure 5 is a chest X-ray illustrating bilateral pneumothorax, also known as pulmonary air leak syndrome or collapsed lung.
Figure 5. Chest X-ray showing a pneumothorax (CC0 Wikimedia).
A pneumothorax is often a side effect of mechanical ventilation (think of the older pressure ventilators). A pneumothorax occurs when air is trapped around or outside the lung in your pulmonary cavity. The dark, "hyperlucent" areas are the pneumothorax in Figure 5. The anterior-posterior and lateral positions with the affected side up will be more visible as air rises up. Clinical signs involve respiratory distress/failure, chest wall asymmetry, and diminished breath sounds on the affected side. The pressures in the cavity are greater than the pressure in the lungs causing partial or full lung collapse. The pliable section is now stiff, and the heart cannot pump as it should. You will have what we call circulatory or peripheral issues. The infant will be very pale and not have good blood pressure because cardiac output is impaired.
Treatment and Outcomes
The key to treatment here is to equalize those pressures—usually needle aspiration or chest tube insertion. Depending on the infant's size, we can sometimes use a 100% nasal cannula or Oxyhood. You may have to insert a chest tube between that fourth and fifth rib, draw some of that air out or connect it to a negative pressure device to allow for healing.
Persistent Pulmonary Hypertension (PPHN)
Clinical Presentation
Let's talk about persistent pulmonary hypertension (PPHN), and increased pressures in the lungs. When the infant takes their first breath, the lungs should drop systemic blood pressure, and heart pressure increases. Increased lung stiffness is caused by decreased oxygen, trauma, mechanical ventilation, pneumonia, RDS, BPD, and meconium aspiration. All those issues interfere with oxygen in the lungs, think of oxygen as a vasodilator. The best way to explain it is when the right side of your heart is trying to pump blood into the vein, it gets tighter and smaller. The pressures in those lungs are high, and the blood will not flow there. It is going to flow back the other way. We call that right to left shunt. The blood builds up in the right side of the heart, and the heart must pump harder against those lungs, causing cor pulmonale. The number one reason you have a child on home oxygen, especially if they are on very low, like 100%, half a liter, is usually due to right-sided heart failure or cor pulmonale. The right to left shunt will allow the blood to pool in that right ventricle. In utero, we have a patent ductus arteriosus. During fetal circulation, only about 10% of the blood goes through the lungs at any given moment because the gas exchange has taken place in the placenta. When you take that breath of oxygen, you begin the respiratory system very soon after birth, and the ductus should close.
If there is increased heart pressure, sometimes the ductus will pop open. It allows deoxygenated blood to exit through the aorta into circulation without going through the lungs. Now you have lower circulation, and it becomes a vicious circle because the more it happens, the lower the partial pressure of oxygen (PaO2) in the blood will be. We put the pulse oximeter on the right hand, measuring "pre-ductal" because the branch off the aorta that feeds the brain also feeds the right hand. It is the blood that has come from the lungs. It gives you a good idea of what is going on in the brain. If you do a "post-ductal" pulse oximeter read where the pulse oximeter is usually on the feet and has lower reading, it tells you there is blood going in the wrong direction. It is a vital tool to treat persistent pulmonary hypertension, identifying a shunt.
Treatment and Outcomes
We need vasodilators, something to dilate those lung tissues. Usually, we can dilate with nitric oxide and 100% oxygen. We will often allow the PaO2 on the blood gas to climb into the 300s before we start weaning to help dilate and relax those blood vessels. We also use various sedatives, analgesics, and paralytics to relax the babies because they will fight the vent, especially if it is a bigger baby. We want them as calm as possible. We provide minimal stimulation and a dark, quiet environment. Anything to help them relax to allow the lungs to reoxygenate and help the pressures come down because the adverse outcomes can lead to chronic asthma, BPD, persistent pulmonary hypertension, and cor pulmonale where the baby ends up on oxygen. At this point, let me say something about keeping that baby warm. I cannot stress the importance of keeping that baby warm because one of the side effects of hypothermia is persistent pulmonary hypertension. It will make your lung pressures high, developing into PPHN. Everyone can do all the resuscitation in the world and give all the meds, but if your baby is cold, it will create a metabolic acidosis that you cannot overcome.
I cannot stress to you the importance of keeping that baby warm. Get the warmer out, get it on the mother's chest, something to keep the baby warm. Many of your local hospitals, even level one and level two nurseries, are more comfortable caring for these babies. That way, they are at the hospital with their mother. If it is a very mild case, they can keep the baby on a low-flow cannula or a pulse ox and let the baby breastfeed. The baby will not get much food that way, but it keeps from breaking up the maternal diad and the baby rushing off to the hospital 100 miles away.
Maternal Drug Use in Pregnancy: Outcomes
Clinical Presentation
I started in the NICU in 1998. We had maybe one or two drug-addicted babies per year. Now, there are anywhere from 10 to 15 at a time probably. They cry and produce diarrhea until their skin is scorched, the nasal passage is snotty, and they do not eat well. There are tons of things that go on with them.
Treatment and Outcomes
Detoxing or "NASSing" (Neonatal Abstinence Scoring System) a baby is not a fun thing to watch. It usually occurs three to four days after birth. These are the babies who may go home before they start detoxing. That may be something that you might see. They are at risk for neural tube defects, congenital heart defects, gastroschisis, miscarriage, preterm delivery, and stunted growth development. Cocaine use is linked to placental abruption, which can cause neonatal hypovolemia or hypoxic-ischemic encephalopathy, leading to serious brain injuries. Smoking in the home dramatically increases the risk for sudden infant death syndrome (SIDS). Mostly you are going to see developmental, neurological, and cognitive issues. Their lung issues might be secondary to congestive heart defects or preterm delivery. Alternatively, you can also have apnea related to hypoxic-ischemic encephalopathy, which does cause brain damage and is a leading cause of cerebral palsy—some pathology that many babies may endure. I pulled out some of the most concerning acute issues that you will see that will turn into issues and why you may be doing follow-ups with the baby.
Clinical Concerns
Positive Pressure Ventilation
- PPV is often not done correctly
- Technique
- Breath 2-3, breath 2-3
- Rate of 40-60 breaths/minute
- PIP of 20
- PEEP of 5
- Timely manner
- Dry, stimulate, remove wet linens, suction, position and assess heartrate with stethoscope
- If heart rate <100 begin immediately
- When PPV begins STOP stimulation
- Place pulse ox to monitor heart rate
Positive pressure is often not done correctly. People struggle with the Ambu bag. They tend to push too fast and want to jump right into chest compressions. I tell everybody to stop themselves when they get ready to start doing this. Take a breath, drop your shoulders think of your rhythm. Breathe two, three, breathe, two, three, breathe, two, three. We do not breathe in so quickly when we breathe, and time in is much shorter than our time out. You want to breathe at about 40 to 60 breaths per minute. You do want to watch your manometer. You squeeze your bag when you let go of the bag, and you do not want it to go to zero, but keep a PEEP of five, a PIP of 20, and follow the steps in NRP promptly. You want to dry, stimulate, remove your wet linen, suction, and assess that heart rate immediately. Start your positive pressure ventilation (PPV) when the heart rate is less than 100 or the baby is gasping or apneic. That is one of the issues that we have. PPV is either not done correctly or not done on time. We are thinking about brain cells here. Place the pulse ox on the right hand to monitor the heart rate. You are not monitoring the pulse ox as much as you are the heart rate on that right hand.
- At 15 seconds reassess heartrate, breathing
- If <100, apneic or gasping > start MR SOPA
- M–Mask
- Right size?
- Good seal?
- R–Reposition
- Neck role for sniffing position?
- Head in midline
- S–Suction
- Bulb or delee
- Mouth then nose
- O–Openmouth
- P–Pressure
- Increase PIP to 23-25 for a few breaths
- A–AlternativeAirway
- Laryngeal mask or ETT
After about 15 seconds of initiating PPV, you notice the baby is not coming up. Your heart rate is still down, and the infant is still gasping. Let's start MR SOPA, a set of corrective measures to ensure we are doing adequate positive pressure ventilation. You cannot resuscitate a baby with that chin on their chest. You have to get the baby in a sniffing position, use a rolled towel under the shoulders, position the head in midline, and suction their mouth and nose. I always open their mouths as babies will not breathe through their noses. If there is a blockage, you need to get that mouth open so they can breathe. Your PIP should be about 20, but sometimes it takes a little extra, 23-25, to get those airways open. Now you do not want too much pressure because you know what will happen, and it usually results in a helicopter ride and much paperwork. We do not want to go there. At this point, is your alternative airway, when you will put in either a laryngeal mask or your endotracheal tube. Please establish an airway before starting chest compressions, as most respiratory concerns are fixed with effective PPV and airway. Ninety-nine times out of a hundred, you never have to go to chest compressions with babies if you get an airway.
Overview of NRP 8th Edition Practice Changes
The neonatal resuscitation program (NRP) will always include "ABC," airway, breathing, and circulation. If you have ever taken a BLS test, they ask you, "What is the first thing you will do?" You will look for an airway for a baby because you are trying to get air into something that has never had air before. Give yourself 30 seconds to assess a heart rate rise once you get an airway. If the heart rate is less than 60 with an airway, turn the Fi02 to 100% and begin chest compressions.
View Full Size Image Figure 6. NRP 8th Edition Practice Changes (Adapted from the American Academy of Pediatrics, 2021).
Figure 7. NRP 8th Edition Practice Changes (Adapted from the American Academy of Pediatrics, 2021).
There are a couple of changes from the seventh to the eighth edition of the NRP (Figures 6 and 7), including one of the questions about gestational age and clear amniotic fluid, how many babies, and additional risk factors? Now, NRP wants you to know umbilical cord management and how many babies will fall under the risk factors because it is a risk factor, to have a twin or triplet delivery (Figure 6). With the umbilical cord management plan, will you delay the cord clamp? It is essential in a preemie because you can increase their blood volume by up to 30% and decrease the need for extra blood. Giving the baby blood allows about 60 seconds of active blood to flow into the baby from the placenta before you clamp the cord. It is not gravity-driven. The placenta still has the heartbeat, and it is still connected. You do not need to hold the baby down. It is going to go in actively. They streamline the initial steps, warm, dry, stimulate, position the airway, and suction. Then they want you to put the cardiac monitor on sooner. In the seventh edition, they wanted it on before you started chest compressions, and in the eighth edition, they want it on if you need an artificial airway. If you have to intubate, put the baby on a cardiac monitor.
We would flush IV epinephrine with 0.5 to 1 mL of normal saline with the seventh edition. Now they want all weights and gestational ages of babies to be flushed with 3 mL of normal saline (Figure 7). Almost like you are giving a little saline bonus to the baby. When you gave epinephrine in the seventh edition, they gave you a range of doses, but now a suggested dose needed is given in the eighth edition. They want you to give the initial IV dose at 0.2 mL per kilogram. The endotracheal tube dose is suggested to be given while establishing vascular access. When giving IV/IO epinephrine through the endotracheal tube at 1 mL/kg, they have extended the amount of time they want you to attempt resuscitation from 10 minutes to 20 minutes. One thing we strive for in the NICU is to protect the baby's brain. It is delicate. Many little blood vessels can break. They are very susceptible to fluctuations in oxygen in their brain.
Neuroprotection of the Premature Infant
Neuroprotection is what we do, strategies capable of preventing neuronal death. We are trying to take care of those little brain cells. Babies born at less than 37 weeks are at significant risk of having intracranial ischemic or hemorrhagic injuries. They are at the greatest risk in the first 72 hours of life. Neuroprotection is strategies that promote optimal synaptic neural connections and supports normal neurological, physical, and emotional development along with preventing disabilities. You must understand that these babies are supposed to be still floating around in the quiet little dark, protected area. Suddenly, they are out here, and we are poking, prodding; the lights are on. It is cold or hot. The babies do not handle these wild stimulations well, resulting in many issues. We try to provide prenatal prevention. If there is any chance that this baby may deliver within the next six hours, we administer maternal corticosteroids and prompt antibiotic treatment for chorioamnionitis. If you suspect the mother has an infection, get those antibiotics on board, and transport them to a tertiary care facility. Perinatal prevention provides a higher level of care, with delivery in a hospital with a high-level care team. When you are in that higher-level care team's hands, outcomes are much better. Note that delayed cord clamping may be needed and pay particular attention to avoid hypothermia. Do not let the baby get cold.
The baby is here. What do we do for postnatal prevention? Promptly, start antibiotics if indicated and make cautious use of inotropes. Examples of inotropes are dopamine dopexamine, milrinone, and epinephrine. Inotropes increase the heart rate, improving cardiac output and blood pressure. What happens is that inotropes are usually hard to control. You will give them dopamine, and their heart rate will go sky-high. You can imagine those little blood vessels popping in their brains. Be careful using those. Sometimes you do not want the carbon dioxide fluctuations (CO2). You will have a CO2 of 60, and if you crank your ventilator down, you will have a CO2 of 30. Research is finding that a little higher CO2 is not as dangerous as fluctuating CO2 on a baby. Avoid rapid, significant fluid shifts, initiate neutral head positioning and provide care bundling. Bundling of care includes: feeding the baby, changing the diaper, turning the baby over, changing the bedding, sticking his heel, and drawing labs. You do whatever you have to do at once and walk away to provide minimal stimulation. We usually do that again for the first 72 hours of a preemie baby, where the room is dark. The bed is covered. We do not do anything more than what we have to do to that baby to decrease stimulation, letting those little nerve endings heal and develop properly.
Multi-Disciplinary Team Approach to Care
- They are at risk for
- Developmental & cognitive delays
- Behavioral difficulties
- Motor skills impairment
- Complex & chronic medical disorders
- Feeding and/or malabsorption issues
- Vision & hearing deficits
- Speech & language problems
It Definitely Takes a Village to Raise a Preemie
It takes a village to raise a preemie. Premature infants are at high risk for developmental & cognitive delays, behavioral difficulties, motor skill impairment, and complex chronic medical disorders. Babies develop what is called necrotizing enterocolitis (NEC). They can have bowel resections, feeding, and malabsorption issues, and we call that short gut syndrome. Many times there are vision and hearing problems. Retinopathy of prematurity is one of the leading causes of blindness worldwide. Many antibiotics will make them deaf.
Speech-language therapy can be excellent for these babies. We do so much to their mouth, including intubating and suctioning them, causing oral aversion to anything coming towards their mouth. The endotracheal tube causes the infants to develop high arched palates, leading to many speech-language development problems. They can become orally aversive to certain food textures they do not want to eat. They have trouble forming words. Lots of speech-language issues with these little guys need to be addressed by the specialists for the best quality of life. Most states have early intervention programs for NICU graduates. They have care management programs that help coordinate services. Know that each of these conditions needs to be treated. They need respiratory therapists, occupational therapists, speech-language pathologists, physical therapists, psychiatrists, and all kinds of things to help them become the best they can be as they grow. Also, services help the parents because it is often not what they signed up for.
Overstimulation Cues
Sometimes you will go into a house with a fussy, overstimulated baby. It is very easy to overstimulate a baby, especially if there are other children in the house or the household is noisy. Here are some cues to overstimulation.
Feels stiff (tense) or limp
- Will outstretch arms and spread finger apart (Splaying)
- Squirms, startles easily, or twitches excessively
- Avoids eye contact and/or turns head away
- Arches back while making a fist
- Skin will pale
- Frowns, fussy, cries
- Spits up or chokes easily
During your assessment and interventions, the baby may feel stiff or very limp. They will often outstretch their arms and spread their fingers, called "splaying." They will squirm, startle easily, or twitch excessively. They will avoid eye contact with you and turn their head away when you are trying to look at them. Arching is an important cue. They will make fists while they arch, especially when trying to change a diaper on a baby. They may bend backward, almost like the baby is trying to get away from you. Their skin will become very pale. They will frown, they will fuss, and they will cry. It may not even be a high-pitched, mad cry but a little whimper. They will let you know they are not happy. Then they will spit up and choke very quickly when they eat if they are nervous or upset.
Calming Techniques
Swaddling is a considerable technique, and swaddle blankets are fabulous. Now, this is up to three to four months old. After that, they do not want to be swaddled as much once they start moving around. Speaking softly to them, adding a pacifier, and dimming the lights are great calming techniques. Take them to a quiet place, a room alone, and place your hands slightly on their tummy. Allow them to hold your fingers, hold their hands, roll a blanket up, and put it under their feet or around them where they can feel it. They like to feel that pressure against them and then use gentle, firm pressure. If you are holding the baby, provide firm, gentle pressure. Never stroke, bounce, or pat an upset preemie. You are not shaking them up like a Polaroid. You want to hold them still. Even when they are lying on the bed, put one hand on their head and one hand on their feet—a calming effect.
Preventative Medicine
If you are treating the baby at home, the parents should have a piece of paper on the refrigerator that says if the baby's doing this, please call the pediatrician or call 911. That is important. If you are working with the baby and notice those symptoms, do not hesitate to get help. The problem with babies is that they cannot raise their hands and say, "My tummy hurts." You have to assess these subtle signs and symptoms to determine whether the baby is getting sick and should they need to go to the doctor. There is usually a parent or a caregiver that is in tune with the baby and knows before anybody that their baby is sick. If you have a parent or another caregiver in the house telling you that this baby is not acting right today, take them seriously. They usually know because the baby will be eating less than usual, have any changes in appetite, or cry regularly.
Again, it is not necessarily a high-pitched cry. It may be a fussy grunt. The baby cannot be comforted, is less active, or has any behavior change. Diarrhea or constipation are the extremes, usually loose, watery stools and vomiting. That means more than spitting up after they eat, usually projectile vomiting that lasts more than a few hours. Babies, especially premature babies can dehydrate very quickly. The baby may have a high fever of 100.4 or higher, seeming more than the mildly ill, vomiting with the fever, a rash, a cold, and trouble breathing. Call 911 if they look blue around the lips or throat. Some signs are subtle, and some of them are not.
Vaccines are essential for the prevention of diseases. Childhood immunizations for all children in the household are important. Common spreadable diseases include respiratory syncytial virus (RSV). Make sure even the adults have their Tdap (tetanus, diphtheria, and pertussis) boosters, and flu shots for everybody. Sometimes parents will say no visitors, especially during the flu season. Smoking in the house is dangerous. The house must maintain a degree of cleanliness, an environment in which a respiratory-challenged baby can live. They cannot live in a dusty, smokey, dirty house. It does not work that way.
Safe Sleep
The last thing I do want to mention is safe sleep. Notice how the baby is sleeping, assist them, and know the importance of being alone in the bed, on their back in a crib, sleeping on the couch, on the recliner, or on daddy's chest is not going to cut it. I have been to several conferences with parents who have lost their babies from things like this. They recommend no bumpers, loose bedding covers, wearable blankets, and fitted pajamas to help. There is lots of information out there for the parents on safe sleep.
References
Altimier , L., Phillips, R. (2016). The neonatal integrative developmental care model: advanced clinical applications of the seven core measures for neuroprotective family - centered developmental care. Newborn Infant Nursing Reviews 16(4), pp. 230 - 244.
Graven, S, Browne J.V. (2008) Sensory development in the fetus, neonate, infant: introductions overview. Newborn Infant Nursing Review, volume 8, pp. 169-172.
Jha, K., Nassar, G. N., & Makker , K. (2021). Transient Tachypnea of the Newborn. In StatPearls. StatPearls Publishing: Available from: https://www.ncbi.nlm.nih.gov/books/NBK537354/
National Institutes of Health, National Library of Medicine (2022). Neonatal respiratory distress syndrome. Retrieved from: https://medlineplus.gov/ency/article/001563.htm
National Institutes of Health, National Library of Medicine (2022). Bronchopulmonary dysplasia. Retrieved from: https://www.nhlbi.nih.gov/healthtopics/bronchopulmonary-dysplasia.
National Birth Defect Registry (n.d.) Premature Births. Retrieved on 01/30/2022 from: https://birthdefects.org/prematurebirths/?gclid=Cj0KCQiAi9mPBhCJARIsAHchl1z3YW5TqskSd5T Aiy1XVTiqjHkfY9DgNtAziU3BVDuKNcwsoBH5mKYaAkxkEALw_wcB
Murthy, P.,et al. (2020). Neuroprotection Care Bundle Implementation to Decrease Acute Brain Injury in Preterm Infants. Pediatric neurology, 110, 42–48.
Pennington, T.C. (2022) personal photos from my Iphone.
Ryan, M., Lacaze - Masmonteil, T., & Mohammad, K. (2019). Neuroprotection from acute brain injury in preterm infants. Paediatrics & child health, 24(4), 276–290.
Yadav S, Lee B, Kamity R. Neonatal Respiratory Distress Syndrome. [Updated 2021 Jul 31]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan. Available from: https://www.ncbi.nlm.nih.gov/books/NBK560779/
Kondamudi NP, Krata L, Wilt AS. Infant Apnea. [Updated 2021 Nov 7]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2022 Jan. Available from: https://www.ncbi.nlm.nih.gov/books/NBK441969
Citation
Pennington, T. (2022). Respiratory concerns for the premature infant. Continued.com - Respiratory Therapy, Article 143. Available at www.continued.com/respiratory-therapy
Apr 5, 2022
1 CE Hour