Course Articles
Personality Pathways to Substance Abuse: Understanding Traits, Risks, and Treatment
Benjamin Ampel, MA, PhD candidate
This text-based course is an edited transcript of a live webinar, presented by Benjamin Ampel, MA, PhD candidate.
Introduction
The landscape of substance use disorders is complex, marked by a myriad of contributing factors that range from genetic predispositions to environmental influences. Among these, individual personality traits emerge as a critical dimension, offering profound insights into why certain individuals may be more susceptible to substance abuse, how their patterns of use might differ, and what therapeutic approaches could prove most effective. This article delves into the fascinating intersection of personality and substance use, providing a comprehensive overview of the theoretical frameworks and empirical evidence that illuminate these pathways. The primary focus will be on understanding how personality forms and influences behavior, identifying key personality traits linked to substance abuse, and predicting treatment outcomes of substance abuse based on personality.
The journey into understanding personality begins with a fundamental distinction between temperament and personality. Temperament, often considered the biological foundation, refers to the innate, genetically influenced behavioral and emotional patterns observable from early infancy. It is the raw material, the predispositions with which an individual is born. Personality, on the other hand, is the intricate tapestry woven when this biological temperament interacts with the environment—both the physical surroundings and the social milieu. It represents the consistent patterns of behavior that manifest across various situations and over time, shaping an individual's unique way of perceiving, thinking, and acting.
While the realm of personality is vast and multifaceted, this exploration will primarily center on the Big Five personality traits, a widely accepted and empirically supported model for describing human personality. Within this framework, particular emphasis will be placed on the dimensions of extraversion and introversion, given their significant and often counterintuitive implications for substance use. Furthermore, the discussion will extend to the Behavioral Inhibition System (BIS) and Behavioral Activation System (BAS), two neurobiological systems that offer a deeper understanding of approach and avoidance motivations, which are profoundly relevant to addictive behaviors. By integrating insights from these models, this article aims to provide a nuanced perspective on how personality shapes the trajectory of substance use disorders and how this understanding can inform more targeted and effective clinical interventions.
Disclosures
Presenter Disclosure: Financial disclosures: Benjamin Ampel received an honorarium for presenting this course. Benjamin Ampel has published peer-reviewed articles on emotional regulation and personality, along with understanding the relationship between goal pursuit, self-regulation, and emotional regulation. Non-financial disclosures: Benjamin Ampel has no relevant non-financial relationships to disclose. Content Disclosure: This learning event does not focus exclusively on any specific product or service. Sponsor Disclosure: There is no external sponsor for this course.
Limitations and Risks
Personality is complex and multifaceted this webinar is not inclusive of all personality traits and factors that impact substance use. Practitioners should actively engage in supervision and self-reflection in an effort to reduce biased clinical judgments or reduced empathy for clients due to linking certain personality traits to substance abuse. Practitioners should practice culturally humility and utilize, and/or incorporate culturally responsive frameworks into practice.
Substance Use Disorders and Personality Overview
To begin, it is essential to establish a clear understanding of what constitutes a substance use disorder (SUD). According to the DSM-5 criteria, a diagnosis of SUD is based on a maladaptive pattern of substance use leading to significant impairment or distress. This pattern is manifested by at least two of the following criteria occurring within a 12-month period. The severity of the disorder is determined by the number of criteria met.
The DSM-5 outlines four main domains of criteria for SUD:
- Impaired Control: This domain encompasses behaviors that indicate a loss of control over substance use. Examples include taking the substance in larger amounts or over longer periods than originally intended, a persistent desire or unsuccessful efforts to cut down or control substance use, spending a great deal of time obtaining, using, or recovering from the substance's effects, and experiencing a strong craving or desire to use the substance. These indicators reflect a diminished capacity to regulate one's own consumption, even in the face of intentions to reduce or cease use.
- Social Impairment: This domain highlights the negative impact of substance use on an individual's social and occupational functioning. Criteria include a recurrent failure to fulfill major role obligations at work, school, or home due to substance use. It also involves continued substance use despite persistent social or interpersonal problems that are caused or worsened by the effects of the substance. Furthermore, giving up or reducing important social, occupational, or recreational activities because of substance use falls under this category, indicating a narrowing of interests and a prioritization of substance use over other life domains.
- Risky Use: This domain pertains to the use of substances in situations that pose physical hazards or despite awareness of negative consequences. It includes recurrent substance use in physically hazardous situations, such as driving under the influence or operating machinery while intoxicated. It also involves continued substance use despite knowledge of having a persistent or recurrent physical or psychological problem that is likely to have been caused or worsened by the substance. This criterion underscores a disregard for one's own well-being in favor of continued substance use.
- Pharmacological Criteria: These criteria relate to the physiological adaptations that occur with repeated substance use. Tolerance is a key indicator, characterized by a need for markedly increased amounts of the substance to achieve intoxication or the desired effect, or a markedly diminished effect with continued use of the same amount of the substance. Withdrawal is the other criterion, involving the development of a substance-specific syndrome due to the cessation of or reduction in substance use, or taking the substance (or a closely related substance) to relieve or avoid withdrawal symptoms. These physiological markers often signify a more entrenched pattern of dependence.
Understanding these diagnostic criteria provides a foundational context for exploring how personality intersects with substance use. As previously mentioned, personality is not merely an inherent trait but a dynamic construct shaped by the interplay of an individual's biological temperament and their environmental experiences. Temperament, the bedrock of personality, refers to the constitutionally based individual differences in emotional, motor, and attentional reactivity and self-regulation. These innate predispositions, evident even in infancy, influence how an individual interacts with and responds to their environment. For instance, some infants may exhibit high reactivity to novel stimuli, while others may be more subdued. These early differences can lay the groundwork for later personality traits, such as introversion or extraversion.
When this biological temperament consistently interacts with the physical and social environments over time, it solidifies into what we recognize as personality. This means that while an individual may be born with a certain predisposition, their experiences—their upbringing, social interactions, cultural context, and significant life events—all contribute to the refinement and expression of their personality traits. For example, a child with a naturally reactive temperament might, in a supportive and nurturing environment, develop coping mechanisms that lead to a resilient personality. Conversely, in a chaotic or unsupportive environment, the same temperament might manifest as heightened anxiety or withdrawal. Therefore, when examining the "personality pathways to substance abuse," it is crucial to consider this interplay, recognizing that both innate predispositions and learned behaviors contribute to an individual's vulnerability and their journey with substance use.
The Essential Trait Approach: The Big 5
To comprehend the profound influence of personality on substance use, it is imperative to first understand the prevailing framework for conceptualizing personality: the essential trait approach, which led to the development of the Big Five personality traits. The essential trait approach represents a scientific quest for a concise yet comprehensively predictive list of traits that can account for the broadest range of human behaviors. The core requirements for such a list are succinctness and non-redundancy, meaning each trait must be independent and contribute unique predictive power without overlapping significantly with others. The goal is to identify a parsimonious set of fundamental dimensions that can describe the vast complexity of human individual differences.
Given the immense vocabulary humans possess to describe personality across virtually every language and culture, a natural starting point for this quest was language itself. This led to the "lexical approach" to essential traits. The lexical hypothesis posits that the most important individual differences in human transactions will eventually become encoded in the natural language. In other words, if a personality trait is truly significant, people will have developed words to describe it. Researchers employing this approach began by sifting through dictionaries and asking individuals to describe people they knew well, identifying adjectives commonly used to characterize personality.
A seminal study illustrating this approach involved 1,300 raters who were given a list of 60 commonly used adjectives for describing people. Each rater was asked to think of a person they knew well and underline the adjectives they might use in a conversational description of that person. By analyzing which words were frequently used and which clustered together, researchers observed recurring patterns. For instance, while "bashful" and "bold" are antonyms, they both clearly describe aspects of the same underlying personality dimension. This systematic analysis of everyday language revealed that despite the seemingly endless array of descriptive terms, a finite set of core dimensions consistently emerged. This empirical process ultimately led to the identification of the Big Five personality traits, often remembered by the acronym OCEAN: Openness to Experience, Conscientiousness, Extraversion, Agreeableness, and Neuroticism.
Let us briefly delineate each of these Big Five traits and their general implications, before delving into their specific connections to substance use:
- Openness to Experience: This trait, sometimes referred to as intellect or culture, describes an individual's receptiveness to new ideas, experiences, and unconventional thinking. People high in openness are often characterized as original, daring, independent, and artistic. They possess a broad range of interests, are imaginative, and enjoy intellectual pursuits. Conversely, individuals low in openness tend to be more conventional, practical, and prefer routine. Interestingly, openness to experience has been linked to substance use, particularly with hallucinogenic substances. Research has even suggested that the consumption of certain psychedelics, such as psilocybin, can temporarily or even enduringly increase an individual's score on openness to experience. One study, for example, found that participants who took psilocybin mushrooms scored higher in openness to experience six months later compared to a control group.
- Conscientiousness: This trait encompasses an individual's motivation to achieve goals and their discipline in pursuing them. It reflects a tendency to be organized, persistent, and planful. Individuals high in conscientiousness are typically careful, self-reliant, scrupulous, and goal-directed. They are often seen as responsible and hardworking. While conscientiousness might intuitively appear to be a protective factor against substance use due to its association with self-control and adherence to norms, its relationship is more nuanced. Paradoxically, highly conscientious individuals, when faced with significant professional setbacks, such as job loss, tend to experience more profound negative emotional responses, including increased depression, anxiety, and reduced life satisfaction. This heightened vulnerability to stress can, in some cases, lead to the development of maladaptive coping mechanisms, including substance use, as a means to manage intense emotional distress.
- Extraversion/Introversion: This dimension describes the degree to which an individual is outgoing and derives energy from social interaction. Extraverts are typically talkative, friendly, spontaneous, and bold, seeking frequent interactions with others and often desiring dominance or leadership roles in groups. Introverts, conversely, are described as quiet, aloof, inhibited, or timid, preferring solitude and finding social interaction energetically draining. This trait is particularly central to the discussion of substance abuse, as it profoundly influences drug preferences and responsiveness to various therapeutic modalities. The intricate biological underpinnings of this dimension, particularly in relation to cortical arousal, will be explored in greater detail.
- Agreeableness: This trait reflects an individual's tendency towards nurturance, emotional supportiveness, and a desire to maintain harmonious relationships. Agreeable individuals are often described as good-natured, helpful, trusting, and lenient. They tend to inhibit negative emotions for the sake of others and prioritize interpersonal harmony. Conversely, individuals low in agreeableness may be more competitive, skeptical, and less concerned with others' feelings. While not as directly linked to specific drug preferences as extraversion or neuroticism, agreeableness can influence an individual's social environment and their susceptibility to peer influence, which are significant factors in substance use initiation and maintenance.
- Neuroticism/Emotional Stability: This trait represents an individual's tendency to experience negative emotions. Individuals high in neuroticism are often described as worrying, emotional, insecure, and jealous. They are prone to experiencing anxiety, depression, anger, and other distressing emotions. Conversely, individuals low in neuroticism, or high in emotional stability, are characterized as calm, unemotional, secure, and not easily perturbed. Neuroticism is a well-established risk factor for various mental health conditions, including substance use disorders, as individuals may turn to substances as a means of self-medication to alleviate intense emotional distress. The strong link between negative affect and substance use makes neuroticism a critical personality pathway to explore.
Each of these Big Five traits, in its own intricate way, contributes to an individual's unique vulnerability and trajectory concerning substance use disorders. While some traits may appear to be protective, their interaction with life events and other personality dimensions can create complex risk profiles. This foundational understanding of the Big Five sets the stage for a more focused examination of extraversion and introversion, and the underlying biological mechanisms that drive their distinct relationships with substance use.
Extraversion and Introversion: The Big Five
Extraversion and introversion constitute a fundamental dimension within the Big Five personality framework, yet their complexities often extend beyond common understanding. This trait is not merely about being outgoing or reserved; it delves into the very source of an individual's energy and their optimal level of environmental stimulation. When discussing extraversion and introversion, it is crucial to recognize that these are relative terms, describing an individual's position on a continuum compared to others. The majority of people, approximately 66%, fall within one standard deviation of the mean, exhibiting a blend of both introverted and extraverted tendencies. This middle ground is often referred to as "ambiversion." Ambiverts are not simply neutral; they possess the capacity to draw energy from both social interaction and solitude, adapting their behavior based on the situation. They might enjoy a lively party but also value quiet time for reflection, demonstrating a flexible mix of tendencies. However, for the purpose of understanding the more pronounced effects on substance use, focusing on the extreme ends of this spectrum—the highly introverted and highly extraverted individuals—provides clearer insights.
The concepts of introversion and extraversion were originally coined by Carl Jung and later popularized by Hans Eysenck, who proposed a strong biological basis for these differences. Eysenck's theory posited that introverts and extraverts differ in their baseline levels of cortical arousal, which influences how they restore energy. Introverts, as the prefix "intro" suggests, seek to restore their energy by pulling inward, into themselves. Social interactions, especially prolonged or intense ones, are energetically draining for them, leading to fatigue. They recharge in solitude, in environments with lower external stimulation. Conversely, extraverts, deriving their name from the prefix "extra," restore their energy by reaching outside of themselves, through social interaction and engagement with the external world. They find solitude and a lack of external stimulus to be draining and even boring, which depletes their energy. This fundamental difference in energy restoration is a cornerstone for understanding their distinct behavioral patterns.
As a direct consequence of these differing energy restoration mechanisms, introverts and extraverts exhibit notable differences in sociality, as articulated by Carver and Scheier (2016). Extraverts are inherently more likely to seek out social interactions. They are often drawn to group settings and tend to seek dominance within these groups, frequently assuming leadership roles. Furthermore, and for reasons that are biologically complex, extraverts tend to experience positive emotions more frequently in general. This propensity for positive affect can further reinforce their pursuit of stimulating social environments. For an individual to gauge their own position on this spectrum, a simple self-reflection can be illustrative: consider how you feel after leaving a large social gathering. An extravert might feel energized and even seek further social engagement, while an introvert might feel depleted and crave quiet time alone to recharge. This visceral experience reflects the underlying biological differences in how their brains process and react to external stimuli.
The distinction between introversion and extraversion extends beyond social preferences, manifesting in various aspects of life, including drug preference, communication styles, choice of workplace, and approaches to relationships. These differences are rooted in varying optimal levels of stimulation. Eysenck's arousal theory, further supported by research from Bullock and Gilliland (1993), suggests that introverts have chronically higher levels of cortical arousal, meaning their brains are naturally more active even in low-stimulus environments. In contrast, extraverts have chronically lower levels of cortical arousal, leading them to seek out more external stimulation to reach their optimal arousal level.
Consider a spectrum of stimulation, ranging from low (e.g., lying still in a dark, quiet room) to high (e.g., being yelled at by an angry mob). For an introvert, their optimal level of stimuli might be a quiet conversation with a familiar acquaintance. This level of interaction provides sufficient stimulation without overwhelming their already highly aroused nervous system. For an extravert, however, this same quiet conversation might be understimulating, leading them to seek out environments with louder music, more people, or more intense interactions to reach their preferred level of cortical arousal. Both introverts and extraverts are ultimately seeking an optimal level of brain activity, but they require different amounts of external stimulation to achieve it. An introvert's brain lights up more in response to the same stimulus compared to an extravert's brain. This means that a loud party, which might be exhilarating for an extravert, could be profoundly overwhelming and draining for an introvert, as their neural activity spikes significantly in response to the high sensory input. This fundamental difference in how their brains process and react to stimuli explains their divergent preferences and behaviors across various life domains.
Affect and Arousal
Before delving deeper into the biological underpinnings of personality and its connection to substance use, it is important to clarify two key terms: affect and arousal.
Affect: In psychology, affect refers to an emotion or feeling. It is the experience of emotion, such as joy, sadness, anger, fear, or interest. Affect is a subjective experience, but it can be expressed through observable behaviors, facial expressions, and physiological changes. When discussing personality, affect often refers to an individual's general emotional disposition or their tendency to experience certain types of emotions more frequently.
Arousal: Arousal refers to the level of physiological activation in the body and brain. It is a state of being awake, alert, and responsive to stimuli. Physiologically, arousal is reflected in various bodily responses, including heart rate, blood pressure, breathing rate, and neural activity in the brain. High arousal signifies a state of alertness and readiness for action, while low arousal indicates a state of relaxation or sleepiness. In the context of introversion and extraversion, arousal specifically refers to cortical arousal, or the level of activity in the brain's cerebral cortex. Understanding these terms is crucial for grasping the biological mechanisms that differentiate personality types and influence their interactions with substances.
Introversion-Extraversion: Biological Basis
The profound differences observed between introverts and extraverts in their preferred levels of stimulation, energy restoration, and social engagement are not merely psychological constructs; they are rooted in distinct biological mechanisms. A compelling perspective on this biological basis comes from Desmond Morris's (1969) concept of the "stimulus struggle," drawing parallels from the animal kingdom. Morris categorized species into specialists and opportunists. Specialists thrive by having a highly efficient, specialized method for obtaining food, which reduces their need to explore diverse environments. Opportunists, conversely, have evolved to specialize in exploration, requiring high levels of environmental stimulation to thrive. Morris posited that humans, as opportunistic animals, also engage in a "stimulus struggle," seeking an optimal balance—not too much, but not too little—of stimulation. This inherent variability in the need for stimulation among humans, Morris suggested, manifests as introversion and extraversion.
This idea aligns with the observation that introverts and extraverts have chronically different levels of cortical arousal in response to stimuli. As previously noted, introverts exhibit higher baseline cortical arousal, meaning their brains are more active even in quiet environments. Consequently, they require less external stimulation to reach their optimal arousal level and can easily become overstimulated. Conversely, extraverts have lower baseline cortical arousal, necessitating more external stimulation to achieve their desired level of brain activity. This difference in preferred stimulus level explains their divergent choices in environments and activities, as both types are ultimately striving for a similar, comfortable level of cortical arousal. For instance, an introvert's brain might experience significant neural activity from a quiet conversation, while an extravert might need the intensity of a loud party to achieve the same level of internal "buzz."
Empirical evidence supports these physiological distinctions. Gray (1970) demonstrated that introverts show an increased brain-stem auditory evoked response (B.A.E.R.) to startling noises. In studies where participants were exposed to static noises of varying decibel levels, introverts consistently exhibited a stronger neural response—more neurons firing—to the same sound intensity compared to extraverts. This means that a car door slamming, or loud music at a party, literally causes more brain activity and a greater sense of overwhelm for an introvert. This heightened reactivity explains why introverts find high-stimulus environments more challenging and why they prefer quieter settings where their brains are not constantly bombarded by excessive sensory input.
The key neurological structure implicated in regulating cortical arousal is the Ascending Reticular Activation System (ARAS). The ARAS is a network of neurons located in the brainstem that connects the cerebral cortex to the rest of the brain. Often referred to as the "ignition system" of the brain, the ARAS is responsible for regulating overall arousal, wakefulness, and the filtering of sensory information. Damage to the ARAS can result in severe states of reduced consciousness, such as a coma, underscoring its critical role in maintaining alertness and responsiveness. The ARAS also plays a vital role in filtering out extraneous sensory information, allowing individuals to focus on relevant stimuli. For example, the constant tactile sensation of clothing on one's skin is typically filtered out by the ARAS, preventing sensory overload. Furthermore, the ARAS regulates sleep and wakefulness, with lower neuronal firing rates during sleep and higher activity levels during waking states. Its regulatory functions are mediated through various neurotransmitter systems, including GABAergic, adrenergic, and dopaminergic pathways, which influence neural activity and arousal levels.
In the context of introversion and extraversion, the ARAS functions differently. For introverts, their ARAS requires less stimulation to become overstimulated, leading to a rapid and significant increase in cortical arousal. This inherent sensitivity means that even moderate levels of external stimuli can quickly push an introvert's brain beyond its optimal arousal threshold, leading to feelings of being overwhelmed or drained. Conversely, extraverts require larger amounts of stimulation to activate their ARAS sufficiently, prompting them to actively seek out more stimulating environments and activities to achieve their desired level of cortical arousal. Recent research further supports this, showing that extraverts exhibit less brain activity in certain areas during memorization tasks and have lower resting brain activity when deprived of stimulation. This under-stimulation is a profoundly uncomfortable feeling for extraverts, driving their continuous pursuit of higher levels of external engagement.
This biological distinction profoundly influences various aspects of an individual's life. For instance, communication styles differ markedly. Extraverts tend to be more blunt, forceful, and prone to pushing social boundaries, such as using nicknames quickly or initiating physical touch, as these behaviors generate stimulating social feedback. Introverts, being chronically overstimulated, are more cautious and less inclined to engage in such boundary-pushing behaviors, as their brains are already working overtime. Workplace preferences also diverge; open-plan offices, designed for constant interaction and stimulation, are often ideal for extraverts but can be detrimental to introverts' cognitive functioning and memory due to sensory overload. Relationship approaches also reflect these differences, with extraverts often seeking broader social networks and introverts preferring deeper, more intimate connections.
Crucially, these biological differences in cortical arousal and ARAS functioning also impact drug preferences. Extraverts, with their chronically under-stimulated brains, tend to gravitate towards stimulants such as caffeine, cocaine, methamphetamine, and MDMA. These substances artificially increase neural firing and cortical arousal, helping extraverts achieve their desired level of internal stimulation. For them, a stimulant can make a quiet conversation feel more engaging or provide the "speed" they naturally crave. Conversely, introverts, who are often chronically overstimulated, tend to prefer depressants and anxiolytics. Substances like alcohol, benzodiazepines (e.g., Valium, clonazepam), and other GABAergic agonists literally slow down neural firing, reducing cortical arousal and helping introverts feel less overwhelmed, particularly in social environments. This allows them to function more comfortably in highly stimulating settings that might otherwise be unbearable. However, this preference also carries the risk of developing dependence on these substances to navigate everyday social interactions or to find solace in solitude, often leading to private and isolated patterns of substance use. Understanding this biological basis is paramount for developing targeted and effective interventions for substance use disorders, recognizing that different personality types may require distinct therapeutic approaches.
Extraversion & Substance Use
The inherent drive for stimulation in extraverted individuals creates distinct pathways to substance use, often mediated by social contexts and positive expectancies. Research consistently highlights several mechanisms through which extraversion is linked to substance abuse.
One significant mechanism is the social-amplification pathway. Extraverts are naturally drawn to social gatherings and environments that offer high levels of stimulation. These settings frequently involve alcohol and other substances, leading to increased exposure and opportunities for use. A longitudinal study of 1,200 first-year undergraduates, for example, found that high extraversion predicted earlier alcohol initiation and a greater number of drinking days throughout their freshman year (Geeraerts & Cooper, 2022). This suggests that the extravert's desire for social engagement and excitement places them in situations where substance use is prevalent, thereby amplifying their risk. Even though alcohol is a depressant, and extraverts generally prefer stimulants, the social context in which alcohol is consumed often provides the stimulating environment that extraverts seek. They are drawn to the party culture, the lively interactions, and the overall buzz of social events where alcohol is a common lubricant. This social aspect can override the physiological effects of alcohol as a depressant, making it appealing for its ability to facilitate social interaction and reduce social anxiety, particularly for extraverts who may also experience neurotic tendencies.
Another crucial mechanism is the positive-expectancy mechanism. Extraverts tend to hold stronger positive expectancies regarding the effects of alcohol and other substances. They anticipate that substance use will enhance their social experiences, increase pleasure, and reduce inhibitions, thereby facilitating the very social engagement they crave. A meta-analysis of 46 studies revealed that extraversion was significantly associated with stronger positive alcohol expectancies, and these expectancies fully mediated the frequency of heavy-episodic drinking (Kuntsche et al., 2021). This means that extraverts are more likely to believe that drinking will lead to desirable outcomes, which in turn drives their higher rates of consumption, particularly in binge drinking scenarios. The expectation of amplified positive social experiences fuels their engagement with substances.
Furthermore, there is a clear drug specificity linked to extraversion. Due to their chronically under-stimulated cortical arousal, extraverts exhibit a pronounced preference for stimulants. These substances, such as caffeine, cocaine, and methamphetamine, artificially increase neural activity, helping extraverts achieve their desired level of internal stimulation. A twin analysis, controlling for shared genetics, found that extraversion was uniquely linked to stimulant and cocaine use (Dash, Martin, & Slutske, 2023). This preference is not merely anecdotal; it is rooted in the biological drive to compensate for lower baseline brain activity. For an extravert, a stimulant can make an otherwise mundane situation feel more engaging and exciting, aligning with their inherent need for high levels of arousal. This explains why they might be more drawn to substances that "speed up" their internal experience, making social interactions and other activities feel more vibrant and stimulating.
It is also important to consider the interplay between extraversion and other personality traits, such as neuroticism. An individual can be a highly neurotic extravert, meaning they are outgoing and seek stimulation but also experience significant anxiety. In such cases, alcohol, despite being a depressant, can function as an anxiolytic, reducing their anxiety in social settings. This dual effect—providing social lubrication and anxiety reduction—can make alcohol particularly alluring, increasing the likelihood of binge drinking episodes. The combination of a desire for high stimulation and a need to manage anxiety can create a complex vulnerability profile for extraverted individuals.
Clinical & Treatment Implications for Extraversion
Understanding the unique characteristics of extraverted individuals has significant implications for tailoring effective clinical interventions for substance use disorders. Treatment strategies for extraverts should leverage their inherent social energy and desire for stimulation, while also addressing their specific vulnerabilities.
- Leverage Social Energy: Extraverts thrive in environments that offer social interaction and engagement. Therefore, treatment approaches should actively incorporate group-based modalities. This includes group cognitive behavioral therapy (CBT), where the interactive nature of the setting can keep extraverts engaged and motivated. Peer-led recovery meetings, such as Alcoholics Anonymous (AA) or Narcotics Anonymous (NA), can be highly beneficial, as they provide a structured social environment and opportunities for connection. While AA generally works equally well for introverts and extraverts once engaged, extraverts may find the group dynamics and shared experiences particularly appealing, fostering a sense of belonging and accountability. Additionally, organizing "sober socials" or other pro-social, substance-free activities can provide extraverts with the stimulation and social connection they crave without the involvement of substances. These interactive activities can boost attendance and engagement in recovery programs.
- Watch Party Culture and Protective Behavioral Strategies: Extraverts are often drawn to high-stimulation settings, such as parties, concerts, or sporting events, where substance use might be prevalent. Instead of advocating for complete avoidance of such environments, which may be unrealistic or unsustainable for some extraverts, it is crucial to teach protective behavioral strategies (PBS). These strategies aim to reduce the risks associated with substance use in high-stimulation settings. Examples include pacing drinks, alternating alcoholic beverages with water, setting limits on consumption, avoiding drinking games, and having a designated sober friend. For extraverts, who may get caught up in the excitement and social dynamics of these environments, learning how to navigate them safely is paramount to preventing binge drinking episodes.
- Use Motivational Incentives: Extraverts are often driven by external rewards and recognition. Incorporating motivational incentives into treatment can significantly enhance their engagement and retention. This could involve public recognition boards for achieving sobriety milestones, offering leadership roles in after-care programs or peer support groups, or providing voucher incentives for adherence to treatment goals. Public acknowledgment and opportunities to lead can tap into an extravert's desire for dominance and social validation, keeping them motivated and invested in their recovery journey.
- Address Relapse Triggers: For extraverts, common relapse triggers often include loneliness and boredom. When deprived of the external stimulation and social interaction they naturally crave, extraverts can experience significant discomfort and a strong urge to seek out substances as a means of alleviating this under-stimulation. Therefore, during early abstinence, it is critical to help extraverts schedule pro-social, substance-free activities. This proactive approach ensures that their need for engagement and connection is met through healthy outlets, reducing the likelihood of turning back to substances. Therapists should work with extraverted clients to identify and plan for periods of potential boredom or isolation, equipping them with a repertoire of alternative, stimulating activities.
While extraverts generally form rapport easily and are highly engaging in therapy, clinicians should be mindful of their potential for quick boredom. Therapy sessions, particularly those involving deep introspection or slow processing of emotions, might feel less stimulating than what an extravert is accustomed to. Therefore, therapists may need to employ more active, engaging techniques, incorporate varied activities, and maintain a dynamic pace to keep extraverted clients invested. The goal is to channel their natural drive for engagement and reward-seeking into the recovery process, transforming their inherent personality traits into assets for long-term sobriety.
Brain Asymmetry: Hemispheric Dominance and Personality
Beyond the broad dimensions of personality, a deeper understanding of individual differences can be found in the subtle yet significant variations in brain activity, particularly in the concept of brain asymmetry or hemispheric dominance. This area, however, has often been subject to popular misconceptions that warrant clarification. The notion of being "right-brained" (creative, emotional, holistic) versus "left-brained" (logical, verbal, analytical) is a sweeping generalization that lacks scientific accuracy. While certain functions, such as language production (e.g., Broca's area), are predominantly localized in one hemisphere, the brain functions as an integrated whole, with both hemispheres constantly communicating and collaborating. Therefore, it is crucial to distinguish scientific understanding from pop-psychology simplifications. This discussion will not delve into psychological interventions like Eye Movement Desensitization and Reprocessing (EMDR) or neurolinguistic programming, nor will it address outdated concepts of "masculine versus feminine hemispheres."
Instead, brain asymmetry, in a scientifically grounded context, refers to the quantifiable differences in activation levels between the right and left sides of the brain, typically measured through techniques like electroencephalography (EEG). This difference is often expressed as a numerical value: a negative number indicates higher activity on the left side of the brain, while a positive number indicates a higher degree of activity on the right side of the brain. These differences, even at rest, have been found to predict an individual's emotional disposition. Specifically, research has shown that individuals with greater right frontal EEG activity (positive asymmetry) tend to exhibit more pessimistic emotional dispositions. Conversely, those with greater left frontal EEG activity (negative asymmetry) are often characterized by more upbeat or optimistic emotional dispositions.
Further research has refined this understanding by examining brain asymmetry in response to emotional stimuli. When participants were exposed to films designed to elicit specific emotions, individuals with higher left hemisphere activity were more responsive to positive mood films, experiencing and expressing more positive affect. Conversely, those with higher right hemisphere activity showed greater responsiveness to negative mood films, indicating a heightened sensitivity to distressing emotions. This suggests that hemispheric dominance is not merely a static state but influences how individuals process and react to emotional information from their environment.
The initial understanding of total differences in hemispheric dominance was limited by the sensitivity of older EEG technology, which could not pinpoint specific brain regions with precision. However, advancements in neuroimaging have allowed researchers to describe these differences more accurately in terms of approach and avoidance emotional tendencies. This refined perspective posits that distinct neural circuits are responsible for motivating behavior towards desired outcomes (approach) and away from undesired ones (avoidance).
Specifically, left hemisphere activity is associated with approach behaviors and emotions. This includes emotions such as joy, interest, and even anger (when anger is directed towards overcoming an obstacle or achieving a goal). The left prefrontal cortex, in particular, is linked to the Behavioral Activation System (BAS), which drives individuals towards incentives and rewards.
In contrast, right hemisphere activity is associated with avoidance behaviors and emotions. This includes emotions such as distress, disgust, and fear, which motivate withdrawal from perceived threats or negative stimuli. The right prefrontal cortex is linked to the Behavioral Inhibition System (BIS), which is responsible for inhibiting behavior in the face of potential punishment or danger.
This shift in understanding from broad hemispheric dominance to specific approach and avoidance systems provides a more nuanced and clinically relevant framework for understanding how brain asymmetry influences personality and, by extension, vulnerability to substance use disorders. It highlights that emotional disposition is not simply about being generally "positive" or "negative," but rather about the relative strength of one's motivational systems for engaging with or withdrawing from the world.
BIS/BAS: Behavioral Activation System and Behavioral Inhibition System
The Behavioral Inhibition System (BIS) and the Behavioral Activation System (BAS) represent two fundamental neurobiological systems that underpin individual differences in motivation, emotion, and behavior, offering a powerful framework for understanding personality pathways to substance use. These systems, rooted in brain asymmetry, govern an individual's sensitivity to cues of punishment versus reward.
The Behavioral Inhibition System (BIS) is a neurological system in the brain that is primarily responsible for causing individuals to withdraw from undesirable stimuli or potential threats. It is associated with vigilance, anxiety, and a tendency to inhibit ongoing behavior in the face of punishment or non-reward. Individuals with a highly active BIS are more sensitive to cues of punishment and tend to experience emotions like distress, disgust, and fear. Self-reports of high BIS sensitivity are correlated with higher activity levels in the right frontal area of the brain, particularly the right prefrontal cortex. This system is thought to involve serotonin activity, which plays a role in modulating mood and anxiety. Greater BIS activity is characteristic of introversion, neuroticism, and low agreeableness, as these traits are often associated with caution, emotional reactivity to negative stimuli, and a tendency to avoid social conflict or perceived threats.
Conversely, the Behavioral Activation System (BAS) directs individuals toward certain desirable goals or incentives. It is responsible for approach emotions such as joy, interest, and even anger when it serves as a motivator to overcome obstacles. Individuals with a highly active BAS are more sensitive to cues of reward and tend to pursue goals vigorously. Self-reports of high BAS sensitivity are correlated with higher activity levels in the left frontal area of the brain, particularly the left prefrontal cortex. This system is strongly linked to dopamine activity, a neurotransmitter crucial for reward processing and motivation. Greater BAS activity is characteristic of extraversion and openness to experience, as these traits are associated with a drive for novelty, social engagement, and a general pursuit of positive experiences.
It is important to understand that BIS and BAS sensitivities are not mutually exclusive; an individual can be high in both, low in both, or high in one and low in the other. Temperament differences often emerge as a relative balance between positive affect/approach behaviors (BAS) and negative affect/inhibition behaviors (BIS).
- BAS sensitivity (Dornbach-Bender et al., 2020) magnifies an individual's reactions to positive events and correlates with higher self-reported positive affect. These individuals are highly responsive to rewards and are motivated by the anticipation of pleasure.
- BIS sensitivity (Lin et al., 2023) magnifies an individual's reactions to negative events and is strongly related to neuroticism. These individuals are highly responsive to potential punishments and are motivated by the avoidance of pain or negative outcomes.
The interplay of these systems can explain various psychological difficulties:
- Anxiety: Often indicative of an oversensitive BIS activity, where individuals are excessively vigilant to potential threats and prone to worry and avoidance behaviors.
- Depression: Can be associated with high BIS activity (increased sensitivity to negative experiences) coupled with weak BAS activity (reduced motivation to pursue rewards and experience pleasure).
- Antisocial personality: Often characterized by high BAS activity (strong drive for reward and sensation-seeking) combined with low BIS activity (weak responsiveness to punishment or negative consequences), leading to impulsive and reckless behaviors without sufficient inhibition.
Understanding the relative strengths of an individual's BIS and BAS provides a powerful lens through which to view their vulnerability to substance use disorders and to tailor interventions more effectively.
BIS/BAS and Substance-Use Disorders
The Behavioral Inhibition System (BIS) and Behavioral Activation System (BAS) framework provides a robust explanation for distinct pathways to substance use disorders, influencing drug preference, craving, and relapse patterns. The differential sensitivity to reward and punishment cues, mediated by these systems, plays a critical role in shaping an individual's relationship with substances.
High BAS (Reward Sensitivity): Individuals with a highly active BAS are inherently more sensitive to cues of reward and are driven by the pursuit of pleasure and positive experiences. This heightened reward sensitivity has been consistently linked to various aspects of substance use. Research indicates that high BAS is associated with earlier initiation of substance use, higher frequency of use, and greater polysubstance involvement (Loxton & Dawe, 2001; Keough & O’Connor, 2014). This is particularly true for stimulants and alcohol. Stimulants, by their very nature, directly activate the brain's reward pathways, providing the intense positive reinforcement that high BAS individuals crave. Alcohol, while a depressant, is often consumed in social, stimulating environments that offer immediate rewards (e.g., social connection, reduced inhibition), making it appealing to those driven by BAS.
Furthermore, a BAS-dominant profile strongly predicts stronger cue-induced craving and rapid reinstatement after abstinence (Franken & Muris, 2006). This means that individuals with a high BAS are more likely to experience intense cravings when exposed to environmental cues associated with substance use (e.g., seeing a bottle of alcohol, being in a place where they used to use). Their strong drive for reward makes them highly susceptible to these triggers, leading to a quicker return to substance use even after periods of abstinence. The anticipation of pleasure and the memory of past rewards associated with the substance exert a powerful pull, making sustained recovery challenging without targeted interventions.
High BIS (Punishment Sensitivity): Conversely, individuals with a highly active BIS are more sensitive to cues of punishment, threat, and negative emotional states. Their motivation is often driven by the desire to avoid pain, anxiety, or discomfort. This heightened punishment sensitivity influences their drug preference, leading them towards substances that dampen negative affect. High BIS sensitivity is associated with a preference for anxiolytic or depressant drugs, such as opioids and benzodiazepines (e.g., Valium, Xanax), and alcohol (Simons, Wills, & Gibbons, 2009). These substances provide a sense of calm, reduce anxiety, and alleviate emotional distress, offering a temporary escape from the discomfort associated with an overactive BIS. For these individuals, substance use is often a form of self-medication, a means to quiet an agitated internal state or to cope with overwhelming negative emotions.
Moreover, a BIS-dominant profile is strongly associated with relapse under stress or social threat, mediated by worry and avoidance coping (Keough & O’Connor, 2014). When faced with stressful situations, interpersonal conflicts, or perceived social threats, individuals with a high BIS are more likely to experience intense anxiety and engage in avoidance behaviors. Substance use becomes a readily available coping mechanism to escape these uncomfortable feelings, even if it leads to long-term negative consequences. The cycle of stress, anxiety, avoidance, and substance use can be particularly entrenched for BIS-dominant individuals, making stress management and anxiety-focused strategies crucial components of their treatment.
In summary, the BIS/BAS framework highlights that substance use is not a monolithic phenomenon but rather a multifaceted issue driven by distinct motivational pathways. High BAS individuals are drawn to substances for their rewarding, pleasure-enhancing effects, leading to a focus on approach-based motivations. High BIS individuals, on the other hand, are drawn to substances for their anxiety-reducing, pain-dampening effects, driven by avoidance motivations. Recognizing these differential sensitivities is paramount for clinicians to develop personalized and effective treatment strategies that address the unique underlying motivational drivers of each client's substance use disorder.
BIS/BAS-Informed Treatment Implications
The insights derived from the Behavioral Inhibition System (BIS) and Behavioral Activation System (BAS) framework offer invaluable guidance for tailoring treatment interventions for substance use disorders. By understanding a client's predominant motivational system—whether they are primarily driven by reward seeking (BAS) or punishment avoidance (BIS)—clinicians can design more effective and personalized therapeutic strategies.
For High BAS Clients (Reward Sensitivity):
High BAS clients, characterized by their strong drive for reward and sensitivity to incentives, respond best to approach-based interventions that emphasize immediate gains and positive reinforcement.
- Contingency Management: This is a highly effective approach for high BAS individuals. It involves providing tangible rewards (e.g., vouchers, privileges) for desired behaviors, such as negative drug tests or attendance at treatment sessions. The immediate and consistent reinforcement directly taps into their reward-seeking motivation, making abstinence and treatment adherence more appealing.
- Voucher Incentives: Similar to contingency management, voucher programs offer monetary or other valuable incentives that can be exchanged for goods or services. This provides a clear, tangible reward system that aligns with the BAS drive for positive outcomes.
- Goal-Oriented Cognitive Behavioral Therapy (CBT): CBT approaches that frame abstinence as an immediate gain, focusing on the positive rewards of sobriety (e.g., improved health, better relationships, financial stability), are particularly effective. This involves helping clients identify and pursue new, healthy goals that provide a sense of accomplishment and reward, replacing the gratification previously sought from substances.
- Tailoring Motivational Interviewing Frames: "Possible Selves" (BAS-focused): In motivational interviewing, clinicians can leverage the concept of "possible selves" to highlight a rewarding future self. For high BAS clients, this means emphasizing the "thriving sober self"—a future where they experience increased joy, success, social connection, and personal fulfillment as a direct result of abstinence. This positive vision taps into their intrinsic motivation for reward and achievement.
- Integrating BIS/BAS Assessments: Utilizing assessments like the Carver-White scale at intake can provide valuable information about a client's BIS/BAS profile. This allows for improved treatment-matching and has been shown to predict treatment retention (Daughters et al., 2008). Knowing a client's motivational tendencies from the outset enables clinicians to select interventions that are most likely to resonate and be effective.
For High BIS Clients (Punishment Sensitivity):
High BIS clients, who are more sensitive to punishment and driven by the avoidance of negative emotional states (like anxiety), benefit most from anxiety-focused strategies that reduce punishment expectancy and provide effective coping mechanisms for distress.
- Mindfulness: Mindfulness-based interventions, such as Mindfulness-Based Relapse Prevention (MBRP), are highly beneficial. These practices help clients develop a non-judgmental awareness of their internal experiences, including cravings and anxiety, without being overwhelmed by them. By observing thoughts and feelings without reacting impulsively, clients can reduce their reliance on substances as an avoidance strategy. Mindfulness helps to lower craving and improve emotional regulation, offering a quiet coping skill that aligns with an introvert's preference for less external stimulation.
- Exposure Plus Relaxation: This therapeutic technique involves gradually exposing clients to anxiety-provoking situations or cues (e.g., places where they used to use, stressful social scenarios) while simultaneously teaching and practicing relaxation techniques. This helps to reduce the conditioned fear response and build tolerance to discomfort without resorting to substance use. It directly addresses the avoidance motivation characteristic of high BIS individuals.
- Safety-Planning: Developing comprehensive safety plans helps high BIS clients identify potential triggers for anxiety and relapse and pre-plan concrete strategies to manage these situations without using substances. This reduces the uncertainty and perceived threat, thereby decreasing punishment expectancy and enhancing their sense of control.
- Tailoring Motivational Interviewing Frames: "Possible Selves" (BIS-focused): For high BIS clients, motivational interviewing can emphasize the "feared future self" or a "rock-bottom" scenario. This approach leverages their avoidance motivation by highlighting the negative consequences of continued substance use (e.g., health deterioration, loss of relationships, financial ruin). By vividly contrasting their current struggles with a potentially worse future, clinicians can motivate clients to pursue abstinence as a means of avoiding these feared outcomes (Simons et al., 2009).
- Individualized and Smaller Group Therapies: Introverts, who often characterize high BIS profiles, tend to have a slower alliance formation in therapy. Building rapport and disclosing intimate details can be highly stimulating and overwhelming for them. Therefore, one-on-one motivational interviews or cognitive behavioral therapy in small groups (rather than large ones) are often more effective. In larger groups, extraverts may dominate, causing introverts to withdraw and limit their disclosure, thereby hindering their therapeutic progress. The increased availability of telehealth services, particularly since the pandemic, has also proven beneficial for naturally introverted individuals, allowing them to engage in therapy from the comfort of their own environment, reducing external stimulation.
By integrating BIS/BAS assessments at intake and tailoring interventions accordingly, clinicians can significantly improve treatment-matching and predict retention rates. This personalized approach acknowledges the unique motivational landscape of each client, fostering greater engagement and ultimately leading to more successful and sustainable recovery outcomes.
Conclusion
The journey through the intricate pathways connecting personality to substance use disorders reveals a profound and multifaceted relationship. It underscores that vulnerability to addiction is not a monolithic phenomenon but rather a complex interplay of innate temperament, learned behaviors, and underlying neurobiological systems. By delving into the Big Five personality traits, with a particular focus on extraversion and introversion, and the Behavioral Inhibition System (BIS) and Behavioral Activation System (BAS) framework, this article has illuminated how individual differences shape drug preferences, patterns of use, and responsiveness to therapeutic interventions.
We have seen that personality, as the dynamic outcome of temperament interacting with environmental influences, provides a consistent lens through which to understand an individual's behavioral patterns across time and situations. The Big Five model—encompassing Openness to Experience, Conscientiousness, Extraversion, Agreeableness, and Neuroticism—offers a comprehensive yet succinct framework for categorizing these enduring traits. While each trait contributes uniquely to an individual's risk profile, the dimensions of extraversion and introversion stand out due to their direct links to cortical arousal and the pursuit or avoidance of stimulation.
The biological basis of introversion and extraversion, particularly the role of the Ascending Reticular Activation System (ARAS) in regulating cortical arousal, provides a compelling explanation for divergent preferences. Extraverts, with their chronically under-stimulated brains, gravitate towards stimulants and high-stimulation environments, seeking to elevate their arousal to an optimal level. Their social-amplification and positive-expectancy pathways often lead to earlier initiation and higher frequency of substance use, especially alcohol and stimulants, within social contexts. Conversely, introverts, with their chronically higher baseline arousal, prefer depressants and quieter environments, using substances to dampen overwhelming neural activity and cope with anxiety or social overstimulation.
The BIS/BAS framework further refines this understanding, distinguishing between approach-motivated (BAS) and avoidance-motivated (BIS) individuals. High BAS sensitivity predicts a preference for rewarding substances and a heightened risk of cue-induced craving and relapse driven by the pursuit of pleasure. High BIS sensitivity, on the other hand, is linked to a preference for anxiolytic substances and a greater susceptibility to relapse under stress, driven by the desire to alleviate discomfort and avoid negative emotions.
The clinical implications of this knowledge are profound. Recognizing a client's predominant personality traits and motivational systems allows for the tailoring of interventions, moving beyond a one-size-fits-all approach. For extraverted, high BAS clients, strategies that leverage their social energy, provide positive incentives, and teach protective behavioral strategies in stimulating environments are crucial. Group therapies, peer-led recovery, and goal-oriented CBT that frames abstinence as immediate gain can be highly effective. For introverted, high BIS clients, anxiety-focused strategies, mindfulness, exposure with relaxation, and safety planning are paramount. Individualized therapy or smaller group settings, where they feel less overwhelmed, are often more conducive to building rapport and facilitating disclosure. Tailoring motivational interviewing to emphasize either "thriving sober selves" (for BAS) or "feared future selves" (for BIS) can further enhance engagement.
Ultimately, integrating personality assessments and principles into substance abuse treatment fosters a more empathetic, nuanced, and effective approach. By understanding the unique internal landscape of each client—their inherent drives, sensitivities, and coping mechanisms—clinicians can develop personalized pathways to recovery that resonate with the individual, enhancing treatment retention and promoting long-term sobriety. This holistic perspective not only improves clinical outcomes but also deepens our appreciation for the rich tapestry of human diversity in the journey towards healing.
References
Avila, C., & Parcet, M. A. (2022). Reward and punishment sensitivity modulate response to anxiety-management training in substance-use disorder. Journal of Psychopharmacology, 26(2), 206–214. https://doi.org/10.1177/0269881111405365
Bullock, W. A., & Gilliland, K. (1993). Eysenck’s arousal theory of introversion–extraversion: A converging-measures investigation. Journal of Personality and Social Psychology, 64(1), 113–123. https://doi.org/10.1037/0022-3514.64.1.113
Carver, C. S., & Scheier, M. F. (2016). Perspectives on personality (8th ed.). Pearson.
Dash, G. F., Martin, N. G., & Slutske, W. S. (2023). Big Five personality traits and illicit drug use: Specificity in trait–drug associations. Psychology of Addictive Behaviors, 37(2), 318–330. https://doi.org/10.1037/adb0000793
Daughters, S. B., Lejuez, C. W., Strong, D. R., Brown, R. A., & Kahler, C. W. (2008). The role of reward sensitivity in the effectiveness of contingency management for smoking cessation. Journal of Consulting and Clinical Psychology, 76(5), 852–861. https://doi.org/10.1037/0022-006X.76.5.852
Dornbach-Bender, A., Ruggero, C. J., Smith, P., & Schuler, K. (2020). Association of behavioral activation system sensitivity to lower-level facets of positive affect in daily life. Personality and Individual Differences, 152, 109570. https://doi.org/10.1016/j.paid.2019.109570
Franken, I. H. A., & Muris, P. (2006). Gray’s impulsivity dimension and substance use: BIS/BAS personality characteristics and cannabis use in adolescents. Addictive Behaviors, 31(5), 849–854. https://doi.org/10.1016/j.addbeh.2005.06.012
Geeraerts, S. B., & Cooper, M. L. (2022). Extraversion and alcohol use in the first year of college: A daily-diary approach. Addictive Behaviors, 131, 107293. https://doi.org/10.1016/j.addbeh.2022.107293
Gray, J. A. (1970). The psychophysiological basis of introversion–extraversion. Behaviour Research and Therapy, 8(3), 249–266. https://doi.org/10.1016/0005-7967(70)90069-0
Keough, M. T., & O’Connor, R. M. (2014). Clarifying the role of worry in substance-use behaviors using the BIS/BAS framework. Addictive Behaviors, 39(9), 1391–1398. https://doi.org/10.1016/j.addbeh.2014.04.017
Kuntsche, S., Kuntsche, E., & Gmel, G. (2021). Personality and alcohol expectancies: A systematic review and meta-analysis. Addiction, 116(11), 2997–3011. https://doi.org/10.1111/add.15470
Lin, Q., Jiang, M., & Xu, Y. (2023). Behavioral inhibition sensitivity magnifies negative affect reactivity: Evidence from a daily-experience study. Personality and Individual Differences, 205, 112005. https://doi.org/10.1016/j.paid.2023.112005
Loxton, N. J., & Dawe, S. (2001). Reward and punishment sensitivity in dysfunctional eating and hazardous drinking in adolescents: The influence of BIS/BAS. Personality and Individual Differences, 31(3), 371–385. https://doi.org/10.1016/S0191-8869(00)00147-0
Morris, D. (1969). The human zoo. McGraw–Hill.
Simons, J. S., Wills, T. A., & Gibbons, F. X. (2009). The role of BAS and BIS in substance use: Cue reactivity and craving in daily life. Addictive Behaviors, 34(3), 252–257. https://doi.org/10.1016/j.addbeh.2008.10.004
Wardell, D. J. (1974). Stimulus intensity and introversion–extraversion: Toward an optimal-level theory. Australian Journal of Psychology, 26(2), 75–82. https://doi.org/10.1080/00049537408255202
Additional Current References
Please Note: The following resources have been included as additional resources associated with this topic area. These resources were not used by the presenter when creating this course.
Ayhan, C. H., Aktas, M. C., Aktaş, S., & Ali Tarakçi, A. S. (2025). The examination of the relationship between 5-factor personality traits and social anxiety among Iindividuals with alcohol and substance use disorders. Eastern Journal of Medicine, 30(1), 82–90. https://doi-org.ezproxy.uu.edu/10.5505/ejm.2025.98853
Forstmann, M., & Sagioglou, C. (2025). The content, consistency and accuracy of stereotypes about recreational users of various psychoactive substances. European Journal of Social Psychology, 1. https://doi-org.ezproxy.uu.edu/10.1002/ejsp.3162
Jain, T., Patriquin, M., & Sanches, M. (2025). Associations between big five personality dimensions and lifetime use of cannabis. American Journal on Addictions, 34(3), 322–326. https://doi-org.ezproxy.uu.edu/10.1111/ajad.13668
Martínez-Gabaldón, E., & Martínez-Pérez, J. E. (2025). Personality traits and drug use: A longitudinal study using data from the British Cohort Study. European Addiction Research, 30(6), 357–365. https://doi-org.ezproxy.uu.edu/10.1159/000541265
Sharifibastan, F., Erevik, E. K., Morken, K. T. E., & Pallesen, S. (2025). Associations between HEXACO personality traits, substance use disorders, and behavioral addictions: a protocol for a comprehensive systematic review and meta-analysis. Systematic Reviews, 14(1), 1–10. https://doi-org.ezproxy.uu.edu/10.1186/s13643-024-02741-8
Citation
Ampel, B. (2025). Personality pathways to substance abuse: Understanding traits, risks, and treatment. Continued - Psychology, Article 109. Available at www.continued-psychology.comMay 30, 2025
1 CE CreditEco-anxiety: Symptoms and Solutions
Karen Magruder, LCSW-S, MSW
Editor's Note: This text-based course is an edited transcript of the webinar, Eco-anxiety: Symptoms and Solutions, presented by Karen Magruder
MSW LCSW-S.Learning Outcomes
After this course, participants will be able to:
- Explain key symptoms of eco-anxiety.
- Describe the prevalence of eco-anxiety among diverse populations.
- List evidence-based treatments for eco-anxiety.
Introduction
Hello, everyone. Thank you for joining me today as we explore the topic of eco-anxiety, how it manifests, and what we, as clinicians, can do about it. Before we dive into the heart of the discussion, let’s take a moment to cover some housekeeping details.
Limitations/Risks
Eco-anxiety is a highly complex topic, and this webinar is designed to provide an introduction to eco-anxiety and some treatment options. It’s important to note that this presentation is not intended to be an exhaustive or all-encompassing exploration of the subject. Eco-anxiety can manifest differently across various cultures and communities, so as practitioners, it’s crucial to exercise cultural humility and acknowledge diverse perspectives. This ensures that we avoid a one-size-fits-all approach and provide care that is sensitive to individual and community needs.
Session Overview
By the end of this session, I hope to achieve the outlined learning outcomes. To set the stage, I’d like to share a bit of my story—how, as a social worker, my professional identity intersected with environmental issues, and how I came to care deeply about and gain knowledge on these topics within a social work context. After that, we’ll explore eco-anxiety by examining its causes, symptoms, and prevalence, particularly among diverse populations. Finally, we’ll delve into clinical interventions that are either evidence-based or show promise in treating and addressing eco-anxiety, with the goal of helping individuals develop effective coping strategies.
What Are Your Burning Questions? (Live Webinar)
Before we get started, I’d like to get a general sense of your questions about eco-anxiety. I see someone caught the intentional use of “burning questions” there—yes, that’s exactly the point. Our house is on fire, after all. I’ve noted a few points to address along the way, and we’ll revisit the rest later. Let’s dive in!
My Story
As promised, I want to provide some context for today’s presentation by sharing my personal and professional journey, particularly how ecological and environmental issues intersect with my work in social services and mental health. I’ve always appreciated the benefits of spending time in nature—the awe, wonder, and mental health boost that comes with being outdoors. Growing up, I valued the beauty of the natural world and tried to be as environmentally responsible as I could, doing things like recycling, reducing waste, turning off lights, and conserving water. These were all small steps to reduce my carbon footprint, but I never really considered the physical environment as an integral part of social work or social service practice.
In my education and early career, we focused on the political, economic, and social environments, but the literal environment wasn’t emphasized in the same way. That began to shift for me as I started seeing not only the benefits I enjoyed from nature but also the challenges and disruptions that environmental issues caused in daily life. For example, living in Phoenix, Arizona, where the heat can be extreme—it’s 110 degrees today as I speak!—I’ve seen firsthand how these conditions can range from small inconveniences, like recycling bins warping in the heat, to major disruptions in daily life.
The turning point for me came during Hurricane Harvey in Texas. At the time, I was living in Dallas and working with older adults in assisted living and nursing facilities. I witnessed the disproportionate impact of the hurricane on this vulnerable population. Many older adults had mobility or health issues, limited support networks, fixed incomes, and a physiological susceptibility to environmental challenges. These factors made them particularly vulnerable during and after the storm. I volunteered at a shelter providing crisis intervention and saw how unprepared the system was to meet their needs. The nonprofit I worked for, The Senior Source, stepped in to provide walkers, adult incontinence supplies, and assistance with continuity of care for home healthcare and medications.
That experience was a wake-up call for me. I realized that social and environmental issues aren’t siloed, with social workers addressing one and environmentalists tackling the other. They’re deeply connected. For instance, as I continued working with older adults, I saw how heat waves strained nonprofits that were trying to bridge gaps in resources, such as installing or repairing air conditioning or providing cooling centers. Older adults, who are less physiologically adaptable to extreme heat, were especially at risk, and it became clear how environmental issues exacerbate social vulnerabilities.
After that lightbulb moment, I pursued more education to deepen my understanding. I earned a certificate in Climate Change and Health from Yale and became involved in the Climate Reality Project through Al Gore’s activism. These experiences helped me educate others about the connections between climate issues and social justice. Now, as a social worker and educator, I focus on treating eco-anxiety, which we’ll discuss more in-depth shortly, while also raising awareness about how clinicians and social service professionals have a critical role to play. Environmental scientists aren’t the only ones who can contribute to solutions. We, too, have skills and expertise that are vital in addressing these intertwined challenges.
Earth Has a Fever
All of that is to say that, in my studies and efforts to better understand these issues and how I could contribute, I’ve come to see it this way: the Earth has a fever. While it’s beyond the scope of this lecture to delve into all the environmental issues we’re facing, I find this simplified analogy helpful. Just as a small increase in my body temperature—from 98.6 to, say, 101 degrees—might seem minor, it makes a big difference in how I feel and function. The same is true for the Earth. Even a few degrees of warming can have profound effects on ecosystems, intensifying disruptions and rippling through the planet’s systems.
While climate change is a major challenge, it’s not the only ecological issue we face. Unfortunately, vulnerable and historically marginalized populations often feel the impacts of these crises first and worst. For example, as I shared earlier, the disproportionate effects of Hurricane Harvey and extreme heat waves in Texas highlighted how environmental challenges exacerbate existing inequities. These realities underscore the need for us to address both the ecological and social dimensions of these problems.
Today's Environmental Injustices
Figure 1 shows some of today's environmental injustices.
Figure 1. Today's environmental injustices.
While it’s beyond the scope of my talk today to provide an exhaustive list of the environmental injustices we face, some key examples include increasing heat waves, the rising intensity of hurricanes, climate-forced migration, and various forms of pollution—whether air pollution, plastic waste, litter, or other contaminants. Other issues include food deserts, where low-income urban communities lack access to fresh and affordable food, and the disposal of toxic waste, such as chemical or nuclear waste. Access to clean and safe water is another critical issue.
These environmental injustices affect not just our clients but many of us as well. They remind us of the interconnectedness of these challenges and the urgent need to address them on both systemic and personal levels.
How Does That Make You Feel?
Given the brief overview I’ve just shared about some of the challenges our Earth is facing, how does that make you feel? Even after just a short discussion of these pressing issues, I’d love to hear your thoughts. If you’re comfortable, please share in the chat how you’re feeling, and I’ll read some of your responses aloud.
I’m seeing a range of emotions here: frightened, anxious, depressed, frustrated, devastated, concerned, helpless, overwhelmed, powerless, worried. Someone mentioned, "The tornado is here," and others shared feelings of anxiety and being uninformed. Thank you so much for sharing. These are powerful and honest responses, and I want to validate and honor these experiences.
It’s certainly not my intention to scare you or ruin your day with this talk. We will absolutely get to solutions and ways to cope. But I think this crowdsourced list of emotions beautifully illustrates the very essence of eco-anxiety. The feelings you’ve shared—anxiety, helplessness, overwhelm, concern—are classic symptoms of eco-anxiety.
For those of you who wanted a clear definition of eco-anxiety, you’ve just captured it in your own words. Eco-anxiety is this collective experience of emotional distress in response to the environmental crises we face. It’s a very real and growing phenomenon, and it impacts not only our clients but also us as professionals. Let’s explore it further.
Eco-anxiety
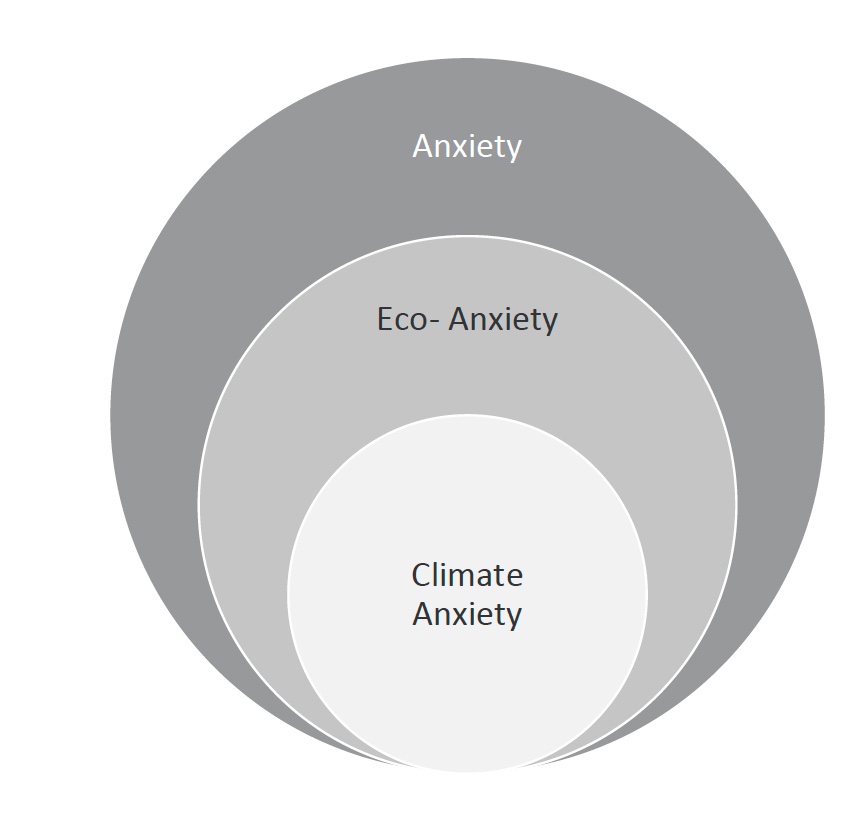
What is eco-anxiety, exactly? Let’s take a closer look at what this really means. It’s described as a pervasive fear of environmental damage or ecological disaster, largely rooted in the current state of the environment and predictions about the future. While I’ll go into more detail about symptoms in the next slide, this definition captures the core of what eco-anxiety entails.
Importantly, eco-anxiety is increasingly recognized as a distinct area of clinical focus—it’s a real and valid concern. However, I want to clarify that it is not currently defined as a distinct diagnosis in the DSM. When I describe it as a topic that clinicians are focusing on, it’s to emphasize the growing interest in understanding and addressing this issue in a sensitive and appropriate way, even though it doesn’t yet have formal diagnostic criteria.
Common Symptoms
How eco-anxiety is defined and its common symptoms are an amalgamation of insights from recent literature, publications, trainings, and other resources on the topic. Since eco-anxiety isn’t codified in the DSM, it’s a bit fuzzier than conditions with formal diagnostic criteria. However, the way I’ll describe it should help you better recognize some of these symptoms or presentations, whether you see them in clients, loved ones, or even yourself.
Some of the common symptoms include pervasive worry. This isn’t just, "Oh, I went to Karen’s lecture, now I’m briefly worried about the Earth having a fever, and then I move on with my day." Instead, it’s a more enduring sense of worry that doesn’t pass quickly. Anxiety, as the term suggests, can present in familiar ways—physiological responses, rumination, and other manifestations typical of anxiety disorders.
A particularly key and unique aspect of eco-anxiety, which many of you touched on earlier, is the feeling of helplessness, powerlessness, or impotence. That overwhelming sense of having little or no control is a common feature. Frustration and anger are also often present, reflecting the emotional toll of witnessing environmental challenges without feeling equipped to make a significant impact. Additionally, we often see symptoms like sleeplessness and changes in eating patterns, both of which are common when stress or anxiety is heightened.
These symptoms paint a picture of how eco-anxiety manifests and how deeply it can affect people, far beyond a fleeting concern. Recognizing these signs is the first step toward addressing and supporting those experiencing eco-anxiety.
Climate Anxiety
Now, to discuss a few different terms, I’m using the term eco-anxiety. Eco-anxiety is kind of middle-level. In Figure 2, I’ve used this graphic to show that we have anxiety in the largest sphere.
Figure 2. Levels of anxiety.
Of course, you can have targets of anxiety related to a number of different issues. Eco-anxiety is a specific subtype of anxiety where you might feel worried, frustrated, helpless, or concerned about issues related to the environment—anything from pollution and toxic waste to climate change and other environmental injustices or problems, like those shown on the previous slide.
Climate anxiety, in turn, is a specific subtype of eco-anxiety, focused specifically on climate change. Given the scope and urgency of climate change, it’s no surprise that climate anxiety is a very common subtype of eco-anxiety. This type of anxiety often centers on what individuals see in the news about the climate crisis and the overwhelming challenge of processing and dealing with it all.
One of the questions I’ve already seen come in is how eco-anxiety differs from general existential dread. In my clinical and professional opinion, they are certainly related. Eco-anxiety and climate anxiety can spur broader existential questions, and having existential conversations can be an effective way to address them. However, eco-anxiety and climate anxiety are more specific than general existential malaise. Hopefully, that helps clarify the distinction.
There was also a question about discussing the evidence of climate change with clients. I’ll touch on that a bit later, as it fits better with what’s coming up next, but I’ll definitely circle back to it.
To summarize, eco-anxiety differs from climate anxiety in that eco-anxiety is broader, encompassing environmental issues beyond climate change, such as toxic waste or pollution, while climate anxiety focuses specifically on the challenges and threats posed by climate change.
Eco-Grief
Another differential diagnosis worth noting is the distinction between eco-anxiety and eco-grief. Eco-anxiety is very future-oriented—it's about worrying over what is to come. In contrast, eco-grief is more past-oriented, involving mourning the loss of what used to be. People might present with both, and they are certainly interconnected and intertwined. However, identifying which one is the more prominent presenting factor can shape the treatment approach. Just as we treat grief differently from anxiety, we also approach eco-anxiety differently than eco-grief.
This talk focuses on eco-anxiety, so we’ll concentrate on addressing future-oriented worries and how to help individuals cope with them effectively.
Other Related Conditions
A final note on related conditions you might encounter: specific phobias are included in the DSM, and you can reference the diagnostic criteria for those. It’s possible for someone to reach the threshold for a diagnosis of a specific phobia, such as one related to climate change. However, eco-anxiety in the general public tends to be less intense than a phobia. Phobias are often perceived as excessive or irrational—not that this perception is necessarily accurate—but eco-anxiety usually falls on a spectrum from realistic concern to potentially more apocalyptic views. For example, as someone mentioned in a question, how do we address individuals with an apocalyptic perspective that may not be rooted in reality? This highlights the spectrum of eco-anxiety, with phobias existing on the more intense end. However, most eco-anxiety doesn’t rise to the level of a diagnosable phobia.
Seasonal Affective Disorder (SAD) is another condition to distinguish from eco-anxiety. SAD is often tied to limited sunlight during certain seasons and affects individuals in a predictable, cyclical pattern. Eco-anxiety, by contrast, is not seasonal and is related to ongoing concerns about the natural environment.
Generalized Anxiety Disorder (GAD) encompasses a broader range of worries, while eco-anxiety is more specific and targeted. Unlike phobias, which may be perceived as irrational, many fears tied to eco-anxiety are well-founded. Concerns about environmental crises—such as animal depopulation, melting glaciers, sea-level rise, extreme weather, and coral bleaching—are grounded in real and observable phenomena. Climate change coverage has shifted from distant "doom-and-gloom" warnings to the unsettling reality that it is already unfolding before our eyes.
One key takeaway, and a spoiler for a treatment strategy, is that validating these concerns is essential. To some degree, eco-anxiety reflects real challenges, and it’s important to acknowledge that it’s not excessive or irrational to feel worried about the climate and the state of our environment. However, the lack of formal inclusion in the DSM can lead to eco-anxiety being underrepresented or misdiagnosed, making it harder to address in clinical settings. This underrepresentation underscores the need for clinicians to approach eco-anxiety with sensitivity and understanding.
Prevalence
Here’s what we know about the prevalence of eco-anxiety. Since it’s not a distinct disorder in the DSM, it’s challenging to measure consistently. However, if eco-anxiety were taken into account with more intentionality in clinical or healthcare settings, scholars and clinicians could gather more reliable statistics. Even with these limitations, reports indicate that eco-anxiety is a growing concern, especially among younger populations.
For instance, "climate emergency" was Oxford Dictionary’s word of the year not long ago, reflecting how pressing this issue has become. In 2021, there was a staggering 4000% increase in Google searches for "climate anxiety," illustrating how awareness and concern are rising. Large-scale surveys, like those conducted by Yale’s Institute for Climate Change, offer additional insights. A recent global survey of over 10,000 young people aged 16 to 25 found that 84% were moderately or extremely worried about climate change. Similarly, a study of the adult U.S. population revealed that 43% of Americans were alarmed or concerned about climate change, and another report indicated that two-thirds of the U.S. population were somewhat or very worried about it.
These figures show that eco-anxiety is not only gaining attention but becoming increasingly relevant in people’s lives. Greta Thunberg’s iconic statement, “Our house is on fire,” resonates deeply, as the concern spans generations. For example, parents may become preoccupied with fears about the future their children or grandchildren will inherit.
Although eco-anxiety isn’t easily measured—there’s no standardized question in the census or in most clinical assessments—estimates suggest that anywhere from 40% to 80% of the U.S. population experiences some level of worry about environmental issues. This means it could reasonably surface in therapeutic contexts, warranting awareness and preparedness among clinicians.
Impacted Populations
Environmental issues affect many, if not all, of us. However, as I mentioned earlier, the impact tends to fall disproportionately on vulnerable and marginalized populations. Eco-anxiety is not just a U.S. phenomenon; it has been documented across the world, including in Canada, Europe, Australia, the Pacific Islands, and Asia. I would venture to say that some degree of eco-anxiety exists everywhere there is concern about environmental issues. Unfortunately, those who have contributed the least to problems like climate change or pollution often suffer the most severe and earliest consequences. These populations face greater exposure to environmental issues, heightened vulnerability, and lower adaptive capacity—the ability to cope and recover from these impacts.
That being said, eco-anxiety is commonly observed among younger people, as reflected in the literature. Youth are often exposed earlier to dire messages about climate change and other environmental injustices, and they arguably have the most at stake. Since they will live to see the long-term effects of environmental crises, they may feel a heightened sense of urgency and responsibility, making them particularly vulnerable to developing eco-anxiety. That said, anyone can experience eco-anxiety, regardless of age or background.
Overview of Interventions
Let’s talk about solutions and interventions for eco-anxiety. This is still an emerging area of focus, with much of the literature having been published since 2020. In my work through a DSW program and other research efforts, I’ve systematically reviewed what scholars and clinicians are identifying as effective ways to address eco-anxiety in therapy. Here’s what I’ve found:
The first and most important step is validation. Recognizing a client’s concern about environmental issues as legitimate is essential. It’s not about labeling someone as an alarmist or dismissing them as a “fragile snowflake.” Often, these concerns are rooted in real evidence of current and worsening environmental issues. Expressing empathy and maintaining a non-judgmental attitude allows clients to feel heard and supported. While eco-anxiety can sometimes involve cognitive distortions that may need to be addressed, most of the time, it’s a natural and valid reaction. Think about Maslow’s hierarchy of needs—food, water, and shelter are fundamental, and when these are threatened, anxiety is a normal response. Validating that anxiety aligns with this reality.
Returning to a pre-submitted question about discussing evidence of climate change with clients: as with any issue, this should be client-led. Meeting clients where they are is crucial. If the topic arises organically, sharing sound, evidence-based knowledge can help validate their concerns or potentially support cognitive reframing. However, this should always be done without imposing an agenda or overwhelming the client with facts unless it feels helpful and appropriate at the moment.
Taking action is another powerful intervention. A hallmark of eco-anxiety is the sense of helplessness. Helping clients regain a sense of control—whether through small, meaningful actions like cultivating a garden, volunteering, or engaging in political activism—can alleviate this feeling. It’s not about solving all the world’s problems as one individual but identifying ways to act in alignment with personal values and passions. For some, this might be through education, art, writing, or science. The key is allowing clients to choose how they engage, rather than prescribing specific actions.
Social support is also invaluable. A strong support network, whether through friends, family, or community groups, can provide understanding, encouragement, and connection. Beyond individual relationships, there are emerging resources like climate cafés—similar to death cafés—where people gather to share their experiences and feelings about environmental issues. These kinds of specific support groups are growing in cities across the U.S. and can offer spaces to process eco-anxiety collectively.
Ecotherapy, or nature-based interventions, is another effective approach. For individuals who associate nature with danger due to experiences like hurricanes or tornadoes, reestablishing a positive connection with the natural world can help. This could involve spending time in parks, hiking, or even incorporating greenery into indoor spaces, such as filling an office with plants. Restoring a balanced relationship with nature can shift perceptions from fear to appreciation and healing.
Mindfulness is a well-established, evidence-based intervention that applies here as well. Eco-grief tends to focus on the past, while eco-anxiety is future-oriented. Mindfulness, with its emphasis on non-judgmental awareness of the present moment, can help clients ground themselves, recenter, and break out of cycles of rumination.
Cognitive reframing is another promising intervention. If a client’s worries are disproportionate or unrealistic, reframing can help create a more balanced perspective. For instance, addressing "should" statements tied to eco-guilt—like “I should be doing more to reduce my carbon footprint”—can encourage clients to acknowledge the efforts they are already making and focus on what is within their control. This technique can foster healthier, more adaptive thought patterns.
Finally, I want to emphasize again the importance of validation. While identifying cognitive distortions is important, it’s equally critical not to shame someone for their response to what is, in many cases, a valid and natural reaction to a real threat. Validation should remain the foundation of any intervention.
Acceptance & Commitment Therapy (ACT)
I see a lot of value and promise in Acceptance and Commitment Therapy (ACT) for treating eco-anxiety. I’ll be presenting at a conference about this in October with a former student of mine. ACT is a well-established, empirically supported psychotherapy that focuses on helping clients accept their current thoughts and feelings rather than getting stuck in past events or excessively worrying about the future.
One of ACT's key strengths is its emphasis on mindfulness. ACT encourages clients to live in the present moment and engage fully with their current experiences, helping them step back from rumination and anxiety while fostering psychological flexibility. ACT also promotes committed action, encouraging clients to take meaningful steps aligned with their values, even in the face of difficult emotions or circumstances.
I find ACT’s hexaflex model for psychological flexibility (as shown in Figure 3) particularly useful when addressing eco-anxiety. It provides a framework for helping clients navigate distressing emotions, build resilience, and make choices that align with their values in a way that feels purposeful and empowering. This combination of acceptance, mindfulness, and committed action makes ACT an especially promising approach for addressing the unique challenges of eco-anxiety.
Figure 3. ACT's hexaflex model of psychological flexibility.
As I’ve already mentioned, mindfulness is a valuable tool, and it’s a key component of ACT. Identifying values is another excellent activity in the context of eco-anxiety. ACT encourages a degree of acceptance around distressing thoughts and emotions, allowing clients to acknowledge their feelings without becoming overwhelmed by them.
What I particularly appreciate about ACT is how it helps align values with committed action. It’s not just about being present, accepting feelings, and defusing unhelpful thoughts—it’s about using that clarity to take meaningful action in alignment with one’s values. This process can be incredibly empowering and is especially effective in addressing the feelings of helplessness that are so often a hallmark of eco-anxiety. By connecting values to action, ACT provides a pathway to move forward with purpose and resilience.
Cognitive Behavioral Therapy (CBT)
As I mentioned earlier when discussing cognitive reframing, Cognitive Behavioral Therapy (CBT) has also been applied to eco-anxiety. One of its strengths is that it’s an evidence-based approach for generalized anxiety and specific phobias, which, as we’ve discussed, share some overlap with eco-anxiety. Cognitive reframing can be a helpful tool for addressing unhelpful thought patterns, but behavioral activation stands out as particularly effective.
Behavioral activation focuses on engaging clients in specific, tangible activities that can improve their mood and help them feel more grounded. These activities might include self-care practices, spending time in nature, or other actions that promote a sense of well-being and resilience. By helping clients identify and engage in meaningful activities, CBT can support them in getting into a better headspace.
That said, it’s important to approach eco-anxiety with care and avoid giving the impression that we are being judgmental or invalidating legitimate concerns. Balancing validation with encouragement toward adaptive behaviors is key to providing effective support.
Self-Care: The UP STREAM Model
I also want to share the UPSTREAM model, a framework I developed to encapsulate best practices for supporting ourselves and our clients who might be experiencing eco-anxiety. As an educator, I love snappy mnemonics and acronyms to make these concepts easier to remember. This model is designed to summarize strategies for addressing eco-anxiety effectively:
U – Understanding and Self-Compassion: This reflects the importance of validation and recognizing that it’s okay to experience distress. Practicing self-compassion helps us acknowledge and manage these feelings without judgment.
P – Participating in the Solution: Taking action is empowering. Encourage clients to decide what this looks like for them based on their own interests, skills, and comfort levels. For example, instead of suggesting specific actions like voting for a particular candidate, ask what resonates with them and aligns with their values.
S – Self-Talk: Addressing and limiting negative self-talk or cognitive distortions that can amplify valid concerns is key. Helping clients identify and reframe these patterns can reduce the intensity of their anxiety.
T – Trauma Healing: While this talk focuses on anxiety, eco-anxiety and eco-grief are interconnected. Many individuals have experienced environmental injustices or personal trauma related to these issues. Supporting clients in processing and healing from these experiences can be essential.
R – Reducing Isolation: Building and maintaining social support is critical. Whether through relationships or participation in community or support groups, reducing isolation can foster resilience and emotional well-being.
E – Ecotherapy: Nature-based interventions help restore a positive relationship with the natural world. Activities like spending time in parks or incorporating greenery into daily spaces can counteract the fear and disconnection that eco-anxiety often brings.
A – Acts of Self-Care: Self-care practices are crucial for maintaining emotional balance and keeping one’s “cup full.” Encouraging clients to prioritize activities that nurture them helps sustain their mental health.
M - Mindfulness: Engaging in present-focused, nonjudgmental awareness is a powerful tool for managing eco-anxiety. Mindfulness helps ground clients and prevents them from becoming overwhelmed by past traumas or future fears.
This model provides a comprehensive and easy way to remember actionable steps for addressing eco-anxiety. We’ve now covered the symptoms of eco-anxiety, described its prevalence, and explored various potential treatments, including this model, to help guide effective intervention.
Summary
To wrap up, let me summarize the key points we’ve discussed.
Eco-anxiety involves feelings of worry, fear, and helplessness related to climate change and other environmental degradation. It is often accompanied by stress, insomnia, a sense of loss, and other related challenges. While eco-anxiety is not officially included in the DSM, tools are being developed to screen for and better understand it. However, it remains less defined compared to other mental health conditions. Even so, a significant portion of people—anywhere from 40% to 80% of Americans—express some level of concern about environmental issues. Among these, a smaller but meaningful subset may need clinical intervention, though it’s likely more prevalent than we might initially assume.
Eco-anxiety is not limited to the United States; it is a global phenomenon, with higher prevalence among younger generations and communities directly impacted by climate change. Indigenous populations and residents of vulnerable regions often experience greater levels of eco-anxiety. This is linked to three elements of vulnerability: exposure, sensitivity, and adaptive capacity. For example, people living in coastal areas are more exposed to rising sea levels, while certain groups, such as children and older adults, are more biologically sensitive to specific environmental issues like air pollution or extreme heat. Additionally, those with limited social, economic, or political resources often have reduced adaptive capacity, making it harder to cope with environmental challenges. These compounded vulnerabilities contribute to higher levels of eco-anxiety in disenfranchised populations.
Younger generations are particularly affected, having grown up with ongoing messages about climate change and environmental degradation. They also face a significant personal stake in how these issues will unfold over the coming decades, adding to the emotional burden they carry.
Eco-anxiety is still an emerging area of focus, offering clinicians opportunities to conduct further research and develop tailored interventions. While many traditional approaches to anxiety are effective, there are specific strategies that show promise for addressing eco-anxiety. Validation is key, providing compassion and reassurance that these feelings are a normal and natural response to real threats. Brief psychoeducation about the validity of their concerns can also help. Encouraging clients to take meaningful action within their circles of influence can help address feelings of helplessness, while social support reduces isolation and fosters a sense of community. Mindfulness practices can assist clients in staying present and managing anxiety that is often future-oriented. Evidence-based therapies like Acceptance and Commitment Therapy (ACT) and Cognitive Behavioral Therapy (CBT) are particularly helpful, using interventions such as cognitive reframing, behavioral activation, and values-aligned action.
While the exploration of other modalities, such as existential therapy and narrative therapy, is ongoing, many tools designed for anxiety, in general, are effective starting points. Ultimately, addressing eco-anxiety involves a mix of validation, action, support, and mindfulness to help individuals navigate these complex and deeply felt concerns.
Questions and Answers
How do you deal with an apocalyptic stance from young people?
It’s important to think of this as a spectrum. Some individuals might not be concerned at all, and perhaps they should be, as increased awareness could lead to meaningful action. On the other end of the spectrum, some may adopt an overly apocalyptic view that might not align with reality and may require gentle balancing. A certain level of anxiety is valid and expected given the circumstances. Accepting and processing these feelings is essential, followed by coping strategies to help manage and minimize distress. For individuals with unrealistic views, sensitive and balanced cognitive reframing can be helpful in addressing distortions without invalidating their concerns.Why are environmental conditions labeled as injustices?
Environmental conditions are often considered injustices because vulnerable and historically marginalized communities tend to suffer first and worst from these issues. For example, environmental racism is a well-documented phenomenon where communities of color are more likely to have undesirable environmental conditions, such as toxic waste disposal sites, in their neighborhoods compared to affluent communities. Urban heat islands provide another example—lower-income residents living in city centers often experience higher temperatures due to reduced tree cover and increased concrete and emissions, unlike residents in wealthier suburbs. While some environmental problems affect everyone, these justice-related elements disproportionately impact marginalized groups.Can environmental issues be coded as a focus of clinical attention?
Yes. In the DSM-IV, environmental problems were often addressed under Axis IV. While the multiaxial system is no longer part of the DSM-5, there is a section in the back for "Other Conditions That May Be a Focus of Clinical Attention," which includes a code for environmental issues. While not a formal diagnosis, this allows clinicians to note eco-anxiety as a relevant factor in therapy. For billing purposes, some clinicians use codes for unspecified anxiety disorders if eco-anxiety is a prominent issue requiring clinical attention.How should clinicians handle eco-anxiety that ranges in severity?
Eco-anxiety can vary significantly. Some clients may only bring it up occasionally, perhaps after reading a distressing news article, requiring brief validation and coping strategies like behavioral activation or limiting news intake. Others may experience more pervasive and severe eco-anxiety that needs ongoing attention. Tailoring the approach to the individual’s needs is essential.What about Gus Speth’s quote on environmental problems and human attitudes?
Speth’s quote highlights that many of the world's top environmental problems—biodiversity loss, ecosystem collapse, and climate change—are human-caused and rooted in attitudes like selfishness, greed, and apathy. Addressing these issues requires not just scientific and technological solutions but also cultural and spiritual transformation. For those interested in actionable solutions, the book and website Drawdown provide a comprehensive list of top solutions for climate and environmental issues. These solutions are multifaceted, involving science, technology, education, and awareness to address the complexity of the problem.What are the limitations of CBT when addressing eco-anxiety?
While CBT can be very effective, there’s a risk that cognitive reframing might be perceived as invalidating by clients if their concerns are dismissed as "irrational." Eco-anxiety often stems from real and pressing environmental threats, so it’s critical to use clinical judgment to balance reframing with validation. Avoiding judgment ensures the intervention remains compassionate and effective.How can clinicians help clients with perfectionism around their environmental impact?
This is often referred to as "eco-guilt." Clients may struggle with the idea that they can’t completely mitigate their environmental impact, or they may find that some actions are not feasible in their lives. Encouraging clients to explore their values, as suggested in Acceptance and Commitment Therapy, can be a good starting point. Helping them balance their values of sustainability with a reasonable and achievable lifestyle is essential. Acknowledge their efforts, emphasize that they’re doing the best they can, and remind them that individual actions are part of a larger collective effort. Encourage grace and self-compassion, as no single individual can solve the issue alone.Can eco-anxiety show up as an OCD theme or other compulsive disorder?
Yes, eco-anxiety can manifest as an OCD theme. Documented cases include obsessions and compulsions related to environmental impact, such as compulsively checking light switches or faucets to save energy or water. In such cases, traditional OCD interventions remain effective, even if there’s an environmental element involved. Similarly, eco-guilt can sometimes be a factor in hoarding disorder, where individuals feel conflicted about discarding items due to concerns about waste. Talking through the impacts of their choices—whether recycling, donating, or discarding—is a compassionate way to address these concerns.I encourage you to reach out if you have more questions. You can find me on LinkedIn or email me at karenmagruder@uta.edu. Thank you so much for your thoughtful questions and participation, and I hope this session provided useful insights.
References
Please refer to the additional handout.
Citation
Magruder, K. (2024). Eco-anxiety: Symptoms and solutions. Continued.com, Article 85. Available at www.continued.com/psychology
Aug 19, 2024
1 CE CreditThe Effect of ADHD on Adults: Providing Support to Clients and Their Loved Ones
Christina Marsack-Topolewski, LMSW, PhD, MSW
Editor's Note: This text-based course is an edited transcript of the webinar, The Effect of ADHD on Adults: Providing Support to Clients and Their Loved Ones, presented by Christina Marsack-Topolewski, PhD, MSW, LMSW.
Learning Outcomes
After this course, participants will be able to:
- Identify the characteristics, signs, and symptoms of ADHD in adulthood.
- Describe the multi-faceted nature of ADHD and co-occurring conditions common among adults with ADHD.
- Identify and apply practical and evidence-based strategies to support adult clients with ADHD and their loved ones.
Welcome/Today's Focus
Hello everyone! Today, we will discuss adults with ADHD and how we can best support them and their loved ones. This is often a significant factor in why they seek our help, as it’s not uncommon for a loved one, spouse, or family member to encourage them to explore what’s going on.
In my career, I’ve worked as both a special education teacher consultant and a clinical outpatient therapist. I’ve supported individuals across different stages of life, from children in K-12 settings who receive an early ADHD diagnosis and benefit from IEPs or 504 plans to adults who come in later seeking an evaluation or a formal diagnosis. For many adults, ADHD has created a ripple effect through various facets of their lives—impacting their work, relationships, and home life. Often, these individuals may not realize how significantly ADHD has been affecting them until something brings it to light, whether it’s a challenge at work, tension in a relationship, or feedback from someone close to them.
As a society, we often associate ADHD with children and adolescents, but millions of adults in the United States—and many more globally—live with ADHD. The truth is that ADHD doesn’t simply dissipate in adulthood. Many adults were either misdiagnosed or not diagnosed at all during childhood and adolescence. They may have developed their coping mechanisms to navigate school and other early life challenges, though often not without significant difficulty. When these individuals reach adulthood, they may encounter professionals—whether therapists, coaches, or evaluators—who help them identify and address what’s been underlying their experiences.
Today, we’re focusing specifically on adulthood and what we can do to support adults with ADHD. ADHD affects many areas of life, such as employment, family dynamics, and relationships, and without the right supports and tailored strategies, these areas can suffer. Our discussion will cover how ADHD presents differently in adults, how stress plays a pivotal role in its manifestation, and the complexities of the condition’s multifaceted nature. We’ll also look at evidence-based strategies and practical approaches to support adult clients and their loved ones.
It’s essential to recognize that ADHD in adulthood doesn’t exist in isolation. It impacts the individual, their relationships, and their broader environment. The ripple effects can be profound, whether it’s a couple navigating challenges, a family dealing with competing needs, or an individual striving to manage their work life. I’m excited to delve into this topic and explore ways we can help adults with ADHD find success and balance in their lives. Let’s get started.
Risks & Limitations
Regarding limitations, I want to acknowledge that this is a one-hour training, and while ADHD is a topic we could easily spend an entire day exploring, we need to remain mindful of the scope of our time together. Additionally, as clinicians, we must be aware of the limitations and boundaries within our scope of practice. Supporting clients with ADHD often benefits from a team-based approach, which might include collaboration with other practitioners, medical providers, or holistic supports. Taking this interdisciplinary perspective can be incredibly valuable for clients, allowing them to access a range of resources and perspectives that complement one another.
It’s also important to recognize that ADHD often doesn’t occur in isolation. Many clients with ADHD present with comorbid conditions, such as anxiety, depression, or learning disabilities. This has certainly been my experience, and I imagine it aligns with what many of you have seen in your own work. These co-occurring challenges can compound the effects of ADHD, so it’s critical to approach treatment holistically. Addressing the strengths, challenges, and unique needs of each client requires us to integrate evidence-based interventions that are both comprehensive and individualized.
Another consideration is the role of cultural beliefs and attitudes toward mental health conditions like ADHD. These perspectives can vary widely depending on the communities and populations we serve. Much of my consulting work has been in a highly diverse area of Michigan, where I frequently work with families to increase their understanding of ADHD and its impact. Part of this work involves reducing stigma, not just around ADHD, but also the co-occurring conditions that are often seen alongside it. Many of these conditions carry additional stigmatization, which can create barriers to accessing care or support.
As clinicians, it’s vital that we practice cultural humility and promote cultural diversity and awareness in our work. Addressing stigma requires intentionality, whether it’s through psychoeducation, fostering understanding, or creating safe spaces for clients and families to discuss these challenges. By doing so, we help create opportunities for clients to access the care they need while feeling understood and supported. These efforts are essential in ensuring that our interventions are not only effective but also culturally responsive and inclusive.
What Comes to Mind When You Think of Adults with ADHD?
When I think about adults with ADHD, a lot of themes come to mind. Disorganization is one of the key challenges, as well as difficulties with focus and memory. Many adults I’ve worked with describe a sense of being paralyzed in their lives—not knowing where to start, struggling with executive functioning skills like planning and organizing, and feeling like they’re unable to move forward. This sense of being stuck often leads to feelings of shame, guilt, and grief, especially when reflecting on how these struggles have impacted their lives over time.
Employment is often a significant pain point. Many clients come to me because ADHD has started to severely interfere with their ability to hold down a job or perform effectively at work. They may find themselves prematurely quitting or facing difficulties meeting the demands of their roles. Similarly, challenges with time management play a major role. Managing deadlines, coordinating household tasks, paying bills, and fulfilling parenting responsibilities all require a level of organization and planning that can feel overwhelming for adults with ADHD.
Another recurring theme is the challenge of motivation and task-switching. Clients often describe bouncing between tasks, becoming distracted, and struggling to follow through. The constant availability of technology can exacerbate this, with many clients recounting stories of picking up their phone for a specific reason only to find themselves derailed by social media or other distractions. These moments can create a frustrating cycle, heightening anxiety and self-criticism.
Impulse control is another topic that frequently arises in conversations. Impulsive decisions, especially related to finances, can have a ripple effect, particularly in relationships. For example, a partner may feel frustrated by unplanned purchases or difficulty sticking to a budget. In a work setting, impulsivity might mean missing out on promotions or opportunities due to impulsive actions or decisions. This can take a toll on self-esteem and contribute to the already complex emotional landscape of living with ADHD.
What stands out most is the cumulative effect of these challenges. Adults with ADHD are often navigating multiple layers of frustration, both internal and external. This makes it especially important to build strategies that are tailored to the individual. Effective supports need to be personalized, addressing not just the practical skills needed to manage daily life but also the emotional impacts like shame, self-esteem struggles, and relationship dynamics. By stepping back and recognizing the unique needs of each person, we can start to develop strategies that truly help them thrive.
Section #1: Characteristics, Signs, and Symptoms of ADHD in Adulthood
Let's first discuss the characteristics, signs, and symptoms of ADHD.
Aspects to Consider
Adults navigating life with ADHD often find their experiences uniquely challenging. Some may have made it through school or early life without significant struggles or noticeable issues, particularly if they didn’t exhibit the more overt behavioral manifestations commonly associated with ADHD. These individuals may have "flown under the radar," avoiding early diagnosis or intervention. However, the challenges can become overwhelming as they reach adulthood and face the complexities of managing multiple schedules, calendars, and competing demands. This is often compounded by the frustrations that arise within familial or relational contexts, where the ripple effects of ADHD may be felt acutely.
The adverse outcomes of unmanaged ADHD can manifest in various aspects of life. Employment difficulties, financial instability, strained relationships, and internal emotional struggles are common. Many adults with ADHD grapple with feelings of shame, embarrassment, or inadequacy when they perceive themselves as unable to meet their expectations or those of others. This internalized frustration can further erode self-esteem and exacerbate feelings of being stuck or unproductive.
Co-occurring conditions often complicate the picture. Anxiety and depression are frequent companions of ADHD in adulthood, particularly when the condition has gone unmanaged or unrecognized. These individuals may also feel regret or loss as they reflect on milestones or opportunities they missed due to their struggles. This can lead to a profound dissatisfaction with their trajectory and challenges in envisioning a way forward.
In my work with adults with ADHD, I’ve often observed how these challenges extend into their family dynamics, adding layers of tension and difficulty. Relationships can become strained as partners, parents, or children navigate the impacts of ADHD together. The frustration of unmet expectations, both personal and shared, can be palpable.
What’s critical is identifying ways to support these individuals and their families so that they can build healthier, more functional dynamics. The goal is to equip adults with ADHD with the tools and strategies to thrive while fostering understanding and collaboration within their relationships. In doing so, we can help create pathways for success and harmony, even amidst the unique challenges ADHD presents.
ADHD in Children
Adults with ADHD often find themselves grappling with challenges that can be traced back to their childhood experiences. Some individuals may have gone through school and other areas of their lives without significant behavioral manifestations, allowing them to avoid detection or diagnosis. These individuals might have only recognized their ADHD in adulthood when faced with more complex and demanding responsibilities, such as managing multiple calendars, work expectations, parenting duties, or relationship dynamics. Others may have known about their diagnosis from an early age but find that their existing strategies no longer suffice as their life circumstances and expectations evolve.
When considering ADHD in children, executive functioning delays are a significant factor. Samantha Woods, the founder of Kaizen Education Services, highlights that children with ADHD may experience a delay in executive functioning skill acquisition of up to 30% of their chronological age. This delay doesn’t vanish in adulthood—many individuals reach adulthood already behind in developing these critical skills, which can exacerbate their challenges in managing their lives.
Per the DSM-5 criteria for individuals aged 17 and older, ADHD presents with symptoms of frequent inattention, which can align with common issues like focus and organization. For a diagnosis, these symptoms must persist for at least six months in inappropriate ways for the individual’s developmental stage. Examples include careless mistakes, lack of close attention to detail, and difficulty sustaining attention on tasks. These behaviors can lead to frustration, reduced self-efficacy, and, in some cases, significant self-criticism.
Another hallmark of adult ADHD is the perception that the individual doesn’t listen when addressed directly. This might manifest as apparent daydreaming, distraction, or fidgeting during conversations, which can be frustrating for both the individual and those around them. In relationships, such behaviors often lead to complaints from partners about inattentiveness or forgetfulness. For instance, in couples counseling, I worked with a wife who described her husband’s daily forgetfulness, difficulty organizing tasks, and frequent distractions. These behaviors made her feel like she had to take on the role of “conductor” in their household, which included managing children, work, and home responsibilities. She also highlighted procrastination, noting her husband’s repeated delays in completing tasks over several years, which led to further marital tension.
Hyperactivity and impulsivity are also key components of ADHD and can persist into adulthood. While children might be unable to play quietly, adults often express these traits differently. This may include talking excessively, blurting out responses, interrupting others during conversations, or struggling to wait their turn. Some adults with ADHD have shared that others perceive them as interrupting or intruding, especially in group or conversational settings.
ADHD “grows up,” and as it does, the manifestations of hyperactivity, impulsivity, and inattention adapt to the complexities of adult life. These challenges can strain relationships, hinder productivity, and impact self-esteem. Recognizing and addressing these behaviors is critical to supporting adults with ADHD in managing their symptoms and improving their quality of life. Through tailored strategies, awareness, and support, adults with ADHD and their loved ones can navigate these challenges more effectively.
ADHD in Adults
For adults with ADHD, it’s important to recognize that this is a developmental disability. While it may not always be diagnosed in childhood or may even go undiagnosed entirely, the criteria for ADHD require symptoms to have been present before the age of twelve. This developmental origin is key, even if the diagnosis or recognition doesn’t occur until much later. Most individuals with ADHD experience a combination of inattentive and hyperactive-impulsive symptoms that affect multiple areas of their lives.
One hallmark of ADHD is that its symptoms manifest across various settings and contexts. These symptoms are not confined to just one environment, such as school or home, and individuals cannot simply “turn it on or off.” In some of my school-based work, I’ve observed children who manage to hold everything together during the school day, masking their ADHD symptoms to meet expectations. However, once they get home, the effort required to maintain that level of control can lead to emotional exhaustion, resulting in a release or unraveling. In adulthood, ADHD continues to impact different aspects of life, including social, professional, and personal settings, creating challenges that span these environments.
A key diagnostic feature of ADHD is that symptoms interfere with or reduce the quality of a person’s social, academic, or occupational activities. This can sometimes create a conundrum, particularly for individuals in the “twice-exceptional” (2e) population. Twice-exceptional individuals are those who possess very high intellectual capabilities while also living with a disability, such as ADHD. I’ve worked with many adolescents and adults in this group, and I find it fascinating to see how they navigate life. These individuals with IQs typically in the gifted range—often 130 or higher—face unique challenges because of their dual exceptionalities.
For 2e individuals, ADHD symptoms don’t disappear despite their intellectual abilities. Often, their intelligence allows them to compensate or “get by,” particularly in academic settings, where they may not struggle with the material but instead find school boring or unengaging. Their cognitive strengths can mask the challenges posed by ADHD, making it harder to identify and address their needs. This masking does not mean ADHD impacts them any less; it simply plays out differently because of their exceptional capabilities. Working with this population often involves meaningful conversations about how they view the world and navigate their unique experiences.
It’s also critical when working with adults with ADHD to ensure another mental disorder does not better account for their symptoms. This delineation is essential for accurate diagnosis and effective intervention. Co-occurring conditions, such as anxiety and depression, are common among adults with ADHD, but it’s vital to assess whether these are secondary to ADHD or independent issues requiring separate attention.
Ultimately, ADHD in adults remains a pervasive influence across multiple domains of life. Whether we’re working with individuals in the twice-exceptional population or anyone else impacted by ADHD, recognizing its developmental roots and multifaceted presentation is essential for providing the tailored support they need.
Executive Functioning
As I mentioned earlier, executive functioning is a key concept when working with individuals with ADHD, and it often plays a central role in their challenges. I like to think of executive functioning as the orchestra of the mind. It’s the cognitive system that allows us to plan, reason, organize, navigate social situations, and problem-solve effectively.
From a neurological perspective, the parts of the brain responsible for executive functioning—primarily the prefrontal cortex—are the last to develop. For typically developing individuals, this brain area doesn’t fully mature until the early twenties. In neurotypical males, this development often occurs slightly later than in females. Ideally, once this part of the brain fully functions, people can make better decisions, plan and organize more effectively, and navigate life’s challenges more easily.
For individuals with ADHD, however, executive functioning is often impaired, which leads to significant challenges. These difficulties are not limited to ADHD—they are also common in other conditions, such as autism spectrum disorder, where executive functioning deficits are prevalent. Impairments in executive functioning can manifest as trouble organizing tasks, maintaining focus, managing time, or navigating complex social and professional situations.
From a clinical standpoint, addressing executive functioning deficits is a crucial part of working with adults with ADHD. These deficits often fragment their ability to manage daily life, and our strategies must be tailored to meet these needs. For instance, interventions might focus on helping clients develop practical tools for planning and organization, strategies for improving decision-making, or techniques for navigating interpersonal dynamics more effectively.
For adults with ADHD, executive functioning challenges can impact every aspect of their lives. Understanding and targeting these deficits with individualized, aligned strategies can make a profound difference in helping them lead more organized, balanced, and successful lives. This work requires a combination of practical tools, empathy, and an awareness of the neurological realities that underlie these challenges.
Propensity of ADHD
Let’s take a moment to discuss the prevalence and presentation of ADHD in adults. Approximately 2.5% of adults are diagnosed with ADHD, though this figure can vary slightly depending on the source. More recent peer-reviewed articles suggest that the prevalence may range from 2% to 4% of the population. These numbers give us a baseline but highlight the importance of continuing research to understand better how ADHD presents across different demographics and contexts.
When it comes to risky and impulsive behaviors, research has found similarities between men and women with ADHD. However, some key differences in presentation are noteworthy. For example, a 2016 article by Dr. Cortes and colleagues observed that women with persistent ADHD were less likely to exhibit hyperactive symptoms or engage in behaviors like reckless driving compared to their male counterparts. Instead, these women were more prone to experiencing anxiety. This finding serves as a clinical red flag, emphasizing the need to assess for co-occurring conditions like anxiety and depression when working with adults—especially women—with ADHD. These overlapping conditions often complicate the diagnostic picture and can influence treatment strategies.
This insight into prevalence and gender differences sets the stage for the next part of our discussion, where we’ll delve further into how ADHD interacts with co-occurring conditions and what that means for clinical practice.
Section #2: Multi-faceted Nature of ADHD and Co-occurring Conditions Among Adults With ADHD
Today, we're going to talk about that multifaceted nature and some of the co-occurring conditions that are likely or more likely to be at play for individuals with ADHD.
Many Domains of Life Impacted
When we begin to think about the domains of life affected by ADHD, several key areas come to mind—though there are certainly more. Work is a recurring challenge for many adults with ADHD. It’s a domain where the symptoms of inattention, disorganization, or impulsivity often collide with the structured demands of employment, leading to frustrations, missed opportunities, or job instability.
Intimate relationships also frequently surface as a significant area of difficulty. Many individuals I work with express that ADHD contributes to tension and dissatisfaction in marital or romantic partnerships. The dynamics of these relationships can become strained when ADHD-related behaviors, such as forgetfulness or impulsivity, interfere with communication, trust, or shared responsibilities.
Sleep quality is another area that is profoundly impacted. Poor sleep isn’t just unpleasant; it amplifies the challenges of ADHD by exacerbating issues with executive functioning, focus, and emotional regulation. When you’re already navigating the difficulties of ADHD, adding sleep deprivation to the mix can make daily life feel nearly impossible.
Friendships can also suffer. Maintaining social connections requires planning, follow-through, and emotional presence—skills that can be inconsistent for those with ADHD. Parenting is yet another domain that often becomes a source of stress. ADHD-related struggles with organization, planning, and consistency can lead to challenges in following through with routines, managing household dynamics, or effectively meeting children’s needs.
Finances are another significant and frequently mentioned area of difficulty. This is especially relevant given the current economic landscape, where financial pressures are heightened. For adults with ADHD, managing finances can be an ongoing source of stress and tension, both within themselves and in the context of their families. Impulsive shopping, online purchases, and difficulty keeping track of budgets can result in significant financial strain. These behaviors can create guilt and frustration for the individual and strain familial relationships due to shared financial responsibilities.
These interconnected domains illustrate the breadth of ADHD’s impact on an individual’s life. Each area influences the others, often creating a compounding effect. Addressing these challenges requires a comprehensive approach that focuses on practical strategies and considers the emotional and relational toll ADHD takes.
Example #1
I want to share a couple of examples to illustrate the challenges adults with undiagnosed ADHD can face. As I mentioned earlier, many individuals go into adulthood without a diagnosis, often because they managed to get through school without drawing significant attention to themselves. However, as the demands of adult life increase, ADHD symptoms can become more apparent, leading to struggles in various areas.
One case involved an adult male who sought counseling at the urging of his friends and family. He was experiencing significant marital challenges and difficulties maintaining steady employment. From his perspective, he was working very hard, but his inability to consistently hold down a job created strain at home. At this point, he had no formal diagnosis of ADHD.
Another example involved a young father, also undiagnosed, whose ADHD was causing tension in his marriage. This couple had a few children, and his impulsivity and financial instability increasingly burdened the wife. For instance, he would occasionally secure a job but then lose it due to impulsive decisions. In one instance, he worked at a store and decided to close early on a quiet night because no customers were coming, despite store policy requiring him to stay until the scheduled closing time. His employer reprimanded him, explaining that the hours were non-negotiable. Yet, on another night, he repeated the behavior—again closing early to join friends or because he didn’t see the point in staying. After several similar incidents, he lost his job.
This pattern left the family in a precarious financial position. The wife, frustrated and overwhelmed, found herself in a caregiver role—managing the household and their children and often stepping in to compensate for her husband’s behaviors. This dynamic created significant marital tension because of the financial stress, and the wife felt she was parenting her spouse rather than partnering with him. This imbalance understandably impacted their intimacy and the overall health of their relationship.
In counseling, the focus was on helping the couple establish clear boundaries and shared accountability. Strategies were developed for the husband to manage his impulsivity better and adhere to work expectations. Equally important was addressing the marital dynamic to ensure the wife was no longer in a caregiver role. The goal was to help them rebuild their relationship as equals, fostering a healthier and more supportive partnership.
These examples highlight how untreated or undiagnosed ADHD can ripple through different aspects of life, affecting not just the individual but also their loved ones. They underscore the importance of identifying strategies that support both the person with ADHD and their relationships, helping them create more balanced and functional dynamics.
How Does ADHD Impact Marriage and Relationships?
Adults with ADHD are more likely to experience increased relationship distress. Based on clinical examples and anecdotal reports, it’s no surprise that the symptoms of ADHD can lead to heightened tension and challenges in navigating the functionality of daily life. These challenges often stem from core ADHD symptoms like inattention, impulsivity, and emotional dysregulation, which can make communication and connection more difficult for couples.
There is also evidence suggesting that adults with ADHD may experience higher rates of breakups, promiscuity, and repeated marriages. Impulsivity and emotional dysregulation, in particular, can contribute to instability in relationships, leading to patterns of risky behaviors or difficulties maintaining long-term commitments. These behaviors can further strain relationships, creating cycles of misunderstanding and conflict.
A recent study by Dr. French and colleagues in 2024 indicated that adults with ADHD are more likely to have been divorced. This aligns with research showing that ADHD symptoms often create significant relational stress, particularly when left unaddressed. Issues such as inconsistent communication, challenges in emotional regulation, and difficulties in managing daily responsibilities can erode relationship satisfaction and contribute to separation or divorce.
Dynamics in Couples
When considering the dynamics in couples where one partner has ADHD, it’s important to examine the internal narratives and feelings that may arise, particularly for the non-ADHD partner. Many individuals I’ve worked with, whether in individual therapy or couples counseling, describe the significant frustrations expressed by their non-ADHD partner. These frustrations often stem from feeling like they carry the weight of responsibilities within the relationship. For example, they might feel responsible for coordinating household tasks, managing childcare, and ensuring everything runs smoothly. This sense of imbalance can lead to resentment, especially when there’s uncertainty about whether the ADHD partner will be able to maintain consistent employment or follow through on commitments.
From the ADHD partner’s perspective, they may struggle with guilt or a sense of inadequacy when faced with their partner’s frustration. This dynamic can create a cycle of tension within the relationship, where one partner feels overwhelmed by their perceived burden and the other feels criticized or misunderstood. These feelings and behaviors often become a central focus in therapy, as they can significantly affect the overall health of the relationship.
Medication is a topic that frequently comes up in these discussions. While many individuals with ADHD report benefits from medication, others express dissatisfaction due to side effects, the way it makes them feel, or its duration of effectiveness throughout the day. For parents with ADHD, this can be particularly challenging, as the demands of parenting often extend well beyond the medication’s effective window. Balancing these challenges while managing the daily demands of parenting and household responsibilities can feel overwhelming for both partners.
Clinically, I’ve often worked with individuals receiving weekly therapy who also consult with a PCP or psychiatrist for medication management. This team-based approach can be particularly helpful, as ADHD often requires a multifaceted support system. When medication is part of the treatment plan, it can be critical to ensure that it aligns with the individual’s daily needs and responsibilities—such as parenting long hours.
For many parents, whether or not ADHD is part of the picture, balancing the competing demands of work, family, and personal responsibilities is already a significant challenge. When ADHD is added to the mix, these challenges can intensify, requiring thoughtful strategies, collaborative efforts, and a strong support network to navigate effectively.
Parenting With ADHD
Parenting, managing children, maintaining a household, and balancing paid work outside the home are challenges that can feel overwhelming for anyone, but these demands are significantly amplified for individuals with ADHD. Many new moms or parents have said, “I just can’t keep up.” This feeling of falling behind, even in the absence of ADHD, is already a significant stressor. When you add ADHD into the mix, especially alongside potential co-occurring conditions, these challenges become even more pronounced.
For individuals with ADHD, difficulties with organization, time management, and memory can make it harder to juggle the various responsibilities of parenting and household management. Tasks that might feel manageable to others can quickly become overwhelming. This can lead to feelings of frustration, guilt, or even anger. For instance, forgetting to sign a child’s permission slip, missing an appointment, or struggling to keep up with basic household chores can create a cumulative sense of failure, even if the person is doing their best.
Frustration often becomes a common thread. Parents with ADHD might feel this frustration not only toward the tasks at hand but also toward themselves for struggling in areas where they wish they could excel. This emotional toll can spill over into relationships and family dynamics, creating a cycle of stress that affects everyone in the household. Understanding and addressing these layers is critical in supporting parents with ADHD as they navigate their unique challenges.
Tips for Moms With ADHD
Some helpful tips for moms—and certainly these can apply to fathers or caregivers—start with creating routines. Routines can be beneficial for most people, providing structure and predictability. For individuals with ADHD, they are particularly valuable in reducing overwhelm and ensuring that essential tasks are completed consistently. Establishing a routine helps set clear expectations, making it easier to navigate daily responsibilities.
Another critical aspect is focusing on problem-solving, often from a solution-focused clinical perspective. Rather than dwelling on what’s gone wrong, the goal is to identify what can be addressed or tackled in the moment. This approach encourages forward movement and reduces the tendency to linger on frustrations or mistakes. Importantly, it’s about avoiding blame, which is rarely productive and often counterproductive, especially for individuals with ADHD. Shifting the conversation to solutions can empower individuals to feel more in control and capable of managing their challenges.
I often encourage starting with smaller, more manageable problems in clinical work. Focusing on issues that can be resolved relatively easily helps build momentum and confidence. Feeling effective—whether as a therapist, a parent, or an individual seeking help—can be incredibly motivating. For clients, tackling even small challenges can create a sense of accomplishment and reinforce their ability to progress.
Equally important is fostering acceptance and self-compassion. For those with ADHD, accepting the reality of living with the condition can be a powerful step toward reducing self-criticism and blame. Self-compassion becomes an essential tool, allowing individuals to navigate their challenges with grace rather than frustration.
This message of self-compassion applies universally. Whether or not someone has ADHD, all parents—especially moms—can benefit from acknowledging the demands of their role and being kind to themselves when things don’t go as planned. Encouraging this mindset can help reduce the pressure of perfection and create space for resilience and growth.
Tips for Dads with ADHD
For dads with ADHD, symptom management skills are essential to fostering stability in their lives and relationships. A primary focus often involves identifying strategies to manage ADHD symptoms effectively, emphasizing approaches that can enhance marriage or partnership stability. One foundational strategy is utilizing structured calendars and routines, which can help mitigate the disorganization and forgetfulness often associated with ADHD.
In recent years, I’ve noticed a growing challenge: the proliferation of multiple calendars. Many individuals now juggle phone calendars, work calendars, Google calendars, paper calendars, and more. This abundance of tools, while helpful, can sometimes add to the confusion rather than reduce it. A simple yet impactful step is ensuring these calendars are synced and coordinated. Consolidating and streamlining scheduling systems can significantly improve organization and communication, especially within a household.
For instance, a shared digital calendar that partners and family members can access allows everyone to stay on the same page about appointments, events, and responsibilities. This coordination not only reduces the likelihood of missed commitments but also minimizes the stress and miscommunication that can strain relationships.
By focusing on symptom management through these practical strategies, dads with ADHD can better navigate their roles at home and work, fostering stronger partnerships and more cohesive family dynamics. These tools may seem basic, but their consistent use can improve daily functioning and relational stability.
Special Considerations for Parents with ADHD Parenting Kids with ADHD
Managing time and staying organized can be particularly challenging for individuals with ADHD. In my experience, working with people to set reminders, use timers, and build in buffers for underestimated time has been incredibly helpful. Time management is often a significant hurdle for this population, and underestimating how long tasks or commutes will take can lead to late or missing commitments altogether, which can cause a cascade of frustrations and complications.
I’ve worked extensively with parents who have ADHD and are also parenting children or adolescents with ADHD. This dynamic can be especially challenging. It’s a situation where both the parent and child are navigating similar struggles with organization, executive functioning, and time management. Supporting the parent is critical—not just to help them better manage their responsibilities but also to empower them to model and coach their child in developing their own executive functioning skills. For children and adolescents, this might include teaching time estimation, breaking tasks into smaller steps, and creating visual supports, which can also benefit the parent.
Visual supports can be powerful tools for improving organization in both parents and children. These might include visual schedules, chore charts, or color-coded systems that help everyone in the household stay on track. Referrals to external resources or support programs can also provide additional structure and coaching, reinforcing these skills sustainably for the family.
Household management and delegation can be tough for any parent, but for those with ADHD, it becomes even more complex. Questions like "Who does what?" and "When should it be done?" can quickly overwhelm if there isn’t a clear system in place. Developing structured routines for household tasks—whether it’s a rotating schedule for chores, shared digital lists, or designated responsibilities—can help reduce confusion and create more stability. These approaches ensure that the burden doesn’t fall disproportionately on one parent and promote collaboration within the family, easing stress and improving functionality.
Impact on Work Roles and Responsibilities
A newly published article from 2022 highlights an important reality: adults with ADHD are less likely to be employed. This is a significant issue, as employment provides not only financial stability but also contributes to self-esteem, daily structure, and a sense of purpose. The challenges that adults with ADHD face in maintaining steady employment often come up in clinical settings, and it’s critical to address them to support overall functionality and well-being.
There are many reasons why employment can be difficult for individuals with ADHD, both from personal observations and supported by peer-reviewed literature. This population tends to experience more frequent job changes, which can lead to increased stress over the trajectory of their careers. Without adequate supports and structures, the workplace can become a particularly challenging environment. Many jobs offer minimal on-the-job training, leaving employees to navigate their responsibilities with little guidance or support. For someone with ADHD, this lack of structure can be overwhelming, amplifying the challenges associated with organization, time management, and task prioritization.
In these situations, clinicians can work with clients to help them develop personal supports and strategies to compensate for workplace gaps. For example, creating a detailed list of responsibilities, setting up reminders and alarms, and organizing their calendar to include meetings and deadlines can be immensely helpful. These are strategies I’ve often used myself in professional settings to stay organized and on track, even without a diagnosis of ADHD. For adults with ADHD, implementing such systems can be life-changing, offering a sense of control and predictability in an otherwise overwhelming environment.
Ideally, these skills would begin developing during childhood or adolescence, but the need often persists into adulthood as the demands and expectations of work and life increase. Employment issues, coupled with challenges in family and professional life, often lead to decreased overall satisfaction. For adults with ADHD, this lack of internal satisfaction can be particularly disheartening, as it often reflects a broader struggle to meet their own and others’ expectations.
Clinicians can help individuals with ADHD navigate these challenges by focusing on strategies that build structure and reinforce confidence. Empowering clients to create systems tailored to their needs improves their employment outcomes and enhances their overall quality of life.
Employment & Education
When considering employment and education, it’s clear that adults with ADHD often experience lower rates in both areas. This is not particularly surprising based on my experience. For many individuals with ADHD, formal education is simply not an area of high interest. I’ve worked with numerous adolescents transitioning into adulthood who have expressed a strong disinterest in continuing formal education despite showing significant aptitudes in various areas.
For these individuals, it’s about finding where they best fit. Many prefer hands-on work, which is a fantastic direction to explore. Hands-on roles can align well with the strengths and preferences of individuals with ADHD, allowing them to engage actively and avoid some of the challenges they might face in more traditional academic or desk-oriented settings.
Supporting these individuals involves helping them identify career paths that capitalize on their strengths and interests, fostering a sense of accomplishment and fulfillment. For those uninterested in formal education, exploring vocational training, apprenticeships, or other experiential learning opportunities can provide meaningful alternatives that lead to success and satisfaction.
Money/Finances
Figuring out where an individual with ADHD can achieve meaningful and sustainable income is critical to supporting their financial and overall well-being. Money and finances, while not always openly discussed, are often areas of significant difficulty for adults with ADHD. In my experience, financial challenges frequently create tension within families and add stress to the lives of individuals with ADHD.
Planning, organizing, and managing finances can be particularly problematic. Adults with ADHD are more likely to miss payments or struggle to keep track of bills due to difficulties with organizational skills. Additionally, they may engage in riskier financial behaviors, making impulsive purchases or decisions that aren’t fully thought through. These habits can result in challenges such as accumulating high credit card balances, further exacerbating stress and stigma.
Providing practical strategies to help manage finances is incredibly valuable. This might include setting up automated bill payments, using budgeting apps that send reminders, or working with a financial coach who understands ADHD-related challenges. Helping individuals create a financial system tailored to their needs and abilities can significantly reduce stress and improve their financial stability.
The stigma surrounding financial struggles can often prevent individuals from seeking help, but it is key to address this openly in a supportive and nonjudgmental way. By normalizing these challenges and focusing on solutions, we can empower adults with ADHD to take control of their finances and, in turn, alleviate some of the associated familial and personal tensions.
Example #2
Another example, which echoes some of the dynamics I’ve shared previously, is the high propensity for frustration within couples where one partner has ADHD. A common theme is one partner feeling as though they’re parenting the other, taking on most responsibilities, and feeling burdened by the imbalance. This sense of inequity can lead to significant tension and dissatisfaction in the relationship.
One specific issue that frequently arises is high screen time. Often, one partner in the relationship might spend a significant amount of time on their phone, tablet, or computer, which can be especially frustrating for the other partner. This frustration is magnified when the non-ADHD partner already feels like they are compensating for a lack of follow-through or organization from their ADHD partner. This dynamic not only exacerbates feelings of inequity but can also create emotional distance and resentment in the relationship.
Co-occurring Conditions
Adding to these challenges are co-occurring conditions that frequently accompany ADHD. These can include anxiety, depression, or other mood disorders, which further complicate the relational and functional dynamics. Addressing these layered issues requires an understanding of the interplay between ADHD symptoms and any co-occurring conditions, along with strategies to improve communication, shared responsibility, and emotional connection within the relationship.
I want to highlight that anxiety is one of the most prevalent co-occurring conditions we see alongside ADHD, as well as autism spectrum disorder (ASD). This aligns with my clinical experience, and I’ve also covered this extensively in webinars focused on autism. ASD, in particular, often presents with a range of co-occurring conditions, with ADHD being one of the most common. However, individuals with ASD frequently experience other challenges, including depression, bipolar disorder, and even substance use disorders. These layered complexities require a nuanced and comprehensive approach to treatment.
A recently published 2023 study using extensive data sets underscores the significant risks associated with these co-occurring conditions. This analysis compared 14.6 million people without ADHD to over half a million individuals with ADHD. The findings revealed that adults with ADHD were five times more likely to have comorbid anxiety disorders and four and a half times more likely to have major depressive disorder. These statistics are a stark reminder of how frequently other significant mental health challenges accompany ADHD.
Clinically, this means we must address not only the core symptoms of ADHD but also the emotional regulation challenges, learning disabilities, and other explosive or reactive behaviors that can accompany these co-occurring conditions. Interventions must be multifaceted, targeting both the ADHD symptoms and the broader mental health needs of the individual to improve their overall functioning and quality of life. Understanding these risks allows us to develop more targeted and effective strategies, focusing on emotional and behavioral regulation.
Section #3: Practical and Evidence-based Strategies For Adult Clients With ADHD and Their Loved Ones
Now, let's talk about what we can do.
Patient/Family Support
One big piece that has proven incredibly effective in the families I’ve worked with is patient and family support. Families need to understand what ADHD is and how it manifests so they can better navigate the challenges it presents. This is especially important in situations where an adult comes into a clinic for an evaluation, often not knowing they have ADHD. They may have managed through their thirties or forties without a diagnosis, but their loved ones often sense something is wrong—they don’t know what it is.
This dynamic can be incredibly confusing and frustrating for families. They may see behaviors or patterns that don’t make sense to them, like an office filled with clutter—everything is there, but there’s no discernible organization. I often hear analogies from clients that resonate with this experience. One of my favorites is comparing it to a car trunk packed with thousands of items, all jumbled together without any clear system. The capacity is there, but the organization is missing.
For individuals with ADHD, this lack of structure can create a chaotic environment, both physically and mentally. And for their loved ones, witnessing this can be equally overwhelming. For example, walking into an office where papers are scattered everywhere, items are piled haphazardly, and no clear order can evoke anxiety. It’s common to hear stories about forgotten lunches unearthed weeks later amid the clutter.
Anything we can do to help support organizational strategies and create systems that bring order to this chaos can make a tremendous difference. Helping individuals with ADHD and their families better understand and address these dynamics not only reduces tension but also fosters greater empathy and collaboration within the household. It’s about finding ways to take the overwhelming and make it manageable, one bucket or trunk at a time.
Care Techniques
Care techniques for adults with ADHD often begin with building awareness. People need to understand what ADHD is, how it manifests, and how it impacts various aspects of life. This awareness extends to individuals with ADHD as well as their families, friends, and employers. Exploring treatment options with primary care providers or psychiatrists can be beneficial, particularly when it comes to considering medications, which can often help manage core symptoms. Additionally, cognitive-behavioral therapy (CBT), relaxation training, stress management techniques, and couples or family therapy can all play crucial roles in comprehensive care.
From my experience, couples therapy has been particularly helpful for many of the couples I’ve worked with. It provides a space to develop strategies for moving forward together, addressing specific challenges, and fostering a better understanding of each partner’s needs. Similarly, from a professional standpoint, job mentoring programs or workplace supports can make a significant difference. While some jobs allow individuals to "hit the ground running," adults with ADHD often benefit greatly from additional structures and supports. These can reduce stress, ease onboarding, and enhance job performance and satisfaction.
Sleep hygiene is another area that often requires attention. Many individuals with ADHD struggle with maintaining regular sleep schedules, and for some, racing thoughts in the middle of the night can further disrupt rest. Establishing consistent bedtimes and wake-up times and creating a bedtime routine can provide a helpful framework. This can include limits on digital device usage before bed—a "digital detox." While this advice is relevant for the general population, it’s especially important for adults with ADHD, who may be more prone to mindless scrolling that disrupts sleep and reduces productivity.
Exercise is another piece of the puzzle. I often hear resistance to incorporating exercise routines because of busy schedules. Some individuals have excellent routines that they would never compromise, but others feel they don’t have time. For those individuals, redirecting even a small portion of digital device time—perhaps 20 minutes a day—toward physical activity can have significant benefits. Having a clear, visual schedule for exercise can also be motivating, especially when it’s paired with practical steps like organizing workout clothes and equipment in an accessible spot to eliminate delays and excuses.
Finally, laughter and emotional connection can profoundly influence managing ADHD. These elements often carry significant weight, providing relief and improving mood while helping to build resilience against the challenges ADHD presents. Creating a balance of structure, support, and positive experiences is key to helping individuals with ADHD thrive.
Practical Solutions
I have many other practical solutions, but I want to take a moment to focus on the incredible strengths I’ve seen in the adolescents and adults with ADHD that I’ve worked with. These individuals often have unique and remarkable abilities, and I think it’s so important to emphasize how we can strengthen and augment these talents. By focusing on their strengths, we’re not just helping them utilize their abilities more effectively, but we’re also contributing to their overall self-esteem and self-efficacy.
When individuals recognize and capitalize on what they’re good at, it has a ripple effect. They begin to see their value in tangible ways, which can profoundly impact how they view themselves and approach challenges. It’s about helping them build confidence in their ability to navigate life, whether that’s in their relationships, their work, or their daily routines.
At the same time, we can’t overlook the importance of self-care and overall well-being. We often need to create tailored strategies that fit the individual’s lifestyle and preferences, ensuring that these practices feel accessible and achievable. Supporting self-care goes hand in hand with fostering strengths, as both are crucial for helping individuals with ADHD manage their challenges and thrive in their personal and professional lives.
Strategies and Supports
Structure and routine can be incredibly helpful, especially for individuals with ADHD who are managing busy lives or facing multiple demands. The question often becomes, how do we balance expectations, roles, and responsibilities? And equally important, how do we build efficiencies that make life more manageable?
One strategy I find particularly effective is the Pomodoro Technique. It’s a fantastic tool, especially for those resistant to starting a task. The concept is simple: you work for a set amount of time—usually five minutes to start—then take a short break and repeat. When introducing this to clients, I often hear, "Five minutes? I can do that." Once they start, they often find it easier to keep going, building momentum. Over time, as they grow more comfortable, the work intervals can be extended to ten, fifteen, or even twenty minutes. The key is using a timer to keep things structured and manageable. If they reach the goal and still feel productive, they can keep working, taking a break only when needed, then resetting the timer. It’s a flexible, adaptable method, and I’ve seen it work wonders with adolescents, adults, and parents seeking strategies to stay on track.
Basic reminders are another straightforward but effective tool. Let’s be honest—most of us benefit from reminders in our daily lives. Whether it’s an alarm, a phone notification, or a sticky note, these small cues can make a big difference in helping people stay organized and meet their goals.
In educational settings, reasonable accommodations can also be a game changer. Section 504 accommodations in schools and colleges, for example, can provide much-needed support. These might include extended time for tests, quiet spaces for work, or assistance with note-taking. The goal with these accommodations, as with any strategy, is to meet the individual where they are and help them build systems that work for their unique needs. These tools, combined with a focus on routine and structure, can make a profound difference in managing ADHD effectively.
Beliefs and Values
Beliefs and values play a significant role in how ADHD is understood and managed, not just by individuals but by families and society as a whole. One important dynamic to acknowledge is the presence of denial, which can often arise within families. This denial may stem from a variety of factors, including the stigma associated with ADHD or a lack of understanding about the condition. Some family members or societal influences may adopt an "if I can’t see it, it doesn’t exist" mindset, creating significant barriers to recognition and support.
Another contributing factor is the history of overdiagnosis of ADHD in certain contexts. This has led some people to dismiss legitimate concerns or downplay symptoms, perpetuating skepticism about the validity of an ADHD diagnosis. These dynamics can complicate seeking proper evaluation and care, particularly when co-occurring conditions occur. Families may struggle to differentiate between what’s attributable to ADHD and what might be a result of anxiety, depression, or other overlapping challenges.
Understanding and addressing these beliefs is crucial, as they directly impact the willingness of individuals and families to seek and accept help. Recognizing the validity of ADHD and its effects while fostering an open and informed dialogue can help overcome these barriers and create a supportive environment for those affected.
Simplify
Simplify, simplify, simplify. This mantra can be helpful, especially when working with individuals with ADHD. If you’re familiar with Marie Kondo and her approach to organizing spaces—focusing on simplifying and clearing clutter—you’ll understand how transformative it can be. Personally, I enjoy her approach, and I often think about how applicable it is when supporting individuals with ADHD.
The principle of simplifying applies not just to physical spaces but also to routines and systems. When things are simplified, they’re often easier to manage. This is true for everyone, but especially for those with ADHD, where reducing chaos can alleviate overwhelm and promote focus. For example, having an organized closet where clothes are easy to find can take one layer of stress out of the day. It’s not just about neatness; it’s about creating an environment that supports efficiency and reduces decision fatigue.
Whether it’s organizing a workspace, streamlining a daily routine, or even decluttering a mental to-do list, simplicity can be a game-changer. It’s about making life more manageable, one step at a time, and creating systems that allow people to focus on what matters.
Keep in Mind
I just want to note that we can put many supports in place to help manage and alleviate the symptoms of ADHD. This can have a positive impact not only on the individual but also on their family, coworkers, and others in their environment. There is a trickle-down effect.
Resources/Books
I have resources and podcasts available as well (in the handout).
Questions and Answers
I have noticed that my adult ADHD clients are hypersensitive to others' attitudes and behaviors towards them, which causes them to retreat physically and emotionally. Would you say that this is a trait of an adult ADHD person, and how do you develop that change?
Yes, I’ve also seen this, and it’s a great question. I think part of this hypersensitivity can come from the feeling of putting in so much effort and still perceiving or experiencing frustration from others. It’s something many of us can probably relate to in certain contexts, but for individuals with ADHD, this sensitivity may be heightened. Oftentimes, I’ve found that my clients with ADHD, or even students I’ve worked with, may inadvertently send signals to others—such as missing deadlines or underperforming in ways that others notice—that lead to frustration.
Initially, others might not vocalize their irritation, but repeated instances can escalate tensions. This is particularly evident in workplace settings or relationships, where the ADHD individual feels they’re doing their best, but others perceive a lack of effort or reliability. To address this, it’s important to build strategies that highlight their strengths, create systems to support consistency and improve self-awareness.
It’s also worth addressing how to balance the potential benefits of self-disclosure. Not every context requires full disclosure, but in some cases, gently educating colleagues or loved ones about how ADHD impacts behaviors can foster understanding and reduce frustration. This education can be done comfortably and doesn’t overexpose the individual’s challenges.
While hypersensitivity is common, building on strengths, setting clear parameters, and creating strategies to meet expectations better can help mitigate these challenges. Education—for the individual and their social or work circles—can also play a key role in improving dynamics.
I have had clients with an ADHD diagnosis who were also seeing me for substance abuse treatment. They often struggled with time management, disorganization, and bouncing between tasks socially and professionally. Many also became addicted through self-medicating with street drugs. How do you navigate this overlap?
Thank you for sharing this—it’s a very real and complex issue. Clients managing both ADHD and substance abuse face a unique set of challenges, and I appreciate the skills you’re bringing to this work, as it’s such a critical area of need.
One of the most difficult aspects is disentangling the overlapping symptoms of ADHD and substance use. For example, impulsivity, disorganization, and difficulty with self-regulation can be hallmark characteristics of both ADHD and substance use disorders, making it challenging to determine where one ends and the other begins.
With many clients, substance use may initially arise as a way of self-medicating for untreated ADHD symptoms, like restlessness, focus issues, or emotional dysregulation. However, over time, the substances themselves can compound these issues, creating a cycle that’s hard to break.
In treatment, it’s essential to approach both conditions concurrently. This often involves helping the client build sustainable routines, work on time management and organizational skills, and develop healthier coping strategies to address ADHD symptoms without turning to substances. Medication management can also play a pivotal role, especially when overseen by a skilled psychiatrist familiar with both ADHD and addiction.
Your awareness of these complexities and work in this area is valuable. Supporting clients through this dual diagnosis is challenging, but your skills and attention to both conditions can make a tremendous difference. Thank you for bringing this issue into focus.
References
Please refer to the additional handout.
Citation
Marsack-Topolewski, C. (2024). The Effect of ADHD on adults: Providing support to clients and their loved ones. Continued.com, Article 84. Available at www.continued.com/psychology
Jun 21, 2024
1 CE CreditUnpacking, Transforming and Healing Shame: Theory and Practice for Mental Health Practitioners
Shira Sameroff, LCSW, MSW
Editor's Note: This text-based course is an edited transcript of the webinar, Unpacking, Transforming and Healing Shame: Theory and Practice for Mental Health Practitioners, presented by Shira Sameroff, MSW, LCSW.
Learning Outcomes
After this course, participants will be able to:
- Describe the origins and development of shame and the difference between shame and guilt.
- Identify cultural and societal influences on shame and its expression.
- Explain the effect of shame on individual clients and on society as a whole.
Welcome
I'm so glad to be here and to welcome you all to this session. It's wonderful to have you here to explore a topic that I believe is incredibly important.
I know how demanding it can be to carve out time for continuing education amidst everything else we do as practitioners. It can sometimes feel like just one more thing on a long list of responsibilities. But I encourage you to see this as a space that’s for you—to orient yourself to what will make this experience meaningful and beneficial. My goal is to make this as valuable and supportive as possible for you, and I’m here to ensure it’s a positive and enriching experience.
Limitations/Risks
Therapeutic practice around issues of shame is a vast and in-depth field that requires ongoing learning and practice to develop a comprehensive knowledge base and skillset. This training serves as an introduction to some of the key aspects of this work.
Historical traumas and systemic injustices often contribute to collective experiences of shame within certain cultural groups. It is crucial for clinicians to recognize the profound impact of these historical and structural factors on individuals' experiences of shame and their capacity for resilience. To effectively navigate these complexities, clinicians must engage in continuous self-reflection and demonstrate cultural humility, ensuring a thoughtful and informed approach to addressing shame within diverse cultural contexts.
Opening Activity (From the Live Event)
I’d like to start with an opening activity that I often facilitate. I also offer webinars and recorded sessions on group facilitation, which is something I’m deeply passionate about. Whenever I’m with a group, I aim to create a true sense of community, and one way to do that is by inviting you to share and participate. From my perspective, experiential learning is one of the best ways to truly engage with the material. Even in this format, where we can’t see or hear each other directly, there are still ways to foster connection and interaction.
I encourage you to participate by asking questions at any time, sharing your thoughts, or simply reflecting on the prompts I provide. This session is meant to be participatory, and I welcome your contributions. To start, I’d love to hear your name, where you’re joining from, and one word that comes to mind when you think of shame. For example, one participant might say “Minneapolis” and “hiding.” That’s a great word—thank you for sharing.
To share a bit about myself, after living in Brooklyn, New York, for a couple of decades, I now reside in Asheville, North Carolina. One word that comes to my mind when I think about shame is lonely. I’ll expand more on that as we go, but that word encapsulates an important aspect of shame for me.
If you’d like to share where you’re joining from and your word, you’re welcome to do so at any point. Regardless, I’m glad you’re here and look forward to exploring this topic together.
Webinar Agenda
Let me start by going over the webinar agenda. I believe it’s always important to know what to expect—it helps set the stage and gives clarity about what we’ll cover.
First, introductions: I’ve already introduced myself, and you’re welcome to introduce yourself at any time. Next, I’ll outline the guidelines for our group to ensure we create a respectful and engaging space for learning and sharing. We’ll then dive into the theory and practice of effective work, exploring key concepts and applications. Finally, we’ll close by honoring our time together and reflecting on what we’ve covered.
Guidelines For Our Group Today
Let’s take a moment to establish our group guidelines for today. Even in this format, I believe it’s essential to create a space that feels supportive and works well for everyone. My hope is that we all approach this session with open ears and open minds, including myself and our facilitators. I encourage you to show up fully and honestly, to listen, to share, and to ask any questions that come to mind.
All questions are welcome here—there’s no expectation for you to know something before you’ve had the chance to learn it. Shame can often be attached to asking questions, and people sometimes hold back because they feel embarrassed or unsure. I want to clear that away in this space. This is a place where curiosity is valued and where questions, no matter how big or small, are seen as an important part of the learning process.
I will be transparent with you about what I know and what I don’t. While I bring a lot of experience to this work, there are always things I’m still learning, and that will always be true. I won’t pretend to have answers when I don’t. This session is for you, and creating an environment where you feel comfortable and supported is my priority. Once again, welcome—I’m so glad you’re here.
Unpacking Shame
I am deeply passionate about addressing and healing shame because it is such a pervasive and powerful experience. Shame often arises as a result of trauma and hurt, and I believe that every individual deserves the opportunity to heal from it. It has an enormous impact on individual lives and, in many ways, on all of us collectively. Shame is a shared human experience, and I’ll speak more about its collective nature as we move through this session.
In my view, true healing, transformation, and the social change we aspire to create require us to confront and clear the shame that stands in the way. Shame is often at the root of so many struggles, and addressing it allows individuals to live fuller, more connected, and more authentic lives. In my own experience, both personal and professional, shame has been a recurring theme. I honestly can’t recall working with anyone, whether individually or in a group setting, where shame wasn’t present in some way. It’s always there, shaping emotions, thoughts, and actions. That’s why I’m so passionate about this work—it gets to the heart of what holds people back.
Carl Jung once said, “Shame is a soul-eating emotion.” This resonates deeply with me because it so accurately reflects how shame feels and how it manifests in others. It’s a weight that can consume and isolate, and I see this again and again in the individuals I work with.
Brené Brown, who has done extensive work on shame, defines it as “the intensely painful feeling or experience of believing we are flawed and therefore unworthy of acceptance and belonging.” She emphasizes that shame isn’t about making a mistake or doing something wrong—it’s about feeling inherently flawed, as though there’s something deeply and uniquely wrong with who we are at our core. That belief is brutal to carry and, as Brown notes, is a collective experience on some level. It’s this shared yet deeply isolating nature of shame that makes it so vital to address and heal.
I also want to share a perspective from Mario Jacoby, another practitioner who has explored shame. He delves into the origins of the word, which he links to the Indo-Germanic root kam/chem, meaning “to cover.” This etymology aligns with the experience of shame—causing us to hide, to cover ourselves, because we feel there’s something inherently wrong with us. It’s fascinating how even the roots of the word echo the lived experience of shame.
The Difference Between Guilt and Shame
The difference between guilt and shame lies in the focus of each emotion. While guilt centers on a specific action—what I did—shame focuses on the global self—who I am. Guilt arises when we recognize that something we did was wrong or out of alignment. For instance, I might feel guilty for lying to someone or not being honest, and I feel bad about that specific behavior. Guilt allows us to reflect on our actions, recognize harm, and potentially make amends. It can be a catalyst for growth and change.
Shame, on the other hand, is far more pervasive and damaging. It’s the belief that I am inherently bad, that there is something fundamentally wrong with me as a person. It’s not tied to a single action but rather to a global, internalized sense of unworthiness. This makes shame much harder to resolve because it’s not about correcting an action—it’s about feeling irredeemable as a human being. That’s why shame is so destructive and why it’s critical to address and heal it.
It’s also worth noting that guilt isn’t always tied to something we’ve actually done. Sometimes guilt is inherited or internalized, stemming from societal or familial messages that have been passed down. We may feel guilty about something that isn’t truly wrong but has been framed as such by external forces. In these cases, we need to discern whether the guilt is valid or misplaced.
The key difference is that guilt, when appropriate, can lead to resolution, learning, and accountability. Shame, however, traps us in the belief that our very essence is flawed, which prevents growth and healing. This distinction highlights why it’s so important to clear shame—it stands in the way of living a whole and authentic life.
Origins of Shame
The origins of shame are deeply rooted in generational patterns and early life experiences. Unhealed, unprocessed shame often gets passed down from generation to generation. Each person experiences it differently, but we all come into a world steeped in it, absorbing its messages and emotions. Our parents, grandparents, great-grandparents, and the generations before them lived through difficult experiences, often without the opportunity to heal. As a result, their unhealed wounds and the associated shame become a legacy that is passed down, often unintentionally.
As children, we are open and highly impressionable, absorbing the world around us without the capacity to critically analyze or process the emotions and dynamics we encounter. Much of the shame we carry isn’t even our own—it’s inherited from those who came before us. Caregivers and parents rarely intend to pass on their shame, but as young children, we internalize it nonetheless, interpreting our environment without the guidance or context needed to understand that certain emotions or reactions aren’t ours to bear.
Shame itself, though not useful, serves a protective function. It warns us to hide, as if doing so could prevent harm or rejection. This instinct has roots in early human history, tied to survival mechanisms like avoiding ostracism or danger. That’s why shame feels so intense and overwhelming—it taps into primal fears that go back to our earliest ancestors. It’s an automatic, protective response designed to keep us safe, even though it often harms us by creating a sense of unworthiness and disconnection.
Peter Breggin, a practitioner who has explored the nature of emotions and healing, offers a valuable perspective. He explains that the initial activation of shame and similar emotions occurs in childhood, a time when we lack the cognitive ability to recall or understand what’s happening to us. He writes, “The origins of our demoralizing emotions are literally prehistoric because they are the result of millions of years of biological evolution, and second, because they were shaped in infancy and childhood before we were cognitively able to recall or understand what was happening to us.”
As children, we experience the world emotionally and viscerally, without the tools to make sense of it. Emotional responses to shame become ingrained as protective mechanisms, often without us consciously recognizing or remembering why. These responses remain with us until we take the steps to identify and clear them. This process can be challenging because shame feels so pervasive and ingrained, but understanding its roots—both generational and developmental—helps illuminate the path toward healing.
Trauma and Shame
The connection between trauma and shame is profound and deeply interwoven. Shame often arises from experiences of being hurt, particularly in childhood, when we are most vulnerable and impressionable. Unhealed and unprocessed shame becomes part of what Peter Breggin calls our "negative legacy emotions." These are emotions passed down through generations, often reflecting not what we have done but what has been done to us. They originate from unresolved traumas and hardships in our lineage and become internalized as part of our emotional landscape.
Breggin describes how these legacy emotions—shame, guilt, and anxiety—are frequently imposed on individuals through experiences of abuse, bullying, and violence. Children who are harmed often feel shame, not because they are guilty of anything, but because shame becomes their emotional response to being mistreated. This is especially evident in cases of sexual abuse but applies to other forms of harm as well. Ironically, those who inflict harm are often carrying their own unhealed shame, which perpetuates a cycle of hurt. Perpetrators may act out of their unresolved pain, and while their behavior must be interrupted, it is essential to recognize that they, too, are in need of healing.
Shame becomes a barrier to healing because it leads to hiding. When we carry shame about our experiences, whether abuse, neglect, or even something as seemingly benign as parental separation, we often isolate ourselves. Children, for example, may interpret a parent leaving for work as rejection, internalizing feelings of unworthiness or inadequacy. In cases of abuse, shame compounds the pain, making it nearly impossible to confront or process the experience openly. This hiding, fueled by shame, keeps the wound locked in, preventing healing and perpetuating cycles of disconnection.
Tara Brach offers insight into how trauma interacts with shame, explaining that trauma occurs when the nervous system is overwhelmed, and our most primal coping mechanisms fail. When we cannot fight or flee, we freeze or dissociate, and the unprocessed fear becomes locked in the body. This state of unresolved fear and reactivity leads to chronic conditions such as anxiety, depression, addiction, and PTSD. Trauma is not a rational experience, and the patterns of reactivity it creates are not conscious choices. They are coping strategies born out of survival instincts, driven by the limbic system, when we lack access to the reasoning and compassion of our higher brain functions.
Trauma leaves individuals disconnected—from themselves, from others, and from the possibility of healing. This is where shame plays a compounding role. The layer of shame placed over traumatic experiences makes them harder to access, process, and heal. Brach emphasizes that the process of disconnecting and living in reactivity is not chosen; it is a survival response that becomes ingrained when conditions for safety and care are absent.
In our work, whether with ourselves or clients, part of the healing process involves helping individuals notice where they are living in reactivity. By creating safety, fostering connection, and addressing the somatic imprint of trauma, we can begin to shift these patterns. Healing shame and trauma requires recognizing the ways they are intertwined and addressing the root causes with compassion and care. This approach opens the door to reconnecting with self and others, creating pathways for true healing and resilience.
Expressions and Effects of Shame
Shame creates a distorted lens through which we see ourselves and the world, isolating us and reinforcing the belief that we are alone in our struggles and fundamentally at fault. This lens profoundly shapes our thoughts and behaviors, making us feel that our challenges and imperfections are shameful. In my experience, this sense of being "the worst" or "uniquely flawed" is nearly universal, whether in therapeutic settings, transformative decluttering work, or other contexts. This highlights how shame distorts reality and isolates us.
Even in the presence of love and support, shame perpetuates separateness and loneliness. It convinces us that we are undeserving of connection, making it difficult to receive love or engage authentically in relationships. The fear of vulnerability—the dread of being seen in our perceived "wrongness"—leads to hiding and secrecy, disconnecting us from others and parts of ourselves. This cycle of disconnection compounds the isolation.
Tara Brach illustrates this well, saying, “The most painful layer of suffering that surrounds trauma is shame. We blame ourselves for the ways our body and nervous system found to survive.” This self-blame becomes a barrier to healing, blocking access to self-compassion and preventing reconnection with our innate aliveness and spirit. Shame thrives in secrecy, convincing us to hide our struggles and preventing us from seeking the help and perspective we need to heal.
Shame also interferes with emotional expression, often shaped by societal norms and oppressive systems that dictate acceptable emotions. For example, women may feel shame about expressing anger, while men may feel shame about showing fear or sadness. This conditioning suppresses emotional authenticity and deepens our disconnection, making healing even more difficult.
Moreover, shame immobilizes us, paralyzing growth and self-reflection. The belief that we are inherently flawed prevents us from addressing mistakes or changing dysfunctional patterns. Brené Brown aptly states, “Shame corrodes the very part of us that believes we are capable of change.” This belief stifles individual growth and collective progress, as shame limits our ability to reach our potential and connect authentically with others.
Shame manifests in various ways, some of which may be unexpected. While it often leads to hiding and withdrawal, it can also present as defensive behaviors like arrogance or grandiosity. These are often misinterpreted as confidence but are, as John Bradshaw describes, "defending scripts" designed to mask deep insecurity and shame. Recognizing this dynamic is essential for practitioners to address the root causes of these behaviors with compassion and clarity.
Despite its challenges, healing and transforming shame is entirely possible. It starts by bringing shame into the light—naming it and creating spaces for individuals to share their experiences without judgment. As Brené Brown notes, “Shame hates it when we reach out and tell our story. It hates having words wrapped around it. It can’t survive being shared.” Sharing dismantles the power of shame, allowing it to dissipate.
For practitioners, helping individuals reconnect—with themselves, others, and their emotions—is essential and transformative. Creating environments where people can risk vulnerability, embrace feedback, and rediscover their inherent goodness is key to healing. When shame is cleared, individuals can step fully into their potential, offering their unique gifts to the world and contributing to collective healing and progress.
As practitioners, you are already part of this important work. It is challenging and often undervalued, but it is deeply impactful. I encourage you to take a moment to honor the effort and heart you bring to your practice. This work matters. Together, we can unlock the profound potential beyond shame, fostering healing for individuals, communities, and the world.
Healing Shame
Healing shame begins with bringing it into the light. Shining the light of day on what we feel ashamed of—naming it, sharing it, and holding it with compassion—opens the door to healing. As much as shame convinces us to hide, it cannot survive exposure. Talking about shame and the experiences tied to it clears the heavy emotional weight. I’ve experienced this personally—moments when the act of speaking aloud something I felt deep shame about immediately lightened the burden. What felt unbearable in silence became manageable and lessened when shared.
This process, however, is not easy. Shame is powerful and protective, making it feel terrifying to expose. That’s where our role as practitioners is vital—walking with people through this vulnerable, edgy space, helping them trust that healing is worth the discomfort. Brené Brown highlights this beautifully: “We desperately don’t want to experience shame, and we’re not willing to talk about it. Yet, the only way to resolve shame is to talk about it.” Sharing in honesty and vulnerability breaks shame’s grip, as shame cannot survive in an environment of openness and connection.
A powerful example of this comes from Tanya Denise Fields, shared in Tarana Burke and Brené Brown’s book on shame and resilience in the Black experience. Fields describes how societal oppressions like racism, fat antagonism, and colorism deeply shaped her self-perception, leading to shame that immobilized her. For years, she shared candid insights into her life with thousands of followers but kept hidden the shame she felt as a survivor of intimate partner violence. Breaking her silence and speaking openly about her experiences was transformative. As she shared, others came forward, empowering one another to confront their own shame and realize they were not defined by it. Her words capture the shift perfectly: “I was giddy, and I felt more free than I ever had in my life.”
This story illustrates how healing shame not only frees the individual but also creates ripples of empowerment and connection for others. When we bring shame into the open, we create opportunities for collective healing, showing others they are not alone and challenging the societal ideologies that perpetuate shame.
Benefits of Working on Shame
As practitioners, we can support this process by creating environments of unconditional love, acceptance, compassion, and belonging. These are the antidotes to shame. We help clients see they are not alone in their struggles or feelings. Sharing relatable stories, connecting them with support groups, and fostering spaces where vulnerability is safe and welcomed are all critical tools in this work.
Groups, in particular, are a powerful way to heal shame. When individuals hear others share experiences they once believed were uniquely shameful, they begin to see through the distorted lens of shame. They realize their struggles are not a personal failing but part of the shared human experience. This recognition dismantles the isolation shame thrives on.
Unconditional love, acceptance, and compassion heal not only our clients but also the collective. When shame is healed, individuals can step into their full potential, offering their unique gifts to the world and contributing to a more connected and compassionate society. This work is transformative, not just for the individual but for all of us.
Practitioner Shame
As practitioners, our role is to support clients in accessing their self-compassion. While we offer love, acceptance, and compassion, it’s not simply for clients to receive passively but to help them reconnect with their own capacity for self-compassion. This connection is deeply healing, as it reopens an innate part of themselves that often gets blocked by shame and painful experiences. We need to communicate to clients their inherent goodness and help them rediscover their acceptance of self, a vital step in their healing journey.
Clients must also feel safe to talk about any and everything in their sessions. However, it’s equally important for us as practitioners to recognize when we are not in a position to support them fully. Whether due to a lack of experience or unresolved personal work, there may be instances where we cannot effectively hold space for certain issues. In those cases, transparency and honesty are crucial. For example, we might say, “I realize I don’t have the expertise or emotional readiness to work with this particular concern.” This acknowledgment, far from being a failure, reflects integrity and care for the client’s well-being.
It’s important to remind ourselves that this transparency is not shameful. There’s nothing wrong with recognizing our limits, just as there’s nothing wrong with a client needing a different practitioner or approach. When this occurs, we must communicate clearly that it’s not about a deficiency in the client or ourselves—simply a matter of fit. Offering referrals or connecting them with another resource reinforces their sense of worth and ensures they continue to receive the support they need.
Mark Jacoby emphasizes the significance of the therapist’s empathetic stability in this process, noting that it prevents the client from feeling forsaken during the ups and downs of their journey. Clients often fear rejection deeply, even when they seem to provoke it. These behaviors can be a way of testing boundaries, but they stem from a profound fear of abandonment. While we may need to give feedback, set boundaries, or even discontinue working with a client, we must never communicate a rejection of them as a person. Maintaining a stance of unconditional regard helps dismantle shame rather than reinforcing it.
Healing shame often requires revisiting the early experiences where it first took root. Clients need to understand that these wounds and their impacts came from external sources—circumstances, relationships, or societal messages—not from inherent flaws within themselves. For some clients, talking through these experiences can be a deeply healing process. For others, however, verbalizing trauma can keep them stuck in their heads and block the emotional and somatic release needed for healing. Recognizing this diversity in client needs is critical, and the healing approach must align with each individual.
There is growing recognition of the importance of embodied therapeutic modalities for healing shame and trauma. Shame lives not only in the mind but in the body, and modalities such as EMDR, somatic experiencing, EFT (Emotional Freedom Techniques), and somatic archaeology address this somatic dimension directly. While modern therapeutic institutions are increasingly incorporating these methods, many cultures have long practiced similar healing techniques. Reintegrating these approaches into mainstream therapy is essential for addressing the full scope of shame’s effects.
Finally, it’s essential to understand that shame must be healed from the inside. External accomplishments or achievements cannot resolve internalized shame. As John Bradshaw writes, “Accomplishments do not reduce internalized shame. In fact, the more one achieves, the more one has to achieve. Toxic shame is about being, and no amount of doing will ever change it.” Healing shame requires a focus on reconnecting with our inherent worth and being, rather than trying to prove our value through external actions or successes. This inward transformation is what ultimately allows clients to release shame and step into authentic, wholehearted living.
Closing
As we come to the close of our time together, I always think it’s valuable to reflect on a new perspective, connection, or highlight from our discussion. I invite you to take a moment to consider what stood out to you, what resonated, or what you might carry forward. If there’s anything you’d like to share, I warmly welcome it, and I’m here to answer any lingering questions you may have.
This is a deeply emotional topic, and the work we do as practitioners—engaging with emotions and bodies—is profoundly layered. It’s important to tend to yourselves, not just in this moment but as part of your ongoing practice. Tune into what you’re feeling, honor your own experience, and take the time you need for care and reflection.
I truly appreciate being with you in this space. Even though I couldn’t see your faces, I felt the connection of sharing and exploring this meaningful topic with you. Thank you for being here, for engaging, and for the work you do. It has been an honor to be part of this conversation with you.
About Me
So, a little about me—you’ll find that information included in the slides you’ll receive. You’re always welcome to reach out to connect with me, whether as a colleague or practitioner or if you’re interested in the work I do. I genuinely value those connections and conversations.
I wish you all the best in your work and in your journey. May goodness and growth accompany you in all that you do. Thank you for being part of this space today.
Questions and Answers
How do you help clients cultivate self-compassion and self-acceptance as part of their journey to overcoming shame?
That’s such an important question. There are many approaches, and the best one often depends on the individual, but here are some key strategies:
One significant way is by offering our own compassion to the client. When we model compassion, it allows them to feel it, often for the first time in this context. It communicates that they are worthy of kindness and care, helping them to start internalizing that perspective. It’s a powerful way to introduce the idea that they deserve compassion simply because they exist.
Another approach is to explore the early childhood experiences where their self-compassion might have been interrupted. Often, it’s helpful to invite clients to think about themselves as young children. I might ask, Would you ever treat a child the way you treat yourself? Would you ever blame a child in the way you blame yourself? These questions can be incredibly eye-opening, helping clients shift their perspective and recognize how harshly they’ve been treating themselves.
Similarly, drawing comparisons to how they treat others can be illuminating. I might ask, Would you say to a friend what you’re saying to yourself? Would you judge me this way if I shared the same feelings with you? Almost always, the answer is no. This contrast often highlights the unnecessary cruelty they direct toward themselves, fostering a new awareness that can shift their perspective.
It’s also vital to address the origins of shame. Clients can’t simply decide not to feel shame; it often requires going back to where it began. This doesn’t necessarily mean identifying specific events—it can be more about reconnecting with the emotions of that time. For instance, I might ask, How old do you feel right now when you think about this? If they say, I feel three, we might explore that three-year-old’s emotions and provide a sense of love and care to that younger self. It’s often easier for clients to extend compassion to their younger selves than to their adult selves, and this process can begin to heal those early wounds.
These approaches help clients gradually rebuild self-compassion and self-acceptance, key components in overcoming shame. Thank you for asking such a thoughtful question—it resonates so deeply with the heart of this work.
References
Please refer to the additional handout.
Citation
Sameroff, S. (2024). Unpacking, transforming and healing shame: Theory and practice for mental health practitioners. Continued.com, Article 82. Available at www.continued.com/psychology
Jun 5, 2024
1 CE CreditSocial Isolation and Loneliness: Who's At Risk and How to Help
Christina Marsack-Topolewski, LMSW, PhD, MSW
Editor's Note: This text-based course is an edited transcript of the webinar, Social Isolation and Loneliness: Who's At Risk and How to Help, presented by Christina Marsack-Topolewski, PhD, MSW, LMSW.
Learning Outcomes
After this course, participants will be able to:
- Explain the difference between social isolation and loneliness.
- Identify populations at risk for social isolation, exclusion, and loneliness.
- Describe the risk factors and signs of loneliness and apply effective and creative strategies and approaches to combat loneliness.
Risks and Limitations
In terms of risks and limitations, I recognize that these topics are sometimes hard and they're sometimes heavy. We know that social isolation is complex, and certainly, in our next 90 minutes together, all facets of social isolation cannot be discussed comprehensively. This is an overview to some of these topics and a way to start to think about some creative solutions and opportunities and where we might be able to even pivot in our own work. We also recognize that this topic can be really emotionally charged for people who have experienced this or maybe are even experiencing kind of the aftermath of supporting individuals who are really at risk or experiencing these facets of loneliness and isolation and so forth.
There are certainly limitations in terms of the cultural context and variations, and even different ramifications and different experiences kind of across different cultural groups and different entities. I do have a nod to that as we get into more of the material and the trends and the percentages and so forth, but I just kind of want to just recognize that as well. Some of you may be working with certain populations who are really at risk for all sorts of different reasons, and have maybe very specific cultural backgrounds that come into play. We start to think about kind of these different facets of social isolation and loneliness.
Introduction
Today, we're going to discuss social isolation and loneliness. Our focus will be on who is at risk, how to help, and the factors involved. For those of us working in behavioral health professions, we encounter many consumers and clients who experience, or are at risk for, social isolation and loneliness, or both. Although these topics have recently gained more attention, social isolation and loneliness have been longstanding issues. The COVID-19 pandemic has exacerbated these realities, making them more visible and drawing significant national and international attention.
We'll also explore the U.S. Surgeon General's recent report highlighting these issues as public health concerns. Additionally, we'll examine how the pandemic has intensified challenges for the families, individuals, and groups we serve. For many in this field, it has been a stark wake-up call, revealing significant challenges in supporting and providing resources to our populations.
The pandemic has increased service waitlists and highlighted gaps in services, along with navigation challenges. The risk of isolation and marginalization has grown, affecting more individuals and groups. We'll identify who is at risk and the signs of loneliness, and we'll discuss effective ways to reduce social isolation and loneliness.
It's encouraging to see comments from people across the United States representing various populations. Your roles and responsibilities will differ based on the populations you serve and the contexts in which you work. I'll share strategies and programmatic options that have proven effective, but remember to adapt them to your specific needs. In Michigan and on the East Coast, we've taken elements from successful programs and tailored them to the populations we serve, bringing these strategies to life.
Social Isolation in the United States: What Comes to Mind?
What comes to mind when you think of social isolation? I'll pause there because this is a loaded question. For those of us working in various settings and supporting marginalized and vulnerable populations, different things may come to mind. If you'd like, please share your thoughts in the chat. I'll give everyone a few seconds to contribute. What comes to mind for you when you think about social isolation in our country?
So many great insights are coming through. Certainly, those living in rural areas face unique challenges. Mental health outcomes such as depression and the effects of retirement are significant. Retirement can be an exciting time for some, but for others, it brings a huge life adjustment with ramifications that might not be as positive. Forced isolation and terrorism also contribute to social isolation. Given current global events, many things have had isolating effects. Some people feel pushed aside, which can lead to school avoidance and anxiety. I'll touch on this more as we go on because I see it in my own work. Poverty, transportation issues, and work demands also play a role. Work demands, in particular, can cause social isolation. There's a PBS video I'll point out later that discusses how work can be challenging for socialization.
The death of a spouse or significant other can cause profound changes in life, leading to social isolation and loneliness. For a period in my career, I did grief counseling. I mostly supported kids who had lost a parent and the surviving parent. Many of these young parents, often in their 30s and 40s, faced social isolation because they didn't know where they fit in. It was harder for them to connect with others in similar situations, unlike older widows, who might find more normative support groups.
I appreciate all the comments in the chat. One person mentioned providing care to a loved one and how various life changes, like retirement and losing a family member, made it difficult to maintain relationships. Caregiving combined with other factors can be extremely isolating. This sheds light on the experiences of caregivers, which we'll discuss further. When we think of social isolation, many thoughts come to mind, both in the United States and worldwide. There are numerous factors at play.
I found a picture that reminds me of a cold, dark day. It has snow at the base of where a person is sitting, evoking a feeling of darkness and cold. This image reminds me of the experiences individuals shared with me during clinical treatments, describing their feelings of darkness and isolation.
Figure 1. Photo by Noah Silliman on Unsplash
Dr. Matthews shared my bio, but I'll give some context. Most of my work has been with populations with developmental disabilities in public schools and their family caregivers. In these experiences, I've seen social isolation and loneliness pervasive for about 20 years. Families sometimes feel socially excluded, and individuals with disabilities can feel lost even in large groups. My other work at the university involves research and teaching while also working in clinical settings where people discuss various realities and experiences. In the last few years, demands in K-12 have escalated. Hearing from students, particularly adolescents, I've noticed darker days and a sense of mundanity. Many feel like every day is Groundhog Day, lacking connection and purpose, which is certainly challenging.
Social Isolation vs. Loneliness
Social isolation and loneliness are not mutually exclusive, nor are they synonyms. Social isolation refers to a lack of social network or social contact. Some of you mentioned in the chat that limited regular social contact is certainly a factor. It's important to understand the differences between social isolation and loneliness. Addressing these issues requires recognizing their overlapping nature. Loneliness, on the other hand, is the feeling of distress from the cognitive appraisal or perception of being alone, separated, or disconnected.
Sue Coyle, in an article published in Social Work Today, stated, "One can also experience social isolation without experiencing loneliness. The latter is a possible effect of the former, not a certain one. In fact, social isolation and loneliness do not always go together. About 28% of older adults in the United States, or 13.8 million people, live alone, according to a report by the Administration for Community Living’s Administration of Aging of the U.S. Department of Health and Human Services. But many of them are not lonely or socially isolated. At the same time, some people feel lonely despite being surrounded by family and friends." This information, along with quotes from the National Institute on Aging from 2019, highlights the complexity of these issues. Coyle also noted, "Loneliness is a perception, as Crewe noted. It is a negative effect feeling of being alone and disconnected. According to the American Psychiatric Association, loneliness usually refers to the distress that people feel when their actual social involvement and relationships are not what they want them to be."
Many of you mentioned social media in the chat. It's profound to discuss this because social media can sometimes exacerbate feelings of disconnection. In clinical practice, I often advised clients to limit social media use and offered alternatives. While social media can be a tool for connection, it can also lead to negative ramifications through constant comparison.
Perception plays a crucial role in differentiating social isolation from loneliness. People might not feel socially isolated or lonely but can still experience adverse physical and mental health impacts. This is important to note as more people work remotely or in hybrid settings. Some thrive in office settings and find positivity in going to work, even in a hybrid capacity. Others find remote work beneficial. However, some may recognize that remote work leads to social isolation and loneliness, impacting their physical and emotional health. Even without perceiving loneliness, individuals can still experience adverse effects. Mother Teresa once said, "I still think that the greatest suffering is being lonely, feeling unloved, just having no one. This is the worst disease that any human being can ever experience." These words, decades old, resonate with the U.S. Surgeon General's report on the profound difficulties of social isolation and loneliness. This is not just a personal issue but a public health issue. Being socially isolated and lonely is akin to smoking 15 cigarettes a day, highlighting the severe impact on health.
Setting the Stage
I want to set the stage for our discussion. Think back to when you first realized the onset of the pandemic. For many, this was a moment of shock and uncertainty. I'll share my experience. I remember being in the grocery store, walking through the frozen food aisle. The shelves were almost empty. Everyone around me looked bewildered and stunned, hesitant to take the last of anything. That moment, for me, was a clear signal that something was seriously wrong. It was an experience unlike anything I'd encountered in my lifetime.
What about you? When did you first realize the pandemic's impact? Feel free to share your thoughts in the chat. I see some of you mentioning similar experiences—grocery shopping, noticing empty shelves, and people panic-buying. One person mentioned it was about a week before the shutdown when they truly understood the scale of it. Celebrations were canceled, workplaces closed, and kids had to be trained to wear masks. Jessica, thank you for sharing your experience with young children, especially those with sensory issues. The toilet paper crisis and bulk-buying of masks were also significant markers of the pandemic's early days. These moments set the stage for what was to come. As we look back, it's clear that this realization came at different times and in various ways for each of us. For our clients, consumers, and students, the pandemic was an amplified experience. Those already dealing with anxiety or depression faced even greater challenges.
Despite these difficulties, my colleagues and I have published work on some unexpected silver linings. We saw increased family cohesion, new communities forming, and innovative solutions emerging. However, the adolescent population and older adults were profoundly impacted. Thank you for sharing your thoughts in the chat. It's always valuable to hear different perspectives as they relate to our work.
Rising Rates of Loneliness for Many Decades
If we look back many decades, even before the 1970s, we see a long trajectory of rising loneliness across all age groups. A common misconception is that older adults are the primary victims of social isolation and loneliness. While it is true that older adults face significant barriers, such as transportation issues and declining social networks, trends show that loneliness affects all age cohorts.
The Epidemic of Social Isolation & Loneliness
Consider this: 60% of Americans feel lonely regularly. This is a profound statistic. In October, I spoke at a social isolation summit for a healthcare company, attended by professionals working with various populations. As a college professor, I see firsthand how loneliness affects students. Many of you treating college students in clinical practice might notice similar trends.
Loneliness is a public health crisis, impacting both physical and mental health. Research supports the link between social isolation, loneliness, and premature mortality. Dr. Lori Santos from Stanford University discusses these issues, noting that people are spending less time together, which exacerbates the problem. She describes the epidemic of loneliness as drastic, affecting both our bodies and minds. There are numerous causes and factors contributing to this increase.
People are not only unhappy but also more isolated than before. The lack of free time for social interaction is a significant factor. Many people spend their days on back-to-back Zoom meetings, losing the casual conversations that might occur in an office setting. These small interactions, like offering support to a colleague, are essential. A personal anecdote highlights this point. I was in the grocery store with my three-year-old daughter. We had a lot of items, so I chose not to use the self-scan and went to the cashier instead. The store was packed, and there was a long line. An elderly man behind me started a conversation, sharing that he was caring for his wife with dementia. These small dialogues, made possible by the long line, allowed us to connect.
Neighborhood and community conversations are also important, but they are not always feasible for people living in rural or unsafe areas. Dr. Lori Santos from PBS talks about the impact of technology on social interactions. Many believe technology connects us, but it often leads to constant comparison and missing out on present interactions.
For example, think about being at a restaurant or in an airport where everyone around you is on their phones. Families sit together but don’t interact because they’re engrossed in their devices. This phenomenon is especially noticeable in schools. When students were allowed to bring their own devices, interactions suffered, and behavioral issues increased. Once the devices were removed, social interactions flourished, and behavioral concerns decreased. Dr. Santos's video discusses how missing out on in-person interactions is a significant issue. Organic, spontaneous conversations are vital for our social well-being, and technology often disrupts these moments.
Health Impact on Social Isolation and Loneliness in Children and Adolescents
Let's discuss the health impacts of social isolation and loneliness in children and adolescents. These challenges encompass various aspects of health and mental health. I currently work part-time consulting for students receiving special education in public schools due to health, mental health, or other reasons. Some students have chosen to go virtual for various reasons, significantly altering their daily experiences. I assist in structuring their learning environments and work with families to provide accommodations and modifications tailored to their specific needs.
I often see co-occurring mental health challenges among these students. Additionally, I work with many adolescents suffering from chronic pain caused by conditions like fibromyalgia or short gut syndrome, which require frequent medical visits. These students often experience increased isolation and loneliness. For instance, a student receiving weekly infusions may face challenges in maintaining meaningful social interactions. It is crucial to balance health needs, particularly for those with compromised immune systems, with efforts to reduce social isolation.
Social Isolation & Older Adults
For older adults, many of you may work with this population or have personal connections to it. One in four community-dwelling adults aged 65 and older are considered socially isolated. Social isolation impacts health in various ways, which the next slide will detail. However, it's important to note that social isolation is linked to premature mortality from all causes—a profound public health issue.
Poor social relationships, characterized by social isolation or loneliness, have significant health implications. These include a 29% increase in coronary heart disease and a 32% increase in the risk of stroke. Loneliness is also associated with physical frailty, cognitive decline, dementia, and both physical and emotional declines. Additionally, it leads to higher rates of falls and, as previously mentioned, increased rates of stroke and heart disease.
Demographics & Loneliness
When discussing the demographics of loneliness, it's important to consider the diverse cultural backgrounds we work with. Disparities and differences significantly impact experiences of loneliness. We cannot apply a one-size-fits-all approach to understanding how loneliness affects people across the United States. Underrepresented racial groups, such as Hispanic adults, face disproportionate impacts. Notably, 75% of Hispanic adults report feeling lonely, a figure that surpasses the 60% national average. If you work with or know individuals in this group, be aware of this issue. Various strategies and supports can help make environments more accessible, welcoming, and inclusive. Some of these strategies will be detailed in the slides at the end.
Similarly, 68% of Black and African American adults report feeling lonely, which is higher than the 60% average. Lower-income individuals also report higher loneliness levels compared to those with higher socioeconomic statuses. Factors such as transportation, literacy, and disabilities often play a role, impacting income and contributing to these feelings of loneliness. These populations face additional barriers and challenges in mainstream society that further exacerbate their situation.
Interestingly, young adults are twice as likely to experience loneliness compared to seniors. This statistic may be surprising, especially for those working with adolescents and emerging adults. Many of you may interact with individuals in this age group, making this information particularly relevant. For instance, in Michigan, a radio station in Metro Detroit starts playing Christmas music around Halloween. The primary listeners are college-aged students who seek the nostalgia and comfort of home during their time away at college. Traditions, community, and family significantly influence young adults' sense of belonging. More young adults feel left out compared to older adults. While it's true that older adults experience loneliness and isolation, younger adults face these feelings to a greater extent. This insight emphasizes the need to maintain and expand programs and services for all age groups. Men and women report similar rates of loneliness, with men slightly more likely to feel lonely.
Age matters significantly in the context of loneliness. A survey found that three in five American adults report feeling lonely, with younger adults being the most affected. Among Generation Z, nearly 80% experience consistent loneliness. For millennials, the figure is slightly lower at 71%. In contrast, about 50% of baby boomers report feeling lonely. These statistics highlight the necessity of ongoing efforts to augment programs and raise community awareness about the widespread impact of loneliness across different age groups.
Loneliness Among Adolescents
I want to discuss adolescents for a bit. As I mentioned, the majority of my current work is with adolescents who have various disabilities and receive special education support. These disabilities include autism, learning disabilities, physical health conditions, and mental health conditions. I work with many individuals with ADHD and co-occurring mental health issues such as anxiety, depression, and suicidal ideation.
A recent study on adolescents identified five main themes based on their experiences. One theme described loneliness as an "extreme dark experience." Another theme highlighted how adolescents are "exhausted by loneliness but unable to sleep restfully." Many of you working with similar populations may notice how sleep is impacted. In my practice, we discuss sleep hygiene informally, addressing routines and late-night activities like social media use, which affect their daytime functioning and schoolwork. Adolescents also reported that loneliness revolves around difficulties with peer relationships, which become more challenging when there is family conflict. For example, since the advent of cell phones, virtual bullying has become common, amplifying peer conflict and isolation. Social media can exacerbate these challenges, even though it has benefits.
The fourth theme is that school becomes a difficult place for those experiencing loneliness. I recall working with a student who decided to take all his high school classes virtually because of severe anxiety and loneliness. He felt more comfortable in a virtual setting, and we worked with his family to provide social opportunities that suited his needs. This student, who had high-functioning autism, struggled with physical illness due to anxiety at school and felt excluded and unsafe.
Lastly, adolescents believe that coping strategies often fail to alleviate loneliness. A 15-year-old in the study stated, "Everyone says it's normal for teenagers to feel like this, but it's not." Another participant mentioned that counseling was unhelpful, as it suggested positive thinking would solve everything, which didn't address deeper systemic and relational issues. Many young adults are reluctant to share their feelings of social isolation and loneliness. Recently, I worked with a student whose grades had plummeted. He expressed feeling lonely, disconnected, and uncertain about his place and purpose daily. These transitional years are particularly challenging as students grapple with graduation, future plans, and finding their path in life. It's crucial to build supportive plans that scaffold positive experiences and address these foundational issues.
Parents & Guardians vs. Non-Parents
I found the comparison between parents and non-parents particularly interesting. Many of you here are likely parents, and as a parent myself, I can relate to these experiences. I have two young daughters, aged two and three-and-a-half, and getting out of the house can be quite a challenge. Between meals, library visits, play places, and parks, I've noticed how tired parents often look, as if we're all just trying to figure it out together.
Notably, 65% of parents and guardians, compared to 55% of non-parents, report feeling lonely. This loneliness impacts not only the parents but also their children. When parents feel lonely, defeated, or isolated, it can have significant implications for their kids. Therefore, anything we can do to augment support, recognize their struggles, and foster connections can be incredibly helpful. There's a wealth of literature supporting the importance of such interventions.
Living Arrangement Matters Usually
Many people live alone and thrive, enjoying robust social lives. I have a colleague in her 70s who lives alone and has a vibrant social life. She's always asking me about my activities, and I often find myself admiring her active lifestyle. In her case, living alone doesn't mean feeling isolated or lonely; she has many opportunities to connect with others through various groups and activities.
However, for many Americans, living with others reduces the likelihood of feeling lonely compared to living alone. An important exception is single parents and guardians. This group can experience significant isolation, which can be detrimental to their health. They are more likely to report feelings of loneliness, highlighting the need for targeted support and interventions.
Major Impacts on Health and Mental Health
We talked about this earlier, but the impact of lacking personal connections on physical health is profound. It's more detrimental than smoking 15 cigarettes a day, being overweight or obese, or experiencing high blood pressure. These effects are significant and alarming.
This issue doesn't end here; I have additional statistics to emphasize the public health implications. As we consider the reasons behind this significant problem, it becomes clear why addressing social isolation is so crucial.
Know the Risk Factors
When considering risk factors, several key points come to mind. Many of you work with individuals who experience some or all of these issues. Living arrangements, such as living alone, certainly present a risk factor.
Individuals who are homebound, near homebound, or have ambulatory or mobility challenges are also at significant risk, particularly in cold climates. I have a friend who developed a severe physical disability after a water accident. When he lived in Michigan, his muscles would tighten up due to the cold, making it extremely difficult for him to walk. Weather challenges, whether it's too hot, too cold, or too wet, exacerbate difficulties for people with disabilities or mobility issues.
Major losses or life challenges also play a role. For example, widowhood can drastically change social structures and group dynamics. Retirement, while potentially positive, often comes with its own set of challenges. Proactive individuals plan their retirement activities, but others may struggle with the loss of daily structure. The loss of caregiving roles, especially among aging caregivers of adults with autism and other neurodevelopmental disabilities, also contributes to feelings of loneliness and social isolation.
Financial challenges can hinder people's ability to connect with others, impacting their access to transportation and other resources. Caregiving, whether for a child, an aging spouse, or a parent, often involves many hours of isolated work. Mental health or cognitive challenges can also create barriers, making it difficult for individuals to commit to plans due to unpredictable conditions.
Physical health issues can similarly deter people from making social commitments, as they might not want to cancel plans if their health declines. Other factors include language barriers, location factors, and experiences of discrimination. Unsafe areas, rural or remote locations, and hard-to-access places significantly contribute to social isolation and loneliness.
I recall working with a professor who studied older adults living in Detroit. These individuals shared their challenges and strategies for maintaining health in an unsafe environment. They discussed activities like playing bridge, attending church, participating in Bible study, and exercising. However, their ability to engage in these activities was often limited by their surroundings, further highlighting the impact of location on social isolation and loneliness.
Benefits of Social Connections
There are numerous benefits to supporting social connections in our own lives and for those around us. Many of you may be, or know, individuals who act as connectors, always introducing people and fostering new relationships. This role can be invigorating and highly beneficial.
Supporting social connections can lead to a lower risk of anxiety and depression, as well as improvements in self-esteem, empathy, and trust. Interestingly, fostering social connections can increase the chances of longevity by 50%. People with strong social ties are more likely to report good overall physical and mental health. Achieving the right balance is crucial—adequate sleep, socialization, and a healthy work-life balance all contribute to well-being. I have references available at the end for anyone interested in further reading.
Community and Belonging: What Comes to Mind When You Think of These Words?
When you think about community and belonging, what comes to mind? Feel free to add your thoughts in the chat. Community and belonging. Yes, joy, as Venus mentioned. Feeling comfortable to be yourself, support, diversity and inclusion, connection, love, social opportunities, purpose, security, respect, fulfillment. Having people to connect with, people helping one another. Reliance and social connection feed the brain and safety. These are all wonderful points.
I remember attending a training session on community, diversity, equity, and inclusion. One of the speakers emphasized the importance of these aspects. When I think of community, I recall seeing smiles appear on people’s faces as they wrote down their thoughts during that session. It was heartwarming to witness.
Many of us have roles that enable us to foster these aspects of community and belonging, whether in our personal lives, communities, or friend groups. People working together for the collective good is crucial. For many years, there has been a strong push for independence in the U.S. While independence is valuable, such as teaching my young daughters to put their dirty clothes in the hamper, I believe we should strive for interdependence. This means relying on each other, giving and taking, much like a potluck where everyone contributes and is included.
Shifting towards a stance of community, belonging, respect, and inclusivity can significantly mitigate feelings of isolation and not belonging. I love this quote from Maya Angelou: "I long, as does every human being, to be at home wherever I find myself." Let's explore the reasons behind societal disconnection. Various barriers contribute to this issue, not just in the U.S., but globally. Although it might be less pronounced in some countries, communication barriers, transportation and technology barriers, structural barriers, workplace changes, and a focus on independence rather than interdependence all play a role. What am I missing here?
A Deeper Dive Into the Root of Disconnection
When we think about the root of disconnection, what other barriers come to mind? What do you see in your own work that isn’t on this list? Yes, trauma, transportation issues, emotional factors, and fear are significant barriers. Anything else? Financial challenges, mental health issues, language barriers, anger, lack of knowledge, and shyness are also crucial factors. I work extensively with individuals with autism, and they face numerous barriers. Communication challenges are common. Transportation is often a hurdle since many don’t drive and can’t access opportunities as easily, including jobs. Structurally, our society is designed for a neurotypical population, creating additional obstacles for those with autism.
Physical challenges are another major barrier. For instance, clients with cerebral palsy face difficulties in participating in activities they enjoy with their loved ones. Transportation becomes an issue, especially in bad weather, which is common here in Michigan. If their ride gets sick, they miss out on activities like church services or going to the symphony. These barriers have significant ramifications, impacting their ability to connect and engage with their communities.
Practical Tips
Here are some practical tips I found useful when working with clients. These strategies are well-known and often come to mind as effective ways to scaffold support based on individual needs.
Practice Wellness:
- Exercise regularly
- Eat healthy
- Maintain good sleep habits
- Engage in enjoyable activities
I’ve worked with clients to implement these practices tailored to their specific needs and challenges. Staying active and connected to others is essential. These habits are often learned and integrated into one’s lifestyle. However, they may need reinforcement, especially for those significantly impacted, such as adolescents who have been hesitant to return to physical school buildings since the pandemic.
Utilize Community Resources and Events:
- Engage with faith communities, which can be effective for those who find a sense of belonging in these spaces. There’s substantial literature supporting the protective role of faith communities, spirituality, and religion in addressing health and mental health challenges.
- Participate in community events and resources, which do not always need to be local. For instance, online communities can provide significant support.
In my research, as part of a national task group on intellectual disabilities and dementia practices, I’ve seen the importance of community. My colleague and I have studied caregivers of individuals with intellectual disabilities and dementia, often including those with Down syndrome. This group of caregivers is often invisible, spending countless hours navigating services, advocating, and providing in-home care for their loved ones who are in a state of decline due to complex health needs and dementia.
One heartening example is an online support group for these caregivers. People from all over the world join this community, sharing tips, offering support, and discussing their challenges. This group has created a sense of belonging and support that transcends geographical boundaries. My colleague and I studied this group with ethical approval, and it was inspiring to see how community can uplift individuals, even from afar. This online community demonstrates how people can lift each other up, regardless of distance, offering a model for how we can foster connections and support in various contexts.
Other Possible Solutions
One possible solution involves leveraging technology. I was connected with a group in Delaware that runs a program offering in-home support for older adults and people with chronic illnesses. These individuals, who are predominantly homebound, often need additional support services and are at risk of feeling isolated or lonely. We adapted their program for our demographic in two Michigan counties and launched it just over two years ago. Essentially, it offers in-home practical support to older adults with chronic illnesses and disabilities through friendly visits from college students.
These students are training to become social workers, nurses, occupational therapists, public health professionals, and more. They seek to expand their experience with older adults, better understand health, and grasp the role of community services, identifying any gaps. We found that in-home practical support is often scarce and expensive in Michigan. While medical care is accessible, necessary in-home support is not always available, leading to loneliness and isolation among many older adults.
Each week, over a hundred older adults receive friendly visits from our students. The intergenerational benefits of this program are significant. As the program grew, we had a waitlist. In January, we piloted a telesupport program from the west side of the state. While this is not a complete replacement for in-person visits, it provides an alternative. We believe these interactions reduce psychological distress and loneliness, offering benefits across generations.
Another solution involves creating comprehensive referral and resource guides. Organizations can collaboratively build these guides to streamline the process, reducing the need for repeated searches for individual cases. Understanding the reasons behind disconnected networks can also help address the issue more effectively.
Programs like the Links Program in K-12 settings connect students with disabilities to peers, fostering relationships, social learning, and appropriate behaviors. Students often prefer learning from peers rather than teachers or social workers, making these programs highly effective.
Family support programs are invaluable. We received grant funding for a program assisting aging caregivers of adults with autism and other neurodevelopmental disabilities. Family support navigators helped these caregivers navigate aging services, disability services, and services for themselves and their loved ones. Relationships were built through this support, greatly benefiting the caregivers and their families. Unfortunately, due to funding constraints, we could not continue the program statewide in Michigan.
Faith-based communities can also be excellent sources of connection and referrals, offering support across various needs. By implementing these solutions and continually seeking innovative ways to support social connections, we can help mitigate feelings of isolation and loneliness across diverse populations.
Intergenerational Programs
Let's discuss intergenerational programs and their impacts. The program I mentioned earlier, called Lori's Hands, is a prime example. Originating in Delaware over a decade ago, this program provides in-home support for people with chronic illnesses. The foundation of their approach is intergenerational collaboration.
In Lori's Hands, college students work with individuals who have chronic illnesses across various stages of life. Here in Michigan, our program specifically focuses on older adults. This focus arose partly from identified needs and partly due to the specific requirements of the grant we received. However, intergenerational programming can take many forms and benefit a wide range of populations.
Intergenerational programs like Lori's Hands create meaningful connections between younger and older generations. These programs provide practical support to older adults while offering valuable learning experiences for students. By bridging generational gaps, they foster mutual understanding, reduce feelings of isolation, and promote overall well-being for both groups involved.
Examples of Intergenerational Programs
Let's get our brains thinking about intergenerational programs and how they can be expanded or integrated into your work. Here are some examples to consider:
- Foster Grandparent Program: This program pairs older adults with children who need extra support, providing mentorship and companionship. It's a fantastic way to foster intergenerational connections.
- Buddy Program: At Northwestern University, first-year medical students are paired with individuals in the early stages of dementia. This program promotes mentorship and social engagement for both participants, enriching their experiences and understanding.
- Opening Minds Through Art: This intergenerational art program pairs individuals with dementia with others to create art together. Art can be a powerful mode of expression, especially for those with cognitive decline, allowing them to connect and communicate beyond language barriers.
- Kindness Creator: This program focuses on fostering kindness and understanding between generations. It's another excellent example of how intergenerational interactions can be beneficial.
- Lori's Hands: As previously mentioned, this program involves college students providing in-home support to older adults with chronic illnesses. It highlights the benefits of intergenerational collaboration.
- Preschool and Retirement Complex: One particularly heartwarming example involves a collaboration between a preschool and a retirement complex. The interaction between preschoolers and older adults brings numerous benefits. For young children, learning from older adults helps shape their views and respect for the elderly. Older adults, in turn, find a renewed sense of purpose. One participant shared that knowing the children expected her made it easier to get out of bed despite not feeling well. This sense of responsibility and connection can significantly enhance the well-being of older adults.
By considering and integrating these intergenerational programs, we can create opportunities for mutual learning, understanding, and support across different age groups. These programs not only combat loneliness and isolation but also enrich the lives of all participants involved.
Benefits of Intergenerational Programming
Other benefits include a greater sense of community connection, enhanced social engagement, and a deepened sense of meaning and purpose, all of which are mutually beneficial. When we consider the advantages of intergenerational programming for different generations, one reason I am particularly fond of it is its holistic impact. I am currently part of a cohort in Michigan examining these benefits.
Intergenerational programming isn't just about helping older adults or kids; it spans the entire lifespan of those involved. Participants experience diverse learning opportunities and numerous benefits. In our program with Lori's Hands, we observed reduced psychological distress and decreased loneliness among older adults. These findings are currently under review in a gerontological social work journal. Additionally, we found that our students gained self-efficacy and competence, as well as meaningful experiences.
Arizona State University hosts a Salvation Army program that provides social services to low-income adults aged 50 and above. They discovered that many seniors wanted to learn technology skills, leading to various program benefits outlined in the final slide of the presentation. However, I want to highlight some quotes from participants. An Arizona State University student noted, "I do believe we had a positive impact on the older adults at the center. Just having new people to talk with and engage with helps sustain their health and mind, making them happy." This student felt their work was impactful and fulfilling. Another student emphasized the community benefits, stating, "The most important thing I learned working with this project is the importance of continuing my involvement in the community." I find this sentiment inspiring, showcasing the profound and positive effects of intergenerational programming.
Social Support
When considering social support, much of my work focuses on this concept. Specifically, I examine quality of life, social support, and caregiver outcomes for aging caregivers of adults with autism. These areas dominate my publications, reflecting the dual focus on both quality of life and support systems.
When we think about building community, we need to consider the sources of support. Informal support encompasses unpaid assistance from family, friends, and neighbors, forming the core of our environment. Formal support, on the other hand, is paid assistance funded by the government or other mechanisms provided through organizations and agencies.
In my research, I often explore how to build caregiver communities and where social support can be derived. Both formal and informal support networks play crucial roles. As you consider your population, it's likely that community building will involve leveraging these informal networks alongside formal structures and supports.
Supporting Clients and Their Family Caregivers
Supporting clients and their family caregivers is essential, as families form a significant part of the community. This support can be provided through education, learning about and accessing resources, and building and maintaining positive relationships. Many of you may be involved in counseling families or groups, focusing on how to foster healthy, positive relationships and promoting a supportive mindset.
I noticed some excellent contributions in the chat. While I can't read all of them now, it's clear that there are many great ideas being shared. For example, the University of Maine has some impressive initiatives, and RSVP provides senior support through phone calls. Thank you for mentioning these. Such efforts highlight the diverse ways we can enhance support for clients and their caregivers.
Systematic Review
A systematic review of 53 peer-reviewed journal articles, with 11 selected for this specific study, examined the benefits of intergenerational programming. Various types of programs were considered, including artistic, educational, health-related, open-ended activities, and citizen projects. Many of you might already be involved in similar initiatives.
When I was pursuing my master's in social work at the University of Michigan, I had the opportunity to explore both aging and school social work. This dual focus allowed me to integrate my interests in aging caregiving and school-based services. During my internship, I coordinated a program where retired senior citizens provided tax preparation assistance to low-income individuals. It was remarkable to witness the extensive knowledge and expertise these seniors had in tax preparation, homestead credits, and energy and heat credits, which they generously shared with others.
Intergenerational programming offers numerous benefits. For children, these programs foster positive attitudes, behaviors, confidence, and competence. For older adults, they contribute to improvements in health, mental health, and quality of life. One significant takeaway from my work in this field is the profound impact intergenerational programs can have on combating social isolation and loneliness, which are detrimental to physical and mental health and can lead to premature cognitive decline and mortality.
Our program currently supports over 100 older adults, with students gaining internships and practicum experiences under the supervision of one paid staff member. This model has proven to be cost-effective. Intergenerational programming for older adults has been linked to decreased loneliness, increased perceived quality of life, and higher levels of generativity, life satisfaction, and positive attitudes towards children. These programs also contribute to spiritual health and overall well-being.
Where Do We Go From Here?
Earlier, I mentioned the U.S. Surgeon General's report. In 2023, the U.S. Department of Health and Human Services published an advisory highlighting the severe consequences of loneliness and isolation, labeling them as a public health epidemic. This advisory provided a framework for addressing the issue, which is detailed in the link on this slide.
The report outlines several key recommendations. Firstly, we need to strengthen our social infrastructure. Our society is fragmented and disconnected, with significant polarization. Strengthening social ties is crucial. Secondly, public health policies should be pro-connection, fostering opportunities for people to connect. This is more important now than ever.
Additionally, mobilizing the health sector to address loneliness and reforming digital environments to make them inclusive and accessible are vital steps. Continued research to deepen our understanding of loneliness is also essential. Finally, we need to cultivate a culture of connection. Many of you might already be fostering connections in your organizations and communities. We need to expand these efforts, inspire others, and grow a culture of connection. Anything we can do to promote and nurture this culture is immensely valuable.
Key Takeaways
As behavioral health professionals, we understand that social isolation and loneliness significantly impact over 60% of our country. These issues affect people across the lifespan, various racial, ethnic, and cultural backgrounds, and different socioeconomic statuses, though some groups are more affected than others. Social isolation impacts health, well-being, and psychological state.
To address this, we need to promote inclusive practices and create spaces for belonging and inclusivity. One approach is to return to the basics and think creatively about building inclusive environments. For example, I work with a colleague focused on third spaces, like libraries, and how to make these places more inclusive for those who rely on them as a primary gathering spot.
Consider the story of a middle school track runner with a profound visual impairment who wanted to join the track team. This student worked with another student who guided her during races, and they became close friends, forming a supportive community. This example highlights the power of innovative thinking and the significant impact of fostering inclusion and belonging. It required two willing individuals and a focus on safety, demonstrating that promoting inclusion doesn't have to be complicated.
I want to leave you with a quote from Helen Keller: "Alone, we can do so little; together, we can do so much." This sentiment is fitting as we consider how to make our world more inclusive, accepting, and connected. Thank you all for joining today.
Q&A
It seems like safety would be an issue with connecting any strangers, especially older, younger vulnerable individuals. Did any of your interventions include any safety precautions?
Absolutely. Let me discuss our Lori's Hands program as an example. In this program, both college students and consumers, such as older adults or individuals with chronic illnesses, undergo background checks to ensure safety. There's a thorough screening process in place for this. Given the intensity and impact of COVID-19, we implemented additional precautions. Some services were adapted to be contactless to reduce risk. It's essential to always have mechanisms to promote safety, and these precautions need to be tailored to the specific needs of each population and program. Different groups will require different safety measures to ensure that all participants are protected.
Is social isolation harmful if the person doesn't feel lonely?
That's an excellent question, and I appreciate you asking it. It's important to consider that some people may not report feeling lonely or isolated and may appear to be happy. However, this doesn't necessarily mean they aren't experiencing the adverse impacts of social isolation and loneliness.
My deep dive into the literature revealed that even those who don't openly acknowledge these feelings can still suffer from their effects. It's a cautionary note for us all: just because someone isn't reporting loneliness doesn't mean they're not experiencing its negative consequences. We need to be aware of the broader implications and ensure we're attentive to these hidden struggles.
What about individuals experiencing homelessness or heavily justice involved?
Absolutely, and thank you for raising this point. Populations such as those who are homeless or heavily involved with the justice system face significant vulnerabilities, impacting their sense of connection and belonging. This issue is substantial and worth deep consideration. I'd like to share a story to illustrate this. A few years ago, I visited a shelter for older adults in Ann Arbor, and one encounter left a lasting impression on me. A woman I met was struggling with homelessness, and one of her biggest barriers was not having a place for her dog. This dog was a major source of connection for her. This experience made me think about the growing body of literature on animal-assisted support for older adults and individuals with disabilities, highlighting the importance of such connections.
The literature and our daily experiences show that people experiencing homelessness are often fragmented from everyday community life. They face challenges in maintaining human connections, as society frequently dehumanizes them. This fragmentation makes it difficult for them to connect with others for various reasons. Addressing these issues requires a deeper understanding and a compassionate approach to fostering connections and belonging for these vulnerable populations.
References
Fuller-Rowell, T. E., Nichols, O. I., El-Sheikh, M., Burrow, A. L., Ong, A. D., & Ryff, C. D. (2024). The pandemic and social experience: For whom did discrimination and social isolation increase? Cultural Diversity & Ethnic Minority Psychology, 30(1), 107-117. https://doi.org/10.1037/cdp0000561
Giraudeau, C., & Bailly, N. (2019). Intergenerational programs: What can school-age children and older people expect from them? A systematic review. European Journal of Ageing, 16, 363-376. https://doi.org/10.1007/s10433-018-00497-4
Harrington, K. D., Vasan, S., Sliwinski, M. J., & Lim, M. H. (2023). Loneliness and cognitive function in older adults without dementia: A systematic review and meta-analysis. Journal of Alzheimer's Disease, 91(4), 1243-1259. https://doi.org/10.3233/JAD-220832
Hayashi, T., Umegaki, H., Makino, T., Huang, C. H., Inoue, A., Shimada, H., & Kuzuya, M. (2020). Combined impact of physical frailty and social isolation on rate of falls in older adults. The Journal of Nutrition, Health & Aging, 24, 312-318. https://doi.org/10.1007/s12603-020-1316-5
Hemberg, J., Östman, L., Korzhina, Y., Groundstroem, H., Nyström, L., & Nyman-Kurkiala, P. (2022). Loneliness as experienced by adolescents and young adults: An explorative qualitative study. International Journal of Adolescence and Youth, 27(1), 362-384. https://doi.org/10.1080/02673843.2022.2109422
Hutten, E., Jongen, E. M., Hajema, K., Ruiter, R. A., Hamers, F., & Bos, A. E. (2022). Risk factors of loneliness across the life span. Journal of Social and Personal Relationships, 39(5), 1482-1507. https://doi.org/10.1177/02654075211059193
Jarrott, S. E., & Lee, K. (2023). Shared site intergenerational programs: A national profile. Journal of Aging & Social Policy, 35(3), 393-410. https://doi.org/10.1080/08959420.2021.2024410
Jarrott, S. E., Scrivano, R. M., Park, C., & Mendoza, A. N. (2021). Implementation of evidence-based practices in intergenerational programming: A scoping review. Research on Aging, 43(7-8), 283-293. https://doi.org/10.1177/0164027521996191
Johnson, E., & Volsche, S. (2024). Covid-19: Companion animals help people cope during government-imposed social isolation. Society & Animals, 32(1), 56-73. https://doi.org/10.1163/15685306-BJA10035
Joyce, J., Ryan, J., Owen, A., Hu, J., McHugh Power, J., Shah, R., Woods, R., Storey, E., Britt, C., Freak-Poli, R., & ASPREE Investigator Group. (2022). Social isolation, social support, and loneliness and their relationship with cognitive health and dementia. International Journal of Geriatric Psychiatry, 37(1). https://doi.org/10.1002/gps.5644
Juris, J. J., Bouldin, E. D., Uva, K., Cardwell, C. D., Schulhoff, A., & Hiegl, N. (2022). Virtual intergenerational reverse-mentoring program reduces loneliness among older adults: Results from a pilot evaluation. International Journal of Environmental Research and Public Health, 19(12), 7121. https://doi.org/10.3390/ijerph19127121
Kenning, G., Ee, N., Xu, Y., Luu, B. L., Ward, S. A., Goldwater, M. B., Lewis, E., Radford, K., Anstey, K. J., Lautenschlager, N. T., Fitzgerald, J. A., Rockwood, K., & Peters, R. (2021). Intergenerational practice in the community—What does the community think? Social Sciences, 10(10), 374. https://doi.org/10.3390/socsci10100374
Kojima, G., Taniguchi, Y., Aoyama, R., & Tanabe, M. (2022). Associations between loneliness and physical frailty in community-dwelling older adults: A systematic review and meta-analysis. Ageing Research Reviews, 81, 101705. https://doi.org/10.1016/j.arr.2022.101705
Lampraki, C., Hoffman, A., Roquet, A., & Jopp, D. S. (2022). Loneliness during COVID-19: Development and influencing factors. PloS One, 17(3), e0265900. https://doi.org/10.1371/journal.pone.0265900
Lee, K., Jarrott, S. E., & Juckett, L. A. (2020). Documented outcomes for older adults in intergenerational programming: A scoping review. Journal of Intergenerational Relationships, 18(2), 113-138. https://doi.org/10.1080/15350770.2019.1673276
Lippke, S., & Warner, L. M. (2023). Understanding and overcoming challenges in times of personal or global crisis—Editorial on the Special Issue on Loneliness and Health. Applied Psychology: Health and Well‐Being, 15(1), 3-23. https://doi.org/10.1111/aphw.12420
Loades, M. E., Chatburn, E., Higson-Sweeney, N., Reynolds, S., Shafran, R., Brigden, A., Linney, C., McManus, M. N., Borwick, C., & Crawley, E. (2020). Rapid systematic review: The impact of social isolation and loneliness on the mental health of children and adolescents in the context of COVID-19. Journal of the American Academy of Child & Adolescent Psychiatry, 59(11), 1218-1239. https://doi.org/10.1016/j.jaac.2020.05.009
National Academies of Sciences, Engineering, and Medicine; Division of Behavioral and Social Sciences and Education; Health and Medicine Division; Board on Behavioral, Cognitive, and Sensory Sciences; Board on Health Sciences Policy; Committee on the Health and Medical Dimensions of Social Isolation and Loneliness in Older Adults. (2020). Social isolation and loneliness in older adults: Opportunities for the health care system. National Academies Press (US).
Pengpid, S., & Peltzer, K. (2021). Associations of loneliness with poor physical health, poor mental health and health risk behaviours among a nationally representative community‐dwelling sample of middle‐aged and older adults in India. International Journal of Geriatric Psychiatry, 36(11), 1722-1731. https://doi.org/10.1002/gps.5592
Peters, R., Ee, N., Ward, S. A., Kenning, G., Radford, K., Goldwater, M., Dodge, H. H., Lewis, E., Xu, Y., Kudrna, G., Hamilton, M., Peters, J., Anstey, K. J., Lautenschlager, N. T., Fitzgerald, A., & Rockwood, K. (2021). Intergenerational Programmes bringing together community dwelling non-familial older adults and children: A Systematic Review. Archives of Gerontology and Geriatrics, 94, 104356. https://doi.org/10.1016/j.archger.2021.104356
Petersen, J. (2023). A meta-analytic review of the effects of intergenerational programs for youth and older adults. Educational Gerontology, 49(3), 175-189. https://doi.org/10.1080/03601277.2022.2102340
Phang, J. K., Kwan, Y. H., Yoon, S., Goh, H., Yee, W. Q., Tan, C. S., & Low, L. L. (2023). Digital intergenerational program to reduce loneliness and social isolation among older adults: Realist review. JMIR Aging, 6(1), e39848. https://doi.org/10.2196/39848
Prada Crespo, D., Montejo Carrasco, P., Díaz-Mardomingo, C., Villalba-Mora, E., & Montenegro-Peña, M. (2024). Social loneliness in older adults with mild cognitive impairment: Predictive factors and associated clinical characteristics. Journal of Alzheimer’s Disease, 97(2), 697-714. https://doi.org/10.3233/JAD-230901
Pstross, M., Corrigan, T., Knopf, R. C., Sung, H., Talmage, C. A., Conroy, C., & Fowley, C. (2017). The benefits of intergenerational learning in higher education: Lessons learned from two age friendly university programs. Innovative Higher Education, 42, 157-171. https://doi.org/10.1007/s10755-016-9371-x
Senese, V. P., Catone, G., Pezzella, A., Almerico, L., Iorio, M., Maresca, M., Nasti, C., Matascioli, N., & Pisano, S. (2024). The association between social isolation, loneliness and psychological problems in young adults: A study during the acute phase of COVID‐19 in Italy. International Journal of Psychology, 59(1), 184-191. https://doi.org/10.1002/ijop.12962
Shen, C., Rolls, E. T., Cheng, W., Kang, J., Dong, G., Xie, C., Zhao, X. M., Sahakian, B. J., & Feng, J. (2022). Associations of social isolation and loneliness with later dementia. Neurology, 99(2), e164-e175. https://doi.org/10.1212/WNL.0000000000200583
Steward, A., & McDevitt, K. (2023). “Otherwise we would be like an island”: A phenomenological understanding of intergenerational engagement aimed at reducing social isolation. Journal of Intergenerational Relationships, 21(2), 215-233. https://doi.org/10.1080/15350770.2021.1997870
Suleman, R., & Bhatia, F. (2021). Intergenerational housing as a model for improving older-adult health. BC Medical Journal, 63(4), 171-173.
Surkalim, D. L., Luo, M., Eres, R., Gebel, K., van Buskirk, J., Bauman, A., & Ding, D. (2022). The prevalence of loneliness across 113 countries: systematic review and meta-analysis. BMJ, 376. e067068. https://doi.org/10.1136/bmj-2021-067068
The Cigna Group. (2023). The loneliness epidemic persists: A post-pandemic look at the state of loneliness among U.S. adults. https://newsroom.thecignagroup.com/loneliness-epidemic-persists-post-pandemic-look
Verity, L., Yang, K., Nowland, R., Shankar, A., Turnbull, M., & Qualter, P. (2022). Loneliness from the adolescent perspective: A qualitative analysis of conversations about loneliness between adolescents and Childline counselors. Journal of Adolescent Research, 0(0). https://doi.org/10.1177/07435584221111121
Xu, L., Fields, N. L., Chen, Z., Zhou, A., Merchant, A., & Zhou, A. (2022). Big and Mini: A promising intergenerational program for social connections. International Journal of Environmental Research and Public Health, 19(8), 4566. https://doi.org/10.3390/ijerph19084566
Zhu, S., Kong, X., Han, F., Tian, H., Sun, S., Sun, Y., Feng, W., & Wu, Y. (2024). Association between social isolation and depression: Evidence from longitudinal and Mendelian randomization analyses. Journal of Affective Disorders, 350, 182-187. https://doi.org/10.1016/j.jad.2024.01.106
Marsack-Topolewski, C. (2024). Social isolation and loneliness: Who's at risk and how to help? Continued.com, Article 66. Available at www.continued.com/psychology
Mar 25, 2024
1.5 CE CreditsThe Opioid Crisis: A Sociological Perspective
Sophie Nathenson, PhD
This is an edited transcript of the webinar, The Opioid Crisis: A Sociological Perspective, presented by Sophie Nathenson, PhD.
Learning Outcomes
After taking this course, participants will be able to:
- Describe the social context of the opioid crisis.
- Identify three societal-level contributing factors of the opioid crisis.
- Identify two aspects of a holistic, population health approach to addressing the crisis.
The Sociological Perspective
Let's start by covering the sociological perspective and what sociology entails. Sociology is the study of society as a whole, classified as a social science, focusing on human behavior, similar to psychology. However, in sociology, the focus lies in examining differences between groups rather than individuals. Individuals are grouped together based on various social factors, such as age, race, gender, and socioeconomic status. The objective is to compare these groups in terms of behavior, prevalence of illnesses, and other aspects that shape an individual's life course.
Thus, sociology delves into analyzing social factors and aspects of social life and status, as well as structural factors inherent in communities and societies. Medical sociology places special emphasis on understanding social and structural determinants of health outcomes—identifying how community characteristics and social status contribute to potential differences in health outcomes. This field differentiates between upstream factors, focusing on prevention, midstream factors dealing with illness management, and downstream factors, which involve emergency approaches to illnesses.
The population health perspective is essential in this regard, as it assesses the health of a group and examines health behaviors, such as the use of opiates, from a broader population standpoint.
Rather than solely focusing on understanding why an individual may use, our aim is to identify factors associated with the prevalence of addiction and overdose within a society. Thus, we approach health behaviors within a social context, considering not only individual factors but also broader influences such as social norms, community, family, relationships, and the environment where individuals live, work, engage in recreational activities, and socialize. This perspective allows us to explore the impact of social and structural factors on our position in society and our social status, encompassing elements like race, gender, socioeconomic status, and power imbalances, which affect our access to resources.
Structural factors involve examining societal systems. When comparing different societies or communities and analyzing the prevalence of issues like addiction and overdose, significant differences prompt us to explore the underlying reasons for these variations. In doing so, we broaden our scope to consider the systems and structure of societies. This includes evaluating aspects such as the healthcare system, educational system, industries present in the society, media influence, cultural dynamics, and the overall economic structure, including income levels and wealth distribution. Employment and unemployment rates, educational attainment, and access to education among various groups also play a crucial role in this comprehensive analysis.
In terms of culture and the social environment, that also includes norms, how people are socializing, the degree of social isolation, and where people come together. That's another aspect of a society that could influence health outcomes. At the most top-down or broadest level, factors such as political instability, policy, and laws, are interconnected and can trickle down and affect behavior and collective wellbeing.
The Opioid Crisis
Now, shifting our focus to the opioid crisis, it was officially declared a national public health emergency in 2017, encompassing both the misuse of prescription opioids and illegal drugs derived from opium, such as heroin.
This crisis has been labeled as the deadliest in American history, with the United States accounting for only 4% of the world's population but experiencing 27% of global drug overdose deaths. However, it's essential to acknowledge that these statistics may change over time. Research and social surveys indicate that pain levels in the United States are comparable to countries like France and Italy, despite the fact that the U.S. consumes a staggering 80% of the world's opioids. This suggests that opioid consumption is not merely linked to pain prevalence or chronic illnesses where opioids are medically necessary for pain management. Rather, there may be underlying societal factors contributing to the crisis. See Katz (2017) for further details.
Trends Over Time
Analyzing trends over time reveals drastic changes in the opioid crisis. Between 1980 and 2008, there was a 600% increase in opioid overdoses, and from 1997 to 2017, the number increased fivefold. Notably, during the pandemic years, from April 2020 to April 2021, drug overdose deaths increased by 28.5%. You can start to think about the context and what may have contributed to this significant rise, such as the social and economic impact of the pandemic.
When we study populations, societies, and countries, we encounter differences. When we analyze statistics, for example when we look at rates of addiction, overdose, depression, suicide, or suicidal ideation, we can be mislead unless we take into account these real differences between groups. For example, while overall statistics might indicate improvements in certain areas, specific vulnerable groups might still be experiencing increasing rates. This variation among social groups is a core concern in medical sociology, as it emphasizes that diseases, illnesses, and addictions are not distributed evenly across a population; there are distinct patterns and societal factors at play.
Significant variation is observed not only between states in the U.S. but also between counties within those states and as mentioned, among different countries. Such disparities suggest that societal factors play a substantial role in the opioid crisis. If rates were the same across all states and countries, for example, it might imply that individual factors alone are responsible. However, the substantial variation prompts us to explore how societies are structured, what individuals are exposed to within these societies, and the access to resources available, all of which may contribute to the differences that are observed.
Data Limitations
Research and surveys provide valuable insights into the opioid crisis. Self-reported data, when individuals rate their own health, tends to be reasonably accurate and aligned with objective measures obtained in healthcare settings. However, it is essential to acknowledge the limitations inherent in data collection and analysis in social science research.
Overdose rates, for instance, can be subject to miscoding or misattribution when entered into data systems, leading to potential misinterpretations. For example, an accidental overdose might be categorized as a suice. Non-fatal overdoses are often missing from national surveys, which primarily focus on fatal overdoses, potentially overlooking critical information about near-miss incidents that could provide information about underlying factors and prevention strategies.
Measuring opioid use, especially non-medical use and diversion, poses significant challenges. Household surveys can suffer from low response rates, making it difficult to obtain a comprehensive picture of opioid use within households. Furthermore, national drug lab data might not be fully representative, particularly concerning drugs sold in the social markets or the "black market". Harm reduction efforts are challenging to quantify. The criminal justice system also poses difficulties when attempting to collect data from arrestees or prisoners due to their vulnerable status. Even hospitalization data might not be captured uniformly or in a standardized manner, which can affect our understanding of the crisis's scope and severity. Finally, assessing access to drug treatment can be hindered by potential under-coverage in insurance data, preventing us from gaining a fully accurate picture of treatment availability and utilization.
While data sources play a pivotal role in comprehending and addressing the opioid crisis, it is vital to approach them with caution, taking into account their potential limitations and biases.
How Did We Get Here?
Understanding how we arrived at the current state of the opioid crisis requires examining the significant changes in statistics over time and the events that contributed to this complex issue.
In the 1980s, there was a notable downplaying of opioid addiction. A report, which was not robust in its scientific basis, was circulated among medical professionals and physicians, indicating that opioids were not labeled as an addictive substance. In the 1990s, a problem was identified: patients were experiencing pain, but it was not always adequately measured or addressed. In response, healthcare professional associations deemed pain as the fifth vital sign, emphasizing its importance and promoting its measurement. In the 2000s, aggressive marketing strategies, educational initiatives, and promotions targeted physicians in a specific and calculated way. There was overpscribing, in part potentially related to patient satisfaction (Fenton, Bertakis, & Franks, 2012). Patients might have demanded opioids for pain relief, and if patient satisfaction was a key outcome for physicians and the healthcare system, it may have played a role in the overprescribing of opioids. Key
From Prescription to Illicit
Apart from changes within the healthcare system, various social and economic factors also contributed to the opioid crisis. The opioid crisis can be traced back to both prescription drugs, and also illicit drugs obtained through that social channel. There is both diversion use by healthcare professionals and recreational use. For example, there was a big spike in heroin use because people who were addicted to opioids but ran out of a supply or money for their prescription, would be kind of pushed into buying it through social channels in order to access a similar or same high with heroin. There is a close connection between opioids, prescription drugs, and heroin. A study by Cicero et al. (2014) showed that 75% of heroin users had used analgesics, and that painkiller users were 40% more likely to be addicted to heroin. In 2017, the CDC found that there was almost equal distribution of opioids from healthcare channels and social channels. Simply addressing the healthcare side of the opioid crisis would not be enough.
Diversion Risks and Signs
According to SAMHSA (Substance Abuse and Mental Health Services Administration), approximately one in 10 healthcare workers may be abusing drugs, though it's important to recognize that this figure might be an undercount due to the challenges of obtaining accurate data in this context.
Fentanyl has been particularly problematic in terms of diversion, as it has caused the most deaths. Detecting opioid diversion within healthcare systems has revealed that this problem exists across different levels and disciplines, not limited to individuals with the most direct patient interactions. It occurs throughout the hierarchy in healthcare.
Several indicators may suggest diversion within a healthcare setting. These include controlled substances being removed without proper authorization, compromised containers that appear tampered with, the use of substitute drugs on patients who were previously prescribed opioids, and verbal orders that have not been appropriately verified. Self-prescription, improper handling or disposal of waste, and instances where health professionals are unusually administering medications can also be red flags indicating potential diversion activities.
Signs of Misuse and Addiction
Signs of misuse and addiction can be categorized using the three Cs: Control, Craving and Preoccupation, and use despite negative Consequences.
Regarding Control, there is a loss of control. Indicators may include reporting of stolen or lost medications, seeking early refills, seeking drugs from sources, experiencing withdrawal symptoms, and being unable to control their use of opioids.
Craving and Preoccupation involve increased requests for specific drugs and increased pain without a worsening of disease. This may be related to increased tolerance. In addition, an indicator of craving and preoccupation include dismissing non-opioid pain management methods.
Use despite negative Consequences refers to over-sedation, reduced daily activities and functioning, and experiencing relationship issues due to opioid use.
Social-Ecological Model of Risk Factors
From a sociological and psychological perspective on addiction and overdose, a social-ecological model of risk factors is used. This model encompasses multiple levels of influence.
The broadest level considers aspects of society as a whole. The community level looks at the characteristics of specific communities, such as neighborhoods or cities. Interpersonal factors relate to socialization and relationships within an individual's social circle. Addiction and overdose are multifactorial. At the individual level, these various factors include sociological, psychological, genetic, and environmental factors, to name a few, that come together to contribute to this issue.
Individual and Interpersonal Risk Factors
We cannot simply focus on a single risk factor and address it, as these factors not only contribute independently but also overlap and influence each other, making it difficult to isolate one. Therefore, we will begin by examining individual and interpersonal risk factors.
At the individual level, various factors play a significant role. Socio-demographics, including personal social standing, stress levels, and past or current traumas, all have an impact. Additionally, genetics, family history, pain levels, withdrawal symptoms, and self-stigma, which may be internalized from social environments and norms, are crucial factors to consider.
Self-stigma can lead individuals to judge themselves and believe that seeking help is frowned upon, affecting their willingness to seek assistance. Moreover, their determination level and the presence of other addictions, such as cross-addictions, where individuals may switch from one substance or behavior to another, can complicate the situation.
Moving to the interpersonal level, the influence of family and peers becomes prominent. For adolescents, peer influence can be even more powerful than that of the family. Access to substances can also be influenced by social circles, and the ability to seek and distribute drugs can depend on the level of access one has within their social group.
We also need to consider the influence of family history, particularly when it comes to use among family members and friends. Additionally, the nature of your relationships and associations, especially in romantic relationships, can significantly impact opioid use. Oftentimes, drugs serve as social lubricants within these contexts. Later on, we'll explore studies featuring personal stories of drug users to shed further light on this aspect.
Key literature in this area includes Jalali et al. (2020) and Cragg et al. (2019).
Community and Societal Risk Factors
As we expand our perspective, it becomes evident that differences exist between communities in terms of opioid use and addiction rates. Some communities experience high levels of opioid use, while others have much lower rates. This disparity calls for researchers and health professionals to delve into the underlying reasons behind these variations. Understanding these nuances can either satisfy your curiosity or pave the way for your potential involvement in community work focused on prevention.
Access to treatment plays a pivotal role at the community level. For instance, in the state where I reside, we face one of the highest addiction rates but struggle with limited access to treatment options. This creates a challenging situation for those seeking help. However, it's worth noting that there are also many individuals in recovery, largely due to the prevalence of addiction in our community.
Norms and culture within communities are crucial factors to consider. If drug use is normalized within a community, it can contribute to higher rates of addiction. Let's say a large employer in a community shuts down, leaving large numbers of people out of work. If drug use is the norm in that community, using drugs may not be perceived of deviant behavior in certain social groups within that community, and drug use may increase. In addition, school and work environments can play into this; whether there is an awareness of the issue and whether or not steps are being taken to address it. Prescribing patterns and prescriber perceptions and attitudes can play a role, as can the quality and level of care in a community. In fact, there are differences according to social status and race when it comes to prescriptions for pain medication.
Societal risk factors include economic conditions, supply, government programs, education, advertising, media, stigma, discrimination and prejudice, law enforcement, and policing. In terms of economic conditions, the distribution of wealth in a society can put a strain on everyone, particularly the most vulnerable. For example, during the pandemic essential workers were working while many other businesses were shut down. This created a strain on individuals and families. Some children had no access to education during the pandemic. Some teachers told me about half their students had access to the Internet, while half did not. This is not a complete list of community-level factors but the types of things to consider when examining differences around opioid use and addiction.
Gaining a deeper understanding of these community-level factors can pave the way for resource allocation further upstream. By doing so, we have the potential to prevent opioid addiction or at least address the issue at a population level. While individual interventions play a critical role and can be successful, we need to address the issue comprehensively. Individual interventions may not have the capacity to influence an entire population, especially considering the less than ideal ratios of individuals in need versus the number of available counselors, therapists, behavioral health specialists, and substance abuse and prevention experts.
Documented Variation
Looking at the documented variation in state and country-level statistics, the lowest prevalence of opioid addiction was found in Nebraska, according to the 2017 research (Hedegaard, Warner, & Minino 2017), while West Virginia had the highest rates.
It's important to note that rural areas tend to be more vulnerable to opioid addiction, and there are spikes in these regions that correlate with economic opportunities and changes. In rural areas, the level of investment in the community and the availability of industries can result in shifts in the social demographics, with people potentially leaving the community in search of better opportunities. Moreover, the concept of "deaths of despair" has emerged, referring to deaths that are attributed, either through research or perception, to the profound sense of hopelessness and lack of individual opportunities. These deaths are not caused by illness or natural causes but are driven by the absence of a positive future vision. See Dasgupta, Bletsky, and Ciccarone (2018) for further reading on this topic.
Indeed, disparities in health outcomes based on race and social status are evident across various health issues, including opioid addiction. There is a significant correlation between race and socioeconomic status, which plays a role in shaping the prevalence of addiction within different communities. Gender differences also contribute to the variations seen in opioid addiction rates. The prevalence of mental illness and physical pain can also vary from one community to another, adding further complexity to the issue. All of these factors combined serve as evidence of the intricate web of factors influencing addiction within a community.
The War on Drugs
Let's delve into the topic of the "war on drugs." This initiative was launched with the positive intention of combatting drug issues in communities across America.
The approach of the war on drugs led to increased arrests, but it did not necessarily reduce access to street drugs. Moreover, it influenced the culture, perception, and stigma surrounding drug use and addiction. The focus on punitive measures rather than preventive or supportive efforts may have contributed to the perception of drug use as a moral failing, stigmatizing individuals struggling with addiction.
Unfortunately, the war on drugs didn't fully recognize the role of trauma, both past and new traumas, that individuals experience in society. If the initiative had been framed as a war on addiction, it might have called for investment in addressing underlying community-level issues and potentially reduced the driving force behind people seeking drugs. In addition, it exacerbated the stigma around drug use.
This is not intended to prescribe specific policies or take a political stance. Instead, our focus is primarily on the research on various policies and actions related to drug use and addiction. People hold diverse attitudes and opinions about the root causes of drug use and the characteristics of drug users. These viewpoints, coupled with the considerable size of the drug industry and the prison industrial complex, all contribute to the context in which drug policies are formulated.
Significance of Root Causes
It is essential to recognize that the relationship between various factors is not linear or one-to-one based purely on availability. Simply addressing one factor, such as prescribing behavior, may not lead to the desired outcome.
A striking study caught my attention, where a 13% drop in prescriptions from 2012 to 2015 was followed by a surge in overdose rates (Dasgupta et al., 2018). This finding challenges the notion that reducing prescription rates alone can effectively combat the opioid crisis.
When access to prescription opioids decreased, some individuals may have turned to social channels to obtain drugs. This shift in behavior may have led to a greater intermixing of drugs, such as heroin, resulting in more severe health issues for those engaging in recreational use or those who have addiction.
Understanding the contributing causes behind the variations in opioid prevalence based on location and social status is important. This involves looking beyond opioids alone because addiction does not occur in isolation. A multitude of factors, such as socioeconomic conditions, mental health issues, access to treatment, and cultural norms, interact to influence addiction rates. Ignoring all these driving forces and just zeroing in on the opioids alone may not be a successful approach.
Deaths of Despair
The term "deaths of despair" was coined by researchers Case and Deaton (2015) to describe what they observed in their research. They researched people with high mortality rates from suicide, drug overdose, and related causes. The researchers delved into the mental and emotional states of these individuals and found a common thread of hopelessness and economic strain.
This is deeply tied to community-level factors. The sense of hopelessness and lack of opportunity can be associated with mental health issues and economic challenges that individuals face within their communities. Income inequality emerges as a powerful indicator of various social problems, not just in specific regions but across the globe. Researchers have consistently found links between income inequality and a range of social issues, such as decreased social trust, increased rates of teen pregnancy, dangerous adolescent behaviors, and interactions with the criminal justice system. Another key study on this topic is Ezell et al. (2022).
Micro, Meso, Macro Levels
Indeed, examining the micro, meso, and macro levels can provide valuable insights into the levels of prevention for addressing opioid addiction. At the micro-level, individual factors such as occupation and job conditions play a significant role. Certain jobs may be more prone to causing physical injuries, while others may have different rates of mortality and injury. Changes in prescribing practices can also have an impact, potentially leading to the illicit use of opioids.
At the meso-level, the focus shifts to the immediate environment of individuals. Limited recreational opportunities may lead some individuals to use opioids as an escape from their reality.
Zooming out to the macro-level, community-wide and societal factors become prominent. The level of investment or divestment in a community can have far-reaching consequences, and economic distress within these communities is often linked to higher mortality rates, particularly in rural areas. These factors can impact mental illness as well.
The interplay of micro, meso, and macro-level factors creates a framework for understanding the complex nature of opioid addiction and its connection to broader community and societal dynamics.
Levels of Prevention
Levels of prevention can be categorized into primary prevention, secondary prevention, and tertiary prevention, each addressing different aspects. Primary prevention focuses on going upstream and addressing factors at the big-picture level, far from the emergency situation. This includes community education, policy changes, and initiatives to reduce stigma surrounding addiction.
Moving on to secondary prevention, the focus shifts to more immediate interventions. This includes measures like needle exchanges, medication-assisted treatment and safe houses, and proper disposal of unused opioids.
At the tertiary level, the emphasis is on providing support and care for individuals. This involves fostering empathy and caring, introducing evidence-based interventions, establishing psychosocial support structures, and facilitating access to support groups.
Role of Stigma
Stigmatizing attitudes towards individuals with opioid addiction can be found not only in the general public but also among law enforcement, health professionals, and emergency services professionals. These negative attitudes can impact how referrals are made and how the issue is addressed, hindering access to care and support.
Health professionals working with individuals facing addiction can experience frustration, disillusionment, burnout, and irritation due to the challenges they witness. Witnessing traumatic experiences, such as domestic violence or deaths resulting from drug use, can take a toll on those in helping professions.
One aspect of stigma is the different assumptions made about prior behaviors of individuals dealing with addiction, such as promiscuity. It's important to recognize that not everyone engaging in drug use necessarily exhibits specific prior behaviors, debunking the misnomer that such behaviors are a prerequisite for addiction.
Stigma has been called the "net absence of empathy" (Ezell et al., 2021), which is an interesting perspective.
Direct Experience v. Role Playing
There is research that compares the perspectives of people who use drugs and their experiences (direct experience) and those of behavioral health professionals. Behavioral health professionals may be in a role-playing position, meaning they have to envision the experience of someone who uses drugs or has an addiction, because they do not have a direct experience with drug use themselves. These perspectives are not about any specific individual therapist but rather about broader trends observed in qualitative research comparing groups. It highlights the need to understand the perspective of people who use drugs (prescribed and illicit), and how that relates to empathy.
Behavioral health professionals often examine the causes and conditions that led to addiction in an individual, and some may have personal experience with addiction, which can be beneficial in their work. However, there may also be presumptions based on known risk factors and evidence from research. While it is important to understand the research, each individual has their own unique circumstances which may or may not align with research. While we know from research that economic conditions may drive addiction rates, an individual may not attribute their use of drugs to their economic situation. It's important to look beyond the research on risk factors to look at each person's direct experience, to find out why they are using drugs or struggling from addiction. What are they saying? What is their reasoning or explanations for their circumstances?
One factor that is sometimes downplayed is sensation-seeking, where they seek the psychic or bodily high, or the increased sensations that come with certain behaviors, in terms of relationships and sexual contact. Coping with social and environmental circumstances is another factor, where drugs may be used to facilitate social and romantic relationships.
One poignant finding from direct experiences is that drug use may not always be a premeditated decision. Many individuals do not actively seek drugs; instead, they find themselves in social circumstances where drug use becomes a part of their lives. For example, a person may start using drugs due to the influence of a romantic partner, where pressure or romantic feelings cultivate a sense of trust that can impact behavior. Drug use may also be driven by addressing physical pain.
Sociology of Empathy
From a sociological perspective, empathy challenges the notion that opioid use and addiction are solely the result of predisposition or deviant behavior. Empathy goes against the belief that "it's those kinds of people" who would be involved in opioid use or that it would be "unfathomable." Instead, understanding empathy from a sociological lens allows us to recognize the influence of social norms and circumstances on individuals' behaviors.
By building empathy, we can better comprehend the complexities of addiction and the factors that lead individuals to use opioids. This includes acknowledging the impact of trusting relationships. In a relationship where there is trust, you may be more likely to engage in riskier behaviors. You may not have interest in mountain climbing, but you may do it with a partner if it is important to them. Empathy-building is crucial for behavioral health professionals to establish a more effective therapeutic relationship and to avoid compassion fatigue and burnout.
Moreover, as attitudes among professionals start to shift through empathy and understanding, it can lead to more informed advocacy for policy changes that align with the needs and experiences of those experiencing addiction. We know racial disparities exist in terms of administering and prescribing drugs, and empathy is related to reducing these differences in treatment.
Beyond the Opioid Crisis: A Holistic Approach
Taking a holistic approach to addressing the opioid crisis involves several key steps.
There should be an expansion of funding and the scope of funding available to tackle the crisis. This funding should not be limited solely to specific interventions or programs targeting opioid users, but rather should consider the broader factors contributing to addiction.
Acknowledging and addressing social and structural determinants of opioid addiction can be done through policy changes and community organizing.
Empathy-building plays a crucial role in successful recovery. Behavioral health professionals should continue to develop their ability to understand and empathize with those facing addiction, while also addressing compassion fatigue and maintaining appropriate boundaries while still being able to understand backstories. Creating a supportive environment where seeking help is destigmatized will contribute to more individuals accessing treatment and support.
By adopting a holistic approach that combines evidence-based practices with empathy and an understanding of social determinants, we can better connect the opioid crisis to the broader context of the population being served.
Why Integrate a Sociological Perspective?
The sociological perspective is crucial when examining addiction, including opioid addiction, as it offers valuable insights into understanding the trends and complexities of this issue at the population level. Addiction is not solely an individual problem; it is deeply influenced by social and cultural factors, and the sociological perspective allows us to recognize and explain these influences.
By taking a sociological approach, we can better comprehend why certain trends in opioid use and addiction change over time, including factors related to initiation and continued use. It acknowledges the significant impact of culture, social norms, social position, geography, and disparities in shaping addiction patterns.
Understanding the social and economic conditions surrounding addiction can help guide research and inform policy development. Through sociological research, we can evaluate the effectiveness of various policies in real-time and retrospectively, allowing for adjustments and improvements in intervention strategies.
Stigma awareness is another crucial aspect addressed through the sociological perspective. By reducing stigma and recognizing contextual factors, we can move beyond seeing addiction as merely an individual choice.
The Mental Health Professional's Role
The role of mental health professionals and behavioral health workers in addressing opioid addiction is essential, and adopting a sociological perspective can further enhance their effectiveness. Understanding the individual within their social and societal context is something we do and this is validation that it is good practice.
Empathy-building and inquiring about personal factors contribute to forming a strong therapeutic relationship and gaining insights into the unique challenges of each individual. Practicing cultural humility allows professionals to set aside assumptions and approach each patient with sensitivity to their cultural background and experiences.
Providing education on non-pharmacological interventions is valuable, as it opens up alternative approaches to managing mental and emotional pain. Integrating these interventions alongside other approaches can have an impact.
Prioritizing self-care and stress management is vital for mental health professionals dealing with the demands of their work and personal lives. Stress in the workplace and society at large can take a toll on professionals. While there are interventions that need to happen on a larger scale in society and workplaces, engaging in self-care practices on an individual level can be empowering and beneficial for mental health professionals in managing their own well-being and maintaining their capacity to provide effective care to their clients.
Summary
In conclusion, mental health professionals and behavioral health workers play a crucial role in addressing opioid addiction. By integrating a sociological perspective into their practices, they can better understand the complexities of addiction, provide empathetic care, and consider the social and contextual factors that influence an individual's relationship with opioids. Prioritizing self-care further enhances their ability to support people with addiction and promote a holistic approach to addressing the opioid crisis.
References
Bolinski, R., Ellis, K., Zahnd, W. E., Walters, S., McLuckie, C., Schneider, J., Rodriguez, C., Ezell, J., Friedman, S.R., Pho, M., & Jenkins, W. D. (2019). Social norms associated with nonmedical opioid use in rural communities: a systematic review. Translational Behavioral Medicine, 9(6), 1224-1232.
Case, A., & Deaton, A. (2015). Rising morbidity and mortality in midlife among white non-Hispanic Americans in the 21st century. Proceedings of the National Academy of Sciences, 112(49), 15078-15083.
Cicero, T. J., Ellis, M. S., Surratt, H. L., & Kurtz, S. P. (2014). The changing face of heroin use in the United States: a retrospective analysis of the past 50 years. JAMA Psychiatry, 71(7), 821-826.
Cragg, A., Hau, J. P., Woo, S. A., Kitchen, S. A., Liu, C., Doyle-Waters, M. M., & Hohl, C. M. (2019). Risk factors for misuse of prescribed opioids: a systematic review and meta-analysis. Annals of Emergency Medicine, 74(5), 634-646.
Dalphonse, L., Campbell, D. A., Kerr Jr, B. J., Kerr, J. L., & Gadbois, C. (2023). More than an opioid crisis: population health and economic indicators influencing deaths of despair. Sociological Inquiry. 10.1111/soin.12546
Dasgupta, N., Beletsky, L., & Ciccarone, D. (2018). Opioid crisis: no easy fix to its social and economic determinants. American Journal of Public Health, 108(2), 182–6.
Davis, M. A., Lin, L. A., Liu, H., & Sites, B. D. (2017). Prescription opioid use among adults with mental health disorders in the United States. The Journal of the American Board of Family Medicine, 30(4), 407-417.
Drwecki, B. B., Moore, C. F., Ward, S. E., & Prkachin, K. M. (2011). Reducing racial disparities in pain treatment: The role of empathy and perspective-taking. Pain, 152(5), 1001-1006.
Dwyer-Lindgren, L. Bertozzi-Villa, A., Stubbs, R. W., Morozoff, C., Kutz, M. J., Huynh, C., Barber, R. M., Shackelford, K. A., Mackenbach, J. P., van Lenthe, F. J., Flaxman, A. D., Naghavi, M., Mokdad, A. H., & Murray, C. J. L.(2016). US county-level trends in mortality rates for major causes of death, 1980–2014. JAMA, 316(22), 2385-2401.
Ezell, J. M., Olson, B., Walters, S. M., Friedman, S. R., Ouellet, L., & Pho, M. T. (2022). A sociology of empathy and shared understandings: contextualizing beliefs and attitudes on why people use opioids. Rural Sociology, 87(3), 1053-1087.
Ezell, J. M., Ompad, D. C., & Walters, S. (2021). How urban and rural built environments influence the health attitudes and behaviors of people who use drugs. Health & Place, 69, 102578.
Fenton, J. J., Bertakis, K. D., & Franks, P. (2012). Satisfied to death: a spurious result? — reply. Archives of Internal Medicine, 172(14), 1110-1114.
Hedegaard, H., Warner, M., & Miniño, A. M. (2017). Drug overdose deaths in the United States, 1999–2015. NCHS data brief, no 273. National Center for Health Statistics.
Jalali, M. S., Botticelli, M., Hwang, R. C., Koh, H. K., & McHugh, R. K. (2020). The opioid crisis: a contextual, social-ecological framework. Health Research Policy and Systems, 18, 1-9.
Katz, J. (2017, August 10). Short answers to hard questions about the opioid crisis. The New York Times. https://www.nytimes.com/interactive/2017/08/03/upshot/opioid-drug-overdose-epidemic.html
Rigg, K. K , & Monnat, S..M. (2015). Urban vs. rural differences in prescription opioid misuse among adults in the United States: informing region-specific drug policies and interventions. International Journal of Drug Policy, 26(5), 484–491.
Ruckert, A., & Labonté, R. (2017). Health inequities in the age of austerity: the need for social protection policies. Social Science & Medicine, 187, 306-311.
Savage, S. R., Kirsh, K. L., & Passik, S. D. (2008). Challenges in using opioids to treat pain in persons with substance use disorders. Addiction Science & Clinical Practice, 4(2), 4.
Salmond, S., & Allread, V. (2019). A population health approach to America's opioid epidemic. Orthopedic Nursing, 38(2), 95.
The Joint Commission, (2019, April). Quick Safety. Drug diversion and impaired healthcare workers. Issue 48. https://www.jointcommission.org/-/media/tjc/newsletters/quick_safety_drug_diversion_final2pdf.pdf
Vitali, A., & Siemaszko, C. (2017, August 10). Trump declares opioid crisis national emergency. NBC News. https://www.nbcnews.com/storyline/americas-heroin-epidemic/trump-declares-opioid-crisis-national-emergency-n791576
Citation
Nathenson, S. (2023). The opioid crisis: A sociological perspective. Continued.com - Psychology, Article 6. Available at www.continued.com-psychology
May 25, 2023
1 CE CreditPediatric Abusive Head Trauma: Recognition, Prevention, and Long-term Impact
Alison D. Peak, LCSW, IMH-E
Editor's note: This text-based course is an edited transcript of the webinar Pediatric Abusive Head Trauma: Recognition, Prevention, and Long-term Impact, presented by Alison D. Peak, LCSW, IMH-E.
Learning Outcomes
After this course, participants will be able to:
- Examine the legislation requiring PAHT continuing education, its origins, and its intentions.
- Identify the prevalence of PAHT, warning signs, and long-term outcomes.
- Analyze effective prevention programs and their role in preventing and mitigating PAHT in communities.
Introduction
We will talk about some heavy stuff today, and I want to ensure you know I will share stories as I share content. I encourage you to slow down, recognize your thoughts and emotions, and take care of yourself as we walk through this together. My great passion is working on behalf of children from birth through age five and their caregivers, working clinically, programmatically, and systemically on behalf of little ones and those who care for them. I also want you to know that I'm a social worker. I identify deeply as a social worker and love my work. It is part of who I am and all the things that come with me. It'll be a big part of my perspective and the stories I tell today.
I also want you to know that in the process of becoming a social worker, I spent four years as a floater in an early childcare center, so I have also been in early childhood classrooms. I remember working with 15 two-year-olds simultaneously and all the pieces that come with that. I remember those kiddos who were the first ones in the door, the last ones to leave, and who often spent more time with us than they did with caregivers at home. Even in that place of having children in your physical presence for long periods, there are still questions about what happens when they leave and what the rest of their day looks like.
This course is for both social workers and early childhood educators. I'll do my best to wear both hats and keep in mind all the different stories and perspectives you bring. Before we jump in, I want you to take a moment. I'm going to guide you through a grounding activity. As I said, we're going to deal with some pretty heavy content today, so I always like to make sure that we're deeply connected to our space and place and are present as we dive into these things.
I invite you to find a comfortable space. Make sure as you sit that your bones are deeply connected to your chair and that your feet are firmly grounded. After you read the instructions, close your eyes or stare softly about six feet in front of you, whichever is best for you. You're going to take three deep breaths. As you breathe in, count to four, then hold the breath for a count of seven, then breathe out for a count of eight. Do this three times, then come back to the course.
Pediatric Abusive Head Trauma (PAHT) in Kentucky
In 2010, the Kentucky General Assembly passed a bipartisan bill requiring many disciplines to receive consistent training in pediatric abusive head trauma. That original piece of legislation is tagged as Kentucky House Bill 285. That legislation has now been morphed into state policy and can be found in various locations throughout the state code. The original legislation is tagged as Kentucky House Bill 285. At that time, the goal was to increase recognition of signs and symptoms of pediatric abusive head trauma, increase prevention efforts for pediatric abusive head trauma, and ensure that professionals who interact with young children are aware of the potential outcomes of pediatric abusive head trauma given its considerable relationship to child well-being and child abuse.
In the state of Kentucky, the following people must be trained in pediatric abusive head trauma.
- Law enforcement
- High school students
- Inmates in state penitentiaries
- Guardian ad litems (attorneys specifically for the child welfare sector)
- Prospective adoptive parents
- Childcare providers
- Pediatricians, radiologists, family practitioners, trauma physicians, and family medicine physicians
- Physician assistants and nurse practitioners
- Paramedics, medical technicians, and first responders
- Nurses
- Social workers
I think it's intriguing to think about how, as individuals get closer to years in which they are no longer children but are becoming parents, we are preparing them to know what it means to take care of littles and show up on behalf of them.
What is Pediatric Abusive Head Trauma (PAHT)?
First and foremost, what is it? Pediatric abusive head trauma describes a constellation of signs and symptoms resulting from violent shaking and impacting an infant's or small child's head. In mainstream media, this more often gets referred to as Shaken Baby Syndrome, but the medical terminology is pediatric abusive head trauma. This definition clearly states that this does not occur and is not caused by general play, falls from a couch, or other things of that nature. Pediatric abusive head trauma is one of the primary physical child abuse incidents that occur in early childhood.
PAHT in the News and Media
We first saw pediatric abusive head trauma come into the news and media in 1962. At that time, a physician named Dr. C. Henry Kempe was beginning to identify a connection between aggressive and neglectful parenting and long-term behavioral and mental health symptomology within children who were the recipients of that aggressive and neglectful parenting. Sometimes in the literature, it gets referred to as scary parenting, based on the idea that the caregiver is the source that the child is afraid of. We think about those consistent moments when caregivers are large and out of control.
As I mentioned, we don't see this constellation of pediatric abusive head trauma with somebody who fell off the couch. Also, we know that all parents get upset sometimes, and kids get yelled at. However, at the other end of the spectrum, the parent may be the person children are afraid of and cannot seek comfort from. Think about really exaggerated, aggressive behavior, including physical abuse, intense emotional abuse, and neglect. Also, keep in mind the intense interpretations of a parent about a child's intentions.
Dr. Kempe's study in 1962 began to categorize these symptoms as battered child syndrome. It was revolutionary for the early '60s to think that child abuse occurred in all types of homes and all types of environments. This was not just seen in families experiencing extreme poverty or only in families with single-caregiver homes. They saw this show up in lots of places regardless of socioeconomic status or kind of caregiving dynamics. This laid the initial foundation for child abuse laws and mandated reporting. When this study came out, the recognition of battered child syndrome prompted legislation to realize that something had to be done. They couldn't just leave things where they were. There needed to be a response to this aggressive and neglectful parenting that deeply impacted these children.
A paper published in 1972 proposed the idea that the brain, as an organ, could sustain injury from being thrown about. They categorized it as whiplash-shaken infant syndrome. It also identified a triad of symptoms observable by X-ray that may or may not accompany other signs and symptoms of abuse, including cerebral swelling and hemorrhaging. Imagine being in a car accident, busting your head open, and needing stitches. There may not be an external manifestation of what is clearly an internal injury.
In 1997, a British nanny was charged with the murder of an eight-month-old baby in relation to a series of symptoms that physicians and police called shaken baby syndrome. This case sparked a series of concerns and awareness from the greater US public about shaken baby syndrome and its potential impacts on children and child well-being. We see this evolution of language from battered child syndrome to whiplash shaken infant syndrome, to the concept of shaken baby syndrome, and, currently, pediatric abusive head trauma.
I was a child when this occurred and remember it fairly clearly because I had an infant cousin at that time. I remember my family being really cautious, more so than they had been in prior years, about who got to hold the baby and where they were standing or sitting when holding the baby. There was an increased awareness that something terrible might happen because of the increased conversations around shaken baby syndrome.
Within broader news media, there is increasing conversation about the role of investigation in child abuse reports. People are slowing down to ask, what is happening, and what is it that occurs in families when there is the experience of pediatric abusive head trauma? Current media is also highlighting that in previous years, people were quick to identify a "victim" and a "culprit" without allowing for the due diligence of an investigation that holds multiple outcomes as a possibility. It is rare to have clear evidence without proof of pediatric head trauma. It's unlikely we're going to catch it on camera. One of the things we are increasingly aware of is that some of the symptoms we begin to see in early pediatric abusive head trauma may be related to an event that occurred weeks or days prior and may not be the thing that happened most recently.
Child Well-Being
Kentucky
Kentucky ranks 37th overall in child well-being for the United States. It ranks 38th in economic well-being for children but 26th in educational well-being for children. It ranks 42nd for family and community well-being. This ranking highlights an above-average presence of alternative caregivers, such as grandparent or kinship placements, single-parent homes, and high poverty. This does not include children engaged in the state child welfare system.
Nationally
Nationally, three out of every thousand children are in foster care. On average, the US spends about $1.3 billion on foster care placements, care, and associated adoption costs every year. Child welfare is not cheap. For the nation to step in and take care of vulnerable children and families comes at a price. I live and work in Tennessee, and right now, there are nearly 30,000 children in foster care in the state of Tennessee. While it might only be three out of every thousand, that is still a significant number of kids.
Regarding the connection between child welfare and child well-being, we want to consider those placement disruptions associated with foster care or other similar arrangements are generally connected to a six-month regression in development for each placement disruption. Statistically speaking, if we have a three-year-old who's removed from their primary caregiver and placed in a foster home, that's one disruption. If that foster home says, "I cannot manage this child. They're going to have to go someplace else," and they are then placed with another foster home, that's a second disruption. Then let's say, heaven forbid, that foster home says, "Oh my goodness, I have had an elderly parent who now has an end-of-life need, and I'm going to no longer be able to foster," and that child moves again, that would be the third disruption. Some of our kiddos in child welfare can be disrupted fairly frequently. It is not uncommon that in most states, children in foster care have an average of three and a half placements in their first year in child welfare.
If a child has three placement disruptions, and we think about that from a mathematical standpoint, that would be an average regression of 18 months' worth of development. That means we are in a place in child welfare where the children in foster care often function as children much younger than their chronological age and present with some significant challenges. Some states have what can generally be referred to as privatized foster care. These states will have programs or nonprofits where parents are allowed to give temporary custody to an agency instead of their child being placed in child welfare for things like rehab stays, short-term incarceration, and homelessness that appears as though it will resolve at some terminal point. Those may not be technically foster care, but they would be very similar. Those kinds of placement disruptions become connected to that six-month regression.
Taking care of our kiddos who've already had experiences of trauma and potentially scary parenting becomes really important because the more there is disruption, the more compounded we see the impact on development and delays. When possible, children are best raised in the care of their families. When that is not possible, we look for permanency in other settings. One of the major goals of child welfare is to try to keep kids in homes and connected to families as much as possible. Awareness, prevention, and intervention opportunities around pediatric abusive head trauma reduce the likelihood of child welfare placements or duration of placements and reduce the cost of long-term out-of-home stays.
Child Welfare
Kentucky
In 2020, 66.9 per every thousand children in Kentucky were the identified minors in a child welfare investigation. Remember, I said about three out of every thousand children go into foster care, but about 67 out of every thousand have some related Child Protective Services (CPS) report. CPS is generally a division of the child welfare system. Of those roughly 67 per thousand kids who were part of a child welfare investigation, about 17 of them had a substantiated abuse finding.
A substantiated abuse finding can be defined in a couple of ways. When a child welfare report comes into the mandated reporting system, it becomes the responsibility of that part of the child welfare system to identify whether or not a report is "valid." There are lots of reasons why a report might not be valid. There are times that folks have told me that they filed a report because they saw a caregiver spank a child in a grocery store, but they didn't know the child, didn't know the caregiver and didn't have names or any information. While they called that in, at the end of the day, the child welfare system couldn't figure out who it was. There's no way to connect it to an individual or to an option to investigate further. All of those calls pretty much get screened out because there's not enough information there to do anything with them.
There are also calls that get made to child welfare that may not rise to the definition of what is considered dependent abuse or neglect. I can think of reports I have filed that did not meet that qualification. There have been times when I was very worried about a family's dynamics and very concerned that choices were unhealthy. That can be difficult to communicate. Unhealthy decision-making does not necessarily equate to unsafe and may not leave bruises or indicate that a child doesn't have a place to sleep and a roof over their head. Those can be screened out.
There are many other reasons a report may not be "substantiated." But a substantiated abuse finding means that the state agrees that there's an issue and that we need some support. Those supports can look like lots of different things, such as foster care or additional services in the home. Of those 17 per every thousand children in Kentucky with a substantiated abuse report, not all of them entered the foster care system. However, of those roughly 17 per thousand, about one per every hundred thousand was specifically a child abuse-related fatality, meaning that the abuse had been egregious enough that the child did not survive. For 2020, there were about 16,750 children in foster care across the Commonwealth. Of those, about 15% were under a year old, and about 47% of all foster care children were age five or younger.
Nationally
I also highlight that, nationally, about 16% of all children engaged in child welfare were one year or younger. Nationally, 42% of all the children in child welfare were age five or younger. Kentucky is not alone in this. Consistently across all the states, infants and young children have the highest rate of engagement with child protective services and the highest rate of removal.
It's a curious statistic to take a step back and reflect on because, most of the time, when folks think about foster care, they think about school-aged children and often think about teenagers. They may have a picture in their head of a 15-year-old who needs a place to go because things at home are so intense and difficult. While nationally, 58% of the kids in child welfare are not aged five or under, the single largest age bracket engaged in child welfare is birth to five. Most of our kids in foster care are young. Most of them are in developmental spaces where they cannot fully give words to their experience or have the kind of cognitive development to connect cause and effect. They cannot understand how they got here and where they are.
Why?
Children aged five and under are at the most risk for CPS investigation and removal because infants and young children are much more dependent on caregivers. When we think about allegations of neglect that are substantiated to removal, it may be the difference between healthy and safe. A 10-year-old can find their own Pop-Tarts. While that may not be great, and it may not be the nutritional density that we would hope for, the reality is that they're fed. Often it is because they feed themselves. A two-year-old won't do that.
They are also less verbal or nonverbal than older children, meaning they cannot be an active narrator about their experiences. I think that makes pediatricians, CPS workers, and others involved aware of what may be happening in the world of young children. Whereas, I think, for older kids, there's some expectation that they'll tell us when something is wrong.
Littles have big emotions in little bodies. As part of the developmental trajectory, even with typical developing, best-case-scenario kiddos, the number of meltdowns children have between birth and 18 continuously decreases. Even more emotional kids have emotional stability the older they get. But littles have a lot of big feelings. One of the statistics we use in ZERO TO THREE talks about how the average number of meltdowns for a two-year-old in a day is about one meltdown every 24 minutes. It is typical that about every half an hour, a two-year-old is completely melting down with all the tears and feelings. We know as kids get older, that tends to dissipate. They can better internalize their coping skills, self-regulate in those moments, and hang in there a little bit longer with all those big emotions.
Children under five are also more at risk for CPS investigation and removal because they've got first-time parents. Often, families will tend to stabilize with repeat children, and first-time parents are often overwhelmed. Babies may very well find themselves welcomed into overwhelmed caregiving systems, where there may be a parental mental illness and parental substance abuse, and grandparents who don't live close by or have their own mental health and substance abuse concerns.
Coming into those spaces, I frequently say, "All babies mean change." The most wanted and planned-for and hoped-for babies mean change and change is hard. I had a meeting this morning with a colleague, and I said, "How's your week been?" She said, "You know, four-month sleep progression plus a time change is not my favorite weekend." Even the most wanted and planned-for babies can be hard. When this may have been a baby who was not planned for or when we think about systems that are already overwhelmed with mental health concerns, low socioeconomic status, and substance abuse concerns (risk factors), welcoming a very needy, very dependent, nonverbal being into the space is often a tipping point.
Across all states, it doesn't really matter where you are; the single largest category age-wise for kids at risk of child abuse is under six weeks of life. The first six weeks of life is the most volatile time and the most likely time for an incident of physical child abuse, specifically for that physical child abuse to be pediatric abusive head trauma.
Babies
As I said before, babies mean change. Even wanted, adored, and loved babies mean change. Change can be really hard, and a new baby is a major adaptation. I think about others in my world who say, "I wanted this baby so much, and I never leave my house. I haven't seen anybody else in weeks. I wanted to apply for this promotion, but it would be more time, and I don't have it to give." Even in the place of intentionally thought-about children, there's change. When we have not had the privilege of slowing down to think about what a baby may mean, that change will be even harder. I use the word privilege intentionally because when we think about insight and reflection, there is truth about it being a privilege. Not all of us live in spaces without risk factors such as mental health concerns, substance abuse, low socioeconomic status, incarceration, legal charges, etc.
When working to survive, we don't often slow down to think and wonder what this might be like. How might it be for all of these things to be different? Because we're just trying to keep a roof over our heads and keep going. Hold in mind that babies mean change. Also, hold in mind that the process of becoming a parent is one of the most emotionally evocative life changes that occur. It's a real dynamic shift to suddenly have someone who needs you far more than you have needed other folks. In that process of being needed and needing help, becoming a parent calls back to the parent's own experience of being parented.
When we've got a parent who had their own history of early neglect, abuse, or emotional abandonment, then when there is a new baby, there is a deep remembering that, oh, I want to do all of these things for this kiddo that I did not get, and grief that they did not get those things. Or, we see parents who say, "Well, it was good enough for me. I don't know why it wasn't good enough for them." We hear that a lot, and so in the process of becoming a parent, we call back to what it was for us to be parented and make decisions from that information.
Early childhood has a certain aspect of universality that nothing else has. Out of everybody who completes this course, there will not be a piece that everybody's ever had. Not everybody will have experienced psychosis. Not everybody will have dealt with a substance abuse issue. Not everybody will have a learning disability. But every single person who accesses this material will have at one time been three. In that space of thinking about infants and young children, there is a universality that also calls us to think about what it was for us to be little and how people cared for us.
I made the caveat early on about leaning into how you are feeling and thinking. Take time to take care of yourself. Take a moment to get up and walk around the room. Find some water and come back. The reality of the parallel between our work, the children we see, and the experience of what it was to be children ourselves is closely connected. As we walk through the next part of our time together, I will tell some stories. I mentioned that I'm a social worker. What I don't know that I named quite prolifically is that my clinical specialization is in severe early childhood trauma, and a lot of that looks like physical abuse.
I always find it very important to name at this point that some of my stories can be quite intense to hear. For me, they are humans, and so I know all of their stories. I know the funny moments in addition to the sad moments. I know the things that make them great and wonderful human beings. You all will get a snapshot for the purposes of educational demonstration. Sometimes that's intense material, and I want to name that outright.
The First Six Weeks
When we think about the statistic that the first six weeks of life are the highest likelihood for an incident of physical child abuse, most often pediatric head trauma, there are a number of reasons. One is that birth can be very traumatic. Frequently, unexpected complications, surgeries, the sense of feeling out of control, or recovery can take longer than expected. All of those things can be frustrating for caregivers.
When I think specifically about labor and delivery complications, mama may be out of pocket, those complications may result in longer healing time, or it may mean that mom is sleeping or has her own physical limitations. I think about a friend of mine who ended up having an emergency C-section and, six weeks later, had to have her gallbladder removed. She didn't sit upright for about 2 1/2 months. Some limitations from unexpected complications can put increased stress on an alternate individual. Sometimes that might be whoever that second biological caregiver is. It may be support from extended family called in, a nanny, or some other type of interim childcare that was hired. That person then is going to be in the position of the primary caregiver for that tiny baby.
The other piece, when we think about the experience of the first six weeks of life, is that the body releases several hormones immediately upon giving birth. The first we'll talk about is oxytocin. Oxytocin is the hormone that tells us to love babies. I always make this joke, and I inevitably get somebody who says, that's not accurate. But brand-new newborn babies are generally not that cute. If you take a step back for a moment and think about it, they're red and slimy, and they're really squished and swollen. Babies get cute after a few weeks as they fill out and have their appropriate color. But, right after they are born, babies are not particularly cute. Again, someone will always argue with me that their newborn baby was very cute, but I will also say that I think that's the oxytocin talking.
The hormone oxytocin that's released at birth is the thing that tells us from an evolutionary, biological state that we're supposed to love for and care about babies. It is the hormone released when you see a picture of a baby, and everybody in the room goes aw. It's a collective shared experience because our brain says, "Oh, that's a thing you're supposed to take care of. That's a thing you're supposed to love." It also happens with dogs. I would say it happens with cats, but I'm not a cat person, so I don't register with that experience. So oxytocin gets released, and we have this kind of euphoria that happens with a deep biological sense to take care of this being.
The second thing that happens is that your hormones crash into a pre-pubertal state. Think about that. You go from age 30 to 13 in about 45 seconds. That can make people fairly moody. For most folks, there's a period of about two weeks of what gets referred to as the baby blues, but for some folks, it can trigger some significant mental health concerns. Both of those pieces together, the hormone release and the possibility of birth trauma and complications, can increase our risk factors and shift our stress.
The other piece is the baby themselves. Babies are not blank slates. Babies come into the world with their own personalities. With that personality, they also bring parents' perceptions of who that baby is. In the first six weeks of life, babies' primary goals are to try to get in a pattern around breathing, eating, and sleeping. That's the goal in the first six weeks, meaning we don't have a pattern in those first six weeks.
Sometimes they're sleeping a lot, not sleeping, or cluster feeding, where they eat about 20 minutes apart and then don't eat for six hours. They're just trying to figure out how to breathe and get into a pattern of being. In the first six weeks, babies often cry excessively without the ability to be soothed. In infant and early childhood mental health, we talk about the concept of being with. One of the examples we give is the process of being the caregiver to a young child, walking the floor, and having no solution. If you have been the caregiver to littles, you know what it is to be up at 2:00 AM, pacing up and down a hallway with a screaming baby, saying, "I don't know what you want. I'm still here, but I have no idea what you want." We've tried all the things we know to try. In the first six weeks, the periods of really intense crying without the ability to be soothed are much more common. Also, during that time, babies don't sleep regularly. They're not predictable and are not yet in a pattern.
That also means that caregivers don't sleep regularly. Think about caregivers who may have had a traumatic experience. Their hormones are off and may have triggered some mental health episodes. Now they have only slept for three hours in the last 24, and their baby is screaming at the top of their lungs. They don't have any paid maternity or paternity leave. They're also concerned about whether or not they're going to make rent because Mom can't go back to work because now she has all of these complications from surgery. All those factors together in the first six weeks can make for a really intense perfect storm.
It is not uncommon in early childhood that parents perceive babies as fussy. There's always the reality that parents perceive their children to be in specific ways that the rest of the world may not. I think about some of the kiddos that I work with clinically that parents will describe as difficult, and they're no more difficult than anybody else. This is not an early childhood example, but we recently had a family who was extremely frustrated and kept referring to their 14-year-old as distracted. The 14-year-old was on Snapchat and losing track of time. They weren't distracted. They were just 14-year-olds on electronics. The same is true with infants. Some families perceive their baby to be fussy and, internally, feel less successful at calming that baby or soothing the process.
We talked about the oxytocin release right after labor and delivery. Remember, this release starts the biological process of bonding that leads us to an attachment relationship. There are situations in which we know that caregivers will produce less oxytocin. These include a history of major depressive disorder, severe mood disorders, anxiety, and obsessive-compulsive spectrum disorders. By virtue of that, this immediate bonding hormone may not be as strong.
When we know that families have support in place and they've got good resources, many families navigate that and can overcome and find their way. But that's not the case for all of our families. While the body will produce oxytocin as a biochemical reward for taking care of something and loving a thing, there's also the reality that the body produces cortisol whenever we're super stressed. When we're stressed, that cortisol comes out, and it says, "Something is wrong. Something is wrong. You have to fix it." I often tell my little kids that it's our brain's fire alarm. It's the thing that beeps and tells us something might not be safe.
In that first six weeks, we're trying to find those cues, develop our patterns, and be in that place. As the baby is soothed and parents feel successful, oxytocin produces the biochemical reward that says, "You did it. See? We did it together." Babies also produce oxytocin that says, "This person can help me feel better. Everything will be okay." On the other side, when we don't feel successful in that place, our body produces cortisol because it is stressful. The crying is really intense, which overwhelms the caregiver, who often feels they aren't doing things right. This will also produce increased cortisol levels in infants, who say, something's not right, and I don't know why, but I can't get calm.
Thinking about our folks engaged in child welfare when there have been persistent incidents of physical abuse and neglect, the overproduction of cortisol long-term can have neurological implications that we can see. Children have an intense stressed time in infancy and early childhood. They are much less able to tolerate shifts and change and self-regulate. Even as they age, they become much more easily overwhelmed and stressed and much quicker to respond to lower-level stimuli. I refer to this process as the ABA of neurodevelopment. If you do a thing well and connect, you get the oxytocin reward. Your brain says, "Good job." That's the thing you should do. When we're unable to find each other and match, our brain produces cortisol, which often means we don't want to do this and want to fix this as quickly as possible. That back and forth begins to add to that place of rhythm and getting into a routine, finding our own way. The first six weeks of that kind of cue and response helps lay that foundation.
The Crying Curve
In 1991, Barr, Kenner, et al. conducted a study examining infant crying to determine what happens, what it means for babies to be fussy, and how bad it is. The study found that generally, crying peaks in intensity and frequency at about six weeks old and then decreases. That study is usually referred to as the crying curve. Now, while the study found that, generally, crying peaks at six weeks and then decreases, that crying curve looks different for all babies. Even in stable, sustainable, consistent, and predictable caregiving environments, some babies just cry more, and others don't cry as much. While they may also reach their peak at six weeks, they may not have cried as much to begin with, and then also cry even less after that six-week mark. But, pretty consistently, crying increases and peaks at about six weeks and then dissipates from there forward.
The information gained from the crying curve established some containment that the experience of "fussy" crying was, to some extent, predictable and typical. We can say that the first six weeks will be rough, but it'll get better. We can't say how much better or exactly when, but we know it decreases after the first six weeks. That gives some normalcy to this process. The National Center on Shaken Baby Syndrome used this initial information from the crying curve to develop the awareness campaign called PURPLE Crying.
PURPLE Crying
PURPLE is an acronym that stands for:
- PEAK of Crying
- Unexpected
- Resists Soothing
- Pain-Like Face
- Long Lasting
- Evening
We know there will be a peak of crying in the first six weeks, which can often be unanticipated. For example, everything seemed fine, and now they're crying for the next 45 minutes, they're not easily soothed, they appear quite distressed, and it can last a while, more commonly in the evening hours. The Period of PURPLE Crying is a period of time, so the awareness campaign hopes to emphasize that this is a typical early childhood development phase, much like biting. No one loves that, and it's not a fun phase. If you've ever been the caregiver of a kiddo who was a biter, you know we want this phase to be over quickly. It is a typical early childhood development phase that we can name and talk about. We can normalize that this event occurs in early childhood and parenting. When we name a thing, we can contain a thing. It also emphasizes that there's an end. That end may not be today. Tomorrow may only be marginally better. But the reality is that there will be an end.
Pediatric abusive head trauma most often occurs during this intense six-week crying curve of the Period of PURPLE Crying. We discussed this already, but parents often report higher-than-average stress around crying when they perceive their baby to be fussy. Whether that baby's actually crying more or less than other babies does not matter. Parents will report increased stress because they perceive their children to be fussy. Some of this can also come from a parent's background or cultural expectations of whether children should be seen and not heard. Is there an expectation that babies obey even when they're very young? By this kind of excessive perceived crying, what does that say about this baby? Is this baby going to be a problem child? Is this baby going to disrupt life as I expected it?
I have heard parents say, "See, this baby already won't listen to me. How am I supposed to parent them when they get older?" That's pretty common. Perceptions of babies begin before birth and are often connected to parents' experiences as a child and to their thoughts about being a parent. One of the things we often wonder about in this space is, who is this baby, and who is this baby to me? Again, I feel like I should asterisk here before I launch into these stories. Know this is about to be intense content.
I think about families where I saw this play out. One of the families I think about most intensely was a family seeing me for their ninth child. The eight prior had all been removed from child welfare, placed, and adopted in various dynamics. The ninth child, who was seeing me, was currently placed in foster care. The 10th baby was born during that process of services. There were many stories about the 10th baby. One time, they got to the office, brought the baby in a stroller, and I dropped into what we generally refer to as mother ease, that vocal tone you use when talking to babies. I said, "Oh, sweet girl, what's the matter?" Her mom looked at me and said, "Nothin'. She just knows when she's around people she doesn't like." This was a four-month-old baby. The four-month-old baby, I promise, did not have an objection to my personality. Her mother, however, did. This is an example of the perception of how we understand babies and what we understand their cues to be.
Here's another story about that same family. There was one time they were with me when Mom asked for a bottle. Dad pulled the bottle out of the diaper bag, shook it up, looked at it, and said, "I'm pretty sure this has gone sour." Mom said, "Ah, she'll learn to live with it," took the cap off, and fed it to her anyway. This is a moment where there is that question of how we perceive who this baby is and who this baby is to me.
Pediatric abusive head trauma occurs most often in kids under six months old. It is generally connected to a caregiver's sense of being overwhelmed, feeling out of control, and having limited support or skills to navigate these intensive periods of crying. We know that higher risk factors in other situations increase risk factors for pediatric abusive head trauma and that frequently, afterward, parents will say, "I did not know how to make it stop. I did not know what to do."
Facts and Figures
Pediatric abusive head trauma occurs in about 1,300 child abuse cases annually. It is the leading cause of child abuse-related deaths in the US. While on a case-by-case basis, it doesn't often happen, usually at the point that it is recognized, which is part of our conversation today, it is very often fatal. For those kids who survive those traumatic experiences, the associated care, rehabilitative supports, educational supports, and child welfare interventions cost the US about $13.5 billion annually.
Possible Signs and Symptoms of PAHT
Possible signs and symptoms of pediatric abusive head trauma include seizures, difficulty breathing, cerebral swelling, and an infant being unable to lift their head when previously they could. A lot of these symptoms are associated with swelling, both cerebrally and into the spinal cord. Other signs and symptoms include unequal pupils, subdural hematomas, lethargy, and decreased muscle tone. With hematomas, there are times that pediatric abusive head trauma could be associated with stroke.
PAHT and Spinal Injuries
A study from the Cleveland Clinic found that spinal injuries are an often undiagnosed component of pediatric abusive head trauma that likely occurs more often than PAHT itself. Since there's no humane way to test pediatric abusive head trauma, the study took car crash mannequins and looked at the force of impact on the spine and the brain. Of the 131 mannequins in the crash simulations, 96% met the criteria for a spinal injury, while only 22% met pediatric abusive head trauma criteria.
As a clinician, I am now much more curious about my kiddos, who I know were involved in stressful early caregiving experiences. They may not have a diagnosis of pediatric abusive head trauma or even some symptoms, but what is the likelihood of some spinal damage that may result in low muscle tone, frustration, or increased pain response? Because of this study, we know that it's highly possible and likely that roughly cared-for babies may experience neck and spinal injuries before any neurological impact or PAHT.
PAHT and Cerebral Functioning
Animal simulations of pediatric abusive head trauma have highlighted a clear connection between subdural hematomas and oxygen loss that occur during shaking or other abusive interventions. The initial cerebral impact can stop oxygen during shaking or other abusive interactions. Loss of oxygen means long-term damage to cells within the brain, which can result in a lack of weight gain, growth restriction, and ongoing respiratory concerns. It can also cause issues with your frontal cortex, which is cause and effect, working memory, reading comprehension, and other things that come much later down the developmental trajectory.
Long-Term Outcomes
Thinking about the long term, pediatric abusive head trauma can cause learning disabilities, fine and gross motor delays, speech delays, cerebral palsy, seizures, and cognitive impairments. Cerebral palsy is a cluster of symptoms that can be diagnosed from a myriad of onsets. Still, it is possible that an event of pediatric abusive head trauma could result in a cerebral palsy diagnosis.
Cerebral Damage
Our brain has three primary regions that impact our social-emotional functioning: the frontal cortex, which sits at the front of your brain, your limbic system, and your brain stem. The frontal cortex supports cause-and-effect, impulse control, and higher levels of thinking. Damage in this area will result in increased impulsivity, difficulty with self-regulation, and learning difficulties. Our limbic system supports access to words and memory. Damage in this area may result in speech delays or speech loss and concerns with long-term, short-term, and working memory. Our brain stem is responsible for heart rate, blood pressure, and body temperature. Damage to the brain stem is generally life-threatening.
Risk Factors
We've talked a lot about risk factors, including the perception of the "fussy baby." Parental mental health concerns are a huge risk factor. When parents are more stressed, they are more likely to respond aggressively when they don't feel like they can problem-solve. In addition to mental health concerns, substance abuse concerns are a risk factor. Parents recently in recovery will fall into this category of being fairly stressed and unable to access all their coping skills.
Also, factors that contribute to low oxytocin include placement with alternative caregivers, single-parent homes, and fathers/boyfriends/stepfathers in the first six weeks of life. Previously I talked about the oxytocin release that happens at birth. That is a biologically triggered response, meaning if you didn't biologically give birth to this baby, you would not have an immediate oxytocin response. When we look at non-biological caregivers, we know that their oxytocin response comes on at about six weeks of life. Euphoric flooding will occur, but it's just not at the same time because there's not a biological process there. Fathers, boyfriends, and stepfathers often end up being the "aggressor" in the first six weeks of life. For example, we may have a mama out of commission for some complication. We've got a father, boyfriend, or stepfather with their own risk factors. We don't have that biological support online yet to say, "I know you're upset, and you've been crying for 45 minutes, but you're really cute." That will increase that difficulty in single-parent homes or with alternate caregivers.
Poverty, low socioeconomic status, and low education are also risk factors. Domestic violence, another risk factor, is part of a very stressed system in which some level of aggression has become typical for navigating big feelings. That then becomes a risk factor that we're going to use that same kind of dynamic with everybody around us, including the littles.
Another risk factor is prior CPS reports. Most infants and young children with pediatric abusive head trauma are found to have evidence of other forms of maltreatment, such as bruising or broken bones. I often think about young children and finger bruises. Thinking through what you might see, you should not have four oddly spaced bruises on the upper part of your bicep. Broken bones are commonly seen in shaking, and you may see a baby with bones in various healing stages. One of the other significant pieces we think about with that CPS report is story inconsistencies.
A Case Vignette
Here's a case vignette to think through. It is a real story and is a case that I worked on. All names and major indicating features have been changed for HIPAA compliance purposes.
Bella is a 10-month-old who was referred for therapy due to excessive crying, difficulty being consoled, and extreme physical responses when visiting with her biological caregivers. Bella was removed from biological caregivers at 3 1/2 months old after EMTs were notified that Bella had stopped breathing. EMTs found Bella unconscious upon arrival, with excessive bruising to her head and face. EMTs transported her to a large, Level 1 trauma hospital, who later identified several broken bones in various stages of healing, including a femur break, a collarbone break, and a broken arm. Bella is the first child of her parents, who live in an under-resourced rural area. Upon questioning, the biological caregivers reported that Bella had been at home with a younger cousin and that a game system controller had fallen off the coffee table and hit Bella in the head.
Holding that in mind, I invite you to pause for a few moments and consider what risk factors you see. What risk factors might not be named that we might be curious about?
Mandated Reporting
In the Commonwealth of Kentucky, any person who has reason to believe a child is dependent, neglected, or abused must report this to the Cabinet, the state or local police, or the local prosecutor's office. That results in making everyone in the Commonwealth of Kentucky a mandated reporter. It's not one's single burden, but everybody's job to do it. If there is suspicion that abuse or neglect may have occurred, individuals in Kentucky are to notify the Cabinet for Health and Family Services. While we are all mandated reporters, confronting the need to make a call can often be emotionally evocative, especially if it's not something you've done before. The first one is always really hard. After 15 years, I've made a lot of CPS calls. They don't bother me anymore. But, in the beginning, they do as you think about what will happen, if it's the right call, and what comes next.
Your role as a mandated reporter is to state facts. Authorities decide what happens next. Our role as mandated reporters is never to investigate, only to state what we know. Then it is up to the folks on the other end, trained in that, to decide where to go from here. Not all reports result in CPS involvement. An overwhelming majority of reports do not result in the child's removal. Even those reports that are substantiated, most get therapy, maybe rehab, and some supportive options. A child is rarely removed and placed in foster care. When that happens, there has to be substantial evidence that that was the choice to make, usually partly because of the legal burden.
PAHT as Public Health
Figure 1. Promotion, prevention, intervention, and treatment of pediatric abusive head trauma.
We've talked a lot about pediatric abusive head trauma and the idea of medical terminology or risk factors or those pieces, but there is also the reality that it is part of public health. When we think about public health models, we're looking for promotion efforts that reach about 100% of the population. Then we look at prevention efforts that reach about 40% of people with higher risk factors and need more intensive support. About 10% of the population will need some intervention and treatment services to address a problem, not just to prevent there from being a problem.
One example of a promotion effort is this course. Another example is that Kentucky must provide some level of education to all high school students. That's 100% of the population. You're getting this information if you go to high school in Kentucky.
Protective Factors
While all families have risk factors, we also want to name that all families have protective factors. When we think about the promotion, prevention, intervention, and treatment levels, we want to leverage the places where families have protective factors and increase parenting capacities to promote positive parenting during challenges. Babies are going to cry, and it's going to be stressful. It will be 2:00 AM at a four-month sleep progression on the weekend of a time change, and those are hard days. Leaning into those protective factors and supporting that place of building positive parenting goes a long way. The protective factors include:
- Knowledge and attachment
- Knowledge of parenting through a developmental lens
- Parental resilience
- Social connections
- Concrete supports for parents
- Social and emotional competence for children
We want to build out nurturing and attachment, knowledge of parenting through a developmental lens, and parental resilience. Often mental health literature presents an expectation that people are born with an internal resilience that will unfold itself magically and that if people are "resilient," they'll figure it out on their own. We know from resilience as a broader topic that resilient people know how to navigate their resources and access what they need. Others may need help building this. Regarding parental resilience, we're talking about those parents who can step away and say, "I've been at this for 45 minutes. My time is up. It is someone else's turn." They can step out, take a deep breath, and come back in.
Social connections mean they're not alone, have somebody to call, and have concrete supports. An example is that the baby goes to Grandma's house every Tuesday. There are predictable, consistent options available to parents. We're building social and emotional competence for children. This begins by thinking through and giving even the smallest babies words like, "You are so upset. Everything feels so big right now. We're going to figure it out together."
Nurturing and attachment include supporting routines, predictability, and shared affect. Shared affect means matching affect. I think about a child we did an observation with a couple of months ago. One of the things we do is ask a parent to leave a room for a brief time so that we can watch the separation and reunion. The caregiver left the room, the child burst into tears, and the caregiver started laughing on the other side of the door. There was a fundamental disconnect in that affect. The child is deeply sad and upset, and the caregiver's affect doesn't match what is expected when seeing the child so upset.
To build the protective factor of parenting and child development knowledge, provide parenting classes and bite-sized, brief information regarding child development and developmentally appropriate behaviors. For example, you may say, "Have you ever heard of PURPLE Crying? Let's check out this website together." Remind parents of developmentally appropriate behaviors and that things like biting happen and are normal. Increase parental resilience, support stress management, frustration tolerance, and flexibility.
Social connections include things like parent cafes. Many states do parent cafes electronically through Zoom so they can be done late at night. Parents don't have to have transportation, and they don't have to leave their houses. There's flexibility, and it doesn't have to be 3:00 PM while getting somebody off the bus. Many churches host moms of preschoolers (MOPs) groups or other support groups.
Concrete supports for parents include WIC offices, Early Head Start, rental assistance, and paid parental leave. I also think about our home visiting sector, including Healthy Families, Nurse-Family Partnership, and Parents as Teachers. There is a variety of home visiting programs. Building social and emotional competence for children includes giving words to feelings and emotions. Becky Bailey's "Conscious Discipline" and the Whole Brained Child can help do this.
Promotions That Work
Let's talk about some promotions, preventions, and interventions that work. A study in Texas conducted from 2017 to 2018 worked with 63 Hispanic mothers to provide education and consultation around infant crying and crying behaviors. The study identified these mothers as Hispanic. Generally, we think about that as Latinx, so I cannot define what they mean by Hispanic. The pre/post tests found that mothers' knowledge and beliefs around infant crying had shifted significantly. Once we talked about it, gave them some education, and normalized it, we saw a change. What is curious about this study is that the pre and post-tests still revealed continued concerns that the information might not apply to their baby. That goes back to the sense of perception of who they are. Am I doing this right? Am I good enough? Is there something wrong? That internal worry, what I often refer to clinically as the heart, can persist even when our head tells us, no, we know differently now.
In Egypt, there was a study of 150 mothers who were given an educational curriculum regarding pediatric abusive head trauma and infant crying. Pre/post-tests were utilized to assess mothers' knowledge, attitudes, and beliefs about infant crying. Post-tests revealed improved knowledge, attitudes, and beliefs and improved implementation of the coping skills gained through the curriculum.
In Turkey, a randomized control trial study administered an eight-week course on skills to calm crying babies and build awareness of pediatric abusive head trauma. Post-tests were administered for the intervention and control groups. Results were statistically significantly higher in the intervention group than in the control trial group, meaning that when they compared an intervention with doing nothing, those who got an education could shift their knowledge and awareness.
Synthesizing Findings
When we think about those promotion efforts, we know education matters. When we talk to caregivers about infant and early childhood crying, we normalize what can be a really difficult experience. When we're able to provide skills to families around self-regulation, they're often able to implement those skills and successfully navigate the trying times of parenting. They can recall that education and hold onto it at 2:00 AM when they walk the floor for 45 minutes.
Preventions That Work
In Kentucky, the statewide home visiting program is called Health Access Nurturing Development Services (HANDS). It is funded by the Maternal Infant Early Childhood Home Visiting program (MIECHV), which provides federal dollars to states to provide early prevention services to at-risk families. Those MIECHV-funded opportunities have federal oversight and specific requirements around implementation and fidelity. HANDS supports first-time parents from prenatal to age three for enrollment. They will stay with a family upon enrollment until that child's third birthday. However, there is a requirement that families must face multiple risk factors. There are places in the US that do what's referred to as universal home visiting, which means everybody's got access to it regardless of socioeconomic status or risk factors. But that's pretty rare and doesn't happen often. I encourage you to look up your state's MIECHV and find out what kind of programs they provide. There are 15 or more curriculums that the federal government approves.
Other in-home nursing supports, such as Nurses for Newborns or Nurse-Family Partnerships, are prevention options that support families in prenatal to early infancy. These programs provide additional resources, in-home support, lactation consultants, and increased screening and referrals for post-partum depression or parental mental health needs. It's like having a pediatric medical home for the parents. All of them have really strong outcomes.
Interventions That Work
Look back at figure one, and you'll see the top tier is intervention. This represents ten percent of the children who have had something happen, and now we have to figure out how to repair things that are not going well. This is infant and early childhood mental health in the early childhood sector. This broad-range clinical field takes a psychodynamic perspective. It states that behaviors are rooted in survival and are recognized to have subconscious depth beyond verbal value. Infant and early childhood mental health services are heavily play-based.
Earlier I told you about the family with the four-month-old baby. In that space of rooted-in-survival, it was deeply evocative to watch that mom feed the baby a potentially soured bottle. As a mandated reporter, I had to call that into their DCS worker, but the other piece was that mama had spent many years of her life without food. She had learned that if you've got something, you eat it regardless of whether it's what you want because you don't know where your next meal will come from. Part of her was rooted in thinking; this baby would take what she gets because we may not have another option someday. The infant and early childhood mental health lens will hold that parent's experience and recognize the motivator for behavior while also being able to say, like, "We can't do that."
Interventions in the early childhood sector include child-parent psychotherapy (CPP) and parent-child interaction therapy (PCIT). CPP is evidence-based for kids as young as six weeks old. Infant-parent psychotherapy is what they're calling the perinatal version. That would work even with moms who have yet to give birth. CPP is dyadic, meaning it is caregiver- and child-focused and frequent, meaning it should happen once a week or more. The assessment phase is lengthy, and it takes a long time to get to know everybody and put all the pieces together. CPP is really intentional about its process. It is what we refer to as trauma forward, meaning that we are intentionally addressing potentially traumatic events that may have occurred.
PCIT is an intervention generally used in children two-and-a-half years old through six years old. We may have a kiddo who has had a pediatric abusive head trauma and who's now getting PCIT. That intervention is behaviorally-based, typically focused on compliance, and parent-coaching focused. It is not technically a trauma treatment but should be fairly intensive with weekly sessions. The assessment period is less, and the duration and frequency of sessions vary. Clinicians are highly trained in parent-child work.
Parent-child interaction therapy (PCIT), child-parent psychotherapy (CPP), trauma-based relational intervention (TBRI), Theraplay, and infant-parent psychotherapy are all evidence-based for kids under six years. I want you to know about them. If you're a social worker and a clinician, I encourage you to find some training because there are never enough early childhood clinicians available in any state. As early childhood educators, I encourage you to know that vocabulary to advocate for the families and kiddos you work with. I want you to know that these interventions exist and should be considered. We should be asking about these things.
Regardless of your perspective, there should be caution around any modality with young children that don't heavily involve the caregiver. There should also be caution around heavily talk-based interventions such as CBT for children under five years or where there are language delays. I am always curious how someone can treat an 18-month-old when no caregiver is involved. 18-month-olds are horrible agents of change, so we must rely heavily on caregiver involvement. Play is the language of children. Play is how they tell us about their fears, how they tell us about the wonderful things, and all the space in between. We want to look at their play and consider it pretty intensely.
Summary
Regardless of our professional role, we can offer families the following tips and skills. Take a deep breath and count to 10. Call somebody for emotional support. Many states have fussy baby lines with somebody you can call to walk you through what it is to be in the moment with a really fussy infant. Call a pediatrician. There could be a medical concern. Sometimes babies cry excessively because things hurt, so check it out and make sure that there's not a problem going on. Advise caregivers to leave babies only with trusted caregivers or those who've had a background or reference check.
As we think about the research findings and our promotion, prevention, and intervention sectors, reflect on what caregivers are going through. Considering the study in Texas, is it that parents' concern that something is "wrong" with their baby persists despite education to the contrary? What causes them to think, maybe it is me, perhaps something is wrong with us, or maybe we are not figuring it out? Hold and name that anxiety, and think through some of the skills we talked about that we might be able to share in whatever setting we're in to support caregivers to care best for their fussy babies.
Our Role in PAHT
So what's our role in pediatric abusive head trauma? First of all, our role is to talk about it. A colleague of mine often says, "Lots of things are green, but that doesn't make them all grass." Grass is a thing. The same is true here. PURPLE Crying is a thing. Lots of things can elicit tears, but this really is its own thing. It's important to remember that caring for young babies is difficult and unique for every caregiver. It's a different journey for everybody involved. Know and remind caregivers that services, resources, and supports are available.
Our role is also to report it. If you've observed concerning behavior, interactions, or signs of abuse or neglect, then we are compelled by state mandate to report it. If you're not sure, but you're worried, or something feels off or just not quite right, consult a mentor, leader, or trusted colleague.
Questions and Answers
How is pediatric head trauma diagnosed?
Generally, much like my vignette about Bella, an event occurs that then becomes presented to an ER. We generally see X-rays, CAT scans, and other types of MRIs or imaging. Within that imaging, we're going to see that subdural hematoma. We'll see cerebral swelling and an impact point that may not be obvious externally. We may not have a child who's got a laceration and stitches, but through that imaging, we will see those kinds of symptoms.
Are there any free assessment tools that social workers or early childhood providers can use to assess risk factors for head trauma?
A couple of parental stress indexes are good tools that will give you risk factors across a broad range. They look at everything from socioeconomic status to parents' caregiving dynamic. An inventory called a Life Stressor Checklist (LSC) is helpful for social workers in thinking about what are all the things that a parent comes to this parenting relationship with. It's a thorough history of parents' perception of their baby and what it means to bring it into the world.
Do you have any suggestions for resources for working with parents and families, especially those that are at risk of causing head trauma?
I spoke about the MIECHV program. I'm a huge fan of MIECHV and have had the great privilege of working with them in the Tennessee statewide MIECHV program. Different states disseminate that differently. The evidence-based home visiting sector does such an incredible job. WIC offices are generally fairly well-trained in connecting folks in early prenatal and infancy to local resources. If there's an Early Head Start in your area, I strongly suggest you connect with them. Most states demonstrate Early Head Start as home visiting, not as childcare. That means you'll have somebody going into houses, looking at things, being responsive to phone calls, and connecting with folks in those first three years.
I also am a huge proponent of Part C services under Early Intervention. Even if a child is not terribly developmentally delayed if you think there is any reason that the child might need a developmental assessment, make that Part C referral. Those folks are great to come out. Even when development is on track, they're always offering parenting support groups or options about community-based programs, and they know what's available locally.
References
A complete list of references is available in the course handout.
Citation
Peak, A. (2022). Pediatric abusive head trauma: Recognition, prevention, and long-term impact. Continued Social Work, Article 204. Available from www.continued.com/social-work
Jan 20, 2023
1.5 CE CreditsNavigating Burnout: Managing Your Own Stress While Taking Care of Others
Jenny Maenpaa, LCSW, MEd
Learning Outcomes
After this course, participants will be able to:
- Identify the physical and emotional symptoms of burnout.
- Distinguish if they are currently experiencing or have experienced burnout by asking themselves specific and measurable questions.
- List manageable coping mechanisms and self-care practices to combat burnout.
Introduction
Today's presentation is navigating burnout, managing your own stress while taking care of others during a pandemic. We keep thinking the COVID pandemic is over, but instead it feels like wave after wave. Many of us allied health providers feel as though we have been running on empty for the last two years. Some of us, including me, came from a mindset of "give until you're empty and then give some more'. It took the pandemic, when I was working seven days a week, answering every email, and taking on every new client, when I started to have the physical symptoms of burnout. I realized that I could not sustain the pace any longer. My hope is that by using my experience with burnout and running a group practice, that I can help other professionals. We are doing important work and there is no end in sight to the need for our services.
]I am a licensed clinical social worker. I have a master's in education, curriculum and instruction, and I have a graduate certificate in organizational and executive coaching. I am the founder of Forward In Heels, an intersectional feminist group therapy practice that empowers all women to stand tall and own their worth so they can light up the world. In my twenties, I was the classic overachiever, with multiple graduate degrees and fellowships. I was always looking for the next gold star to make me feel valid. I was constantly making lists and plans only to have to rewrite them when something unexpected came up, as it always does. I would go to a therapist and after three sessions, they would say, well there's nothing wrong with you, which I know now was the worst thing I could have heard. I'd think, clearly I just have to work harder. Finally, I realized that I suffer from high functioning anxiety, and that just because I'm often able to sublimate my anxious tendencies into achievements doesn't mean it is not negatively impacting me.
I created a practice that recognizes that being a badass doesn't mean you never have doubt, and that being the strong one doesn't mean you never need to be checked on. Being the one everyone always goes to for solutions doesn't mean you're never vulnerable. What makes me come alive is seeing women realize the unrealized, unlimited potential in them. When women can take care of themselves personally, their light shines through, and the best version of themselves shows up professionally.
I specialize in combining cognitive behavioral therapy and psychodynamic approaches to help stressed out, overachieving women overcome imposter syndrome and dissatisfaction. As a result, women go from chasing the brass ring to achieving sustainable happiness in every aspect of their lives. This may sound similar to how many of us chase that next thing, but what we have to recognize is that the search towards self actualization is not one that we're ever going to reach.
Pre-pandemic studies showed that two in 10 US adults experienced an episode of mental illness or chronic mental illness each year. One in 10 US adults reported symptoms of anxiety or depressive disorder from January to June 2019. These statistics are from the Kaiser Family Foundation (read the issue brief here) who does ongoing reports of the state of the health in this country. During the pandemic, about four in 10 adults in the US have reported symptoms of anxiety or depressive disorder. That is an increase from about 50 million people in 2019 to just over 100 million people in 2020. No wonder therapists have waiting lists and clients seem to multiply by the day.
Think about a time when you've been in a car and you've experienced a near miss, where you and the other driver don't actually collide. Your nervous system doesn't immediately calm down. It could take minutes or hours before your heart rate stabilizes and your breathing becomes normal again. That example - a near miss car accident - is when a short term threat appears, disappears and doesn't return. Now, realize that your body and your brain on an unconscious level have been perceiving a permanent threat for over two years due to the pandemic. Think about how that situation elevates all of the emergency response systems in your body to a new baseline. When we are no longer in a pandemic, but in an endemic (meaning that this virus will be with us always but managed by vaccines and treatments like the annual flu), we will still have a long road ahead of us. It will take a long time to change how our bodies and brains are perceiving our environments.
Fight, Flight, Freeze, Fawn, Fold
We are familiar with "fight flight freeze", and there are some more recent add-ons like "fawn or fold".
For many of us, instead of getting stuck in one response of fight, flight, or freeze, we've been cycling through them. This may sound familiar to you or your clients: You're lethargic all day, you have trouble finding motivation to do anything because nothing really seems to matter. The work keeps piling up no matter how much you do, and the laundry always needs to get done. You feel stuck on a hamster wheel. You're stuck in freeze all day, conserving energy for some imaginary future fight. Then when it's finally time for bed, you're wide awake. Your mind is racing and you can't fall asleep no matter how many sleep hygiene strategies you use. Your brain thinks it's time to fight. When you finally do fall asleep, no matter how long you sleep, you don't wake up well rested. This is because instead of letting your brain get into deep REM sleep, your flight response is keeping you closer to the surface, just in case a threat attacks in your sleep, and you might have to jump out bed and run.
You're essentially catnapping. You know how when a cat seems asleep, but you walk by and they open one eye just to make sure you're not a threat? That's what cats are supposed to do evolutionarily, but humans are not. We are supposed to get into deep REM sleep. No wonder we're burned out. When our brains are overburdened, we can't think critically and our executive functioning is compromised. When we are in fight, flight or freeze the blood rushes from our brain to our bodies - our muscles and our heart and our lungs - in case we have to fight or run. We need to think about strategies and problem-solving when we're feeling calm.
What is Burnout?
What is burnout? This word is everywhere, but let's dissect it. Before burnout is languishing, which is a fairly new phrase that has been created by Adam Grant. Grant is a researcher and public figure in the field of self-help, mental health, and self-care. Languishing refers to a state where you still have some level of energy and maybe some hope, but you feel joyless and aimless. It's the opposite of flourishing. It's a sense of stagnation and emptiness. When you're languishing, you may feel like you're muddling through your days, looking at your life through a foggy windshield. The symptoms of languishing can mimic depression, but they are externally caused by your circumstances. The next step is burnout if you don't address or recognize languishing.
Burnout is a state of emotional, mental and physical exhaustion caused by excessive and prolonged stress that can leave an individual feeling helpless, disillusioned, and exhausted. As the stress continues, you begin to lose interest and the motivation that led you to take on a specific role in the first place. Many of us got into allied health professions because we care about people and we want to make the world a better place. When we feel like we are being crushed under the weight of all of our expectations, both personal and professional, we stop remembering why went into healthcare. Jobs with higher pay and fewer hours start to look really attractive when you're burned out, as does quitting altogether.
Burnout can also lead to long term problems with your body that make you more vulnerable to illnesses like colds and flu. How does burnout affect productivity and energy? It reduces productivity and zaps your energy, leaving you feeling helpless.
Other signs of burnout include:
- Anger/irritability
- Exhaustion
- Frustration
- Impatience
- Decreased ability to be flexible with unforeseen changes
Regarding anger and irritability, it may show up as something that might have bothered you only a little bit before, bothers you a lot more when you are burned out.
Regarding exhaustion, I mentioned that when you are stressed, your body does not get the restful sleep that it needs, and is not replenished. Think of yourself like an iPhone battery. When your phone battery is depleted and you have 0% battery left, you don't expect that you will be able to continue making calls and using apps. You are the same as a battery. You cannot keep burning yourself out, going down to zero, and then expecting yourself to keep going.
Frustration and impatience are similar to anger and irritability. When you are frustrated, you don't have patience with yourself, let alone others, to keep doing things that are hard. Maybe you don't have the time tolerance to do anything longer than watch a TikTok video. These are all symptoms of burnout because your brain is attempting to conserve the energy that it needs to keep going for life. Your brain is really meant to keep you going for as long as possible. Burnout is like you're running a sprint, not a marathon.
Another sign of burnout is a decreased ability to be flexible with unforeseen changes. Many people had to reschedule vacations, weddings, family events, over and over again during the pandemic. Understandably at this point, people are done with it. They are sick of having to reschedule, only to have one more curveball thrown at them. They may not have the capacity for more unforeseen changes.
Burnout can look like distancing yourself from social activities, and from friends and family. If you're experiencing excitement about upcoming projects, feeling well rested after vacation or able to maintain your empathy and compassion, you're likely not experiencing burnout. However, that doesn't mean you might not be on your way there. Look at this holistically. Maybe you still have hope for some future project at work, but you find yourself starting it and then abandoning it after 20 minutes instead of an hour. That may be a sign that you are starting to burn out.
Burning out can also have physical symptoms like exhaustion, hair loss, and digestive issues.
Other ways that burnout can show up in yourself and others include:
- Missed deadlines
- Poor communication
- Poor conflict resolution
- Less proactive behavior
- Great Resignation
- Calling out more often
- Poorer work quality
Missed Deadlines
Burnout shows up practically in many ways including missed deadlines, and a lack of drive. Maybe things you cared about don't seem important anymore. You may have an important presentation at work and think, "Who cares if the slides are not perfect; millions of people are dead of COVID." Or, "Who cares if my kid's permission slip is late?" You see dinosaurs at a museum and you think they represent a fast-approaching dystopian future. While these examples may sound dramatic, they're the kinds of things I hear over and over again from clients. And if I'm being honest, sometimes they are part of my own internal narrative. It can be frustrating as a practitioner to sit in front of someone who is saying, "What's the point of all of this?" and to recognize that you don't have a great answer. You can't give them a simple solution because they are concerned with global issues, war, political discourse and other complex problems. That makes me feel very helpless, which as a practitioner is something that I don't often encounter because I usually have ideas and solutions for clients to try.
Poor Communication and Poor Conflict Resolution
As social workers, we have graduate degrees in human behavior. However, during these past few years, I know for me, it sometimes seems like all of my communication skills have gone out the window. I have seen some of the worst behavior in communication in Facebook groups, exclusively made up of therapists. We're all burnt out and all of those skills we spent years honing feel useless in such a time of acute layered crises. Everyone has spent the last two years in some ways alone in an echo chamber of their own thoughts. Our worlds got smaller, even if you live with people, and even if you kept working.
If you think about a day in the life previously, it included so much more social interaction. For me, I started my day getting coffee from a barista first thing in the morning, interacted with a security guard, and then with colleagues. I would come to work with a bounce in my step. During the pandemic, a lot of us were (and maybe still are) alone in a room, whether it's at home behind a computer screen or in a safe sanitized version of our old offices. Things have changed and all those intangible communications that we used to have, don't exist anymore, so everything takes on higher importance. Poor conflict resolution goes along with poor communication.
Less Proactive Behavior
A lot of people that I've worked with have big questions. They have expressed concerns such as, "Why should I save for retirement if the financial system will collapse and there will be no social security, that I have spent my life contributing to?" They are asking why they should exercise and be healthy if they followed all the rules and still got COVID. Maybe grieving family members who "followed the rules" still died. Understandably, that can lead to less proactive behavior and more reactive behavior.
The Great Resignation
My clients seemed to have one of two experiences during the pandemic. Some were laid off or furloughed. They felt that no matter how hard they worked, how highly they performed, or how they did everything right at work over the years, external forces were at play and their efforts didn't matter. They were in the same boat as colleagues who didn't work as hard. The other experience was one. where companies had more business during the pandemic. These clients began working even harder, 24/7, to keep their companies afloat. The lines were blurred between home and work. People started working on the weekend to try and get ahead because they had nothing to do in their personal lives, but the emails kept coming and the work kept coming. At the end of the year. maybe they saved their company or had record profits, but the individual received no raise and no promotion. These clients realized that no matter how hard they worked, the promise of a reward that was commensurate with the work they put in was a mirage. Regardless of which experience clients had, they came to a the same realization: it's futile to work hard and care so much about work, because much of what happens to me is outside my control.
This led to what has been referred to as the "great resignation". People left their jobs, and some people found new jobs. Some people who were asked to return to an in-person office wanted to continue working from home, and some companies have been inflexible about that. Some people are not leaving the workforce entirely, but leaving the strict corporate structure to do their own thing. This has been coined the "great reshuffle". You might see this in healthcare providers - many therapists have left community mental health centers, agencies, and hospitals to go into private practice. In private practice, they can organize their schedules around their families, and they realized they can do much of their work at home as they did during the pandemic. Other people are having realizations that life is short, and they are leaving their jobs for work that is more meaningful. While that could be a great thing, it is also a time of fear, uncertainty, and tumult for many od our clients.
Calling Out Sick / Cancelling
Another thing you might see is calling out sick more often. Clients might say, I just couldn't get up. Sometimes we do that because we can plan something restful or restorative like a planned mental health day where we get in a few doctors' appointments and then maybe work in an enjoyable activity. Other times, it's a last minute panic-induced choice of opening your eyes in the morning and thinking you just can't go to work. That is when we're reaching that point of burnout.
If you find yourself canceling with clients or being grateful when a client cancels, you might want to examine if you're reaching that point of burnout.
Poorer Work Quality
In the case of burnout, poorer work quality is not the result of being lazy or not caring. For a lot of people it's because their brain is overtaxed and they just don't have it in them to keep performing at that 100% level hour after hour, day after day. It's not that they're trying to deliver poor quality work. As a social worker, maybe you are I'm so tired, overworked, and overburdened. I need to look at my schedule and see what I can control. Maybe I can shift people around or take a longer break. Maybe I just have too many clients and I have to think about that referring out or doing something differently. If you are also managing people where all of these behaviors are showing up, it might be incredibly frustrating.
New Perspective
If you are able to view these effects as the result of the trauma responses of fight flight and freeze, could it change how you approach caring for others and for yourself? What would you do if you viewed poor work quality as a trauma response? If you've ever had an employee come to you in a crisis, did you treat them differently? If an employee disclosed a serious illness, discussed exitting a violent relationship or experienced a miscarriage, did you treat them differently while they were experiencing their crisis? Were you more understanding, more accommodating or more flexible?
What if we could take that perspective and energy and change the expectations for ourselves and the people around us? What if we zoom out and say, we need to draw the results we need from ourselves and others without criticism. We still have to get these results to our clients. We still have to design this project for our stakeholders. Both things are true- we understand that we're coming from a trauma brain and that we also still have to work towards a larger goal. What would it look like to be understanding, but not to be excusing?
Which of these symptoms have shown up for your clients in the past few years? Here are the results of the poll of attendees from the live webinar format of this course:
- 43% missed deadlines
- 57% poor communication
- 61% said poor conflict resolution
- 54% less proactive behavior
- 21% great resignation
- 25% calling out more often
- 43% poorer work quality
Self-Care Strategies
When we go back to the basis of what makes us better or worse at conflict resolution, it often starts with how we're taking care of ourselves or how we're not. What can we do at the individual level? I care very much about immediately actionable stragegies. It's important to me to start with the why, to find out what is happening and how we notice it. The next step is what we can do about it. This is the macro level of the Cognitive Behavioral Therapy (CBT) and psychodynamic approach that we take in my practice. Self-care is more important than ever because we are living through an epidemic of anxiety and depression. Self-care allows us to better cope with daily stressors, such as trying to keep up with the pace of daily life, technology loneliness, and it includes ability to unwind.
Our bodies and our minds are intricately connected. Self-care allows us to take positive steps to tend to our physical, emotional health. The practice of self-care allows individuals, families, and communities to promote health, prevent disease, maintain health and cope with illnesses alongside the support of a healthcare provider. I am sure you have seen the research that shows time and again tne of the number one predictors of health and longevity is community. The actionable strategies I will discuss today include: Thought Stopping, Box Breathing, Physical Grounding, Focus on What You Can Control, Wait 24 Hours, Positive Reframing, and Gratitude Practice.
Thought Stopping
I often hear a spiral that sounds like this: "Oh no, my boss scheduled a 15 minute meeting with me at the last minute with no context. That's never happened before. Obviously I royally messed up on the last assignment, and I'm costing the company money. You know what, I've bankrupted my company, I'm getting fired. I'm probably getting sued, too.
I'm sure many of us have heard a version of that from our clients or we recognize that type of thinking in ourselves. Thought stopping involves saying the word "stop" loudly and forcefully. You can also tie a rubber band around your wrist and snap it when you notice the thoughts start to spiral. Hearing the word "stop" (or feeling the snap) jars you, and stops that spiral in its tracks. At that point you're not going to actively resume the spiraling thoughts, because you've noticed that it's not working for you. You can start replacing those thoughts. Maybe you think, I did mess up on the last assignment, but I have boss to give me feedback so that I can correct it and do better for next time. Meeting for 15 minutes would probably not be long enough to tell me that I ruined everything and I'm getting fired and sued. And, I don't see Human Resources listed as an invite to the meeting. I'm probably not that powerful to bankrupt the company, anyway. The purpose of thought stopping is not to get too caught up in the story until we have actual information and evidence to know which direction to go. The purpose of replacing the thoughts is not to paint a rosy picture and tell yourself everything is amazing. The point is to pause and focus on the information you have without continuing the spiral.
Box Breathing or Four Square Breathing
Box breathing (also called four square breathing) is one of my favorite practices that I use, when I can't fall asleep, or I find that my heart is racing for whatever reason. It involves exhaling to account of four, holding your lungs empty for a four count, inhaling for a count of four, and holding air in your lungs for a count of four before exhaling and beginning the pattern anew.
This simple technique forces your brain to focus on one repetitive thing and to slow your breathing, which leads to a calmer nervous system and a more relaxed mind. It's basically a shortcut meditation and it can increase resilience to stress, decrease feelings of depression and increase positive feelings. You can do it almost anywhere - on the subway. in your car, at your desk. You can pair it with a literal box that you can see. If you're sitting at your desk, you can use your eyes to trace around your computer monitor while you do this and no one will notice. You can do this yourself and pretty quickly, to slow your breathing down, and then your brain will resume focus.
When I say this technique is simple, I want to clarify simple is not the same thing as easy. A plank is simple, right? You get down on the floor, put hands on the floor, and put your feet on the floor. A plank is not easy. By simple I mean the practice has one action or very few actions.
How do you encourage clients who say that they already know everything about breathing techniques? I pose the question back to the client and say, tell me what's working for you. Often, they may know what to do but they're not actually implementing it. Ask them questions; ask them to walk you through that sequence. Validation is important, but then get more information. Find out what hasn't worked, and bring it back to the client as the expert in their own self. Validate their expertise and then find out how it's working in a noncombative, non-confrontational way. Sometimes you will hear a client say, "well I haven't done it in a while or maybe I rushed through it", and that's why it's not working for them.
Physical Grounding
I'm a big fan of forcing physiological changes, although force sounds like a strong word. When we start to feel panicked, it can lead to what is described as an out of body experience of feeling disconnected. This intensifies the panic, leading to flush cheeks and feelings of dizziness and warmth. You might find that you're describing yourself as feeling heavy, disconnected or out of body. By using an external source - like drinking a glass of really cold water, splashing your face with it or holding that cold glass in your hands - you bring your body back to stasis. You're reminding your body that all of those panicky experiences are temporary and can be altered with intervention. Another physical grounding technique is sitting up straight in a chair, putting our feet on the ground, our hands on the armrest and our backs flush against the back of the chair, to remind our bodies that we are tethered to earth and that everything is tangible.
Focus on What You Can Control
Anxious feelings and panic often arise from feeling like we're out of control. We often then try to choose to control something we actually can't because we're not thinking clearly in those moments. In the early days of the pandemic, I would find myself spiraling into thoughts about the virus on a global scale, and feel despondent and hopeless about a vaccine ever being developed. I worried if I'd get to meet my niece or nephew, whether or not I'd get to see my parents again, whether or not I would get to have my wedding, and so forth. All of those thoughts give our brain something to do, but it's not the same thing as being productive.
The people who fared best focused on things that they could control, such as I can wash my hands and use sanitizer, I can wear a mask. I can go to the grocery store when it opens, I can creatively meal prep with what I have instead of going shopping again, I can think strategically about my space as it exists and use it to improve my situation. Drilling back down into what is within individual control was helpful for me and for a lot of other people.
Consistency/Routines
This is not a strategy that will go viral and be the latest TikTok sensation: Consistency and routines. Nobody likes to hear that we should go to bed and get up at the same time every day, but there's a reason routines are always recommended during times of struggle, The more consistent we can be, the more our brains can perform these routines on autopilot, which frees up our brain space to do other things that are more taxing. If you think of your brain like a computer, some programs will run in the background and some are actively working. When you have too many tabs open, what happens? Your computer overheats, processing is slow, and it shuts down. The same is true with your brain.
Hierarchy of Needs
Consider Maslow's hierarchy of needs. The basic needs at the bottom of the hierarchy are physiological: Food, shelter, sleep and clothing. Then comes safety, job security, medical care, and home safety. Next is love and belonging, friendship, and connection. Then we have esteem, mastery, achievement, recognition, and finally, self actualization. Self actualization is the pursuit of realization of a person's potential and self fulfillment; it is seeking personal growth and peak experiences. This level is the desire to accomplish everything that one can and to live up to one's fullest potential. When those bottom needs aren't met - food, shelter, sleep, clothing, safety, job, security, medical care, home safety - how could we possibly pursue higher needs? We often jump to fulfillment, achievement and potential, and we don't recognize that we're not eating right, or our sleep is erratic. Basic needs must to be taken care of before we can move on to the higher level needs.
Wait 24 Hours
This is truly one of my favorite strategies for when I'm feeling in high conflict. It was taught to me as a child back when waiting meant writing a physical letter and putting it in a drawer before sending it. When we are in conflict or we sense that we're in danger, we enter a heightened state of arousal. This has protected our species for millennia.
That's why your hair stands up when you hear things that go bump in the night, it's why you pull your hands away from a hot stove or from a boss who's been criticizing you for the past 45 minutes. This built in alarm system is called the diffuse physiological arousal system. When your body is in diffuse physiological arousal or DPA, your heart speeds up, blood flows to your gut, your kidneys slow down, and adrenaline starts to pump. Ultimately you move into the fight, flight or freeze response. Think about any time you've fired off a response via email or text in the heat of the moment. Have you ever looked back and cringed at what you wrote once the adrenaline wore off? Practice writing your response in a draft that cannot be accidentally sent. For a text, put it in your notes app or for an email, put a whole new window with no recipient attached so that there is no danger of accidentally sending it. If after 24 hours, you still feel that way, go ahead and send it, but in my experience, I have never sent the first draft. I might take things out of it and say it differently, but I can't think of a time where I've went ahead and sent that first draft.
Positive Reframing
Positive reframing is not toxic positivity. It's not pretending everything is fine when it isn't. It's also not about stopping yourself from experiencing negative or painful thoughts or emotions. Instead, it means evaluating whether or not you want to believe a thought. Based on your decision, you can decide to support yourself instead of constantly criticizing yourself. For example, rather than say "I hate my job. I hate my coworkers, I hate everything. I don't want to adult anymore", replace that with, "Things are tough right now and I'm feeling pretty disconnected from work. I wonder if I can change anything about my job, my situation, or my expectations and start to feel better." It doesn't take away from the fact that you hate your job, but it focuses on and what you can do within your control.
Gratitude Practice
This is something I love. I tried to do a gratitude practice a few years ago and I found that it was kind of a chore after a few weeks, and I was repeating things. When we express gratitude, we often do it generally such as "I'm grateful for my health." After a few days, this gets rote. Instead, I practice specific gratitude. Today I might say, "I'm grateful that I woke up today with clear lungs to open the window and breathe in the fresh spring air." Tomorrow, I may say, "I'm grateful that I woke up today with clear lungs so that I can go for a run." Gratitude for something specific keeps it fresh and novel.
These are simple practices and you could do all of them in one day, or you could do one per day, whatever works for you. What I like about these strategies is that you don't have to remember complicated things. They don't ask our clients to do really complicated things. They are simple but they're not necessarily easy.
Separation and Boundaries
We talk about boundaries, but we sometimes forget how to set them. Let's review boundaries from a few different perspectives.
Creating Physical Space
If you're continuing to work from home or you're part of a hybrid model, think about how you may need to redesign your work environment to be optimally productive without burning out. Maybe you could set up room dividers, white noise machines, noise, blocking headphones, or even use peel and stick wallpaper. When I was in my old space, which was not conducive to work from home, I put a room divider in a corner of my bedroom so that when I was facing my computer, I couldn't see my bed. I put peel and stick wallpaper behind me so that it looked like an office when I was working with clients even though I was cramped in the corner of my bedroom. It worked for me while I was in that apartment. I moved because I had the opportunity to create a different physical space.
Creating Emotional Space
Create emotional space with family or roommates. You can use timers and tell your children or family, when this timer goes off, you can come interrupt me, but not before then. You can also use nonverbal signals. I find a lot of success with colored sticky notes on the back of a laptop. A red sticky note might say, do not interrupt unless you're bleeding. A yellow sticky note might say, if it's really important, you can interrupt but I prefer that you didn't. Green says, I'm open to chatting, come interrupt me if you need. You don't have to stop what you're doing for someone to know which stage that you're in. With roommates or family it is sometimes helpful to have personal schedules. You may keep a shared Google calendar, similar to what is used that in an office setting. These solutions can be simple but really effective.
Creating Mental Space
Take breaks while you are working. I love the Pomodoro Technique, which is also called the tomato timer. This method involves working in set intervals separated by breaks, and you can vary the lengths to your preference. The way I do it is 25 minutes of work and five minutes of rest. Rest means getting up, walking away from my computer, stretching and taking the full five minutes without returning back to work. No matter if you're in the flow while working, you still stop at 25 minutes. And if you're done with your break after three minutes, you still go for five minutes. It's very effective. Build in yoga and stretching breaks. You can do Yoga with Adriene on YouTube or a 5- or 10-minute Peloton work out. You don't have to come up with your own routine - you can do a guided activity.
Take PTO time off strategically to get the most out of it. Don't wait until you get to the point of you don't want to go to work today. Plan it out - think about scheduling a day off in the middle of a week to get things done so maybe you can feel less overwhelmed.
Self-Care is Not Selfish
Self-care is not selfish. The message about self-care is that it's a reward for working ourselves to the bone, when actually self-care is mandatory for allied healthcare providers. We need self-care to ensure we don't do harm to others. When we give until we're empty and then try to give some more, we think we're being martyrs. If we are always available, always flexible with reschedules, always gracious when someone is late or a no show, it sounds like we're being caring, right? In actuality we are building exhaustion and resentment inside of ourselves.
How can we show up and be present attentive and empathetic and focused, if we're not taking care of ourselves? We could actually do permanent, irreparable harm. Balance is a word people use a lot, but they usually use it to imply perfection. Balance in yoga means the space between effort and ease. Think about your everyday life. You're never fully standing and equally distributing your weight on both legs, you lean on one side, on one leg. When that gets tired, you shift to the other leg. That's balance.
Work-life balance is not equally distributing your time everywhere. Sometimes work takes more. Sometimes home takes more, sometimes family takes more. Sometimes friends take more. Sometimes you take more from all of those areas and you don't have a lot to give. Balance is picking up the slack when the pendulum needs to swing in one direction for a while. The problem with the pandemic is that no one has the ability to give right now. As allied healthcare providers, we are often praised for how giving we are. The thing no one talks about is that we can do harm if we're trying to give from an empty vessel. My job as a therapist is to hold space, to observe and reflect, to validate and challenge and to actively listen. If I am stressed out, burned out and not nourishing myself, I can do actual harm with a thoughtless response.
We can't fix anyone's problems in one day, but if we're in a bad head space, we can exacerbate them and possibly do permanent damage. Taking care of ourselves has to be part of our ethical obligation. For that reason it has been added to the National Association of Social Workers Code of Ethics in 2021. The code was amended to include new language in the purpose section that says professional self-care is paramount for competent and ethical social work, practice, professional demands challenging workplace climates and exposure to trauma warrant that social workers maintain personal and professional health, safety and integrity. Social work organizations, agencies, and educational institutions are encouraged to promote organizational policies, practices, and materials to support social worker's self-care.
Creating Separation and Setting Boundaries - Example
To create separation and set boundaries:
- Take the onus on
- Align and join together
- Explain clearly and without apology
- Validate
To create separation and set boundaries, first I take the onus on. Then, I align myself with the client who's asking me for more than I can give. I align and join together with them using a lot of "we" language. I explain clearly, but without apology. And, I validate.
Here's my standard response when clients text me at a time that's outside of business hours, or email me to share something that's personal. I have younger clients who might share a video with me, which is very sweet, but is not what our relationship should be.
I take the onus on, and explain that I want to clarify why our policies are the way they are because I think transparency is important. I say that the reason I have specific hours and modes of communication is that I would hate it if on a Friday night they had an expectation that I would be available to respond and they contacted me expecting a response. Maybe I would be out to dinner with my family and possibly had a glass of wine at dinner. I'm aligning and joining with the client by saying I would hate that for you. I tell them that I would then have to choose between answering them, which would be unethical and not in their best interest, or ignoring them, which would make them feel rejected. I explain without apologizing. I say that it works best for everyone to know when and how to communicate so that I can be fully present for our work together, which is validation. As a practitioner in private practice, I am often seen as being available all the time so this is the boundary that I have established.
Questions and Answers
Do you have any suggestions for working back from the place of burnout?
That's one thing that I didn't have time to cover, which is what if you're already burned out? That's tough and I'm not going to pretend that we can just say, "Do this and you'll feel great". I think it starts with zooming out and taking the 30,000 foot view of your life. Break it down into domains, such as family, personal, professional, friends, health, etc. Start listing out all the ways in which you would like to live. Ask yourself what would it look like if you were actually doing those things. For example with health, I would love to work out five days a week, but let's be realistic. Is that really what you want that would make you feel best? Maybe it's three days a week for 45 minutes. Block out that time.
Make adjustments and then ask what would it look like for you to say to your family, I need 45 minutes (or maybe an hour so you can build in some buffers) three times a week. Often we don't set boundaries because we are afraid of the answer. We're afraid that the people that we love won't show that they love us enough back by doing the thing that we've asked. Then we're not telling people how to show up for us. I hear this all the time from my younger clients who are dating. They say, "I can't say that to them because then they'll break up with me". Then we have the conversation of whether they want to be with someone who can't respect their boundaries or can't listen to them.
You may do a lot for other people maybe out of a sense of obligation or because you think it's what you are supposed to do. And maybe that actually isn't the best answer for everyone involved. You may think about stepping back from a project at work, but find a solution for who can take it on. Maybe you can delegate and support a junior person in learning how to take the project and run with it. Unfortunately, coming back from burnout is specific to each individual but in general it will involve looking at the big picture and determining where you are giving without receiving reciprocity and figuring out where you can find support. Boundaries are not about rejecting people and saying "stay out". Rather, boundaries are an invitation of where you can meet and work together.
My contact information is in the slides and I'm always happy to talk with other practitioners if you want to have further conversations.
References
A complete list of references is available in the course handout.
Citation
Maenpaa, J. (2022). Navigating burnout: Managing your own stress while taking care of others. Continued Social Work, Article 161. Available from www.continued.com/social-work
Aug 25, 2022
1 CE Credit