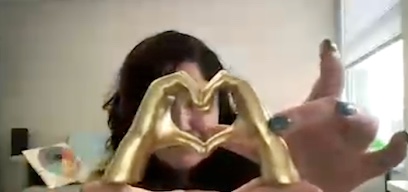Course Articles
Supporting Queer and Trans Clients in the Current Political Climate: Ethical Dilemmas and Interventions in Trying Times
Giselle Levin, PsyD
This text-based course is an edited transcript of the webinar, Supporting Queer and Trans Clients in the Current Political Climate: Ethical Dilemmas and Interventions in Trying Times, presented by Giselle Levin, PsyD on October 6, 2025.
Course Overview
This course provides a comprehensive examination of the current sociopolitical landscape affecting queer and transgender clients in the United States. It explores the profound impact of anti-transgender legislation, media rhetoric, and healthcare bans on the mental health and psychosocial functioning of gender-diverse individuals. Through the lens of minority stress theory and clinical case studies, the course outlines specific ethical dilemmas mental health providers face, including issues related to detransition, "Do-It-Yourself" (DIY) hormone therapy, and documentation safety. Ultimately, it provides clinicians with actionable interventions and advocacy strategies to support client resilience and navigate these complex challenges.
Course Information
Giselle Levin, PsyD (they/she/he), is a licensed psychologist in the state of California specializing in transgender healthcare and sex therapy. Giselle completed their doctorate at Pace University in New York, NY, and trained as a postdoctoral resident in LGBT mental health at the San Francisco VA Medical Center. They currently work as a gender specialist at the University of California San Francisco - Child and Adolescent Gender Center. Giselle is a member of UCSF’s Mind the Gap consortium of gender-affirming providers for youth and is in the process of completing their AASECT sex therapy and WPATH transgender healthcare certifications.
Disclosures
Presenter Disclosure:
Financial: Dr. Giselle Levin, PsyD received an honorarium for presenting this course. Giselle Levin has published articles on transgender healthcare, sex therapy, multiple minority stress, and adapting evidence-based interventions for marginalized populations.
Non-financial: Giselle Levin has no relevant non-financial relationships to disclose.
Content Disclosure: This learning event does not focus exclusively on any specific product or service.
Sponsor Disclosure: There is no external sponsor for this course.
Limitations/Risks
Practitioners should cultivate cultural humility and cultural competence while committing to respect the diverse ethical and legal obligations associated with different regions and cultures.
This course is geared toward mental health professionals who already possess fundamental knowledge and skills necessary to work with LGBT individuals.
Ensure that you have adequate training prior to working with the above populations; consult or refer out as necessary.
You are ethically required to refer out if you hold significant negative bias toward LGBT individuals.
Reparative/conversion therapy is unethical and harmful.
Ethics Codes
Below are links to Ethics Codes for some of the major behavioral health professions. Please ensure you always refer to your own ethical code.
AAMFT: https://www.aamft.org/Legal_Ethics/Code_of_Ethics.aspx
ACA: https://www.counseling.org/resources/aca-code-of-ethics.pdf
APA: https://www.apa.org/ethics/code
NBCC: https://nbcc.org/assets/ethics/nbcccodeofethics.pdf
NAADAC: https://www.naadac.org/code-of-ethics
NASW: https://www.socialworkers.org/About/Ethics/Code-of-Ethics/Code-of-Ethics-English
Learning Outcomes
After this course, participants will be able to:
Explain at least three reasons for increased mental health concerns in queer and trans clients, including substance use, depression, suicidality, anxiety, self-harm, and disordered eating.
Analyze ethical conflicts and considerations when working with queer and trans clients, including youth and their families.
Identify two interventions that can be used with queer and trans clients to mitigate the impact of minority stress on mental health.
Current Climate
It's Going Down in History...
The current sociopolitical environment in the United States and globally is characterized by a significant intensification of rhetoric and policy directed against transgender and gender-diverse individuals. Providers and clients alike are navigating a period that some historical records may eventually classify as a time of persecution. For example, Wikipedia currently hosts an article titled "Persecution of transgender people under the second Trump administration," highlighting the severity with which these legislative and social shifts are being documented and perceived.
The rhetoric has shifted dangerously from pathologizing transgender individuals as "mentally ill" to framing them as "actively malicious" or as "terrorists." This progression—from stigmatization to dehumanization—is a known trajectory in the persecution of marginalized groups. This dehumanization manifests in several specific ways:
Removal of Legal Rights: There are active efforts to strip transgender individuals of legal protections and recognition.
Purge of Trans Government Employees: Reports indicate threats to the careers of transgender individuals working within the federal government and military sectors.
Restriction on Passports and International Travel: New policies and proposals threaten the ability of transgender people to travel freely and safely.
Promotion of Trans Healthcare Misinformation: Major news outlets, including those traditionally viewed as progressive, have published articles that question the validity and safety of gender-affirming care, causing confusion even among supportive allies.
Attempts to Shut Down and Intimidate Providers: Clinics providing gender-affirming care (GAC) face threats to funding and legal intimidation, leading some to close or cease services.
Portrayal of Trans People as Social Threats: The framing of transgender individuals, particularly trans women, as threats to women and children contributes to a hostile social environment.
Passport Updates
The ability to obtain accurate identification documents is a critical component of safety and social functioning for transgender individuals. Recent executive orders and legal challenges have centered on the inclusion of "biological sex" on passports, threatening to reverse progress made in allowing gender markers that align with an individual's identity (such as "X" markers or allowing self-selection of "M" or "F").
While lower courts have blocked some discriminatory policies, allowing some individuals to successfully update their documents, the threat of reversal remains. For example, a transgender man who passes as cisgender male may have a driver's license with an "M" marker. If his passport were forced to revert to an "F" marker based on birth assignment, international travel would become dangerous. Presenting a passport with a female marker while appearing phenotypically male in countries with strict gender laws or hostile climates could lead to harassment, detainment, or violence.
Furthermore, these restrictions impact families. Parents of transgender children express profound fear regarding travel. A parent of a six-year-old transgender girl, who has socially transitioned and lived as a girl for years, may fear that traveling internationally could result in accusations of child abuse or the removal of the child from their custody if documents do not align with the child's presentation. These fears effectively trap families within the country, limiting their freedom of movement.
State-by-State Map for GAC Youth Bans
The legal landscape regarding gender-affirming care for youth is a patchwork of bans, restrictions, and protections that varies significantly by state. It is crucial for providers to understand that the bans targeting gender-affirming care often prohibit treatments that are deemed medically necessary by every major medical association in the country.
A critical ethical and legal distinction exists regarding these bans: the medications being banned for gender-affirming care are often legal and routinely prescribed for other conditions. For instance, puberty blockers (GnRH analogues) are the standard treatment for precocious puberty (puberty occurring too early). A child with precocious puberty can access these medications with standard parental consent. However, in states with bans, a transgender child seeking the exact same medication to pause puberty for gender-affirming purposes—a fully reversible intervention—is denied access. This highlights the discriminatory nature of the legislation, which targets the identity of the patient rather than the safety of the medication.
Image Caption: As of 2025, over 25 states have enacted bans on best practice medical care for transgender youth, with some states making it a felony crime to provide such care (Movement Advancement Project, 2025).
As illustrated in the map above, the legal status of care is volatile:
Felony Crime to Provide Care: Enacted in states such as North Dakota, Oklahoma, Idaho, Alabama, South Carolina, and Florida.
Bans to Provide Care: Enacted in over 20 states including Texas, Utah, Georgia, and North Carolina.
Protections: States like California, New York, and Minnesota have enacted "shield laws" or remain states where care is legal.
However, legality does not guarantee access. Even in "green" states, clinics may face immense pressure to stop providing care due to funding threats or harassment.
Other GAC Updates
Beyond state laws, other systemic threats are eroding access to care:
Surgical Centers: Many surgical centers have voluntarily stopped providing care to youth under 19, even in states where it remains legal for those under 18 with parental consent. This age limit is often a reaction to executive orders or fear of litigation rather than clinical guidelines.
Clinic Closures: Some major medical centers have shut down their gender health programs entirely due to political pressure, effectively abandoning patients who rely on them for hormone management and mental health support.
Funding Threats: There are ongoing threats that the Centers for Medicare & Medicaid Services (CMS) could withdraw federal funding from hospitals that provide gender-affirming care. Because most major hospitals rely on CMS funding for their general operations, this threat endangers the financial viability of entire medical institutions, forcing them to choose between financial survival and providing specialized care.
Tracking Anti-Trans Legislation
Given the rapid changes in legislation, mental health providers must stay informed about the laws in their specific jurisdiction. Reliable resources for tracking this information include:
Erin in the Morning: An independent journalist providing an "Anti-Trans Legislative Risk Assessment Map" and frequent updates.
ACLU: Tracks anti-LGBT bills moving through state legislatures.
Trans Legislation Tracker: A comprehensive database of bills impacting transgender rights.
Impact on Patients
Increase in DSM-5 Symptoms & Decrease in Psychosocial Functioning
The hostile political climate has a direct and measurable impact on the mental health of queer and transgender clients. Clinicians are observing a rise in clinical symptoms and a decline in psychosocial functioning across the lifespan, from young children to older adults.
Commonly observed symptoms include:
Depression and Anxiety: Exacerbated by chronic uncertainty and fear.
Suicidality and Self-Harm: Rates are rising as hope for a safe future diminishes.
Disordered Eating: Often linked to attempts to control body shape or suppress secondary sex characteristics.
Somatic Complaints: Many children present with gastrointestinal (GI) issues, often linked to anxiety or avoiding school bathrooms due to safety concerns.
School Refusal: Children are increasingly refusing to attend school due to bullying and lack of safe facilities.
Social and Family Conflict: The political climate has polarized families, leading to rejection or conflict where there may previously have been tolerance.
Decreased Job Performance: The stress of potential job loss (e.g., for military or government employees) impacts professional functioning.
Research supports these clinical observations. A study by Lee et al. (2024) found statistically significant increases in suicide attempts among transgender youth aged 13-17 in the first year after state-level anti-transgender laws were enacted. Furthermore, exposure to news about anti-transgender legislation is associated with higher levels of depression, anxiety, and physiological stress responses (Dhanani & Totton, 2023). Restar et al. (2024) also found that transgender adults living in states with hostile policy environments reported significantly higher symptoms of depression and anxiety compared to those in more protective states.
Understanding Increase in Symptoms
The correlation between the political landscape and mental health symptoms is driven by several factors:
Reduced Access to Care: Patients fear losing access to hormones or puberty blockers. For a young person who has socially transitioned, the prospect of undergoing an endogenous puberty that contradicts their gender identity is terrifying.
Bullying and Harassment: School environments have become increasingly hostile, with reports of physical assaults and death threats against queer students becoming more common.
Job Instability: Transgender individuals in the military or federal sectors face the potential erasure of their careers.
Media Exposure: Constant exposure to dehumanizing media rhetoric acts as a chronic stressor. While some clients may try to disconnect, many feel a need to monitor the news to assess threats to their safety ("knowing the hunter is out there").
Fears of Future Discrimination: Anxiety is often future-oriented, focused on the potential for forced detransition, family separation, or the need to flee the country.
Minority Stress Theory
Minority Stress Theory provides a framework for understanding how societal stigma translates into individual mental health outcomes. It posits that marginalized groups face chronic stress distinct from the general population.
Image Caption: The relationship between external stressors and internal psychological processes leading to adverse health outcomes (Testa et al., 2015).
As defined by Testa et al. (2015), the theory divides stressors into:
Distal Stress Factors (External): These are objective events such as discrimination, rejection, victimization, and non-affirmation of identity.
Proximal Stress Factors (Internal): These are the internal psychological processes resulting from the distal stressors, including internalized transphobia, expectations of rejection, and concealment of identity.
These factors combine to degrade mental and physical health, leading to higher rates of suicide and chronic illness.
Multiple Minority Stress
Clients often hold multiple marginalized identities, leading to compounded stress (intersectionality). Clinicians must consider the unique experiences of:
BIPOC Communities: particularly Black, Indigenous, and Latinx transgender individuals who face racism alongside transphobia.
Immigrant Communities: Undocumented families may fear that seeking gender-affirming care will draw attention to their immigration status.
Religious Minorities: Jewish and Muslim transgender individuals may face rising antisemitism or Islamophobia in addition to transphobia.
People with Disabilities: There is a high overlap between neurodivergence (specifically autism) and gender diversity. Attacks on disability rights and healthcare access further marginalize this population.
Veterans: Those relying on the VA for care face specific anxieties regarding federal policy changes.
Increase in Disordered Eating
Disordered eating in the transgender population is often functionally different from that in cisgender populations. It can be a mechanism to manage gender dysphoria by altering the body. For example, starvation may be used to stop menstruation or reduce breast tissue development, while other behaviors might be used to reduce muscle mass or curves.
Research indicates that gender-affirming hormone therapy (GAHT) is protective against disordered eating. When individuals can access hormones that align their physical body with their gender identity, the need to use maladaptive eating behaviors to control their body often decreases. Conversely, losing access to GAHT may precipitate a relapse into disordered eating. Additionally, logistical barriers, such as the lack of safe bathrooms, can lead to restrictive behaviors (avoiding food and water) to prevent the need to use the restroom during the school or work day.
The Dangers of Conversion Therapy
With the restriction of affirmative care, some political factions promote "conversion" or "reparative" therapy as an alternative. This practice attempts to change a person’s sexual orientation or gender identity.
Data from the 2015 U.S. Transgender Survey highlights the extreme danger of this approach. Youth exposed to conversion therapy had a 55% increase in the risk of attempting suicide compared to those who were not. The risk of running away from home also doubled. These risks were highest for those exposed to the practice at a young age (between 11 and 14) (Campbell & van der Meulen Rodgers, 2023).
Mental health professionals have an ethical mandate to "Do No Harm." Engaging in or referring clients to conversion therapy violates this fundamental ethical principle.
Ethical Dilemmas
The current political climate creates complex ethical dilemmas where legal mandates, client safety, and clinical best practices may conflict.
Can You Support Detransition?
Case Study: Jay Jay is an 80-year-old transfeminine nonbinary veteran who, after a lifetime of suppressing their identity, began estrogen therapy. They experienced great joy in developing a feminine body. However, due to economic factors, Jay lost their housing in San Francisco and had to move to a rural area in Oregon to afford a home. In this new environment, Jay perceived a high threat of transphobia and physical violence. Consequently, Jay decided to stop taking hormones and "detransition" to ensure their physical safety.
Ethical Consideration: Clinicians may struggle with supporting a client in stopping a treatment that clearly benefits their mental health. However, in this case, the detransition is driven by external safety concerns rather than an internal shift in identity. Research indicates that over 82% of individuals who detransition do so because of external factors like family rejection or societal stigma, rather than a realization that they are not transgender.
In this scenario, the clinician’s role is to respect the client's self-determination and safety needs. Supporting Jay involves validating the unfairness of the situation, helping them grieve the loss of their authentic expression, and prioritizing their physical safety and housing stability.
When Clients Choose to Go DIY
Case Study: Jasper Jasper is a 23-year-old trans man who wishes to take testosterone. However, he distrusts the medical establishment, fearing that a formal prescription could be tracked or cut off by future legislation. Instead, he obtains testosterone from an unregulated source ("DIY"). He wants to continue therapy to process the changes but refuses to see a medical provider for the hormones.
Ethical Consideration: This presents a dilemma regarding scope of competence and safety. A therapist cannot prescribe or manage medication. However, refusing to treat Jasper could alienate him from his only source of mental health support.
The recommended approach is harm reduction. Similar to working with a client who uses substances or engages in self-harm, the clinician does not condone the risky behavior but works to minimize danger. This involves:
Acknowledging the client's valid fears of the medical system.
Educating the client on the risks of unmonitored hormone use (e.g., polycythemia, liver strain).
Encouraging any possible safety steps (e.g., "If you won't see a doctor for a prescription, would you consider getting blood work done at a private lab to check your levels?").
Discussing safe injection practices.
Documentation & Ethics
With the Department of Justice and other entities issuing subpoenas for medical records of transgender patients, documentation has become a safety issue.
Key Questions for Clinicians:
Diagnosis: Do you include a diagnosis of Gender Dysphoria (F64.0)? While necessary for insurance coverage, it can also serve as a flag in medical records. If a client is paying out of pocket or seeking therapy for unrelated issues (e.g., anxiety), is the diagnosis necessary?
Names and Pronouns: Do you document the client's chosen name and pronouns in the official chart, or keep them in a separate "shadow" file? Documenting them validates the client but could expose them if records are seized.
Relationship Status: How are same-sex partners documented?
Intervention: Adopt a consent-forward approach. Have transparent conversations with clients about documentation. Ask: "I want to respect your identity, but I also want to protect your privacy. Here are the risks and benefits of documenting your chosen name in the official record. What do you prefer?"
Should We Delay GAC?
Case Study: Molly Molly is a 16-year-old trans girl who has socially transitioned and is desperate to start estrogen. Her therapist and doctors agree it is medically appropriate. However, her parents, while affirming of her identity, are terrified of the political climate. They want her to wait until she is 18 or until the political situation stabilizes to ensure her safety.
Ethical Consideration: This is a conflict of values: Safety vs. Authenticity. The parents prioritize physical safety; Molly prioritizes the quality of her life and her authentic development.
Intervention: The clinician's role is to facilitate a values-based conversation. For Molly, living as a boy might feel like a fate worse than the risk of discrimination. The therapist can help the family navigate this by validating the parents' fear while highlighting that denying care also carries severe risks (e.g., suicidality, worsening dysphoria). The goal is to help the family find a consensus that respects the adolescent's developing autonomy and the reality of their dysphoria.
Can Therapists Be Political?
Historically, mental health professions encouraged neutrality. However, the current context challenges this stance.
The Personal is Political: The DSM-5 itself is a sociopolitical document, not just a scientific one. The laws governing practice are political. Conceptions of mental health are shaped by societal values.
Ethical Obligation: Hope and Puckett (2024) argue that mental health providers are ethically required to engage in advocacy. Silence in the face of legislation that harms clients can be complicit.
Scope of Advocacy: Advocacy can take many forms, from voting and calling legislators to attending protests or simply creating a safe, affirming space in the therapy room.
Image Caption: Engaging in public advocacy is one form of ethical action for mental health providers (Image: G. Levin).
Recommendations
General Recommendations for Providers
Consultation: Do not make decisions in isolation. Consult with legal experts regarding state laws and with colleagues regarding ethical gray areas.
Avoid Rash Decisions: Do not preemptively strip all charts of pronouns or cease care based on rumors. Base actions on verified legal and clinical information.
Communication: Clearly communicate your stance on privacy and advocacy to your clients. Knowing their therapist is "on their team" is a vital intervention in itself.
Advocacy: Engage in advocacy appropriate to your capacity. "Be loud" where you can.
Self-Care: Vicarious trauma is real. Find your own sources of resilience and joy.
Building Rapport
Explicit Allyship: Do not assume clients know you are safe. State clearly that you are committed to LGBT rights.
Proactive Inquiry: Do not wait for the client to bring up the news. Ask: "I know there has been a lot of heavy news regarding trans rights lately. How is that impacting you?"
Knowledge: Do not place the burden of education on the client. Stay informed about major legislative updates so the client does not have to explain basic news events to you.
Recommendations for Patients: The Crash Pad
Clinicians can use the metaphor of a "Crash Pad" with clients. If the client feels they are climbing a dangerous cliff (navigating society), they cannot control whether they fall (legislation/discrimination), but they can build a crash pad to catch them.
Components of a Crash Pad:
Community: Connection with other trans people.
Supportive Individuals: A trusted cousin, friend, or therapist.
Affirming Environments: A workplace or hobby group where they are respected.
Practices: Meditation, exercise, or art that grounds them.
T4T Relationships: "Trans for Trans" relationships, where partners share a mutual understanding of the gendered experience, can be a profound source of safety and intimacy.
Image Caption: The "Crash Pad" intervention helps clients visualize and strengthen their support network.
Queer/Trans Joy as Resistance
While it is necessary to discuss trauma and safety, it is equally important to center Queer and Trans Joy. Encouraging clients to access joy—through community events, pride celebrations, or personal expression—is a form of resistance against a system that seeks their misery
Recommendations for Parents
Parents often ask how much they should share with their children about the political climate.
Assess Capacity: Consider the child's age and emotional maturity.
Assume Knowledge: Children often know more than parents realize through social media and peers.
The "Need to Know" Approach: A parent can ask, "Do you want to know what is going on in the news, or do you want me to handle it?"
Example: A father asked his 12-year-old daughter this question. She replied that she just wanted to be a kid. The father agreed to carry the burden of political awareness and advocacy so she could focus on her childhood. This is a model of protective parenting.
Using a Values-Based Approach
When clients or families feel stuck, a values clarification exercise can be powerful.
Image Caption: Mapping conflicting values helps clients understand their decision-making process in complex situations.
Clinicians can help clients identify their core values (e.g., Authenticity, Safety, Family Harmony) and acknowledge that these values may currently be in conflict. There is no single "right" answer; different clients will prioritize different values (like Jay choosing safety vs. Molly choosing authenticity).
Resources
Providing clients with concrete resources is an essential intervention.
Relocation and Logistics:
Keshet Move to Thrive: Offers interest-free loans for relocation.
Project Open Arms: Resettlement project for trans families.
Elevated Access: Volunteer pilots providing free transportation to states with legal healthcare access.
Legal and Support:
Trans Family SOS: Guiding families through legal and medical navigation.
Trevor Space: Online community for LGBTQ youth.
Human Rights Campaign: Emergency funds and resources.
References
American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Association. https://doi.org/10.1176/appi.books.9780890425787
Campbell, T., & van der Meulen Rodgers, Y. (2023). Conversion therapy, suicidality, and running away: An analysis of transgender youth in the US. Journal of Health Economics, 89, 102750. https://doi.org/10.1016/j.jhealeco.2023.102750
Dhanani, L. Y., & Totton, R. R. (2023). Have you heard the news? The effects of exposure to news about recent transgender legislation on transgender youth and young adults. Sexuality Research and Social Policy, 20(4), 1345-1359. https://doi.org/10.1007/s13178-023-00869-7
Hope, D. A., & Puckett, J. A. (2024). Bans on evidence-based care for transgender and gender diverse people present risks for clients and dilemmas for mental health providers. Cognitive and Behavioral Practice, 31(1), 15-19. https://doi.org/10.1016/j.cbpra.2023.08.001
Lee, W. Y., Hobbs, J. N., Hobaica, S., DeChants, J. P., Price, M. N., & Nath, R. (2024). State-level anti-transgender laws increase past-year suicide attempts among transgender and non-binary young people in the USA. Nature Human Behaviour, 8(11), 2096-2106. https://doi.org/10.1038/s41562-024-01928-0
Movement Advancement Project. (2025). Healthcare laws and policies: Bans on best practice medical care for transgender youth [PDF]. Movement Advancement Project. https://www.lgbtmap.org/img/maps/citations-youth-medical-care-bans.pdf
Restar, A., Layland, E. K., Hughes, L., Dusic, E., Lucas, R., Bambilla, A. J., & Kershaw, T. (2024). Antitrans policy environment and depression and anxiety symptoms in transgender and nonbinary adults. JAMA Network Open, 7(8), e2431306. https://doi.org/10.1001/jamanetworkopen.2024.31306
Testa, R. J., Habarth, J., Peta, J., Balsam, K., & Bockting, W. (2015). Development of the Gender Minority Stress and Resilience Measure. Psychology of Sexual Orientation and Gender Diversity, 2(1), 65-77. https://doi.org/10.1037/sgd0000081
Citation
Levin, G. (2025). Supporting Queer and Trans Clients in the Current Political Climate: Ethical Dilemmas and Interventions in Trying Times. Continued - Counseling, Article 118. Available at www.continued.com/counselingOct 6, 2025
1 CE CreditIntroduction to Sand Tray Therapy
Katie Fries, LCSW, MSW
Editor's Note: This text-based course is an edited transcript of the webinar, Introduction to Sand Tray Therapy, presented by Katie Fries, MSW, LCSW.
Learning Outcomes
After this course, participants will be able to:
- Identify the various categories of sand tray miniatures and the ways in which clients of various ages frequently use them in therapy.
- Explain the difference between directive and non-directive sand tray prompts and benefits to both.
- Identify the importance of being grounded in clinical theory when utilizing sand tray therapy.
Diversity, Equity, and Inclusion
Continued.com is committed to infusing the principles of diversity, equity, and inclusion (DEI) into its continuing education courses. Please ensure that your course meets the following DEI criteria:
- The course content discusses treating a range of different populations/backgrounds and how different groups may be affected.
- The course content acknowledges differences between populations.
- The course addresses limitations and where necessary, specific limitations related to DEI.
- The course uses inclusive and culturally sensitive language. The following resource may be helpful: APA Inclusive Language Guidelines.
Introduction
Thank you so much, and hello, everyone. I’m delighted to be here with you today to explore a topic that I hope you’ll find engaging and thought-provoking. We’ll dive into a therapeutic approach that offers an alternative to traditional talk therapy—something a little different but incredibly meaningful in its application.
When most people think of therapy, they often picture sitting and talking about how their day went or working through challenges verbally. While talk therapy is undoubtedly valuable and effective, today we’ll discuss sand tray therapy as an alternative or complementary approach. We’ll explore how it works, why it’s impactful, and how it can benefit different populations.
Throughout this presentation, I hope to spark your curiosity and help you envision how sand tray therapy could expand the ways we support clients in their journeys. Let’s get started!
Limitations/Risks
Sand tray therapy is a specialized therapeutic tool that can be integrated with various therapeutic approaches, depending on the modality or theoretical framework you align within your practice. For instance, sand tray therapy can be applied through a cognitive behavioral lens, a psychodynamic perspective, or even within an internal family systems framework. However, it’s not just a general technique—it is a unique and nuanced practice that requires specific training and expertise to use competently and ethically.
I want to emphasize that this webinar serves as an introductory overview. We will be scratching the surface, offering a broad introduction rather than an in-depth training or certification. If this material resonates with you and interests you in delving deeper, the resource handout accompanying this presentation includes excellent books and training opportunities. Many of the authors listed provide comprehensive clinical training in sand tray therapy. While there are numerous sand tray therapy trainings available online, I strongly encourage clinicians to pursue education, certification, and supervision to ensure their competency in this area.
Another crucial point to recognize is the cultural nuances of symbols and metaphors in sand tray therapy. The meanings of these elements can vary significantly across different cultural backgrounds. Clinicians must approach this work with cultural humility and sensitivity, as we’ll explore further during the presentation. Understanding the symbolic language of clients requires not only training but also an ongoing commitment to cultural competence.
It’s equally important to be mindful of the emotional intensity that sand tray therapy can evoke. This modality taps into a deep, symbolic, and emotional part of the brain, often engaging the limbic system, which stores some of our most profound emotional experiences. Because of its unique capacity to access these deeper layers, sand tray therapy may elicit strong emotions or memories that clients may find overwhelming.
As therapists, it is our responsibility to manage these risks effectively. This includes ensuring client safety, providing emotional regulation strategies, and offering resources to support clients as they navigate this often intense therapeutic process. Whenever we use modalities designed to access the deeper parts of a person’s emotional or neurological experience, we must be equipped to handle what emerges. This requires both training and practice in grounding techniques to help clients feel contained and supported, especially when exploring emotionally charged content.
What Is Sand Tray Therapy?
Let’s dive into what sand tray therapy is. Some of you might already be familiar with this approach, while for others, it might be entirely new. For today’s training, our focus is on the practical techniques of sand tray therapy and how it looks in a clinical session. While we won’t delve deeply into its history, I encourage you to explore it further if this topic sparks your interest. The development of sand tray therapy has a fascinating background that enriches the understanding of this modality.
One distinction I want to make clear is the difference between what we’re covering today and what is often referred to as sand play therapy, particularly from a Jungian perspective. Sand play therapy, especially in its Jungian form, involves specific training and a unique framework for interpreting symbols. This is different from the approach I’ll be presenting. It’s not a matter of one being better or worse—they are simply different modalities with unique philosophies and methods.
What I’ll be teaching today is focused on sand tray therapy, which has its techniques and applications. While both share similarities and overlap in using symbols and metaphors, the processes and theoretical underpinnings differ significantly. To illustrate, the image shown here (Figure 1) is from my practice and offers a glimpse into how I approach sand tray therapy in a clinical setting.
Figure 1. Example of a sand tray.
The image shown here is a real representation of the miniatures and sand tray we use in our practice—not a stock photo from the internet. These are actual tools we have in our office, and this particular setup was created by some of my colleagues selecting items from the shelf and placing them in the tray. It’s important to note that this isn’t a depiction of anyone’s emotional or internal experience. Nothing about this image reveals private or therapeutic content.
When you look at this picture, consider what it evokes in you. What questions or curiosities arise as you observe the items in the tray? You might notice fences, a snake, some hands, or even recognize a character like Sadness from Inside Out. There’s a toilet, a ring of fire, and other items. If I were processing a sand tray with a client, I wouldn’t direct them by saying, “Tell me about the fire” or “Explain the fences.” Instead, I’d simply say, “Tell me about this.” This allows the client to define their meaning. What appears to be a fence to us might represent a wall or a barrier to them, and what we interpret as fire could symbolize something entirely different. It’s critical to avoid projecting our interpretations onto the client’s creation.
Sand tray therapy is a form of play and creative expressive therapy that can be used across all ages. This versatility is one of its strengths. While miniatures, or figures, might resemble toys to younger children—an entirely valid perception—they are tools for expression for anyone, not just children. Sand tray therapy can be highly effective with adults, families, couples, or groups, offering unique opportunities for shared exploration and communication.
Why Sand?
When working with sand in sand tray therapy, the sand itself often becomes part of the environment being represented. For example, a client might shift the sand to one side to create the appearance of a hill or a valley. The blue base of the tray might suggest water, although it’s important to remember that clients might interpret or use these elements in entirely different ways. The flexibility and open-ended nature of the sand allows it to serve as a canvas for a client’s imagination and emotional expression.
One particularly valuable aspect of sand tray therapy is how the sand can function as a regulating resource. Many clients find comfort or soothing simply by raking their hands or objects through the sand. This tactile engagement can provide a sense of calm and grounding. For those familiar with EMDR (Eye Movement Desensitization and Reprocessing) or other therapies that incorporate the concept of a safe or calm place, this may sound familiar. The beach, for example, is a common setting that clients often associate with relaxation and comfort. Just imagining the sensations of being at the beach can elicit a deeply embodied sense of calm for many people.
Similarly, physically interacting with the sand—whether with hands, tools, or funnels—can have a calming effect, providing regulation and comfort without the need to include miniatures. This quality makes sand tray therapy not only expressive but also a resource for grounding and emotionally soothing, adaptable to clients of all ages.
The sand in sand tray therapy can function as a therapeutic tool, even beyond its metaphorical use. Simply interacting with the sand—sifting, shaping, or smoothing it—can give clients a sense of grounding and regulation. This tactile engagement creates a safe and soothing starting point for deeper therapeutic work.
Use of a Metaphor
Now, let’s turn to the central component of sand tray therapy: metaphor. Metaphors are powerful tools in therapy because they allow clients to express ideas or emotions that they may not fully understand or articulate yet. For instance, imagine a client describing their dynamic with a boss as "hard to put a finger on." They may feel triggered or dysregulated in this relationship but struggle to pinpoint why. By creating a sand tray representation of their relationship, they can choose symbols that bring clarity to their experience, enabling them to explore and articulate the complexities of their feelings in a way that words alone may not allow.
Metaphor also facilitates the expression of subconscious material just beginning to emerge into awareness. Through the selection and arrangement of miniatures, clients may unconsciously reveal patterns, dynamics, or emotions that can then be explored more consciously in therapy. This process allows deeper insights to surface gently and organically, guided by imagery and symbolism rather than direct confrontation.
Similarly, metaphor can serve as a bridge when clients are not yet ready to bring certain issues fully into consciousness. For example, a child dealing with bullying might feel too vulnerable to explicitly state, "I am being bullied." Instead, they might use a miniature dog and a larger dinosaur to represent their feelings. The client doesn’t have to verbalize the connection between the figures and their real-life situation. They might simply arrange the figures in the tray or act out a scene. The therapist can then engage with the symbolism at a safe distance, asking open-ended questions like, "I wonder what it’s like for the dog to be this size compared to the dinosaur." This approach provides the client with a safe therapeutic distance, enabling them to explore challenging emotions without feeling overwhelmed.
This distance is particularly helpful when working with younger children, who might use play to express their experiences. By engaging with the symbols and scenarios in the sand tray, the therapist can help the child process their feelings indirectly. For instance, rather than asking directly about the client’s sense of powerlessness, the therapist can explore the dynamic between the miniatures, fostering reflection and insight in a way that feels safe and non-threatening.
Metaphor also makes it possible to communicate something that is difficult to say outright. This difficulty might stem from vulnerability, emotional intensity, or lacking the right words to express the experience. The saying "a picture is worth a thousand words" aptly captures the power of sand tray therapy. A single miniature or arrangement in the tray can convey complex emotions, experiences, or relationships far more deeply than verbal language might allow.
By leveraging metaphor, sand tray therapy helps clients externalize their inner experiences, offering both a mirror and a safe container for exploration. Whether working with children, adults, or groups, this approach allows for deep, meaningful work while maintaining a sense of safety and regulation.
Frequently Used Figures By Age Group
Let’s discuss the figures frequently used in sand tray therapy across different age groups. It’s essential to start by acknowledging that clients of any age might select and use any figure to represent a wide range of feelings, experiences, or metaphors. The meaning of each figure is deeply personal, and its significance is entirely determined by the client’s unique perspective. That said, certain symbols do tend to resonate more frequently with specific age groups, which can provide helpful context for understanding the choices clients might make.
I’ll show a few examples of sand tray miniatures I have here. These miniatures can help illustrate the kinds of items that are often included in sand trays and how they might be used in practice. Take Figure 2, for example, which I describe as a wave. This is a versatile symbol that could mean different things depending on the client’s interpretation. For a child, it might represent a beach scene, a place of play, or a source of comfort. For an adolescent or adult, the wave might symbolize a feeling of being overwhelmed or a representation of life’s ebb and flow. The beauty of sand tray therapy is that the meaning of any figure, including something as seemingly straightforward as a wave, is fluid and shaped entirely by the client’s narrative.
Figure 2. A miniature of a wave.
For example, a client might use a wave figure to represent their safe and calm place, such as being at the beach—a setting that brings them comfort and relaxation. Another client might use the same figure to depict a happy memory, like a vacation involving water. Alternatively, someone could use the wave to express the feeling of being overwhelmed by stress, perhaps at work. In that scenario, they might even place a small person in the tray alongside the wave to symbolize how it feels to have the wave crashing over them, embodying their sense of being engulfed by stress or responsibility.
The key point here is that there is no right or wrong way for clients to use these symbols or miniatures. Each figure’s meaning is entirely subjective, shaped by the client’s personal experience and narrative. Hopefully, this gives you a sense of the versatility and depth of how a single sand tray miniature can explore a wide range of emotions and experiences.
2-7 Years Old
When working with young clients, the sand tray miniatures they often gravitate toward include houses, people, trees, fences, and animals. Interestingly, younger clients frequently prefer using animals over people figures, though they may still select miniatures like babies, parents, houses, or even bathroom fixtures to represent their world or emotions. These choices often reflect their way of processing experiences and expressing feelings symbolically.
One critical guideline when working with clients, especially younger ones, is to refrain from labeling the items in the tray until the client does. As we discussed earlier, instead of saying, “Tell me about the tree” or “What does the rabbit represent?” it’s better to ask something open-ended, like “Tell me about that.” For instance, while we might see a wave and naturally label it as such to the client, it might represent something entirely different, like a cloud or a nest. By allowing the client to define the miniature’s meaning, we open the door to their unique perspective and encourage them to take ownership of their narrative.
This approach helps ensure the therapeutic process stays client-centered and free from projection, allowing the client’s voice and experiences to emerge authentically.
7-11 Years Old
For clients in the 7-11 age range, it’s common to see sand trays that include elements like additional trees, farm scenes, cars, wedding figures, fire, knights, and soldiers. Of course, this isn’t a hard and fast rule, and it’s important to stress that the absence of these items in a client’s tray doesn’t indicate something is wrong or clinically significant. Sand tray work is deeply personal, and what a client includes—or doesn’t include—reflects their unique experiences and preferences.
However, for therapists who are newer to sand tray therapy or building their collection of miniatures, it can be helpful to know what items are frequently chosen by different age groups. This insight can help you ensure you have a diverse selection of miniatures that resonate with the clients you work with most often.
For example, in my practice, I’ve noticed that younger clients, particularly those under 11, tend to gravitate toward animals as one of their primary choices for depicting their world. This is not to say that older clients won’t use animals—they do—but animals are often the go-to choice for younger clients. Being aware of these tendencies can help you anticipate what miniatures might be most meaningful or engaging for your clients while still leaving plenty of room for individual expression.
Age 11 Years and Up
For clients aged 11 and up, it’s helpful to have miniatures that allow them to create towns or villages, including schools, places of worship, or other community structures. This age group often uses figures to depict experiences or environments tied to their growing sense of identity and their place in the world. Additionally, landscaping elements like trees and bridges are frequently chosen alongside more mythical or fantastical figures such as princesses, dragons, or dungeons. These symbols often represent themes of imagination, adventure, or personal challenge that resonate with this developmental stage.
Age 21-65 Years
When working with adults, generally between the ages of 21 and 65, the themes explored in sand tray therapy often shift to reflect significant life experiences and relationships. Miniatures such as houses, trees, places of worship, wedding items, and figures representing couples are frequently chosen. These symbols align with common experiences adults navigate, such as partnerships, marriage, family dynamics, or significant personal milestones. These miniatures can serve as powerful tools for clients to explore and express their emotions and experiences in a tangible and meaningful way.
It’s important to remember that these tendencies are not universal or prescriptive. Each client will bring their unique perspective, and their choices in the sand tray will reflect their individual stories and needs. However, understanding these general trends can be helpful when selecting miniatures for your collection. Having items that resonate with the life stages of the populations you work with most frequently ensures that clients have access to various symbols to construct representations of their inner experiences in ways that feel authentic and relevant to them.
Late Adulthood
When working with individuals in later adulthood, the miniatures they choose may often reflect themes of spirituality, mystery, or the unknown. These figures might symbolize existential questions or struggles related to end-of-life challenges, transitions, or reflections on legacy and meaning. The selection and arrangement of these figures can provide a profound way for clients to explore and express emotions and thoughts that may be difficult to articulate verbally.
There’s a quote that I find particularly meaningful in explaining the power of sand tray therapy:
"When the sand play figurines become symbols, they begin to express the language of our unconscious. Connection to what is unconscious in us supports emotional healing and personal development."
This beautifully captures why sand tray therapy is such an impactful tool. It allows clients to access and give shape to deeper emotional experiences, connecting them to parts of themselves that might otherwise remain unspoken or unrecognized. The figurines become conduits for healing and growth, offering a safe and creative way to engage with the complexities of their inner world.
Main Categories of Miniatures
To start building a sand tray miniature collection, it’s helpful to focus on a few main categories. One key category is environmental and structural items, such as bridges, trees, rocks, houses, and fences. These items help clients create a physical setting in their tray, allowing them to represent environments that feel meaningful to them.
Another important category is people and character figures. These should reflect the population you work with. For example, if you primarily work with children, your collection should include figures that look like children, not just adults. Similarly, if you’re working with adults, it’s important to have figures that represent adults. Beyond age, it’s essential to include diverse representations in your collection. Figures should reflect the racial, cultural, and religious backgrounds of your clients to ensure they feel seen and supported in the therapeutic process. Tailoring your collection to the demographics of your client base makes the sand tray experience more relevant and meaningful.
It’s also worth considering the level of abstraction in your miniatures. For younger clients or individuals in a more concrete developmental stage, figures that are more literal and specific may be easier to work with. These clients may find it challenging to project onto abstract miniatures. On the other hand, older clients or adults often appreciate more abstract miniatures, as these can invite deeper reflection and projection, allowing them to explore their experiences in a symbolic way.
To give a sense of what this might look like, I’ve brought some examples from my own collection. Here’s one miniature (Figure 3) depicting a person holding a new baby. This could resonate differently for each client, representing anything from a nurturing relationship to a memory or a life transition.
Figure 3. A miniature of a person holding a new baby.
If you’re working in a shared space where not everyone uses sand tray therapy, it’s important to organize your collection thoughtfully. For instance, using shelves with doors can significantly reduce visual clutter, creating a calmer environment. This is especially beneficial for clients who may feel overwhelmed by excessive visual stimulation. Having a well-organized, contained space helps maintain the functionality of the shared area while ensuring the sand tray collection is accessible and inviting for clients.
Although I can’t display my entire collection right now, I’ve brought a few examples to give you an idea of what a versatile selection of miniatures might include. For instance, Figure 4 shows a miniature of heart hands. This figure can hold a variety of meanings depending on the client’s perspective—symbolizing love, connection, or even self-compassion. Its versatility allows it to serve as a meaningful tool for clients of various ages and backgrounds.
Figure 4. A miniature of heart hands.
By curating a thoughtful and well-organized collection of miniatures, you create a therapeutic environment that supports a wide range of client needs and enhances the therapeutic experience. Again, you can see how emotionally evocative these can be.
Figure 5 shows a miniature of a person with what looks like a blindfold over their eyes and mouth. This figure can hold various meanings for different clients, as a powerful symbol to explore complex emotions or experiences.
Figure 5. A miniature of a person with a covering over their eyes and mouth.
Next is a miniature of what looks like a person looking at their phone or a screen and a child reaching up to them (Figure 6).
Figure 6. A miniature of a person looking at a screen with a child looking up at them.
And often, this miniature can be used to describe experiences like emotional neglect. There are so many different miniatures available, and if you’re interested in exploring this further, you’ll find an incredible variety of figures that can represent a wide range of experiences.
Other common categories of miniatures include transportation and machines, animals and creatures, and general objects or "things." As those familiar with play therapy may already know, it's important to emphasize that miniatures can serve as a client’s words. This applies not only to children but to people of any age. Essentially, the more miniatures you have available, the more "words" your clients have to articulate and describe their experiences in the sand tray. This diversity allows for richer and more meaningful exploration of their inner worlds.
Non-Directive Sand Tray
Now, let’s talk about an example of what a non-directive sand tray session might look like. In a non-directive approach, you might invite the client to select as many or as few miniatures as resonate with them. One way to do this is by prompting clients to choose the miniatures they are positively drawn to and those they feel negatively repelled by. For example, they might say, "I like this one," or experience a visceral reaction of dislike toward another. The invitation would then be for them to place these chosen items in the tray in any way they feel fits, followed by a processing discussion.
Another approach could involve a simple, open-ended prompt, such as, "Create your world in the tray." This can be an introductory way for the client to explore the sand tray and for you, as the therapist, to gain insight into what feels significant in their internal or external world.
For example, you might notice whether the world they create feels sparse, with few items placed, or chaotic and full of activity. These observations can inform your understanding of what might be important in the client’s life and offer a starting point for deeper exploration.
Directive Sand Tray
Examples of directive sand tray prompts might include inviting a client to create a scene about a specific topic, such as, "Create a scene about what school feels like." This prompt is versatile and adaptable for clients of all ages, whether in first grade, ninth grade, college, or graduate school. It highlights how sand tray therapy can meet the needs of individuals at different stages of life.
You could also ask clients to create a scene about a relationship, such as a romantic, family, or peer relationship. Another idea is to invite them to depict an abstract concept, like "Create a tray about what love feels like." These prompts encourage clients to explore their inner experiences in a symbolic way that can provide meaningful insights.
A particularly impactful prompt is asking clients to create a tray about their safe or calm place. This approach is especially useful in trauma therapy or when helping clients develop grounding and resourcing skills. It aligns well with polyvagal theory, a framework developed by Stephen Porges and expanded upon in clinical practice by Deb Dana. Polyvagal theory explores how different states of the nervous system impact our experiences and behaviors.
Incorporating polyvagal theory into sand tray therapy might involve asking the client to create a tray that reflects the different states of their nervous system. For example, you could have them divide the tray into three sections and depict what it feels like to be in the ventral vagal state, often associated with connection, rest, and safety. They could then create a tray about the sympathetic state, reflecting anxious, heightened, or jittery energy. Lastly, they might depict the dorsal vagal state, often characterized by low energy, withdrawal, or depressive feelings.
What the client creates and the miniatures they select to represent these states can offer a window into their experiences. This process can be a powerful way to help clients understand and articulate their internal states, fostering self-awareness and promoting regulation in a way that is both accessible and deeply personal.
Important Sand Tray Skills
Let’s talk about some foundational skills for sand tray therapy. One critical aspect is the importance of reflecting on what the client creates without interpreting or judging it. This approach might differ from other modalities that use sand or miniatures. For example, if a client places a wave-like figure in their tray, it wouldn’t be helpful to ask, "Why did you put that in there?" or to say, "That doesn’t belong—it looks like something from a beach, but everything else you’ve placed looks like animals." Similarly, just as we wouldn’t tell clients in talk therapy that their feelings or statements are incorrect, we must avoid suggesting a "right" or "wrong" way to create their tray.
We also avoid interpreting their choices or projecting meaning onto what they’ve created. For example, if they use the wave figure, we wouldn’t say, "You must have chosen a wave because you’re overwhelmed." Instead, we might ask open-ended questions like, "Tell me about what you placed over there," or, "I’m curious about this part of the tray." This leaves space for the client to share their interpretations and insights, ensuring the process remains centered on their experience.
Another key component of sand tray therapy is maintaining a mindful presence. This means staying fully attuned to the client’s verbal and nonverbal communication throughout the process—whether they’re selecting miniatures, arranging their tray, or discussing it. For example, if a client picks up a figure and hesitates, perhaps cringing or showing tears before setting it down or placing it in the tray, these actions can offer valuable insights into their emotional world. How they interact with the miniatures—whether they place them gently or quickly, keep or put them back—can hold significant meaning. If we’re distracted, perhaps looking out the window or checking a phone, we risk missing these subtle but important cues. This attunement is essential for creating a therapeutic connection and understanding the client’s experience.
Equally important is respecting the client’s ownership of the tray. The sand tray is their sacred space to depict their experience, so we should refrain from physically interacting with the tray or its contents. For example, we don’t run our hands through the sand while they’re working, as this could feel invasive or disruptive. There is an exception to this, often when working with younger children who might create what is called a "moving world." In these cases, the client may invite the therapist to participate, saying, "You be this figure, and I’ll be this one." If the client invites this kind of participation, you can use your clinical judgment to decide whether and how to engage. However, unless invited, keeping your hands out of the tray is important to preserve the client’s sense of control and safety.
By respecting the client’s autonomy, staying present, and avoiding judgment or interpretation, we can create a space where clients feel supported and free to explore their inner worlds authentically and safely.
General Helpful Questions
Here are some additional examples of questions that can be helpful to ask during a sand tray session. For example, “As you look at the tray from different angles or sides, what feelings are you noticing or sensing?” This question can be particularly powerful because creating a sand tray allows clients to externalize their internal experiences. By doing so, they may notice or access emotions that have previously felt trapped or inaccessible. This process can open up new insights, but it’s important to approach it slowly and thoughtfully. Rather than rushing to make meaning or interpret the tray, inviting the client to tune into their emotional or physical sensations while observing their creation can be equally significant.
Another useful question is, “If this picture, or the sand tray, had a title, what would the title be?” This question can help encapsulate the overarching theme of what the client has created. For example, imagine you give a child the prompt to create a tray about what school feels like. After they finish, you ask them to give their tray a title, and they respond with something like I Am Invisible, The War Zone, or Useless Place. Their chosen title can be deeply revealing, offering a clear window into their perspective or emotional experience regarding the depicted situation.
You might also ask, “Are you located in the tray anywhere?” This phrasing avoids implying that they should have placed themselves in the tray, which could create unintended pressure or expectations. Whether they include themselves or not can provide valuable clinical insight. For instance, their choice might reflect how they see themselves in the scene, whether they feel included, excluded, or even absent from the experience they are depicting.
These open-ended, non-directive questions allow clients to reflect on their creations in ways that honor their unique experiences and perspectives, fostering a deeper understanding of the emotions and meanings behind their work.
Deepening the Process
There are several ways to deepen the sand tray therapy process through thoughtful questions and prompts. One example is asking the client, “Are there any pieces in the tray with something to say to you?” This invites the client to imagine the figure or object as having a voice, potentially uncovering new layers of meaning. Similarly, you might ask, “Are there any pieces you have something to say to?” This can encourage the client to externalize their feelings and engage in a dialogue with parts of their tray.
From an internal family systems perspective, you could ask the client to notice how they feel toward a specific piece in the tray. This can help identify whether the figure represents a part of themselves or an aspect of their experience. Processing these feelings metaphorically and externally can offer a safe way to explore internal conflicts or unresolved emotions.
You might also ask, “Are there any pieces in the tray that have something to say to each other?” For instance, a wave figure might “speak” to another object it covers, saying, “I’m going to consume you,” or “I will overtake you if you don’t move.” While the meaning behind this interaction may not be immediately clear, it allows the client to explore their internal world through imagery and metaphor. This reinforces the idea that the sand tray reflects the client’s experience, with no predefined expectations about what they should create or feel.
Another way to deepen the process is by asking, “Is there anything in this scene that you want to change or shift, even just a little?” This question can be especially powerful in couples, families, or group sessions. For example, if a family creates a scene that reflects emotional disconnection, the creator of the tray might adjust the figures to depict a desire for connection by moving them closer together. Conversely, the client might move the figures further apart in cases of enmeshment or lack of individuation. Either response offers valuable insight and an opportunity for curiosity and further exploration.
In family or group settings, this process can also allow other members—whether parents, partners, or group participants—to witness aspects of someone else’s experience. By depicting it in the tray, they can observe from a safe distance rather than engaging in direct conversation, which may be challenging for various reasons. This externalized perspective can foster understanding and connection within the system while respecting the emotional needs of each individual.
Importance of Being Grounded in Theory
Let’s discuss why it’s crucial to be grounded in your clinical theory when guiding interventions or developing prompts for sand tray sessions. Your theory serves as a roadmap, helping you determine how to utilize sand tray therapy best to support your client’s specific needs and experiences. Here’s an example to illustrate this point: imagine working with a 16-year-old girl navigating her first breakup. She is isolating, experiencing depression, and her parents dismiss her feelings as dramatic. While this scenario is fictional, it’s a relatable situation many therapists encounter.
Understanding your clinical theory will shape how you approach this case. For instance, if you work from an internal family systems (IFS) perspective, which emphasizes exploring parts of the self, you might invite the client to create a tray representing the different parts of herself that are responding to the breakup. You could then guide her in exploring these parts by asking, “How do you feel toward this part?” or “Does this part have anything it wants to say to the others?” The use of miniatures can facilitate the externalization and exploration of her internal system, making abstract concepts more tangible.
If your approach is cognitive behavioral therapy (CBT), which focuses on the interplay of thoughts, emotions, and behaviors, you might use prompts to explore how her cognitions influence her emotional experience. For example, you could ask her to create a tray depicting how she feels when she has the thought, It’s all my fault. Then, you might invite her to create another tray based on the thought, I did the best I could. This process could help her identify and understand the emotional shifts that occur when her perspective changes.
For therapists using family systems theory, which examines how family dynamics shape individual experiences, a prompt could be, “Create a tray about what love, emotions, or struggle looks like in your family.” This exercise might reveal dynamics that contribute to her current emotional state, providing valuable insights for intervention.
If you work from a dialectical behavior therapy (DBT) framework, you might incorporate the concept of the “wise mind,” which integrates the emotional and logical minds. A helpful prompt could be, “Make a tray about what your wise mind says about the breakup.” Alternatively, you could explore her inner conflict by asking her to create separate trays for how her emotional and logical minds view the breakup, facilitating a discussion about how these states interact and influence her decision-making.
These examples highlight how grounding your sand tray interventions in your clinical theory ensures that the process aligns with your therapeutic goals. Your theory not only guides the prompts you offer but also informs what you observe and assess in the client’s creation, deepening the therapeutic experience and tailoring it to the client’s unique needs.
Main Things to Track During a Sand Therapy Session
Some main things to track during a sand tray therapy session are critical for understanding the therapeutic process and can also help guide parents or caregivers when observing their child’s sand tray creation. Observations can be made on multiple levels, including the client, the therapist, and interaction.
First, we want to observe the client's engagement with the metaphorical process. For instance, is the client creating the sand tray quickly, or are they taking their time? Do they frequently look at you for approval or validation? Are they asking questions like, “Did I do this right?” Does their selection process seem hesitant, with miniatures being picked up and put back repeatedly? What emotions or states are visible in their nonverbal expressions during the different stages of the session—selecting miniatures, placing them in the tray, and processing the creation? Do they seem calm, present, anxious, or perhaps dissociated? These behaviors provide valuable insights into how the client is experiencing the process and what it might reveal about their internal world.
Equally important are observations about yourself as the therapist. You should ask yourself, “What is occurring in me as I witness this tray?” Are you feeling calm and grounded, or do you notice anxiety, frustration, or worry? For example, are you wondering if you gave the right prompt or feeling overwhelmed by how the client engages with the materials, such as taking a long time to choose or dumping many miniatures into the tray? These reactions are part of countertransference, which, as in talk therapy, can provide important clinical information. While sharing these reactions with the client may not always be appropriate, they are crucial to track and reflect on as part of the therapeutic process.
Another key element to observe is your communication through presence. Ask yourself, “Am I fully present and attuned to this client?” Your presence is a powerful therapeutic tool, and clients should be able to feel your care, empathy, attunement, focus, and responsiveness. This is essential because, as clients create their tray, they are externalizing and exploring deeply personal aspects of their experience. The process is significant whether they are approaching this from a left-brain perspective—choosing a wave to explicitly symbolize overwhelm—or from a right-brain, intuitive perspective, where they are unconsciously drawn to the wave without fully understanding why.
Recognizing the depth of what is being communicated through the tray, both verbally and nonverbally, underscores the importance of maintaining a grounded, attentive, and empathetic presence. Creating a sand tray is not merely about arranging objects; it is a form of expressing and processing profound emotional and experiential truths. Just as in talk therapy, being attuned to all levels of communication ensures that the client feels supported and understood as they engage in this deeply personal work.
Common Fears of New Sand Tray Therapists
Let’s talk about some of the common fears that new sand tray therapists may experience as they consider incorporating this modality into their practice. These concerns are normal and worth exploring to build confidence and normalize the process.
One of the most common fears is the thought, This is expensive. Many therapists worry about the cost of building a large collection of miniatures. While it’s true that miniatures can add up, there are creative and cost-effective ways to start a collection. Thrift stores, garage sales, and estate sales often have unique and evocative items at a fraction of the cost. For instance, I once found a set of Winnie the Pooh miniatures at a garage sale, which was a wonderful addition. These characters—Tigger, Piglet, Eeyore, and others—can represent various emotional experiences. A client might select one of these figures, not necessarily to identify with its emotional qualities but perhaps because it evokes a personal memory, such as a connection to childhood.
Another option is to create miniatures using clay, 3D printers, or resin. Many therapists also use online resources to purchase starter packs of miniatures, which can provide a good foundation. Building a robust collection takes time, but it doesn’t have to be prohibitively expensive.
Another common fear is that I won’t have what my client needs. Therapists may worry that a client will require a specific miniature, like a rain cloud, and its absence will disrupt the session. It’s important to remember that no collection will ever include every possible item, and that’s okay. Clients are remarkably creative and resourceful. If a client wants to depict a rain cloud but you don’t have one, they might use a snowball, crumble a piece of paper, or even repurpose part of another miniature to represent it. This adaptability is a valuable part of the therapeutic process and often leads to meaningful expressions of their experience.
Another concern therapists often have is that I won’t be able to interpret or understand what their sand tray depicts. This fear stems from the misconception that the therapist must analyze or decode the client’s creation. In the type of sand tray therapy I’m describing, interpretation is not your responsibility. Your role is facilitating the client’s self-expression, asking open-ended questions, and cultivating curiosity about their creation.
For instance, rather than assigning meaning to a wave figure in a tray, you might ask, “What does this piece mean to you?” or “Tell me about this part of your tray.” This approach empowers clients to articulate their insights and ensures the process remains client-centered. Trust that the meaning resides within the client’s experience and that your role is to provide a safe and supportive space for them to explore.
It’s also worth noting that different approaches to sand tray therapy, such as Jungian sand play therapy, may emphasize interpretation more. However, my teaching framework prioritizes the client’s autonomy and self-expression, removing the pressure to analyze or decode their creations. By addressing these fears and embracing the client-centered nature of this work, you can approach sand tray therapy with confidence and curiosity.
Summary
I want to reinforce that many wonderful resources are available to learn more about sand tray therapy. Depending on your specific clinical orientation, you can find books and materials tailored to integrating sand tray therapy with your preferred modality or population. These resources can help you deepen your understanding and application of this powerful therapeutic tool.
It’s also important to recognize that using metaphor and imagery in therapy doesn’t have to involve sand. Some clients may dislike the texture of sand for sensory reasons, and it’s essential to approach this work with flexibility and adaptability. Sand tray therapy should always be offered as an invitation rather than an expectation. If a client is uncomfortable with sand, alternatives such as rice can be used, or the tray can be covered, allowing the miniatures to be used without direct contact with the sand. This ensures the process remains accessible and client-centered, honoring their preferences and needs.
Ultimately, sand tray therapy provides a modality that helps clients process and access deeper aspects of their experiences—parts of their emotional world that may be difficult to reach through words alone. Attuning to each client’s specific needs and preferences is key, as this work is about meeting them where they are rather than imposing any predetermined structure or expectation.
Thank you so much for your time and attention. I think that wraps up our session for today.
Questions and Answers
Is there a standard sand tray size that is often utilized?
You can easily look up the specific standard sand tray size, which is often the size shown in the original slide with the picture from our office. This standard size is widely used because it provides a good balance—offering enough space for clients to create a meaningful scene while remaining manageable in a therapy setting.
That said, it’s important not to feel restricted to the standard size. Depending on the context, there are benefits to using smaller and larger trays. For instance, smaller trays can be useful when working with a family, allowing each family member to have their tray. This can encourage personal expression while still being part of a collective experience.
In contrast, a bigger tray can be beneficial when working with a larger group, such as a classroom of students. This allows all participants to contribute their miniatures to a shared space, promoting collaboration and highlighting group dynamics.
Ultimately, the size of the tray you use should depend on your therapeutic goals and your clients' needs. The flexibility to adapt tray sizes to the session’s context ensures that the process remains inclusive and effective.
Resources
Some resources listed in the resource sheet include books exploring the pros and cons of using different-sized sand trays. I encourage you to read those for a deeper understanding.
In response to the question about which age group feels most comfortable using this modality, I’ll share my experience. Younger children, typically up to about ten or twelve, often embrace sand tray therapy without hesitation or insecurity. To them, it naturally feels like a form of play, which is already a familiar and comfortable medium for expressing themselves.
With older children, teens, or adults, there’s sometimes a greater need for psychoeducation to build buy-in. These clients may initially feel hesitant or uncertain about the modality, perceiving it as overly playful or wondering how it could apply to their situation. Providing some brain science-based psychoeducation can help them understand how sand tray therapy facilitates deeper emotional exploration and can convey thoughts or feelings that might be difficult to articulate with words. This explanation can normalize the process and help them see the value of the work.
While I’ve successfully used sand tray therapy with clients of all ages, I’ve found that adults often benefit from a brief introduction or explanation to ensure they feel respected and understand the modality's purpose. This step is important to avoid any misconceptions that the approach is only for children or to prevent them from feeling like they’re being treated as such.
That’s everything for today. Thank you!
References
Please refer to the additional handout.
Citation
Fries, K. (2024). Introduction to sand tray therapy. Continued.com, Article 77. Available at www.continued.com/counseling
Jun 10, 2024
1 CE Credit